

Loading, please wait...
Loading, please wait...

Young children remain underrepresented in clinical inquiries and healthcare dialogues concerning illness, death, and bereavement. Historically, investigators and medical professionals assumed that children aged three to eight lacked cognitive capacities to articulate grief. Consequently, traditional adult-centric clinical interviews frequently overlooked young patients during severe family bereavement. A Danish study by Lytje and colleagues challenges these outdated assumptions through innovative methodological insights. Effective preschool bereavement communication does not force young children to speak like adults. Instead, healthcare providers must design compassionate clinical encounters that respect early developmental capacities. Furthermore, medical practitioners often experience considerable apprehension when discussing mortality with grieving children in hospital settings. When clinicians understand how early childhood grief manifests, they create supportive environments. Therefore, pediatric teams must recognize that young individuals possess unique experiential expertise regarding their personal losses. By modernizing clinical approaches, healthcare professionals can validate childhood bereavement with greater sensitivity and diagnostic accuracy. Ultimately, recognizing children as experts transforms them from passive research subjects into vital clinical partners.
Preschool-aged children perceive loss through an evolving developmental framework that differs substantially from adult bereavement. For example, children under six years of age frequently view physical death as temporary and reversible. In addition, young children often engage in magical thinking, secretly believing their angry thoughts or minor misbehaviors triggered a relative's death. Furthermore, grieving children rarely sustain prolonged, continuous sadness. Instead, they shift rapidly between intense crying spells and exuberant imaginative play within minutes. Clinicians who observe this fluctuating behavior might mistakenly label it as emotional detachment or superficial grief. However, this intermittent grieving pattern represents a normal, protective developmental defense that prevents emotional overwhelm. As children enter early primary school, their cognitive comprehension matures toward understanding biological cessation. Nevertheless, young children still struggle to translate complex internal turmoil into formal clinical vocabulary. Because linguistic abilities lag behind intense affective experience, conventional verbal inquiries often fail. Thus, pediatricians and child mental health experts must interpret behavioral expressions as primary diagnostic cues. When providers identify these developmental subtleties, they tailor clinical interventions with greater therapeutic accuracy.
The Danish researchers evaluated three innovative methodological frameworks that successfully engaged children aged three to eight years in sensitive dialogues. First, they implemented a home-based sand tray interview designed specifically for parentally bereaved children. The sand tray provided a tactile medium where children arranged miniature figures to represent complex family relationships and emotional losses. Consequently, this physical medium established safe emotional distance from distressing material while enabling rich personal expression. Second, researchers employed a laboratory timeline task to examine how children understand the progression of physical death. Children arranged concrete visual markers across chronological pathways, which allowed clinicians to track cognitive perceptions without intrusive verbal questioning. Third, investigators conducted practice-based evaluations within an established family bereavement support network. This intervention demonstrated that children participate willingly when practitioners establish predictable, comfortable clinical settings. Furthermore, these techniques permitted participants to pause, step back, or discontinue the dialogue whenever emotional distress surfaced. In contrast to rigid interrogations, these responsive strategies respected individual boundaries. Therefore, creative tactile tools facilitate profound communication without triggering overwhelming vulnerability.
Conventional clinical assessments typically treat verbal language as the sole credible source of diagnostic information. However, pediatric specialists must challenge this narrow adult-centered standard to understand young patients experiencing profound loss. The Danish study emphasizes that healthcare teams must broaden what counts as meaningful clinical data. Specifically, clinicians must treat imaginative play, physical gestures, manipulated objects, and intentional silence as vital communicative expressions. For instance, a grieving child might express inner conflict by burying a toy figure rather than answering direct verbal questions. Similarly, prolonged silence or sudden topic divergence does not signify communicative failure or defiance. Instead, quiet intervals often represent necessary cognitive pauses as young minds process complex emotional burdens. Interviewers who cultivate acute observational sensitivity can interpret these nonverbal signals with high diagnostic fidelity. In addition, when adults solicit direct guidance from children, young participants offer valuable advice regarding their emotional needs. Rather than forcing adult communicative patterns onto developing minds, clinicians must adopt adaptive methods that honor children's natural expression. Ultimately, broadening our clinical gaze illuminates previously hidden childhood experiences.
For pediatricians, child psychiatrists, and family physicians in India and globally, these insights provide actionable clinical guidance. Healthcare providers frequently encounter children grieving parental death, terminal sibling illness, or major household medical crises. Rather than relying on interrogative clinical assessments, physicians should incorporate developmental play tools into outpatient consultations. For example, maintaining drawing materials, figurines, and storytelling props in consultation rooms enables children to process distressing diagnoses naturally. In addition, clinicians must train multidisciplinary medical teams to interpret subtle behavioral cues, including sudden withdrawal or emotional regression. Medical professionals should also reassure anxious caregivers that magical thinking represents a standard developmental grief response. Moreover, pediatric practitioners must avoid confusing euphemisms such as saying a deceased parent went to sleep. Instead, clear, compassionate language paired with creative expression prevents persistent cognitive anxiety and ungrounded fears. Therefore, adopting child-centered methodologies elevates the standard of pediatric mental health care across diverse clinical practices. By listening attentively to diverse modes of communication, healthcare professionals build enduring therapeutic alliances.
Children between three and six years old typically view death as temporary and reversible rather than final. Because young minds engage in magical thinking, they frequently assume their thoughts or minor misbehaviors caused a loved one to fall ill. Consequently, they experience fluctuating emotional states, moving rapidly between normal play and acute distress. Clinicians must provide simple, concrete explanations without ambiguous euphemisms, reassuring young children that they bear no blame for family losses.
Sand trays and creative play materials provide young children with safe psychological distance from intense grief. Because young patients lack sophisticated verbal vocabulary, traditional adult-style clinical questioning often induces confusion or defensive emotional withdrawal. In contrast, tactile manipulation of figures allows children to project inner conflicts, family dynamics, and fears external to themselves. Pediatricians and mental health professionals can observe these interactions, gathering accurate diagnostic information while fully preserving the child's emotional comfort.
Healthcare providers protect ethical safety by granting young children complete control over the conversational pace. Specifically, practitioners must offer explicit visual and verbal cues allowing children to pause, change topics, or stop the encounter altogether. Conducting evaluations in familiar, comfortable settings prevents clinical intimidation. Furthermore, clinicians must work collaboratively with surviving family members. This respectful approach validates children's experiential expertise, prevents retraumatization, and ensures that sensitive clinical interviews prioritize child welfare above all else.
Disclaimer: This content is for informational and educational purposes only and should not be substituted for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Recent Danish research demonstrates that preschool bereavement communication requires creative, play-based methodologies. By reframing young children as experiential experts rather than passive subjects, clinicians and researchers can assess pediatric grief with sensitive, ethically grounded communication strategies.
Today
New PEX-NET registry data reveal that the right atrial pressure to cardiac output (RAP/CO) slope during exercise right heart catheterization is an independent predictor of long-term mortality in pulmonary hypertension, outperforming conventional resting measures.
Today

A review of the evolution of maternal and pediatric therapeutics over two decades, examining developmental pharmacokinetics, lactation pharmacology, pediatric formulations, and evidence-based guidance for clinicians managing pregnancy and childhood diseases.
Today
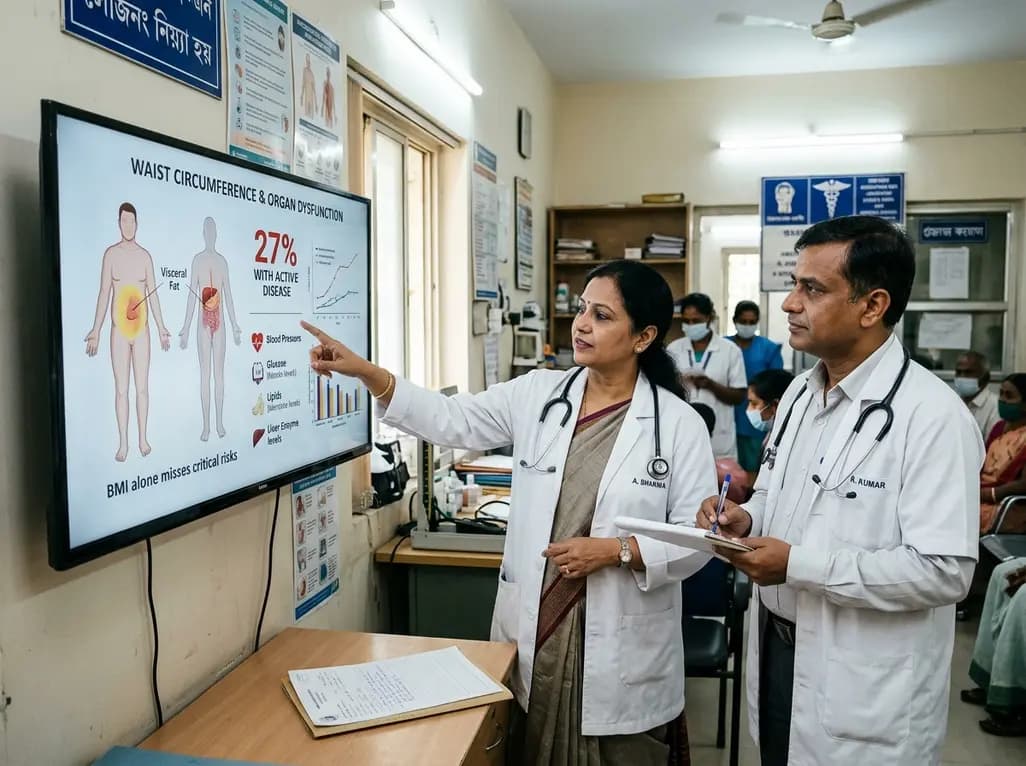
A landmark Nature study reveals that only 27% of individuals with obesity have active clinical disease. By incorporating waist circumference and organ dysfunction, this new diagnostic framework moves beyond BMI to prevent widespread misclassification and guide personalized metabolic intervention.
Today
Chronic nonbacterial osteomyelitis (CNO) is a pediatric autoinflammatory bone disorder. This review covers the French protocol, emphasizing whole-body MRI as the diagnostic gold standard, prudent biopsy avoidance, first-line NSAID treatment, and second-line biologic or bisphosphonate therapies for spinal lesions.
Today

A real-world retrospective study demonstrates that combining intravitreal ranibizumab with focal/grid macular laser significantly improves visual acuity and central macular thickness compared to laser monotherapy in patients with center-involved diabetic macular edema.
Today
