

Loading, please wait...
Loading, please wait...

Clinicians frequently utilize exercise right heart catheterization to evaluate unexplained exertional dyspnea and suspected pulmonary vascular disease. Resting hemodynamic measurements often fail to unmask early pulmonary vascular pathology. Consequently, physiological stress testing provides critical insight into cardiopulmonary reserve. When patients exercise, systemic blood flow increases to meet peripheral oxygen demands. Healthy cardiovascular systems accommodate this elevated blood flow with minimal elevation in right-sided filling pressures. However, patients with occult vascular remodeling or impaired compliance demonstrate substantial pressure increases. Historically, clinicians prioritized the mean pulmonary arterial pressure to cardiac output relationship. While that relationship identifies vascular resistance anomalies, it often overlooks right ventricular diastolic performance. Right ventricular function fundamentally dictates functional capacity and survival across various cardiopulmonary conditions. Therefore, incorporating right atrial pressure dynamics into exercise right heart catheterization protocols offers a superior diagnostic advantage. By tracking pressure changes relative to flow increments, physicians can directly quantify right ventricular chamber stiffness and compliance. Recent collaborative studies emphasize that dynamic exercise metrics significantly improve clinical risk prediction compared to static resting values alone. Thus, exercise stress testing serves as an indispensable diagnostic instrument in contemporary cardiopulmonary evaluations.
The slope linking right atrial pressure to cardiac output quantifies the change in upstream venous filling pressure per unit increase in systemic blood flow. Under physiological conditions, an increase in cardiac output recruits pulmonary capillaries and preserves low right ventricular filling pressures. As a result, healthy individuals exhibit a flat right atrial pressure to cardiac output trajectory during physical exertion. Conversely, a steep trajectory indicates impaired right ventricular diastolic compliance or inadequate volume handling. When the right ventricle becomes stiff, rising venous return rapidly drives up end-diastolic intracavitary pressures. In addition, severe tricuspid regurgitation exacerbates this abnormal steepening by transmitting systolic blood backward into the right atrium. Consequently, right atrial hypertension develops rapidly during low-level physical exertion. This hemodynamic pattern warns clinicians about early right ventricular uncoupling before overt clinical failure manifests. Furthermore, increased venous congestion directly impairs hepatic, renal, and splanchnic microvascular perfusion. Therefore, a steep slope does not simply reflect an isolated pressure spike; it signals systemic venous congestion under metabolic stress. Evaluating this dynamic relationship enables clinicians to identify precarious hemodynamic reserves that resting assessments consistently fail to detect.
The Pulmonary Hemodynamics during Exercise Network, known as PEX-NET, analyzed a robust retrospective cohort from twenty-three international centers. The investigators examined 856 patients who underwent diagnostic exercise testing for suspected or confirmed pulmonary hypertension. Among these participants, 336 individuals received a verified pulmonary hypertension diagnosis. Over a median follow-up interval of 6.5 years, 114 patients, representing 13 percent of the cohort, died. The researchers analyzed right atrial pressure to cardiac output slopes obtained using standardized patient positioning. Notably, higher slope values demonstrated an independent association with increased all-cause mortality. Specifically, multivariable Cox proportional hazard models adjusted for age, sex, and baseline hemoglobin confirmed an elevated risk of death. Each incremental unit increase in the slope conferred an eight percent higher mortality risk. Furthermore, this dynamic parameter retained its prognostic significance after adjusting for established resting hemodynamic metrics, including mean pulmonary arterial pressure. Time-dependent receiver operating characteristic curves established precise prognostic cutoff values to guide clinical decision-making. Consequently, these findings validate the right atrial pressure to cardiac output slope as an indispensable prognostic biomarker in cardiopulmonary disease.
Differentiating precapillary pulmonary hypertension from heart failure with preserved ejection fraction remains a challenging clinical endeavor. Both clinical entities can produce significant exercise intolerance and abnormal exertional pressures. However, their underlying physiological drivers and therapeutic strategies diverge substantially. Heart failure with preserved ejection fraction typically causes marked elevations in left atrial pressure, which transmit backward into pulmonary circulation. Consequently, these individuals often demonstrate steep right atrial pressure responses because central vascular stiffness and stressed blood volume increase rapidly during physical exertion. In contrast, patients with isolated precapillary vascular remodeling may preserve right ventricular compliance during the early phases of disease. Therefore, analyzing dynamic filling curves helps cardiologists distinguish primary right ventricular strain from secondary congestion caused by left-sided diastolic failure. In addition, clinicians frequently encounter patients with combined postcapillary and precapillary pathology. In these complex cases, dynamic exercise slopes reveal whether right ventricular remodeling has already developed. Recognizing these diverse phenotypic differences allows clinicians to avoid administering potentially harmful pulmonary arterial vasodilators to patients suffering primarily from left ventricular congestion.
Conducting exercise right heart catheterization requires strict methodological rigor to obtain reproducible and clinically meaningful measurements. Catheterization teams must record baseline resting measurements and exercise data in identical body positions. Supine exercise induces significant venous return augmentation compared to upright cycle ergometry. As a result, body position substantially alters intracardiac pressure dynamics and cardiac output measurements. In addition, interventionalists must ensure precise zero-level referencing before initiating the exercise protocol. Clinicians typically apply progressive workload protocols using bicycle ergometers until patients reach symptom-limited exhaustion. Furthermore, measuring pressures during consistent end-expiratory pauses prevents respiratory pressure swings from confounding right atrial measurements. Standardizing these testing protocols across clinical centers ensures that calculated slopes reflect genuine cardiopulmonary physiology rather than testing artifacts. Moreover, incorporating exercise slopes into routine clinical algorithms identifies disease progression before irreversible ventricular failure develops. Therefore, specialized referral centers should routinely integrate dynamic exercise hemodynamics into their diagnostic evaluations. Ultimately, adopting standardized physiological assessments enhances personalized therapeutic decision-making and improves long-term outcomes for patients facing complex cardiopulmonary diseases.
An elevated slope indicates impaired right ventricular compliance and inadequate volume handling during physical exertion. When cardiac output increases, a stiff right ventricle cannot accommodate increased venous return without abnormal pressure spikes. Consequently, intracavitary pressures elevate rapidly, transmitting backward into systemic veins. This abnormal hemodynamic pattern reflects subclinical right ventricular dysfunction and warns clinicians of elevated long-term mortality risk in patients undergoing cardiopulmonary diagnostic evaluations.
Resting catheterization evaluates baseline hemodynamics, which often appear deceptively normal during early disease stages. Conversely, physical exertion introduces significant metabolic stress and increases systemic venous return. Under these challenging conditions, the pulmonary circulation and right ventricle must accommodate augmented flow. Therefore, exercise testing unmasks latent vascular remodeling and diastolic stiffness that resting assessments miss, providing clinicians with crucial diagnostic clarity and superior long-term prognostic risk stratification.
Body position significantly alters cardiovascular preload and pressure dynamics. Supine exercise increases venous return to the right heart much more dramatically than upright cycling. As a result, right atrial pressures and cardiac output shift differently depending on posture. Interventional teams must therefore maintain consistent positioning between resting and exertion phases to ensure accurate slope measurements, avoid confounding artifacts, and achieve standardized clinical comparisons across multicenter patient registries.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New PEX-NET registry data reveal that the right atrial pressure to cardiac output (RAP/CO) slope during exercise right heart catheterization is an independent predictor of long-term mortality in pulmonary hypertension, outperforming conventional resting measures.
Today

A review of the evolution of maternal and pediatric therapeutics over two decades, examining developmental pharmacokinetics, lactation pharmacology, pediatric formulations, and evidence-based guidance for clinicians managing pregnancy and childhood diseases.
Today
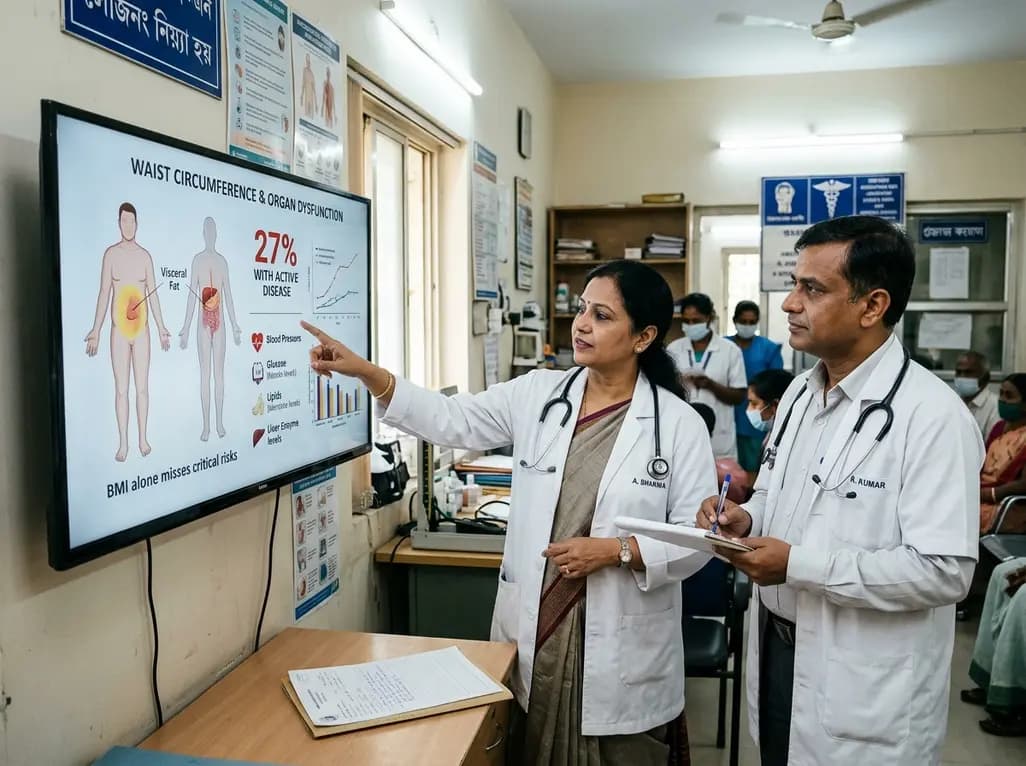
A landmark Nature study reveals that only 27% of individuals with obesity have active clinical disease. By incorporating waist circumference and organ dysfunction, this new diagnostic framework moves beyond BMI to prevent widespread misclassification and guide personalized metabolic intervention.
Today
Chronic nonbacterial osteomyelitis (CNO) is a pediatric autoinflammatory bone disorder. This review covers the French protocol, emphasizing whole-body MRI as the diagnostic gold standard, prudent biopsy avoidance, first-line NSAID treatment, and second-line biologic or bisphosphonate therapies for spinal lesions.
Today

A real-world retrospective study demonstrates that combining intravitreal ranibizumab with focal/grid macular laser significantly improves visual acuity and central macular thickness compared to laser monotherapy in patients with center-involved diabetic macular edema.
Today
