

Loading, please wait...
Loading, please wait...

Management of pediatric herpetic keratitis poses a formidable diagnostic challenge for clinicians worldwide. Herpes simplex virus causes significant ocular morbidity during childhood. However, primary ocular manifestations often escape early detection because young children cannot articulate subtle visual disturbances. Consequently, pediatric patients frequently present with advanced disease or atypical corneal involvement. While adults typically develop classic dendritic epithelial lesions, pediatric presentations frequently feature severe stromal inflammation, disciform edema, or endothelio-keratitis. Furthermore, corneal epithelial healing in children triggers intense local inflammatory cascades. This heightened immunological reactivity produces significant corneal haze and tissue remodeling. In addition, severe ocular pain, photophobia, blepharospasm, and persistent tearing routinely accompany acute episodes. Clinicians frequently misdiagnose initial presentations as routine bacterial conjunctivitis. As a result, treatment delays frequently occur, allowing the viral infection to compromise corneal transparency. Therefore, ophthalmologists and pediatricians must maintain a high index of suspicion when evaluating any child with persistent unilateral red eye. Early diagnostic confirmation prevents severe corneal scarring and protects the developing visual pathway. Prompt identification enables rapid implementation of targeted antivirals to preserve normal vision.
Recurrence represents the major clinical hazard of ocular herpetic disease. Following primary infection, the herpesvirus establishes latency within the sensory trigeminal ganglion. Viral reactivation periodically drives infectious virions back into the cornea, generating destructive relapses. Recent pediatric investigations identify several distinct clinical predictors that increase recurrence vulnerability. Specifically, children with a history of stromal keratitis face a markedly higher recurrence probability than patients with purely epithelial disease. In addition, younger age at initial presentation correlates strongly with frequent relapses throughout childhood. Bilateral corneal disease also portends an elevated risk of recurrent flare-ups. Furthermore, constitutional conditions, particularly childhood atopic disease or underlying immunodeficiency, significantly amplify reactivation frequencies. Atopic children exhibit dysregulated corneal mucosal immunity, making them unusually vulnerable to severe inflammatory episodes. Moreover, premature cessation of acute antiviral therapy often precipitates rebound inflammation. Clinicians must evaluate these risk factors during initial assessments. Identifying vulnerable children helps physicians tailor monitoring intervals and implement aggressive long-term management protocols. Stratifying patients based on clinical risk profiles ultimately averts recurrent tissue damage. Early stratification protects vulnerable eyes from progressive structural impairment.
Long-term systemic antiviral prophylaxis serves as the cornerstone of secondary prevention in recurrent disease. Although clinical trials initially verified efficacy in adults, pediatric studies confirm similar robust benefits in children. Specifically, continuous oral acyclovir suppressive therapy reduces both epithelial and stromal recurrences substantially. Physicians utilize acyclovir widely because of its established safety profile and available liquid suspension formulation. In adolescent patients, clinicians frequently prescribe oral valacyclovir because convenient once-daily or twice-daily dosing enhances compliance. Prophylactic therapy suppresses asymptomatic viral shedding, thereby preventing recurrent corneal antigen exposure. Consequently, maintaining prophylaxis for at least twelve months significantly curtails inflammatory relapses. However, physicians must calculate pediatric dosages accurately using body weight to prevent subtherapeutic exposure. Furthermore, clinicians must periodically adjust dosages as pediatric patients gain weight during prolonged treatment courses. While oral antivirals demonstrate excellent tolerability, baseline renal function and periodic complete blood counts provide safety assurance. Overall, sustained antiviral prophylaxis drastically lowers disease relapse rates, effectively stabilizing ocular surface health throughout critical developmental stages. Continuous suppression also provides a reliable therapeutic window for visual pathway rehabilitation.
The visual consequences of recurrent herpetic disease extend far beyond temporary discomfort. During early childhood, clear retinal imagery is indispensable for healthy visual system maturation. However, herpetic stromal inflammation generates persistent central corneal opacities, irregular astigmatism, and corneal neovascularization. Consequently, deprivational and refractive amblyopia develop rapidly in children experiencing repeated flare-ups. In fact, clinical studies demonstrate that over half of affected young children develop amblyopia without timely intervention. Therefore, preserving optical clarity through effective antiviral suppression remains vital. In addition to medical antiviral suppression, clinicians must initiate prompt amblyopia screening and optical correction. Refractive correction using spectacles or contact lenses counteracts secondary irregular astigmatism effectively. Furthermore, occlusion therapy of the healthy eye frequently becomes necessary to stimulate neural pathways in the amblyopic eye. Clinicians must also monitor corticosteroid usage closely because unmonitored topical steroids trigger viral proliferation, ocular hypertension, and cataracts. By preventing stromal scarring and persistent neovascularization, prophylactic therapy protects visual acuity. Early multidisciplinary care ensures that children retain functional vision and avoid lifelong sensory deprivation. Aggressive monitoring guarantees that visual development remains uninterrupted.
Successfully managing herpetic eye disease in children demands coordinated collaboration between pediatricians, general practitioners, and pediatric ophthalmologists. Once clinicians confirm keratitis, they must establish an individualized treatment regimen combining acute antiviral therapy with long-term prophylaxis. Topical ganciclovir gel or trifluridine drops resolve acute epithelial ulcerations, while systemic acyclovir controls deeper stromal inflammation. When stromal keratitis presents without epithelial breaks, physicians cautiously introduce topical corticosteroids under systemic antiviral cover. However, clinicians must taper corticosteroids slowly over several months to avert rebound inflammation. In addition, parents require clear education regarding medication adherence, warning signs, and follow-up schedules. Caregivers must report early signs of reactivation, such as photophobia, redness, or eye rubbing. Furthermore, scheduled slit-lamp examinations every three to six months enable clinicians to assess corneal clarity and monitor refractive status. If corneal scarring progresses despite optimized medical therapy, specialized interventions such as rigid scleral lenses or corneal keratoplasty may become necessary. Ultimately, structured surveillance protocols minimize recurrence rates and preserve long-term visual potential in affected pediatric patients. Coordinated management fosters excellent therapeutic compliance and superior long-term clinical outcomes.
Clinicians commonly prescribe oral acyclovir at 800 milligrams daily divided into two or three doses, or 20 to 40 milligrams per kilogram daily in young children. Alternatively, clinicians choose oral valacyclovir at 500 milligrams daily for older children. Physicians must adjust weight-based doses periodically as the child grows. Prophylactic therapy typically continues for at least twelve months to achieve significant recurrence reduction and protect visual acuity.
The most significant clinical predictor of disease recurrence is a documented history of stromal keratitis rather than isolated epithelial disease. In addition, younger age at initial presentation markedly increases the risk of repeated reactivation throughout childhood. Other prominent predisposing factors include underlying atopic disease, bilateral ocular involvement, and systemic immunosuppression. Premature cessation of acute antiviral therapy also precipitates early recurrences, highlighting the need for prolonged maintenance prophylaxis in high-risk pediatric cohorts.
Pediatric herpetic keratitis directly affects the cornea during the sensitive window of ocular neural development. Recurrent stromal inflammation creates dense corneal opacities, irregular astigmatism, and severe light distortion. Consequently, these structural disruptions deprive the developing visual cortex of clear retinal input, triggering rapid deprivational and refractive amblyopia. Furthermore, young children rarely describe subtle visual deficits. Delayed clinical recognition worsens sensory deprivation, making aggressive antiviral suppression and early optical rehabilitation essential.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Explore recurrence predictors and antiviral prophylaxis outcomes in pediatric herpetic keratitis. Learn how long-term suppressive therapy reduces relapses, prevents corneal scarring, and mitigates amblyopia risk in children.
Today
A fixed eGFR cutoff of 60 mL/min/1.73 m² across all ages risks overdiagnosing chronic kidney disease in older adults and missing early decline in younger patients. Novel percentile charts for eGFR offer an age-adapted, precision-guided paradigm for evaluating renal function from childhood through senescence.
Today
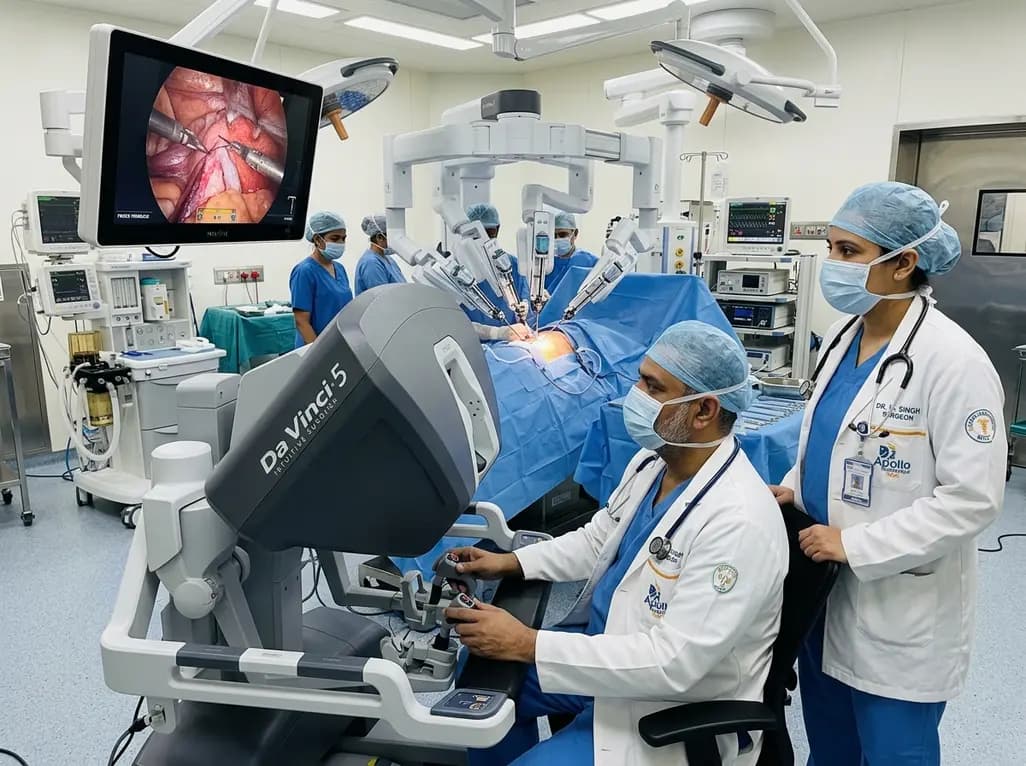
India expands its minimally invasive surgical landscape as Intuitive unveils its fifth-generation robotic platform. Equipped with real-time force feedback and immense computing performance, this innovation assists clinical specialists across urology, gynecology, and general surgery in optimizing operative care.
Today

Large-scale biobank research demonstrates that low-grade systemic inflammation quietly remodels ventricular architecture years before cardiovascular symptoms appear. Learn how emerging biomarkers like GlycA and targeted anti-inflammatory pathways could reshape preventive cardiovascular screening and clinical risk evaluation.
Today

Systematic review comparing labral repair and reconstruction in primary hip arthroscopy shows comparable short- to mid-term patient-reported outcomes, with lower THA conversion after repair but superior outcomes for reconstruction in patients aged 40 and older.
Yesterday
Diabetic peripheral neuropathy involves chronic neuroinflammation and blood-nerve barrier dysfunction. This review discusses advanced nanomedicine formulations, including nanoparticles and hydrogels, designed to overcome pharmacokinetic barriers and modulate the peripheral neuroimmune axis.
Today
