

Loading, please wait...
Loading, please wait...

Cardiovascular disease often develops surreptitiously over decades, escaping routine detection until acute clinical events manifest. Recent population-scale research indicates that chronic inflammation serves as a direct driver of subclinical myocardial remodeling, fundamentally altering myocardial structure well before outward symptoms emerge. Investigators from Imperial College London and the MRC Laboratory of Medical Sciences evaluated nearly 480,000 UK Biobank participants to decipher how continuous systemic inflammatory signaling reshapes human cardiac geometry. Consequently, the findings expose an intricate biological bridge connecting psychosocial stressors, socioeconomic disparities, and premature heart failure.
Systemic inflammatory activity exerts profound mechanical and cellular stress on the myocardium. The landmark UK Biobank investigation utilized high-resolution cardiovascular magnetic resonance imaging to capture structural nuances across thousands of individuals. Researchers observed that persistent inflammatory states correlate directly with decreased left ventricular end-diastolic volumes, concentric wall thickening, and reduced stroke volume. Therefore, the heart undergoes restrictive geometrical remodeling, forcing a compensatory increase in resting heart rate to preserve baseline cardiac output.
Moreover, sustained inflammatory signaling disrupts physiological extracellular matrix equilibrium within cardiac interstitium. When circulating inflammatory cascades persist, myocardial fibroblasts accelerate collagen deposition, causing progressive interstitial fibrosis. As a direct result, myocardial compliance declines, impairing passive diastolic ventricular filling during resting states. This stiffening process mirrors the pathophysiology seen in early heart failure with preserved ejection fraction. Thus, subclinical inflammatory damage compromises functional cardiac reserves long before patients report exercise intolerance or dyspnea.
To quantify persistent immune activation, the research team focused on glycoprotein acetyls, widely recognized as GlycA. Unlike high-sensitivity C-reactive protein, which fluctuates sharply during acute infections, GlycA reflects integrated, long-term systemic inflammatory activity through nuclear magnetic resonance spectroscopy. The metric captures composite signals from multiple circulating acute-phase glycoproteins, including alpha-1-acid glycoprotein and haptoglobin. Consequently, GlycA offers superior temporal stability for assessing subtle, smoldering vascular and systemic inflammation.
Clinical analyses revealed striking predictive associations with this metabolomic signature. Participants placed in the highest quintile of GlycA demonstrated a 43 percent greater risk of experiencing major adverse cardiovascular events, such as myocardial infarction and stroke, compared to those in the lowest quintile. Furthermore, multivariable statistical adjustments confirmed that these associations persisted independently of traditional risk markers, including low-density lipoprotein cholesterol and baseline systolic blood pressure. Therefore, GlycA provides clinicians with an objective, durable window into subclinical cardiovascular vulnerability.
The investigation uncovered compelling biological links connecting environmental adversity with physiological cardiovascular damage. Chronic psychological distress, lower socioeconomic status, and environmental challenges correlated strongly with elevated baseline inflammatory biomarkers. For decades, epidemiologists observed that socioeconomic hardship markedly increases cardiovascular mortality, but the underlying molecular mechanisms remained incompletely defined. Hence, this extensive study establishes chronic inflammation as a tangible biological mediator translating daily societal strain into measurable organ damage.
In addition, lifestyle factors compound these environmental pressures. Excess visceral adiposity, physical inactivity, and tobacco consumption amplify systemic immune activation, fostering an uninterrupted cycle of cytokine release. However, the researchers emphasized that individual genetic susceptibility significantly modulates these environmental interactions. Variations in cytokine regulatory genes render certain individuals particularly susceptible to inflammation-induced cardiac stiffness, whereas others exhibit intrinsic biological resilience. Consequently, cardiovascular prevention must account for the intimate interplay between an individual's exposome and their genetic background.
Beyond mapping gross anatomical changes, the researchers scrutinized eighty circulating inflammatory proteins to locate direct causative drivers. Intriguingly, mediation analyses demonstrated that interleukin-1 receptor antagonist accounted for approximately 27 percent of the observed association between GlycA levels and diminished left ventricular end-diastolic volume. Similarly, signaling cascades belonging to the tumor necrosis factor superfamily played critical roles in accelerating adverse myocardial geometry. Thus, specific upstream cytokine networks appear to govern subclinical ventricular restructuring.
These molecular insights carry profound implications for contemporary cardiovascular pharmacotherapy. Rather than treating heart failure only after extensive myocardial injury occurs, clinicians might soon utilize targeted anti-inflammatory agents to interrupt structural remodeling early. Many monoclonal antibodies and small molecules directed against interleukin-1 beta and tumor necrosis factor pathways are already approved for rheumatologic conditions. Therefore, repurposing these anti-inflammatory therapeutics for high-risk cardiovascular cohorts could represent a groundbreaking shift toward true disease-modifying prevention.
Integrating advanced inflammatory profiling into routine cardiovascular risk algorithms could transform primary prevention paradigms. Currently, traditional clinical scores overlook young or middle-aged adults who harbor silent vascular inflammation alongside normal cholesterol levels. By combining comprehensive inflammatory markers such as GlycA with polygenic risk scores, physicians could identify asymptomatic individuals undergoing silent ventricular remodeling. Consequently, clinicians can initiate intensive risk-reduction strategies decades before irreversible mechanical failure develops.
Nevertheless, pharmacological intervention represents only one facet of comprehensive inflammatory management. Physicians must continue emphasizing structured lifestyle modifications, including anti-inflammatory dietary patterns, smoking cessation, and consistent aerobic exercise. These non-pharmacological interventions demonstrate robust efficacy in downregulating circulating inflammatory cytokines and mitigating metabolic stress. Furthermore, addressing systemic health inequities and mental well-being remains essential to reducing cardiovascular disparities. Ultimately, recognizing inflammation as a primary cardiovascular pathogen equips practitioners to protect vulnerable patient populations far more effectively.
Q1: What is the primary difference between GlycA and hs-CRP when measuring cardiovascular inflammation?
High-sensitivity C-reactive protein is an acute-phase reactant that fluctuates rapidly during short-term infections, trauma, or minor systemic illnesses. In contrast, glycoprotein acetyls reflect the composite glycosylation status of multiple circulating acute-phase proteins. Because GlycA exhibits remarkable biological stability over months, it serves as a highly dependable biomarker for chronic systemic inflammation and long-term cardiac remodeling risk.
Q2: How does chronic inflammation cause structural changes to the heart without symptoms?
Low-grade systemic inflammation quietly stimulates cardiac fibroblasts, increases extracellular matrix cross-linking, and promotes microvascular endothelial dysfunction. Over several years, these continuous biological processes cause concentric left ventricular wall thickening and reduce chamber compliance. Because resting cardiac output is maintained through compensatory mechanisms like elevated resting heart rate, patients remain entirely asymptomatic until substantial cardiac reserve is lost.
Q3: Can lifestyle modifications reverse silent heart damage caused by chronic inflammation?
Early inflammatory remodeling is highly dynamic and substantially responsive to lifestyle intervention. Adopting an anti-inflammatory dietary pattern, engaging in regular aerobic exercise, discontinuing tobacco use, and reducing visceral adiposity significantly decrease circulating inflammatory cytokines. When individuals implement these lifestyle modifications early, they alleviate mechanical stress on myocardial tissues, attenuate progressive myocardial fibrosis, and prevent clinical heart failure.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Large-scale biobank research demonstrates that low-grade systemic inflammation quietly remodels ventricular architecture years before cardiovascular symptoms appear. Learn how emerging biomarkers like GlycA and targeted anti-inflammatory pathways could reshape preventive cardiovascular screening and clinical risk evaluation.
Today
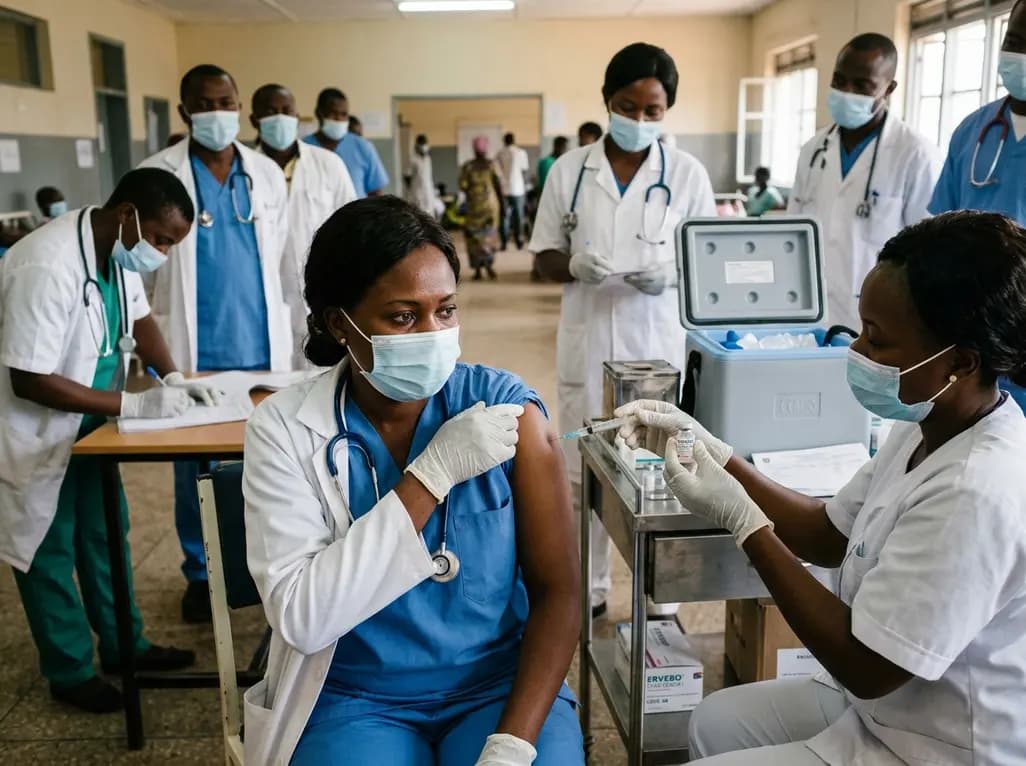
The Democratic Republic of the Congo has initiated an emergency immunisation drive for front-line health workers in Ituri province. Facing a severe Bundibugyo virus outbreak, authorities are deploying the Ervebo vaccine under compassionate use and clinical research protocols to evaluate potential cross-protection.
Today

A multi-institutional trial revealed that daily AlphaSperm supplementation induces novel epigenetic changes and regional DNA hypermethylation in sperm without improving conventional semen parameters or DNA fragmentation, urging caution regarding empirical use.
Today

Systematic review comparing labral repair and reconstruction in primary hip arthroscopy shows comparable short- to mid-term patient-reported outcomes, with lower THA conversion after repair but superior outcomes for reconstruction in patients aged 40 and older.
Today

A preclinical study reveals that alpinetin significantly alters glimepiride pharmacokinetics by inhibiting CYP2C9. This drug-herb interaction enhances hypoglycemic potency and underscores critical safety concerns regarding severe hypoglycemia in diabetic management.
Today
