

Loading, please wait...
Loading, please wait...
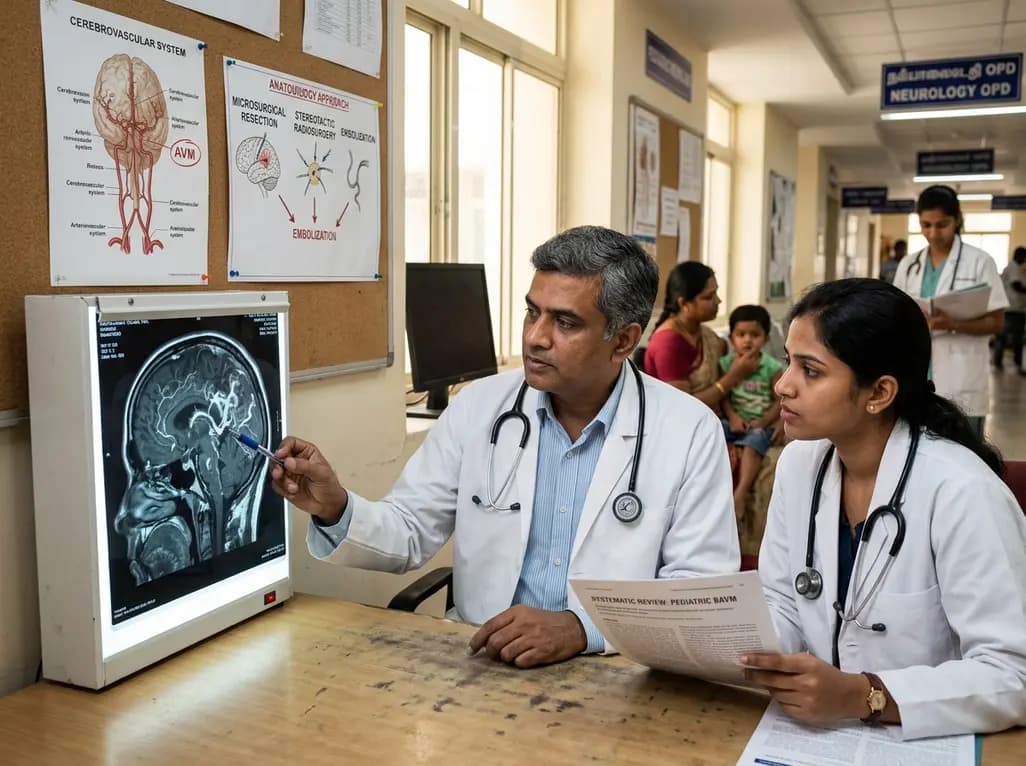
Pediatric brain arteriovenous malformations represent critical intracranial vascular lesions that constitute the leading cause of hemorrhagic stroke in the pediatric population. Although relatively uncommon compared to adult vascular disorders, a pediatric brain arteriovenous malformation carries a substantially higher lifetime cumulative risk of rupture. Consequently, clinicians face delicate decisions when balancing immediate intervention against conservative observation. A contemporary systematic review published in Neurosurgical Review evaluated 20 retrospective cohort studies comprising nearly two thousand classifiable patients. The authors systematically characterized interstudy variability, therapeutic paradigms, obliteration rates, and post-cure recurrence risks.
Unlike adult presentations where incidental discovery is increasingly frequent, children present predominantly with intracranial hemorrhage. In the reviewed cohorts, spontaneous bleeding occurred in the majority of admitted children. Furthermore, secondary presentations included intractable seizures, progressive focal neurological deficits, and severe refractory headaches. Vascular architecture and angioarchitectural grade significantly influence therapeutic decision-making. Across cohorts reporting Spetzler-Martin (SM) grading, low-grade lesions (SM I–II) comprised 44.1% of patients. Meanwhile, intermediate SM III lesions accounted for 38.4%, and high-grade complex malformations (SM IV–V) represented 17.5%.
Therefore, precise angiographic classification remains fundamental. Deep venous drainage, intranidal aneurysms, and lesion compactness critically modulate future rupture risk. Pediatric patients experience greater hemodynamic instability due to vessel immaturity. However, their enhanced neuroplasticity offers superior functional recovery potential following acute hemorrhagic events when compared to adults. As a result, prompt diagnostic evaluation with digital subtraction angiography (DSA) and magnetic resonance imaging (MRI) is essential to establish baseline anatomy and guide subsequent intervention.
Microsurgical resection remains the definitive primary treatment for accessible low-grade pediatric lesions. In the systematic review, microsurgical cohorts achieved complete obliteration rates ranging between 81% and 100%, yielding an unweighted mean obliteration rate of approximately 93%. Consequently, microsurgery provides immediate protection against re-hemorrhage by definitively eliminating the high-flow arteriovenous shunt.
Moreover, surgical intervention is particularly effective for Spetzler-Martin Grade I and II lesions located in non-eloquent cortical regions. In cases presenting with life-threatening hematoma expansion, emergent surgical evacuation combined with simultaneous nidus excision often saves lives. Nevertheless, microsurgical approaches carry inherent surgical morbidity, including postoperative ischemic injury or cranial nerve deficits. Surgeons must exercise extreme care during dissection around eloquent brain regions. Therefore, proper patient selection and intraoperative neurophysiological monitoring remain indispensable to maintaining favorable functional outcomes and minimizing long-term neurological disability.
Stereotactic radiosurgery (SRS) serves as a valuable non-invasive modality, especially for deep-seated, surgically inaccessible, or eloquent lesions. The systematic review revealed that standalone SRS achieved obliteration rates ranging from 51% to 68.5% across the largest unselected pediatric cohorts, with a wider range of 36% to 84% across all reporting series. Radiosurgery induces progressive endothelial hyperplasia and gradual vascular thrombosis over several years.
However, clinicians must account for the distinct latency period inherent to radiation-induced closure. During this two-to-three-year interval before complete nidus thrombosis, patients remain exposed to bleeding risks. The reviewed series documented latency-period hemorrhage rates between 1.1% and 3.2% per cohort. Additionally, radiation-induced changes, such as regional brain edema or radionecrosis, require close neuroimaging surveillance. Thus, radiosurgery represents an optimal option for small, compact, deep malformations where surgical morbidity outweighs the cumulative risk of latency hemorrhage.
Endovascular embolization alone rarely achieves complete obliteration in pediatric patients. Instead, interventional neuroradiologists utilize liquid embolic agents predominantly as an adjunct to facilitate subsequent microsurgery or radiosurgery. Preoperative embolization reduces high-flow shunt volume, eliminates dangerous associated aneurysms, and diminishes intraoperative blood loss.
Nevertheless, multimodal therapy requires careful calibration. Evidence indicates that partial embolization prior to radiosurgery can paradoxically decrease subsequent radiosurgical obliteration rates. Embolic materials may induce shielding artifacts or obscure nidus margins on stereotactic planning scans. Consequently, clinicians should avoid uncoordinated embolization unless targeting specific high-risk angioarchitectural weaknesses. In complex Spetzler-Martin Grade III through V lesions, multidisciplinary teams must coordinate staged embolization, targeted radiosurgery, or tailored microsurgery to maximize therapeutic synergy and minimize procedural complications.
A critical observation highlighted by contemporary literature is that pediatric patients demonstrate higher rates of lesion recurrence after angiographically confirmed cure than adults. The systematic review noted recurrence in seven cohorts, underscoring this unique pediatric phenomenon. Angiogenesis, vascular endothelial growth factor signaling, and ongoing brain development drive nidus reconstitution even after complete initial resection.
Furthermore, definitions of obliteration varied widely across retrospective cohorts, with discrepancies between catheter-based DSA confirmation and non-invasive MRI assessments. Catheter angiography remains the gold standard for verifying absolute cure. Because recurrence can occur years after initial intervention, long-term neurovascular follow-up is mandatory. Clinicians should schedule delayed surveillance DSA, typically one to three years post-treatment, and continue non-invasive imaging through physical maturity to intercept late recurrences before catastrophic re-rupture occurs.
Managing pediatric neurovascular conditions requires integrated expertise across pediatric neurosurgery, interventional neuroradiology, pediatric neurology, and radiation oncology. Because natural history studies show substantial lifelong rupture risks, observation alone carries high cumulative mortality in children. However, treatment strategies must be tailored to lesion grade, clinical presentation, and anatomical feasibility.
Low-grade accessible lesions generally warrant definitive microsurgical resection to achieve immediate cure. Conversely, deep-seated or intermediate lesions benefit from targeted stereotactic radiosurgery or multimodal intervention. Importantly, continuous standardized documentation and multicenter prospective registries will be crucial to resolve retrospective reporting heterogeneity. Standardizing definitions of angiographic obliteration and enforcing strict follow-up protocols will ensure optimal long-term functional recovery and neurological safety for affected children worldwide.
Unlike adult cases where incidental detection is frequent, intracranial hemorrhage represents the predominant presentation in children. Hemorrhagic stroke accounts for most emergency admissions, while other common symptoms include new-onset seizures, progressive focal neurological deficits, and severe headaches.
Pediatric patients possess active angiogenic potential and developing cerebral vasculature, which elevates their risk of post-obliteration recurrence compared to adults. Delayed digital subtraction angiography and longitudinal non-invasive imaging remain necessary through physical maturity to detect vascular recanalization before recurrent hemorrhage occurs.
Microsurgical resection provides immediate, high obliteration rates exceeding 90% in accessible lesions, eliminating re-bleed risks instantly. Stereotactic radiosurgery achieves 50% to 70% obliteration non-invasively for deep or eloquent lesions, but carries a latency period of two to three years with residual hemorrhage risk.
Disclaimer: This content is for informational and educational purposes only. It is not intended to substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of qualified healthcare professionals with any questions you may have regarding medical conditions. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review of 20 retrospective cohorts evaluates management strategies for pediatric brain arteriovenous malformations, comparing microsurgical resection, stereotactic radiosurgery, embolization, and long-term recurrence risks to guide multidisciplinary pediatric neurovascular care.
4 weeks back

A recent clinical report identifies a novel GDF2 frameshift mutation in a patient with hereditary hemorrhagic telangiectasia presenting with acute cerebral infarction secondary to microscopic pulmonary arteriovenous malformations, emphasizing the necessity of comprehensive screening and genetic evaluation.
Today

India experiences an exponential rise in robotic-assisted procedures, with Delhi NCR leading system installations and clinical volume. Discover how multidisciplinary surgical adoption, remote telesurgery breakthroughs, and standardized international consensus guidelines are shaping surgical care nationwide.
Today

Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A media-based study of 278 European professional football players finds no clear association between time to return-to-play after ACL reconstruction and the hazard of a first additional injury or matches missed, reinforcing the need for criteria-based clearance over calendar timelines.
Today
A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
Today
