

Loading, please wait...
Loading, please wait...
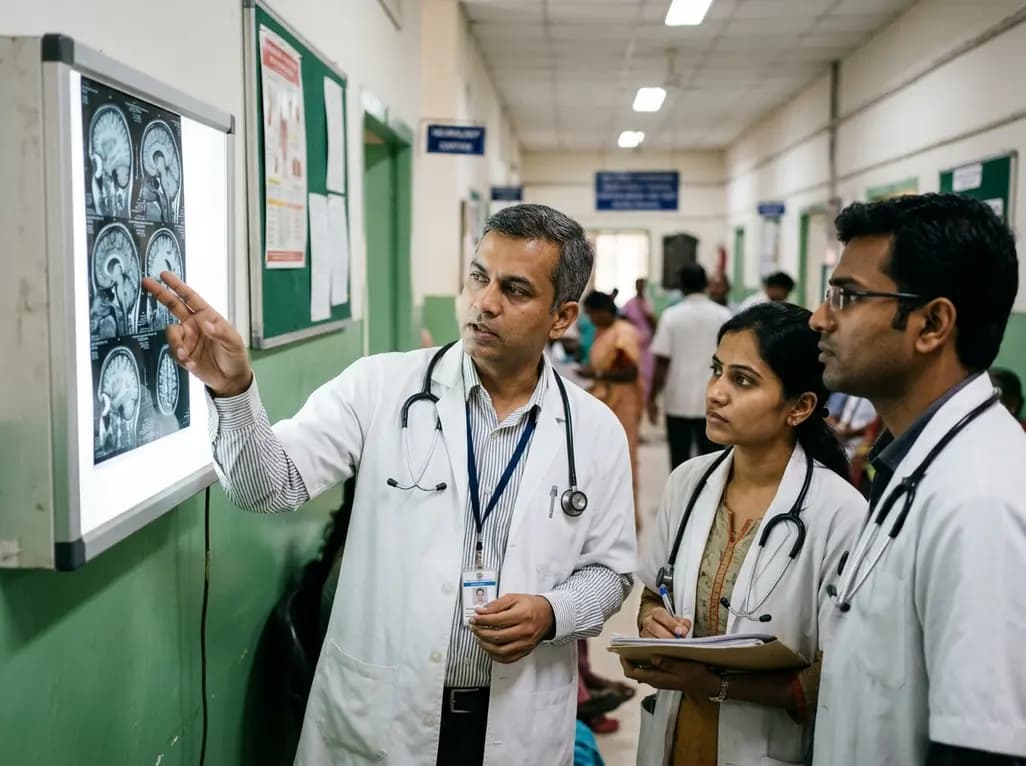
Frontotemporal lobar degeneration encompasses diverse clinical presentations characterized by profound personality, linguistic, and socioemotional disruptions. Clinicians frequently encounter severe behavioural changes in FTD across both behavioural-variant frontotemporal dementia (bvFTD) and semantic dementia (SD). Historically, clinicians assumed that distinct qualitative patterns differentiated these subtypes entirely. However, recent empirical findings challenge traditional diagnostic assumptions. Comprehensive neuropsychological and neuroimaging investigations indicate that behavioural disturbances exist along a continuous spectrum rather than manifesting as segregated categorical entities.
Frontotemporal dementia manifests with early alterations in interpersonal conduct, executive oversight, and emotional regulation. In typical clinical practice, bvFTD presents predominantly with apathy, disinhibition, loss of empathy, hyperorality, and stereotyped motor or verbal behaviours. Conversely, semantic dementia, also recognized as semantic-variant primary progressive aphasia, primarily features progressive loss of conceptual knowledge and vocabulary comprehension. Despite these primary language deficits, semantic dementia cases routinely develop prominent neuropsychiatric and personality changes over time.
Consequently, clinicians often struggle to distinguish whether these manifestations arise from shared pathological mechanisms or independent cognitive pathways. The overlap creates significant diagnostic confusion, particularly when personality changes appear early in semantic presentations. Therefore, identifying whether behavioural alterations differ qualitatively or merely quantitatively is essential for refining clinical evaluations and improving caregiver counseling. Systematic evaluations help multidisciplinary teams establish realistic care goals across all disease stages.
Recent investigations using the Cambridge Behavioural Inventory-Revised and targeted psychometric tools demonstrate a broad spectrum of neuropsychiatric disturbances across all FTD presentations. Although patients with bvFTD display quantitatively greater severity across most behavioural domains, detailed item-level analyses show no qualitative double dissociations between bvFTD and semantic dementia. In other words, patients with semantic dementia experience the same core behavioural disruptions, including apathy, dietary changes, and ritualistic habits, but often with lower initial severity.
Moreover, principal component analyses reveal three consistent behavioral dimensions across all patients: apathy, challenging behaviours, and activities of daily living impairments. These three latent constructs appear reliably across both diagnostic categories. Thus, the clinical distinction between these syndromes reflects a continuous gradient of severity rather than mutually exclusive neuropsychiatric phenotypes. Recognizing this shared phenotypic vulnerability prevents clinicians from overlooking neuropsychiatric symptoms in patients presenting predominantly with fluent language degradation.
Accurate clinical assessment in frontotemporal lobar degeneration relies heavily on collateral history from family members and caregivers. Notably, comparative analyses between patient self-reports and informant ratings demonstrate marked discrepancies in perceived functional status. Patients frequently exhibit severe loss of insight or anosognosia, leading them to underestimate their behavioural deficits significantly. In contrast, caregivers report profound functional burden and pervasive daily behavioural challenges.
Interestingly, objective neuropsychological batteries demonstrate significantly superior discriminative accuracy for separating bvFTD from semantic dementia compared to caregiver-reported behavioural scales alone. Formal cognitive measures of general semantic memory, executive function, and social cognition reliably distinguish between subtypes. Conversely, informant questionnaires often capture generalized distress and overlapping functional decline. Therefore, clinicians must combine structured informant interviews with standardized psychometric testing rather than relying solely on subjective caregiver reports to differentiate these neurodegenerative conditions.
Structural magnetic resonance imaging provides critical insights into the neural substrates driving neuropsychiatric features in frontotemporal lobar degeneration. Neuroimaging analyses reveal that severe apathy across both bvFTD and semantic dementia correlates strongly with grey matter atrophy in the anterior cingulate cortex. Furthermore, increased apathy corresponds directly with deteriorating executive control, reflecting disruption of frontostriatal and cingulate networks essential for motivated behavior.
Surprisingly, informant ratings of impaired social conduct do not correlate directly with anterior temporal lobe atrophy or degraded social-semantic knowledge. Although bilateral anterior temporal damage impairs conceptual understanding of social rules, real-world behavioural breakdowns align more closely with frontal network disruption. Consequently, executive dysfunction and cingulate degeneration represent the primary neurobiological drivers of motivational and behavioural deficits across the entire frontotemporal spectrum.
These empirical insights strongly support a transdiagnostic framework for managing frontotemporal dementia syndromes. Rather than viewing bvFTD and semantic dementia as rigid clinical silos, clinicians should evaluate patients along continuous cognitive, behavioural, and neuroanatomical dimensions. Such an approach accommodates atypical or intermediate cases that exhibit mixed linguistic and socioemotional features. Furthermore, understanding the shared pathophysiology of apathy enables more rational therapeutic exploration.
Currently, pharmacological interventions for apathy and behavioural disruption remain limited. However, targeted non-pharmacological strategies, environmental modifications, and structured caregiver support can mitigate behavioral escalation. Clinicians can better anticipate care challenges by monitoring anterior cingulate involvement and executive decline over time. Furthermore, psychoeducation regarding anosognosia helps family members comprehend that patient indifference stems from organic network degeneration rather than intentional interpersonal detachment.
Clinicians evaluating suspected frontotemporal syndromes should implement standardized diagnostic protocols that integrate objective cognitive testing with neuroimaging. High-resolution structural magnetic resonance imaging or fluorodeoxyglucose positron emission tomography can identify focal anterior cingulate, insular, and temporal lobe atrophy or hypometabolism early in the disease trajectory. Additionally, standardized caregiver-completed instruments, such as the Cambridge Behavioural Inventory-Revised, provide comprehensive baseline tracking of neuropsychiatric burden.
Ultimately, comprehensive management demands proactive multidisciplinary collaboration among neurologists, psychiatrists, geriatricians, speech therapists, and social workers. Addressing caregiver burnout is equally paramount, given the substantial emotional strain associated with profound apathy and disinhibition. Regular follow-up visits allow clinicians to titrate symptomatic medications, adapt behavioral strategies, and coordinate supportive resources as neurodegenerative changes progress over time.
No, research demonstrates that behavioural symptoms do not differ qualitatively between bvFTD and semantic dementia. Both patient cohorts experience identical types of neuropsychiatric disturbances, including apathy, dietary changes, and disinhibition. However, patients with bvFTD typically demonstrate greater overall severity on standardized behavioural rating scales across the disease course.
Apathy across frontotemporal dementia subtypes correlates primarily with grey matter atrophy in the anterior cingulate cortex and associated executive dysfunction. Degeneration within these frontal circuits disrupts goal-directed behavior, motivation, and initiation, whereas anterior temporal lobe atrophy does not demonstrate an independent direct correlation with caregiver-reported apathy scores.
Objective neuropsychological testing reliably captures specific cognitive dissociations, such as semantic memory degradation versus executive dysfunction, which clearly distinguish bvFTD from semantic dementia. Informant behavioural questionnaires reflect generalized neuropsychiatric burden and caregiver distress, resulting in substantial clinical overlap that reduces their diagnostic discriminative accuracy when used alone.
Disclaimer: This content is for informational and educational purposes only and is not intended as medical advice, diagnosis, or treatment. It does not replace professional clinical judgement, local medical protocols, or established clinical pathways. The interpretations and clinical management discussions reflect current scientific literature and expert consensus but may not apply to every individual clinical scenario. Healthcare professionals must exercise independent clinical discretion when evaluating individual patient presentations. Refer to the latest local and national guidelines for clinical practice.
References
1. Rouse MA, Husain M, Garrard P, Patterson K, Rowe JB, Lambon Ralph MA. Behavioural changes in frontotemporal dementia and their cognitive and neuroanatomical correlates. Brain. 2025 Aug 01;148(8):2730-2745. doi: 10.1093/brain/awaf061. PMID: 39938002.
2. Rascovsky K, Hodges JR, Knopman D, Mendez MF, Kramer JH, Neuhaus J, et al. Sensitivity of revised diagnostic criteria for the behavioural variant of frontotemporal dementia. Brain. 2011 Sep;134(Pt 9):2456-2477. doi: 10.1093/brain/awr179.
3. Gorno-Tempini ML, Hillis AE, Weintraub S, Kertesz A, Mendez M, Cappa SF, et al. Classification of primary progressive aphasia and its variants. Neurology. 2011 Mar 15;76(11):1006-1014. doi: 10.1212/WNL.0b013e31821103e6.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark study in Brain examines behavioural changes across frontotemporal dementia subtypes, showing that bvFTD and semantic dementia share qualitative behavioral features differing primarily in severity, with apathy mapped to anterior cingulate atrophy and executive decline.
last month

A bioengineered oral nanozyme microsupplement converts pathological ROS into a protective polydopamine hydrogel shield. By curbing neutrophil extracellular traps and balancing T cells, this platform outperforms standard 5-ASA in preclinical colitis models, opening new paths for sustained remission.
Today

India experiences an exponential rise in robotic-assisted procedures, with Delhi NCR leading system installations and clinical volume. Discover how multidisciplinary surgical adoption, remote telesurgery breakthroughs, and standardized international consensus guidelines are shaping surgical care nationwide.
Today

Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today
A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today
A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
Yesterday
