

Loading, please wait...
Loading, please wait...

Anterior cruciate ligament reconstruction remains a primary intervention for restoring athletic knee stability. In India and worldwide, surgeons frequently utilize hamstring tendon autografts. However, objective assessment during postoperative rehabilitation remains challenging. Orthopedic clinicians and physiotherapists rely on knee flexion strength tests to monitor recovery and determine return-to-sport clearance. Traditionally, practitioners use the limb symmetry index to gauge bilateral symmetry. Yet, new evidence reveals that symmetry values vary significantly across different testing modalities, warning clinicians against relying on a single test.
Clinicians often expect hamstring recovery to progress uniformly across distinct muscle actions. However, biomechanical requirements vary substantially between concentric shortening, eccentric deceleration, and static contractions. When sports physicians evaluate athletes four months or more following reconstruction, deficits remain distinctly task-specific. Harvesting the semitendinosus tendon alters muscle architecture and decreases active torque generation. Therefore, knee flexor capacity varies across dynamic joint angles. Furthermore, compensatory recruitment from neighboring synergists masks underlying flexor weakness during certain maneuvers. Specifically, the gastrocnemius provides substantial knee flexion assistance when the ankle remains dorsiflexed. Conversely, plantar flexion slackens the gastrocnemius, isolating the semitendinosus and biceps femoris. Thus, test configuration directly influences calculated symmetry outcomes. When clinicians fail to recognize these differences, they risk making flawed clearance decisions. Sports medicine specialists must appreciate that each strength assessment engages distinct neuromusculoskeletal pathways. Consequently, relying on an isolated protocol provides a misleading impression of true athletic recovery and joint readiness. Clinicians who recognize this variability can design more comprehensive evaluation frameworks.
The study evaluated four distinct functional assessments in patients recovering from autograft surgery. First, researchers performed seated isokinetic concentric dynamometry to measure torque output across a predefined arc. While isokinetic dynamometry provides precise data, equipment expenses restrict its routine use in many Indian clinics. Second, authors evaluated eccentric strength during the Nordic hamstring exercise with a dedicated force board. This assessment measures bilateral eccentric braking force, reflecting high-speed sprint deceleration demands. Third, investigators tested prone isometric knee flexion at ninety degrees with the ankle dorsiflexed. This setup allows accessible evaluation but permits significant gastrocnemius assistance. Fourth, the protocol tested prone isometric flexion at ninety degrees with active plantar flexion. By minimizing gastrocnemius contribution, this variation isolates the deep hamstring units. Notably, patient performance diverged sharply across all four modalities. Athletes showing excellent symmetry during concentric isokinetic testing often demonstrated substantial deficits during eccentric Nordic testing. Similarly, isometric values shifted significantly based solely on ankle positioning. These observations highlight the danger of assuming equivalence between different testing modalities in post-surgical patient populations.
Sports physicians generally mandate a limb symmetry index of ninety percent before clearing athletes for competitive play. However, research proves that the proportion of patients achieving this threshold varies significantly between modalities. When investigators applied McNemar's test, passing rates differed markedly across tests. An athlete might achieve ninety-two percent symmetry on isokinetic testing, yet reach only seventy-five percent on the Nordic hamstring exercise. Consequently, clinicians using a single modality risk granting premature clearance to vulnerable patients. This erroneous clearance carries grave consequences, because residual flexor weakness increases secondary graft failure risk. Furthermore, inadequate hamstring torque impairs joint stability, alters landing mechanics, and elevates patellofemoral stress. In multidirectional sports, eccentric hamstring control protects the reconstructed graft from anterior tibial translation during sudden deceleration. Therefore, medical teams must interpret limb symmetry index values with caution. A high score on one testing device does not ensure comprehensive functional restoration across all athletic demands. Therefore, relying on a single test score creates substantial clinical risk and may precipitate catastrophic reinjury in returning competitors.
Graft selection profoundly influences long-term strength recovery patterns. The investigators compared patients who received hamstring tendon autografts against cohorts receiving patellar tendon or quadriceps tendon autografts. Utilizing independent-samples testing and Fisher's exact test, researchers observed significant differences in flexor symmetry profiles. Patients with extensor-mechanism autografts achieved superior knee flexor symmetry across every testing modality. This contrast occurs because harvesting the semitendinosus causes persistent donor-site morbidity within the medial hamstrings. Conversely, bone-patellar tendon-bone and quadriceps autografts spare posterior muscle structures entirely, although they create extensor deficits instead. For Indian orthopedic surgeons, who frequently recommend hamstring autografts to minimize donor-site anterior knee pain, these results provide critical guidance. Surgeons must anticipate persistent flexor deficits and guide targeted postoperative conditioning. Furthermore, rehabilitation programs must prioritize progressive posterior chain loading rather than focusing solely on quadriceps rebuilding. When teams address donor-site deficits systematically, they optimize functional recovery and prevent reinjury. Ultimately, understanding these anatomical nuances allows orthopedic surgeons to set realistic recovery milestones and counsel patients effectively.
Given the substantial variability across strength tests, sports medicine centers should abandon isolated test evaluations. Instead, physical therapists and surgeons should deploy a comprehensive testing battery. First, clinicians should combine concentric and eccentric assessments to capture distinct contraction dynamics. While isokinetic dynamometry evaluates continuous torque, eccentric Nordic testing identifies lingering deceleration deficits. Second, when advanced dynamometers are unavailable, practitioners can utilize standardized isometric testing with hand-held dynamometers. However, therapists must carefully control ankle positioning during prone testing. Testing both dorsiflexion and plantar flexion clarifies whether calf musculature is masking hamstring deficits. Furthermore, practitioners must remember that symmetry indices evaluate relative balance rather than absolute capacity. If an athlete experiences deconditioning in the uninjured limb, the symmetry index artificially appears normal. Therefore, teams should compare postoperative metrics against pre-injury baselines or established normative standards. Finally, clinicians must integrate objective strength metrics with psychological readiness assessments and movement quality evaluations before granting sports clearance. This holistic methodology safeguards athletes against premature discharge and establishes a standardized benchmark for modern rehabilitation clinics.
Ankle position significantly changes knee flexion strength because the gastrocnemius muscle crosses both the ankle and knee joints. When an athlete dorsiflexes the ankle, the gastrocnemius stretches and generates substantial compensatory knee flexion force. Conversely, active plantar flexion slackens the gastrocnemius, which isolates the hamstring muscles. Therefore, testing knee flexion in plantar flexion unmasks genuine donor-site hamstring deficits that dorsiflexion routinely conceals during clinical examinations.
Most orthopedic rehabilitation protocols demand a limb symmetry index of at least ninety percent before granting athletic clearance. However, clinicians should not view ninety percent on a single isolated test as definitive proof of readiness. Because different contraction modalities yield divergent symmetry scores, clinicians must require ninety percent symmetry across multiple assessments, including eccentric and isometric evaluations, while simultaneously confirming that absolute muscle strength meets pre-injury normative standards.
Physical therapists should not discard isokinetic dynamometry, but rather integrate the Nordic hamstring exercise alongside it. Isokinetic dynamometry accurately assesses concentric torque across the entire knee range of motion, providing critical diagnostic data. Meanwhile, the Nordic hamstring exercise specifically interrogates high-load eccentric capacity, which is essential for injury prevention during sprinting. Utilizing both tools concurrently ensures a complete evaluation of flexor strength profiles in high-performing athletes.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today

A recent clinical report identifies a novel GDF2 frameshift mutation in a patient with hereditary hemorrhagic telangiectasia presenting with acute cerebral infarction secondary to microscopic pulmonary arteriovenous malformations, emphasizing the necessity of comprehensive screening and genetic evaluation.
Today

India experiences an exponential rise in robotic-assisted procedures, with Delhi NCR leading system installations and clinical volume. Discover how multidisciplinary surgical adoption, remote telesurgery breakthroughs, and standardized international consensus guidelines are shaping surgical care nationwide.
Today
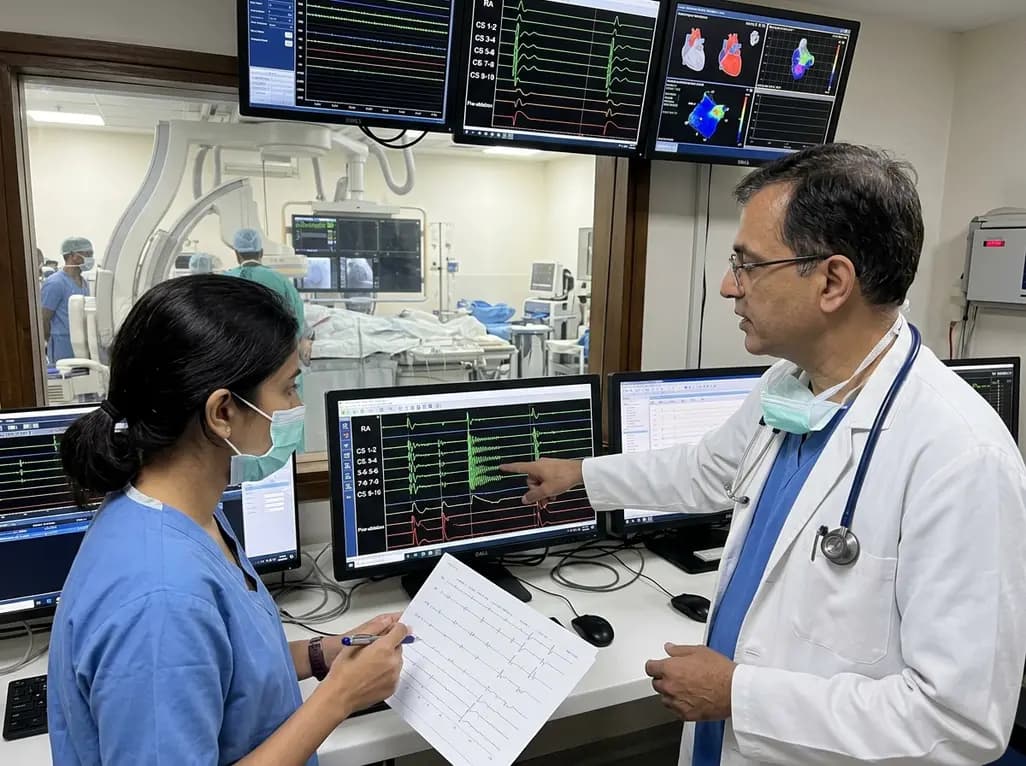
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
Today
