

Loading, please wait...
Loading, please wait...

The Food Safety and Standards Authority of India (FSSAI) has published a pivotal draft amendment targeting infant nutrition products. Specifically, the regulator proposes prohibiting the addition of sucrose and fructose in foods intended for infants up to six months of age. This public health intervention directly reinforces optimal infant feeding practices across India. Furthermore, it addresses growing clinical concerns regarding early metabolic programming and childhood obesity.
The draft Food Safety and Standards (Foods for Infant Nutrition) Amendment Regulations, 2026, marks a decisive turning point in commercial infant nutrition. Under the existing 2020 regulatory framework, lactose and glucose polymers serve as the primary and preferred carbohydrate sources. Previously, manufacturers could incorporate sucrose or fructose within specified limits when carbohydrate additions were deemed necessary. However, the new draft amendment explicitly removes this allowance for formulations catering to babies under six months. Consequently, manufacturers must reformulate any baby food products that currently utilize these simple sugars. The Union Ministry of Health and Family Welfare emphasizes that this transition safeguards infants during a foundational stage of metabolic development. In addition, the draft notification initiates a sixty-day public consultation window for stakeholders, clinicians, and researchers to provide feedback. Thus, regulatory authorities are proactively prioritizing preventive healthcare over convenience in manufacturing. By eliminating non-essential sweeteners from commercial feeds, the government aligns Indian standards with international benchmarks. Moreover, this mandate urges the baby food industry to respect biological physiology rather than commercial marketing trends.
Introducing refined sugars during the earliest months of life alters physiological development and long-term health trajectories. Human breast milk provides lactose, which delivers balanced glucose and galactose for rapid neural and somatic growth. In contrast, added sucrose and fructose provide high caloric density without contributing superior micronutrient value. Therefore, early exposure to sweet taste profiles significantly distorts nascent taste preferences. Infants naturally exhibit an innate affinity for sweetness, but artificial reinforcement solidifies a persistent craving for sugary items. Consequently, children accustomed to heavily sweetened formulas resist accepting nutrient-rich, unsweetened complementary foods later in infancy. Furthermore, pediatric researchers associate excessive early sugar consumption with rapid weight acceleration during critical infancy windows. As a result, infants face elevated risks of early adiposity rebound and metabolic dysfunction later in childhood. In addition, frequent sugar exposure directly compromises erupting deciduous teeth by promoting microbial colonization and acid demineralization. Pediatricians recognize that preventing these issues requires stringent dietary controls from day one. Hence, removing unnecessary caloric sweeteners forms the bedrock of long-term cardiovascular and metabolic risk reduction.
The immature gastrointestinal tract and liver of an infant require specific, easily metabolizable nutrients. Naturally, an infant possesses high levels of intestinal lactase to cleave milk lactose efficiently into usable monosaccharides. Conversely, infants develop sucrase and fructose transport mechanisms, like GLUT5, more gradually over time. When manufacturers add high concentrations of fructose or sucrose, an infant's digestive capacity can quickly become overwhelmed. As a result, unabsorbed sugars travel into the colon, causing osmotic water shifts, abdominal distension, and painful colic. Moreover, excessive fructose absorption demands rapid hepatic phosphorylation through the fructokinase pathway. Consequently, unregulated hepatic uptake of fructose promotes de novo lipogenesis even in young pediatric populations. This early lipid accumulation places metabolic stress on immature hepatocytes. In addition, high sugar loads induce dysbiosis within the neonatal gut microbiome by favoring opportunistic bacterial overgrowth. Healthy bifidobacteria thrive best on human milk oligosaccharides and natural lactose rather than refined disaccharides. Therefore, restricting added sweeteners directly shields vulnerable organ systems from unintended metabolic derangements during crucial developmental windows.
Public health institutions worldwide unanimously advocate exclusive breastfeeding for the first six months of human life. The World Health Organization clearly asserts that breast milk alone meets all normal nutritional needs during this window. Similarly, national health authorities advise against early complementary feeding before completion of six completed months. Introducing commercial foods sweetened with sucrose or fructose directly undermines this global nutritional objective. Furthermore, sweetened breast milk substitutes frequently displace mothers' own milk, accelerating premature weaning in vulnerable populations. Consequently, infants lose the immune protection, bioactive enzymes, and growth factors naturally present in breast milk. In addition, global pediatric societies recommend against any added sugars in foods for children under two years of age. By barring sucrose and fructose, FSSAI firmly reinforces these evidence-based pediatric nutrition standards. This regulatory action harmonizes domestic legal frameworks with recommendations from global health agencies. Meanwhile, it sends an unambiguous message to parents and clinicians that infants require wholesome, unadulterated nourishment. Therefore, India establishes a robust defense against aggressive commercial infant feeding promotion.
Healthcare professionals play an indispensable role in translating food regulations into daily patient management. In clinical consultations, pediatricians must proactively educate mothers about the perils of hidden added sugars. Often, parents assume that packaged infant cereals or commercial preparations are inherently balanced and medically sanctioned. Therefore, physicians should teach parents to scrutinize nutritional labels and identify disguised carbohydrate additives. Specifically, doctors must explain why exclusive breastfeeding remains the gold standard of early infant care. When formula supplementation proves medically unavoidable, practitioners should recommend compliant formulas containing lactose as their primary carbohydrate. Moreover, doctors should guide families through the upcoming complementary feeding phase starting at six months. During this transitional milestone, clinicians must advise caregivers to avoid adding table sugar, honey, or artificial syrups to homemade weaning preparations. Consequently, infants develop a diverse palate that embraces bitter, savory, and mildly sweet natural flavors. By advocating for clean nutrition in clinical encounters, doctors actively curb the ongoing pediatric obesity epidemic. Hence, clinical guidance and robust statutory policy together achieve meaningful health improvements.
Q1: Why is FSSAI proposing a ban on sucrose and fructose in infant food?
The regulatory authority proposes this restriction to prevent unnecessary early exposure to added sugars among infants up to six months old. During this period, infants require pure nutrition that supports optimal metabolic programming. Adding sucrose and fructose elevates the risk of childhood obesity, promotes tooth decay, and instills unhealthy sweet taste preferences. Therefore, eliminating these added sugars protects lifelong pediatric metabolic health.
Q2: What carbohydrate sources will manufacturers use in infant foods under the new rules?
Under existing regulations and proposed amendments, lactose and glucose polymers remain the preferred carbohydrate sources for infant formulations. Lactose mimics the natural sugar profile found in human breast milk and provides vital galactose for central nervous system development. Consequently, infant formulas will continue to deliver necessary energy without relying on artificial sweeteners, table sugar, or concentrated fructose.
Q3: How does this regulatory draft affect current breastfeeding recommendations in India?
This regulatory amendment strongly supports national and international health recommendations advocating exclusive breastfeeding for the first six months of life. By removing hyper-palatable sweetened baby foods from store shelves, the draft reduces the commercial temptation to introduce early supplementary foods prematurely. Furthermore, it encourages healthcare providers to champion maternal lactation and evidence-based complementary feeding practices after six months.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The Food Safety and Standards Authority of India has issued draft regulations prohibiting added sucrose and fructose in baby food formulas for infants under six months. This regulatory move seeks to protect metabolic health, reduce future non-communicable disease risks, and reinforce exclusive breastfeeding practices.
Today
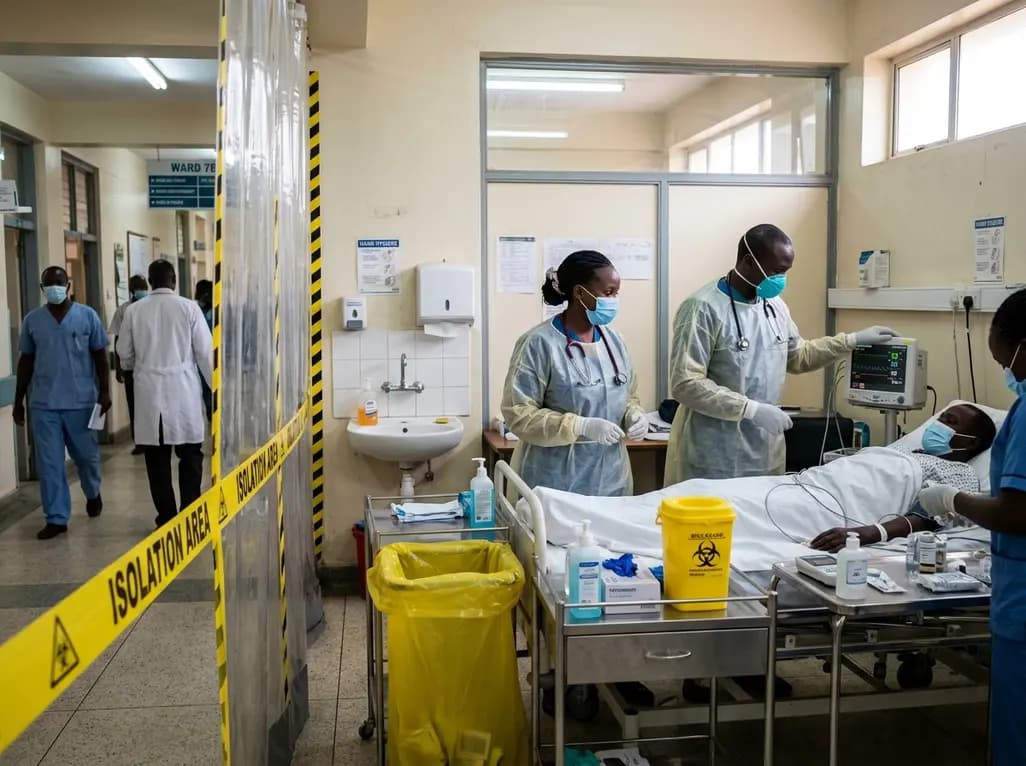
Kenya's confirmation of its eighth Ebola infection highlights the acute risk of secondary transmission in hospital environments. Clinicians must maintain high vigilance, enforce strict infection prevention protocols, and implement rapid triage mechanisms for viral hemorrhagic fevers across healthcare settings.
Today
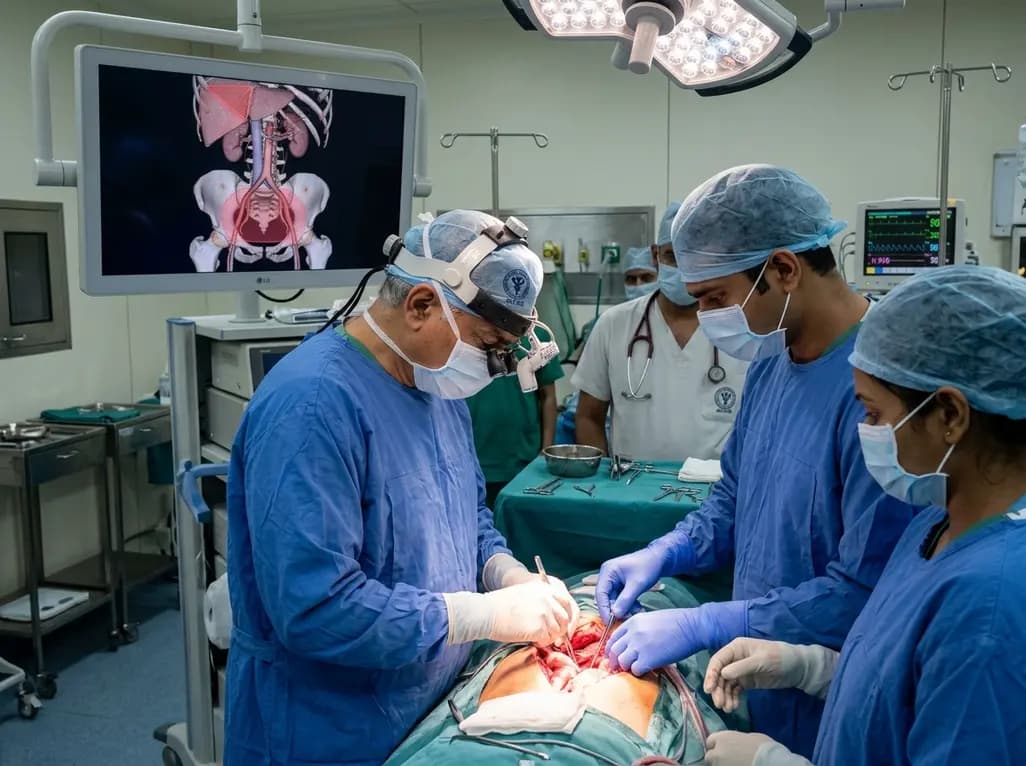
Surgical oncologists at AIIMS Delhi have mapped two critical anatomical landmarks: Ray's Zone in the deep pelvis and Ray's Hepatocaval Triangle near the liver. These predefined hazard boundaries guide dissection, dramatically reduce severe intraoperative bleeding, and preserve vital nerves and visceral organs.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Today

A novel sacrificial-template technique combines FDM polymer 3D printing and micro-arc oxidation to fabricate orientation-controlled porous titanium scaffolds. These bioactive constructs offer tailored stiffness, exceptional multidirectional load resistance, and robust osseointegration for bone defect repair.
Today

A novel label-free electrochemical biosensor utilizing magnetic nanocomposites enables ultrasensitive TERT C228T mutation detection (LOD: 0.67 pM) for rapid risk stratification in papillary thyroid cancer, offering promising point-of-care utility for endocrine oncology.
Today
