

Loading, please wait...
Loading, please wait...
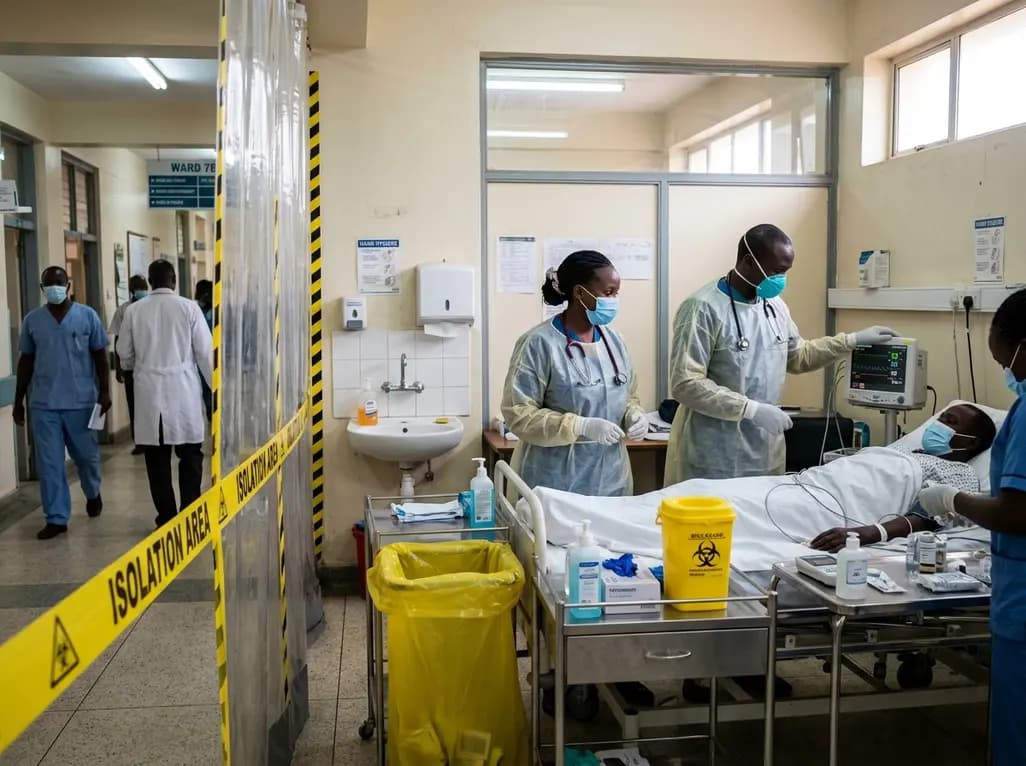
Kenya has recently confirmed its eighth case of filoviral infection, spotlighting critical vulnerabilities in cross-border surveillance and clinical infection control. Health authorities identified the new patient as a hospital attendant who handled contaminated linens and utensils. Consequently, this transmission underscores how Ebola virus disease can spread rapidly beyond initial imported presentations. Clinicians across high-traffic healthcare hubs must remain acutely alert to early clinical warning signs. Therefore, recognizing epidemiological links and hospital transmission pathways is essential to prevent secondary institutional clusters. Immediate isolation and robust contact tracing remain the primary defense against wider community dispersion.
The current cluster in Kenya originated after an index traveler journeyed from the Democratic Republic of Congo and succumbed to the illness in Nairobi. In response, public health teams initiated rigorous contact tracing and placed dozens of suspected contacts into monitored quarantine. Simultaneously, health authorities in the Democratic Republic of Congo reported that the ongoing outbreak reached an eighth province, North Ubangi. Consequently, this geographic expansion highlights the constant threat of cross-border filovirus transmission in interconnected regions.
International mobility facilitates the rapid transit of infected individuals during the asymptomatic incubation phase. Because travelers frequently present to acute medical centers only after symptoms manifest, clinicians must maintain high diagnostic suspicion. Furthermore, regional transport corridors link endemic zones with urban tertiary centers in neighboring countries. Therefore, emergency departments must systematically record complete travel histories for all febrile individuals presenting with unexplained constitutional symptoms. In addition, health systems must establish real-time reporting channels with national disease surveillance authorities. Collaborative regional monitoring and shared epidemiological data enable hospitals to anticipate imported cases. By understanding regional outbreak dynamics, front-line healthcare workers can act decisively before secondary infections take root in vulnerable clinical environments.
Nosocomial transmission represents one of the most perilous amplification mechanisms during any filovirus outbreak. In this recent Kenyan case, infection occurred in a patient attendant tasked with cleaning contaminated hospital utensils and linens. Therefore, support personnel who manage medical waste and environmental sanitization face substantial biological hazards. Filoviruses exhibit extreme virulence, meaning that microscopic inoculations through breached mucous membranes or broken skin can trigger severe disease.
Unfortunately, routine infection control measures frequently overlook auxiliary hospital workers, including housekeeping, transport, and laundry teams. Although physicians and nurses often receive priority access to high-level personal protective equipment, environmental service staff handle heavily soiled materials. Consequently, linen management protocols require dedicated isolation handling, impermeable containment bags, and validated decontamination processes. Furthermore, chlorine-based disinfectants or standardized virucidal agents must be applied diligently to all patient contact surfaces. Healthcare facilities must also institute supervised donning and doffing monitoring stations to prevent self-contamination. When support workers lack comprehensive biosecurity training, hospitals inadvertently become focal points for explosive viral spread. Therefore, institutional preparedness plans must treat every member of the patient-care ecosystem as a critical infection control stakeholder.
Ebola typically begins with non-specific, flu-like symptoms that closely mimic endemic infections such as malaria, typhoid, or dengue fever. The newly confirmed Kenyan patient developed fever, intense headache, and generalized myalgia after exposure to the index case. Because early clinical features lack pathognomonic characteristics, healthcare providers often misattribute initial presentations to common community-acquired pathogens. However, the incubation period ranges from two to twenty-one days, providing a vital window for early quarantine.
As viral replication accelerates, patients frequently develop severe gastrointestinal manifestations, including profuse watery diarrhea and persistent vomiting. These symptoms lead to profound fluid loss, severe electrolyte derangements, and hypovolemic shock. Later stages may involve coagulopathies, petechiae, mucosal bleeding, and multisystem organ failure. Therefore, clinicians must utilize reverse transcription-polymerase chain reaction testing for definitive confirmation during active viremia. In addition, rapid triage systems must immediately isolate any febrile contact displaying compatible symptoms. Health facilities should never postpone isolation while awaiting confirmatory laboratory results. Instead, clinicians must institute empiric supportive care, replace ongoing fluid deficits, and maintain strict barrier precautions. Timely clinical intervention significantly lowers case fatality rates while halting subsequent healthcare-associated transmissions.
Preventing institutional transmission demands unwavering adherence to standardized infection prevention and control bundles. First, healthcare facilities must establish a single-entry triage protocol that screens every arriving patient for fever and travel history. When a patient meets suspect case criteria, clinical teams must immediately relocate them to a dedicated negative-pressure isolation room. Furthermore, clinicians must implement strict contact and droplet precautions, avoiding aerosol-generating procedures whenever possible.
Personal protective equipment must include full-body fluid-resistant coveralls, double gloving, fluid-impermeable boots, and complete facial protection with respirators and face shields. Moreover, trained observers must oversee every personal protective equipment removal sequence, because self-contamination occurs most frequently during doffing. In addition to personal barrier protection, environmental decontamination requires meticulous execution. Hospital waste, contaminated linens, and body fluid spills necessitate prompt neutralization with appropriate sodium hypochlorite solutions. Furthermore, dedicated medical equipment must remain within the isolation perimeter to eliminate fomite transfer to clean wards. Healthcare centers should also conduct scheduled simulation drills to reinforce compliance with emergency isolation workflows. By combining strict administrative oversight with physical barriers, hospitals can safeguard both clinical personnel and non-clinical support staff from life-threatening exposures.
Although the current outbreak remains localized to East and Central Africa, globalized travel creates real vulnerabilities for international transit hubs. In India, major metropolitan hospitals regularly care for international travelers, business personnel, and returning diaspora from African nations. Therefore, Indian medical facilities must ensure that emergency departments retain operational preparedness for viral hemorrhagic fevers. Clinicians should maintain heightened vigilance for travelers returning from endemic areas within the preceding three weeks.
Furthermore, Indian hospitals frequently manage complex viral illnesses, including Crimean-Congo hemorrhagic fever and Kyasanur Forest disease. Consequently, reinforcing foundational infection control systems provides broad protective benefits across multiple pathogen categories. State health departments and tertiary centers must establish designated isolation units and maintain rapid referral pathways to reference testing laboratories. Moreover, routine training modules must educate nurses, junior doctors, and sanitary staff regarding viral hemorrhagic fever protocols. Effective public health coordination between airport screening authorities and acute care centers ensures rapid case containment. Ultimately, international outbreaks serve as urgent reminders that hospital infection control standards must remain resilient against emerging biological threats across all healthcare settings.
Q1: How does Ebola virus disease transmit within hospital environments?
Transmission within healthcare facilities occurs primarily through direct contact with infected blood, secretions, or bodily fluids such as vomitus, feces, and sweat. In addition, indirect exposure via contaminated fomites, including medical instruments, soiled linens, and bed rails, poses significant risk. Support staff who handle patient laundry or waste without adequate protective ensembles face severe exposure dangers, making rigorous adherence to personal protective equipment protocols and environmental disinfection mandatory.
Q2: What initial symptoms warrant immediate isolation in suspected patients?
Clinicians must immediately isolate individuals presenting with sudden onset of fever, intense headache, generalized myalgia, fatigue, and sore throat if an epidemiological link exists. As the infection progresses, patients typically develop severe watery diarrhea, recurrent vomiting, and abdominal pain. Because early symptoms mirror malaria or typhoid fever, a travel history to an outbreak region within the past twenty-one days remains the decisive diagnostic screening trigger.
Q3: What core infection control measures protect non-clinical hospital workers?
Protecting hospital attendants, cleaners, and laundry personnel requires comprehensive training on biohazard management and supervised equipment use. Institutions must supply fluid-resistant coveralls, heavy-duty gloves, protective eye gear, and impermeable footwear. Furthermore, contaminated linens and waste must undergo secure containment in labeled biohazard bags and immediate chemical disinfection. Routine surveillance and monitored quarantine of exposed workers ensure early detection if an accidental exposure breach occurs.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Kenya's confirmation of its eighth Ebola infection highlights the acute risk of secondary transmission in hospital environments. Clinicians must maintain high vigilance, enforce strict infection prevention protocols, and implement rapid triage mechanisms for viral hemorrhagic fevers across healthcare settings.
Today
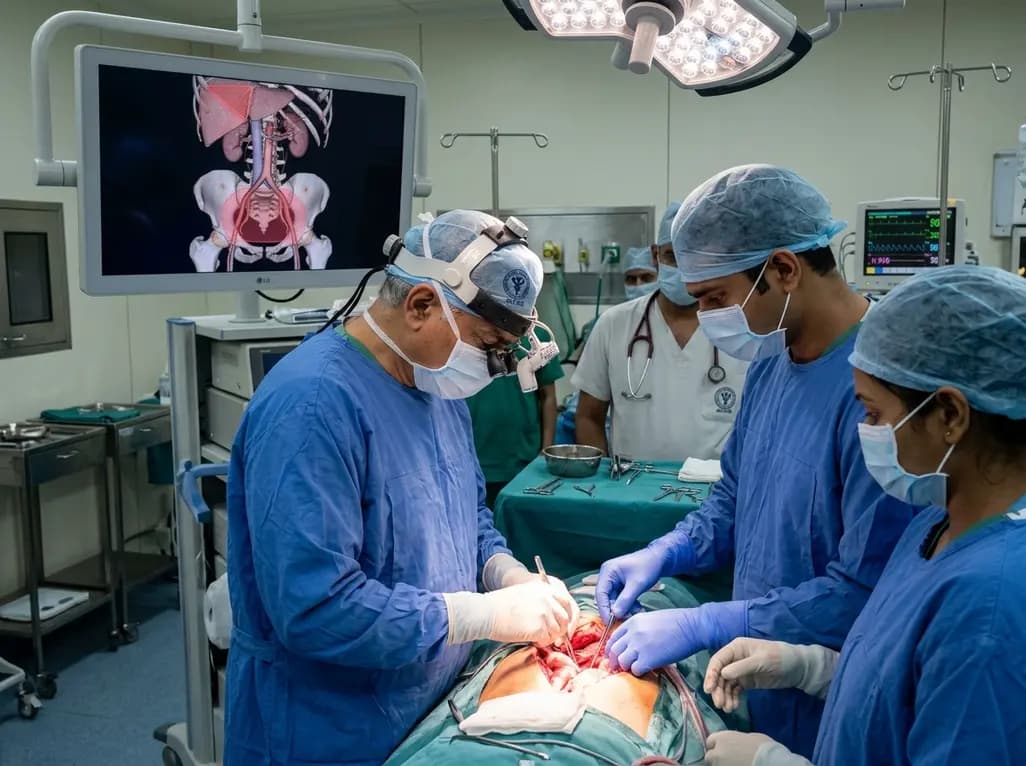
Surgical oncologists at AIIMS Delhi have mapped two critical anatomical landmarks: Ray's Zone in the deep pelvis and Ray's Hepatocaval Triangle near the liver. These predefined hazard boundaries guide dissection, dramatically reduce severe intraoperative bleeding, and preserve vital nerves and visceral organs.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Today

A novel sacrificial-template technique combines FDM polymer 3D printing and micro-arc oxidation to fabricate orientation-controlled porous titanium scaffolds. These bioactive constructs offer tailored stiffness, exceptional multidirectional load resistance, and robust osseointegration for bone defect repair.
Today
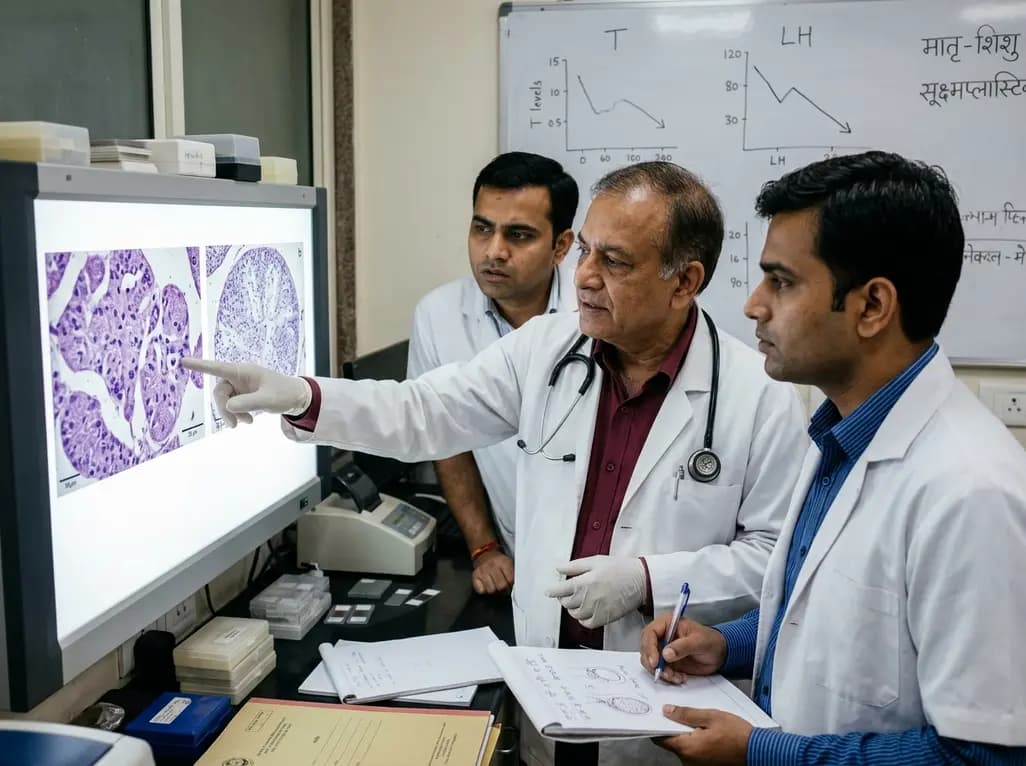
An animal model study reveals that gestational exposure to polystyrene microplastics causes persistent intrauterine growth restriction, testicular hypoplasia, Leydig cell depletion, and an atypical low-testosterone, low-LH endocrine profile in male offspring from birth into adulthood.
Today
