

Loading, please wait...
Loading, please wait...

Ventral hernia reconstruction presents a formidable operative challenge, particularly in medically complex individuals with compromised immunity. Surgeons frequently encounter immunosuppressed patients presenting with abdominal wall defects after solid organ transplantation, intensive chemotherapy, or chronic corticosteroid administration. Because impaired host defenses elevate the risk of wound contamination, placing permanent synthetic prosthesis carries substantial hazard. Consequently, surgeons increasingly explore absorbable mesh ventral hernia repair to minimize chronic foreign material exposure. Permanent synthetic materials provide dependable mechanical reinforcement, but they often necessitate complete explantation if severe infection develops. Biologic prostheses offer an alternative, yet their prohibitive cost and variable long-term durability restrict routine adoption. In contrast, biosynthetic scaffolds degrade gradually while promoting native collagen deposition across the defect. Therefore, slowly resorbable polymers have gained considerable interest among reconstructive surgeons globally. Furthermore, they balance initial mechanical integrity with lower long-term foreign body burdens. Determining whether bioabsorbable scaffolds mitigate perioperative infection without increasing mechanical failure remains an urgent priority. Additionally, underlying comorbidities such as diabetes and malnutrition compound operative risks in these individuals. Surgeons must therefore evaluate individual patient risk profiles carefully before selecting prosthetic materials.
A recent multicentric French cohort investigation led by Joliat and colleagues evaluated poly-4-hydroxybutyrate biomaterials in abdominal wall reconstruction. This biopolymer degrades over 12 to 18 months via natural enzymatic hydrolysis into non-toxic metabolites. The researchers analyzed 465 consecutive patients undergoing ventral hernia repair between 2017 and 2024 across two tertiary institutions. Specifically, the team examined 27 immunosuppressed patients receiving poly-4-hydroxybutyrate mesh. They compared these vulnerable individuals against two distinct cohorts: 232 immunocompetent patients repaired with poly-4-hydroxybutyrate mesh and 206 immunocompetent patients receiving permanent synthetic mesh. The authors defined immunosuppression as reduced physiological immunity resulting from systemic diseases or pharmacological agents. Moreover, the surgical teams deployed standardized retrorectus and component separation techniques when reconstructing substantial fascial defects. The primary objective focused on assessing short-term wound morbidity and mid-term infectious complications. In addition, the investigators monitored structural recurrence throughout extended postoperative surveillance. Furthermore, rigorous statistical comparisons between these diverse groups help delineate whether clinical complications arise from the chosen prosthetic material or baseline patient vulnerability.
The study revealed reassuring safety findings regarding surgical site infections across the study cohorts. Notably, immunosuppressed patients receiving poly-4-hydroxybutyrate mesh demonstrated postoperative outcomes comparable to immunocompetent patients receiving the same scaffold over a mean follow-up of 15 months. Neither group showed statistically meaningful divergence in wound breakdown, surgical site occurrences, or early mechanical failure. However, when researchers contrasted immunosuppressed patients against immunocompetent individuals with permanent synthetic mesh, overall morbidity differed significantly. Immunosuppressed patients experienced an overall complication rate of 44 percent, whereas immunocompetent synthetic recipients had a morbidity rate of 18 percent. This disparity primarily reflected systemic medical complications rather than catastrophic biomaterial contamination. In fact, surgical site infection rates and mesh infection rates remained statistically indistinguishable between the two cohorts over a mean follow-up of 19 months. Furthermore, multivariate regression demonstrated that immunosuppression was not an independent predictor of surgical site infection. Consequently, clinicians can manage postoperative issues aggressively without prematurely attributing systemic deterioration to early surgical implant failure.
Although infectious complications remained low, surgeons must carefully evaluate structural durability following complete mesh degradation. The study reported equivalent mid-term recurrence rates across all study arms during intermediate surveillance. Nevertheless, full enzymatic clearance of poly-4-hydroxybutyrate typically requires up to 18 months. As the polymer degrades, mechanical load gradually transfers onto newly formed host collagen fibers. If immunosuppressive medications or systemic illness impair collagen maturation, late fascial laxity or incisional herniation might emerge. Furthermore, external registry data suggest that recurrence curves for slowly absorbable meshes diverge slightly between two and five years. Clinicians must therefore avoid assuming mid-term safety guarantees permanent fascial stability. In addition, previous studies identify hypertension, previous hernia repair attempts, and defect width as substantial drivers of structural failure. Surgeons should incorporate these procedural and patient factors during operative planning. Therefore, careful longitudinal follow-up beyond two years remains essential for validating mechanical durability. Moreover, routine radiologic evaluations during annual reviews can detect subclinical fascial attenuation before overt clinical bulging creates distressing physical symptoms.
These clinical findings provide valuable guidance for surgical practitioners managing complex abdominal walls across Indian healthcare settings. Indian tertiary hospitals encounter rising numbers of immunosuppressed patients, including renal transplant recipients, patients on biologics, and diabetic individuals. In these vulnerable populations, prosthetic mesh infections create catastrophic dilemmas involving prolonged hospitalization and expensive secondary explantations. Consequently, utilizing a slowly resorbable biosynthetic scaffold offers an appealing alternative when surgeons fear devastating prosthetic contamination. However, surgeons must balance this clinical advantage against substantial cost considerations in resource-constrained environments. Poly-4-hydroxybutyrate meshes remain significantly more expensive than standard polypropylene prostheses in India. Therefore, surgical teams should selectively reserve resorbable meshes for high-risk, contaminated, or immunocompromised patients where mesh removal would prove life-threatening. Additionally, surgeons must maintain rigorous operative technique, ensuring primary fascial closure and well-vascularized retrorectus placement. By combining precise surgical execution with selective biomaterial allocation, Indian surgeons can achieve optimal clinical outcomes while managing financial expenditure responsibly. Ultimately, judicious patient selection empowers surgical teams to protect delicate abdominal reconstructions without placing excessive financial strain on patients or institutions.
Immunosuppressed patients exhibit blunted inflammatory responses and impaired phagocytic activity, making bacterial eradication exceptionally difficult once a biofilm forms on permanent synthetic materials. Consequently, conservative antibiotic therapy frequently fails in this vulnerable population. Persistent mesh sepsis often causes chronic sinus formation, enterocutaneous fistulas, or severe systemic bacteremia. Therefore, resolving the infection usually demands complex surgical explantation, which results in extensive abdominal wall loss, prolonged hospitalization, and elevated perioperative mortality.
Poly-4-hydroxybutyrate degrades through slow enzymatic hydrolysis into 4-hydroxybutyrate, a naturally occurring human metabolite found across brain and soft tissues. This bioresorption spans approximately 12 to 18 months, maintaining structural strength during early tissue remodeling. As the scaffold gradually absorbs, mechanical tension transfers steadily onto newly deposited host collagen fibers. Consequently, this biological transition encourages organized neo-vascularized fascial regeneration while completely eliminating foreign prosthetic material, thereby preventing late-onset chronic mesh complications.
Surgeons should consider resorbable synthetic meshes in contaminated operative fields, high-risk immunosuppressed hosts, or patients undergoing reoperation for prior mesh infection. In these perilous scenarios, permanent polypropylene carries an excessive risk of chronic infection and demanding explantation. Conversely, clean elective reconstructions in immunocompetent individuals still favor standard permanent synthetics due to proven long-term durability and lower material expenditure. Therefore, clinicians must individualize mesh selection based on patient-specific contamination and host immunity.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Joliat GR et al. Outcomes of Long-Term Absorbable Mesh Use for Ventral Hernia Repair in Immunosuppressed Patients. World J Surg. 2026 Oct 04. doi: 10.1002/wjs.70609. PMID: 42829876.
Elemosho A, Janis JE. Comparative Long-term Performance of Biologic, Synthetic, and Long-acting Resorbable Meshes in Ventral Hernia Repair: Population Survival Kinetics Approach. J Am Coll Surg. 2025.
Buijsman L et al. Long-Term Outcomes After Slowly Resorbable P4HB Mesh Implantation: A Multicenter Analysis From European Registry. World J Surg. 2026; doi: 10.1002/wjs.70331.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multicentric cohort study shows long-term absorbable P4HB mesh yields similar surgical site and mesh infection rates in immunosuppressed and non-immunosuppressed ventral hernia repairs, though overall systemic morbidity remains higher in immune-compromised hosts.
Today
A bioengineered oral nanozyme microsupplement converts pathological ROS into a protective polydopamine hydrogel shield. By curbing neutrophil extracellular traps and balancing T cells, this platform outperforms standard 5-ASA in preclinical colitis models, opening new paths for sustained remission.
Today

India experiences an exponential rise in robotic-assisted procedures, with Delhi NCR leading system installations and clinical volume. Discover how multidisciplinary surgical adoption, remote telesurgery breakthroughs, and standardized international consensus guidelines are shaping surgical care nationwide.
Today
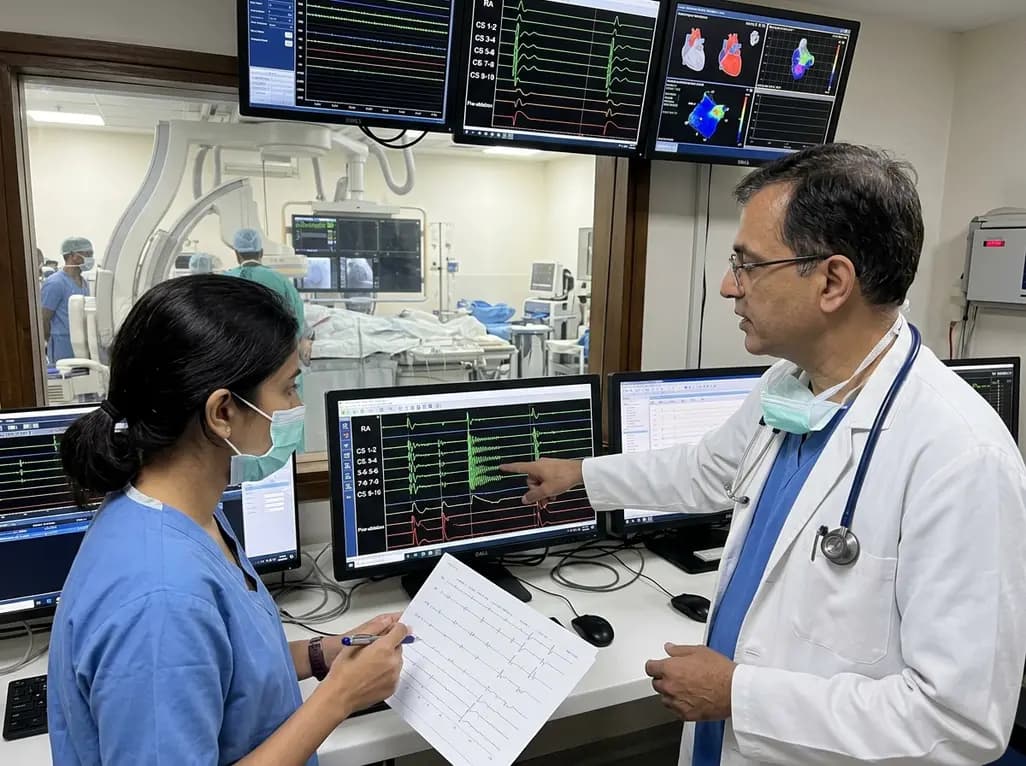
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today
A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today

A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
Yesterday
