

Loading, please wait...
Loading, please wait...
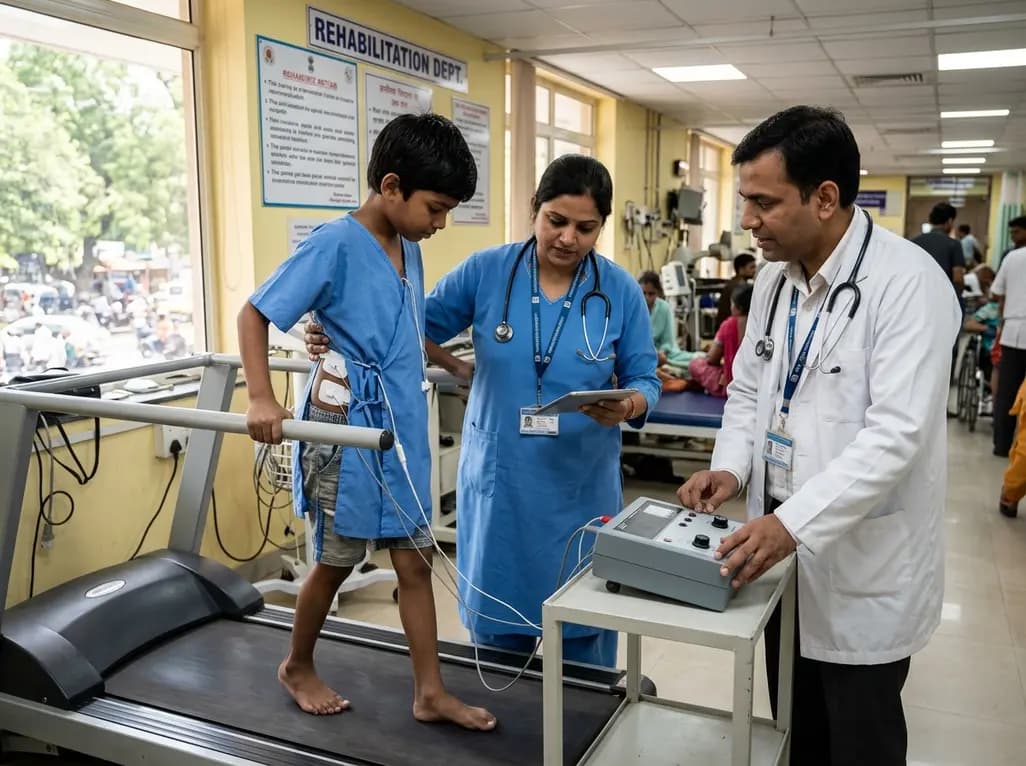
Clinical consensus traditionally regarded motor-complete spinal cord injury as an irreversible condition causing permanent paralysis below the lesion. However, emerging neurorehabilitation paradigms challenge this dogma by engaging latent neuroplasticity within isolated neural pathways. Recent clinical breakthroughs demonstrate that transcutaneous spinal neuromodulation can reactivate dormant spinal networks in pediatric patients. Consequently, clinicians now observe voluntary movement in children once deemed permanently paralyzed.
Human spinal cord architecture contains complex central pattern generators that coordinate rhythmic locomotor patterns independently of direct cerebral input. In healthy individuals, descending supraspinal drives modulate these spinal interneuronal networks to execute purposeful ambulation. Following traumatic injury, disrupted axonal pathways deprive these circuits of critical tonic excitation, resulting in functional paralysis. However, anatomically silent axons frequently survive across the injury site even in motor-complete lesions. Transcutaneous stimulation delivers targeted electrical currents across dorsal roots through non-invasive surface electrodes placed over specific spinal segments. Therefore, this external current elevates spinal excitability to a physiological threshold near functional activation. When combined with intensive physical cues, these primed central pattern generators interpret peripheral sensory feedback effectively. Furthermore, descending cognitive intention synchronizes with local circuits, reopening dormant communication channels across damaged tracts. Additionally, repetitive multisegmental stimulation promotes neuroplastic reorganization within lumbar enlargements. Over multiple sessions, synaptic efficacy strengthens substantially among local interneurons and surviving descending fibers. Consequently, clinicians stimulate natural physiological plasticity rather than relying purely on passive biomechanical bracing.
A landmark pediatric study investigated this multimodal approach in five non-ambulatory children with chronic, motor-complete spinal cord injury. The cohort averaged 9.6 years of age, presenting with sustained injuries lasting over one year. Specifically, four participants suffered thoracic injuries, while one experienced cervical cord trauma. The therapeutic intervention combined activity-based locomotor training with transcutaneous spinal stimulation and focused cognitive intent to step. Over sixty rigorous training sessions, clinicians systematically recorded motor responses and kinematic joint trajectories. Initially, researchers assessed participants in a gravity-neutral apparatus to eliminate weight-bearing barriers. During their very first session with active stimulation, all five children successfully initiated small, reciprocal hip and knee flexion-extension cycles. Furthermore, these cyclic stepping patterns expanded significantly as training progressed. By session twenty, quantitative analyses revealed statistically significant kinematic enhancements across all participants. For example, mean right hip excursion increased from 10.1 degrees to 25.9 degrees. Similarly, right knee excursion improved from 9.3 degrees to 39.6 degrees. Moreover, therapists adjusted electrical parameters continuously to facilitate natural stepping without discomfort. Consequently, the children engaged actively during every therapeutic session, reinforcing their volitional neural drive.
Beyond gravity-neutral kinematics, the intervention achieved groundbreaking milestones in functional ambulation overground. Between session twenty and session sixty, all five children advanced to initiating overground stepping maneuvers. Specifically, three participants accomplished voluntary overground steps by session twenty, while the remaining two reached this milestone by sessions fifty and sixty. The children actively initiated and alternated reciprocal leg swings on treadmills and solid ground. Most importantly, participants maintained the ability to initiate bilateral steps even when therapists turned off electrical stimulation entirely. This critical observation confirms genuine neuroplastic restructuring rather than simple device-dependent motor substitution. Furthermore, formal assessments conducted three to six months post-intervention demonstrated sustained motor retention across all pediatric participants. The children did not lose their acquired stepping capacity during the follow-up window. In contrast to historical assumptions regarding chronic paralysis, these findings illustrate persistent functional reorganization within spinal locomotor centers. Additionally, pediatric neuroplasticity likely accelerates these adaptive synaptic modifications compared to adult cohorts. Consequently, early therapeutic neuromodulation during critical developmental windows may alter long-term prognostic trajectories for injured youths worldwide.
The benefits of non-invasive spinal stimulation extend far beyond voluntary motor kinematics. During the clinical trial, both parents and children reported notable, unanticipated enhancements across several secondary physiological domains. Specifically, participants demonstrated meaningful improvements in tactile sensation and lower-extremity proprioceptive awareness. Neurological recovery also positively influenced autonomic bowel and bladder regulatory functions, which represent paramount quality-of-life priorities for paralyzed youths. Additionally, parents observed dramatic gains in core trunk stability and posture control. These foundational trunk improvements facilitated smoother transfers between wheelchairs and beds, significantly easing daily caregiving burdens. Children required substantially less physical assistance when standing, dressing, and performing routine activities of daily living. Furthermore, enhanced trunk stability directly reduces the long-term risk of progressive neuromuscular scoliosis, a devastating complication common in pediatric spinal trauma. Emerging clinical literature also associates regular locomotor activation with improved bone mineral density and cardiovascular health. Therefore, multisystemic rehabilitation addresses systemic physiological deterioration alongside locomotor paralysis. Clinicians must recognize that restoring partial autonomic and trunk competence profoundly impacts psychosocial development in growing children.
Translating non-invasive spinal stimulation into broader clinical practice holds immense promise, particularly within developing healthcare landscapes like India. Pediatric spinal cord injuries from road traffic accidents, falls, and infections pose substantial long-term economic and psychological burdens on families. Surgical epidural stimulators entail significant hardware costs, surgical infection risks, and inevitable revision surgeries as pediatric spines grow. In contrast, transcutaneous spinal stimulation utilizes non-invasive surface electrodes, offering a remarkably cost-effective and adaptable modality. Physiotherapy centers across tertiary institutions can readily incorporate this technology without demanding specialized operating theaters or implant maintenance. However, successful translation requires comprehensive, multidisciplinary protocols combining electrical stimulation with intensive activity-based locomotor training. Rehabilitation teams must train physical therapists to recognize signs of autonomic dysreflexia and monitor skin integrity beneath stimulation electrodes. Additionally, clinicians should educate caregivers to reinforce active cognitive engagement during rehabilitation rather than expecting passive technological remedies. Indian tertiary hospitals and research institutes can lead multicentric trials to standardize pediatric dosage parameters. Ultimately, expanding access to non-invasive neuromodulation could transform pediatric disability management and democratize advanced neuro-recovery nationwide.
Transcutaneous spinal stimulation delivers electrical currents non-invasively through cutaneous electrodes over the spine. In contrast, epidural stimulation requires surgical implantation of electrode arrays and pulse generators. Transcutaneous neuromodulation eliminates surgical morbidity, infection risks, and hardware revision challenges, making it particularly advantageous for growing pediatric patients who experience ongoing spinal elongation.
Descending cognitive intent actively recruits residual, anatomically preserved corticospinal pathways that bridge the spinal lesion. When patients concentrate on moving their limbs, descending volitional impulses coincide with sensory afferent feedback and electrical stimulation. Consequently, this synergistic activation promotes long-term synaptic potentiation, neuroplastic circuit rewiring, and durable recovery independent of external electrical devices.
Beyond motor stepping gains, participants experienced meaningful improvements in tactile sensation, proprioception, and voluntary bladder regulation. Furthermore, children demonstrated enhanced trunk stability, allowing easier bed transfers, assisted standing, and independent dressing. These systemic enhancements substantially ease caregiver dependency, lower risks of progressive scoliosis, and elevate the overall daily quality of life.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A groundbreaking study shows that non-invasive transcutaneous spinal neuromodulation paired with locomotor training restores durable voluntary stepping and autonomic improvements in children with chronic motor-complete spinal cord injury, challenging historic dogmas of permanent paralysis.
last month

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
Perimenopause brings erratic hormonal surges and metabolic shifts that significantly affect breast tissue. This comprehensive clinical review examines benign breast conditions, cancer risk stratification, mammographic density challenges, and endocrine therapy transitions in midlife women.
Today

The VOCAL-AHF study reveals that most acute heart failure patients across reduced and non-reduced ejection fraction categories are eligible for in-hospital GDMT initiation. Notably, nearly two-thirds of HFrEF patients qualify for quadruple therapy, while non-reduced EF patients show high eligibility for dual therapy.
Today
A retrospective study evaluates pediatric osteoarticular infections in immunocompromised children and neonates, emphasizing diagnostic challenges, elevated CRP, diverse microbiology, and the necessity of multimodal surgical and medical management to achieve favorable functional outcomes.
Today

This review examines the pharmacogenomics of antidiabetic agents, highlighting how genetic variations in SLC2A2, SLC47A1, CYP2C9, ABCC8, and GLP1R influence drug transport, therapeutic efficacy, and hypoglycemia risk to enable tailored precision medicine in type 2 diabetes.
Today
