

Loading, please wait...
Loading, please wait...

Recent political declarations advocating for splitting childhood vaccines into five distinct doses have reignited public discussions on immunization policy. Proponents claim that administering fractional doses at prolonged six-month intervals might curb neurodevelopmental disorders. However, pediatricians and immunologists warn that such unverified modifications lack scientific justification. Established childhood vaccination protocols emerge from exhaustive clinical research designed to balance safety, immunogenicity, and timely protection. When political assertions challenge evidence-based medicine, healthcare professionals must critically examine the scientific literature. Clinicians need clear insights to counsel concerned parents and preserve community immunity against dangerous infectious diseases.
Vaccine development relies on precise pharmacodynamics and immunological kinetics. Vaccine researchers formulate childhood immunizations with calibrated antigen levels to generate adequate protective titers. When clinicians administer a complete scheduled dose, specialized antigen-presenting cells engulf the target proteins. Subsequently, these cells migrate to regional lymph nodes to activate naive helper T cells and B lymphocytes. This coordinated cellular cascade induces long-lasting memory cells capable of neutralizing wild pathogens upon future exposure.
However, splitting an established vaccine into arbitrary fractional quantities disrupts this immune activation cascade. Sub-potent antigen doses frequently fail to cross the activation threshold required for durable humoral immunity. Instead of conferring partial safety, micro-dosing can stimulate immunological tolerance or weak, transient antibody responses. Furthermore, spacing fractional components across arbitrary six-month intervals introduces wide temporal gaps. During these unprotected periods, circulating maternal antibodies wane, leaving the young infant entirely defenseless against virulent pathogens. Therefore, dividing verified formulations contradicts foundational principles of vaccine immunology. Pharmaceutical manufacturers cannot arbitrarily dilute or segment products without conducting extensive clinical trials to re-verify safety, adjuvant stability, and therapeutic immunogenicity. Additionally, altered doses can destabilize vital preservatives and adjuvants, further diminishing clinical efficacy and batch sterility.
The belief that pediatric immunizations cause autism spectrum disorders remains one of medicine's most durable misconceptions. This fallacy originated from a fraudulent 1998 case series that the medical journal later completely retracted. Since that initial publication, global medical researchers have conducted dozens of large-scale epidemiological investigations. For example, massive population studies involving hundreds of thousands of children in Denmark, Sweden, and the United States evaluated potential associations. Researchers consistently concluded that vaccinated and unvaccinated cohorts display identical autism incidence rates.
Furthermore, contemporary developmental neurobiology reveals that autism spectrum disorders develop long before infant vaccination schedules begin. Comprehensive genetic investigations and prenatal imaging demonstrate structural cortical abnormalities emerging during early fetal gestation. These neurological variations reflect complex polygenic architecture and prenatal environmental influences rather than post-birth immune exposure. Additionally, global systematic reviews by the Institute of Medicine have examined various vaccine components, including thimerosal and measles antigens. Consequently, authoritative institutions have repeatedly affirmed the complete absence of causal associations between vaccines and autism. Promoting arbitrary dose division to prevent autism contradicts decades of scientific evidence and distracts families from proven developmental interventions.
Modern pediatric practice frequently utilizes combination vaccines, such as pentavalent and hexavalent formulations, to protect against multiple lethal pathogens. Historically, children received multiple single-antigen injections, which resulted in significant discomfort and increased clinical visits. Consequently, immunologists engineered combination products that deliver antigens against diphtheria, tetanus, pertussis, hepatitis B, and Haemophilus influenzae type b simultaneously. These advanced products undergo stringent compatibility evaluations to guarantee that combined antigens do not induce immune interference.
Importantly, an infant's immune system possesses an immense natural capacity to process diverse antigenic challenges. Every newborn encounters thousands of novel bacterial and viral antigens immediately upon birth through respiration, feeding, and tactile contact. In contrast, the entire modern childhood vaccination schedule contains fewer than two hundred distinct antigens. Therefore, combination immunizations represent a minuscule fraction of daily immunological exposures. Moreover, combination formulations dramatically improve compliance and completion rates by minimizing injection visits. Separating these combinations into single injections or multiple fractional doses would increase clinic encounters exponentially. As a result, healthcare systems would experience heightened logistical burdens, while children would endure unnecessary physical stress and appointment fatigue. In addition, missed appointments during drawn-out schedules leave pediatric cohorts vulnerable to vaccine-preventable mortality.
Delaying or fractionating childhood vaccinations generates immediate and dangerous public health hazards. Current immunization timelines coordinate precisely with the natural decay of protective maternal antibodies. When physicians follow established calendars, children develop endogenous immunity before their vulnerability peaks. However, proposing five-dose regimens spaced by six-month intervals delays complete protection well past infancy. Consequently, children remain unprotected during their first two years, facing severe risks from measles, pertussis, and invasive bacterial infections.
Furthermore, incomplete immunization coverage severely compromises herd immunity within broader communities. Highly contagious pathogens like measles require a community immunization threshold above ninety-five percent to halt local transmission. When unverified dosing schedules gain traction, parental adherence drops, creating dangerous pockets of under-vaccinated individuals. Recent surges in global measles cases underscore how quickly transmission resumes when vaccination coverage slips below critical benchmarks. In addition, treating preventable outbreaks drains intensive care resources and imposes substantial financial costs on healthcare infrastructure. Thus, arbitrary schedule alterations jeopardize individual pediatric patients and undermine community disease elimination achievements. Moreover, unvaccinated infants expose vulnerable neonates and immunocompromised individuals who cannot receive active immunization to severe, life-threatening nosocomial infections. Consequently, delayed schedules threaten pediatric survival across entire population cohorts.
When political rhetoric promotes unverified immunization alterations, clinicians encounter heightened parental hesitation in everyday consultations. Parents frequently seek reassurance because they fear overwhelming their child's body with standard vaccine formulations. Therefore, healthcare providers must adopt empathetic, transparent, and structured communication strategies to address these anxieties effectively. Dismissing parental concerns often backfires, driving caregivers toward unregulated online misinformation. Instead, clinicians should acknowledge the parent's protective intent while providing clear, accessible scientific explanations.
Specifically, doctors can explain that infant immune systems manage countless environmental pathogens daily without difficulty. Clinicians should emphasize that standardized schedules maximize protection during the months of highest pathogen risk. Furthermore, physicians can highlight that clinical trials have validated existing dosing intervals for optimal safety and efficacy. By contrasting rigorous scientific data with unsubstantiated claims, practitioners help parents distinguish clinical reality from political discourse. Additionally, healthcare clinics should train nursing staff and frontline personnel to deliver unified, evidence-based messaging during routine well-child visits. Ultimately, strong physician-patient rapport and consistent educational dialogue remain essential tools for maintaining immunization compliance. Moreover, dedicated pediatric counseling sessions build enduring trust, ensuring families complete necessary vaccination series on schedule.
Q1: Does any clinical evidence support dividing routine childhood immunizations into multiple smaller doses?
No robust clinical evidence supports dividing routine immunizations into multiple smaller doses. In fact, regulatory agencies approve vaccines based on rigorous dose-finding trials that identify the optimal antigen concentration. Therefore, altering these established formulations without pharmacokinetic data threatens immune efficacy. Splitting doses reduces antibody titers below protective thresholds. Consequently, children face prolonged susceptibility to life-threatening infections without gaining any therapeutic or developmental benefit whatsoever from the unproven regimen.
Q2: Why do pediatric guidelines advocate for combination vaccines rather than separated single-antigen injections?
Pediatric guidelines advocate for combination vaccines because they streamline immunization and minimize physical trauma for infants. Moreover, combination shots reduce clinic visits and lower administrative burdens for families and healthcare systems. Decades of immunological research confirm that simultaneous antigen exposure does not overwhelm an infant's resilient immune system. Instead, combination formulations maintain robust seroconversion rates comparable to separate injections. Thus, they protect infants promptly against multiple communicable pathogens during their most vulnerable developmental windows.
Q3: What scientific consensus exists regarding the purported connection between childhood vaccines and autism spectrum disorders?
An overwhelming global scientific consensus confirms that vaccines do not cause autism spectrum disorders. Extensive epidemiological studies involving millions of children across multiple continents have thoroughly investigated this hypothesis over several decades. Consequently, health authorities including the World Health Organization have completely refuted any causal link. Genetic and prenatal neurological research demonstrates that autism originates during early fetal brain development long before routine vaccinations occur. Therefore, delaying or altering immunization schedules offers zero neurological protection.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Recent political proposals advocate dividing pediatric immunizations into multiple fractional doses to counter unproven developmental risks. However, extensive clinical trials confirm that standardized schedules maximize antibody response while arbitrary fractionation leaves infants vulnerable to severe pathogens.
Today

The Central Council for Research in Ayurvedic Sciences emphasizes that integrating traditional medicine with mainstream healthcare requires scientific rigor. Enhanced pharmacovigilance networks, adverse drug reaction monitoring, and validated clinical trials remain pivotal to elevating clinical credibility.
Today
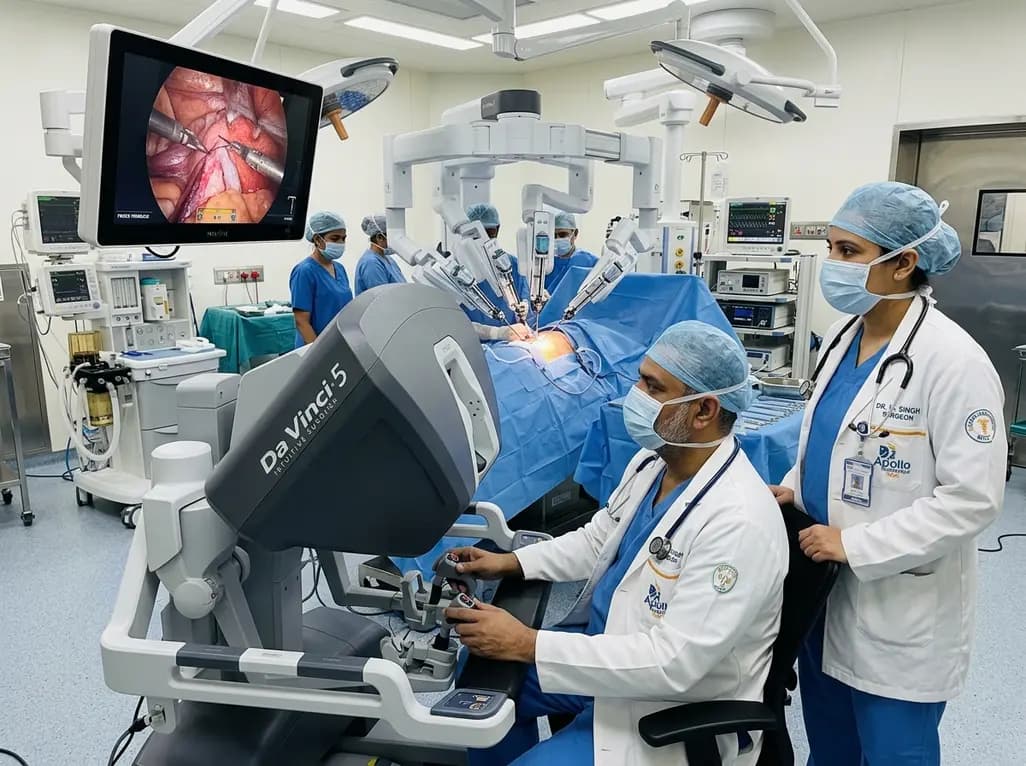
India expands its minimally invasive surgical landscape as Intuitive unveils its fifth-generation robotic platform. Equipped with real-time force feedback and immense computing performance, this innovation assists clinical specialists across urology, gynecology, and general surgery in optimizing operative care.
Today

Large-scale biobank research demonstrates that low-grade systemic inflammation quietly remodels ventricular architecture years before cardiovascular symptoms appear. Learn how emerging biomarkers like GlycA and targeted anti-inflammatory pathways could reshape preventive cardiovascular screening and clinical risk evaluation.
Today

Systematic review comparing labral repair and reconstruction in primary hip arthroscopy shows comparable short- to mid-term patient-reported outcomes, with lower THA conversion after repair but superior outcomes for reconstruction in patients aged 40 and older.
Today

A preclinical study reveals that alpinetin significantly alters glimepiride pharmacokinetics by inhibiting CYP2C9. This drug-herb interaction enhances hypoglycemic potency and underscores critical safety concerns regarding severe hypoglycemia in diabetic management.
Today
