

Loading, please wait...
Loading, please wait...

Prenatal screening has evolved significantly over the past decade, moving beyond common aneuploidies toward subchromosomal genomic alterations. Non-invasive prenatal testing now frequently evaluates fetal copy number variants across the genome. However, low fetal fraction and low sequencing depth often restrict analytical precision during conventional screening. A landmark study evaluated how size-selective placental cell-free DNA enrichment enhances the performance of low-depth sequencing for detecting these microdeletions and microduplications. Consequently, these findings offer vital guidance for obstetricians managing modern prenatal screening pathways.
Circulating cell-free DNA in maternal blood contains both maternal genomic material and placental fragments. Typically, placental trophoblast-derived fragments measure slightly shorter than background maternal fragments. Size-selective enrichment exploits this length difference to preferentially isolate shorter fragments before sequencing. In this study, enrichment achieved an impressive mean fetal fraction of 18.88% ± 5.82%. Therefore, laboratories amplify the fetal signal without increasing costly sequencing depth. Because maternal background DNA often dilutes fetal anomalies, raising the fetal fraction improves the signal-to-noise ratio significantly. Furthermore, higher fetal fractions minimize test failure rates and mitigate analytical ambiguity. Clinical geneticists recognize that identifying subchromosomal gains and losses demands robust algorithmic resolution. Hidden Markov Models effectively detect subtle copy number alterations when supported by adequate fetal representation. Thus, physical enrichment directly addresses the primary biological limitation of non-invasive prenatal screening. As a result, clinicians gain greater analytical reliability when screening for actionable microdeletions.
The investigative team conducted a retrospective analysis involving 86,012 pregnant women undergoing low-depth prenatal screening. Through advanced bioinformatics powered by Hidden Markov Models, researchers identified 340 copy number variations in 339 women. Consequently, the overall CNV positive screen rate was 0.39% [95% CI: 0.35%, 0.44%]. Deletions constituted the majority of positive findings, representing 249 cases, whereas duplications accounted for 91 cases. This distribution aligns with global literature indicating that deletions occur more frequently or elicit stronger bioinformatic signals. Moreover, screening performance remained consistent across diverse maternal demographics. Because the study analyzed such an extensive cohort, it provides realistic prevalence figures for subchromosomal imbalances in routine screening. Clinicians must realize that subchromosomal anomalies occur independently of maternal age, unlike standard trisomies. Therefore, universal screening platforms must maintain strict analytical thresholds to prevent excessive false-positive alerts. Ultimately, establishing baseline detection rates allows obstetric units to allocate genetic counseling resources effectively.
Evaluating the clinical utility of any screening test hinges entirely on its positive predictive value. In this cohort, screen-positive patients received confirmatory prenatal diagnosis through chromosomal microarray analysis. The total positive predictive value reached 59.20% [95% CI: 52.05%, 66.00%], reflecting 119 confirmed true positives out of 201 evaluated pregnancies. Notably, historical studies of genome-wide screening without enrichment often report predictive values below 40%. Hence, size-selective enrichment provides a tangible leap in diagnostic reliability. In addition, the predictive yield correlated positively with larger aberration sizes and higher fetal fractions. However, clinicians must remember that nearly 41% of screen-positive results represented false positives. Confined placental mosaicism, maternal copy number variants, and bioinformatic artifacts frequently drive these discordant results. Therefore, while enriched screening sharpens risk stratification, it remains strictly a screening modality rather than a diagnostic test.
Beyond identifying the mere presence of an imbalance, clinicians require precise structural characterization of genomic segments. The investigators examined breakpoint validation accuracy between non-invasive screening and invasive chromosomal microarray testing. Surprisingly, 85.83% [95% CI: 78.01%, 91.29%] of detected variants exhibited size discrepancies between the two platforms. Low-depth sequencing inherently limits base-pair resolution, frequently overestimating or underestimating exact genomic breakpoints. Furthermore, repetitive sequence elements and variable GC-content across chromosomes disrupt sequencing coverage uniformity. Consequently, an assay may flag a pathogenic region accurately, yet misestimate its exact genomic span. This nuance carries significant clinical weight during prognostic evaluation. Phenotypic severity often depends heavily on whether critical dosage-sensitive genes fall inside or outside the affected interval. Therefore, obstetricians cannot rely on non-invasive screening coordinates to predict clinical prognosis. Invasive chromosomal microarray analysis remains essential to define exact chromosomal boundaries and guide parental testing.
Integrating expanded genomic screening into daily practice demands structured and empathetic genetic counseling protocols. Before ordering non-invasive screening, clinicians must articulate the boundaries between screening and diagnostic assays clearly. Patients should understand that low-depth sequencing screens for potential risks rather than providing definitive answers. When a positive result emerges, clinicians must avoid premature reproductive decisions or unindicated pregnancy terminations. Instead, practitioners should promptly arrange genetic counseling and offer invasive confirmatory testing via amniocentesis. Chorionic villus sampling requires caution because it samples placental trophoblasts, which share the biological origins of cell-free DNA. Consequently, confined placental mosaicism can produce misleading concordance during villus sampling. Amniocentesis provides true fetal amniocytes, ensuring definitive chromosomal microarray assessment. In addition, targeted prenatal ultrasound examinations should evaluate fetal structural anatomy for associated dysmorphic features. By establishing a methodical diagnostic pathway, clinicians alleviate maternal anxiety and guide families responsibly.
The emergence of size-selective fragment enrichment marks an important technological advancement for reproductive medicine. By boosting the fetal fraction naturally, laboratories achieve higher analytical sensitivity without incurring unsustainable sequencing expenses. This balance between cost-efficiency and clinical performance proves vital for expanding genomic access across diverse healthcare settings. However, widespread adoption requires standardized reporting guidelines and universal quality metrics across molecular diagnostic laboratories. Professional societies emphasize that clinical implementation must prioritize patient autonomy and transparent risk communication. Moreover, artificial intelligence and refined machine learning models may soon enhance breakpoint estimation and artifact removal. As sequencing technologies continue to mature, non-invasive workflows will provide increasingly accurate genomic insights. Nevertheless, clinical judgment and ethical responsibility remain the cornerstone of prenatal medicine. Obstetricians and fetal medicine experts must actively educate themselves to interpret complex genomic screening data accurately.
Fetal copy number variants represent subchromosomal deletions or duplications of genomic material that can cause severe neurodevelopmental disorders and congenital malformations. Screening for these variants using maternal plasma is challenging because fetal cell-free DNA fragments circulate at low concentrations against a vast background of maternal DNA. Additionally, low sequencing depth and variable genomic architecture make distinguishing true microdeletions from background analytical noise technically difficult without specialized molecular enrichment.
Placental cell-free DNA fragments are naturally shorter than maternal background fragments in peripheral blood. Size-selective enrichment isolates and concentrates these shorter DNA fragments prior to library preparation and sequencing. Consequently, this physical selection significantly increases the fetal fraction to an average near nineteen percent. A higher fetal fraction enhances the signal-to-noise ratio, reduces analytical ambiguities, and boosts positive predictive values for microdeletions and microduplications without increasing sequencing depth.
Non-invasive prenatal testing functions strictly as a screening tool rather than a definitive diagnostic test. In clinical evaluations, over forty percent of positive findings represent false positives due to confined placental mosaicism or maternal variants. Furthermore, low-depth screening displays substantial breakpoint discrepancies in over eighty-five percent of cases. Invasive amniocentesis followed by chromosomal microarray analysis provides diagnostic certainty, precise genomic boundaries, and accurate gene content essential for clinical prognostication.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A retrospective study of 86,012 pregnancies demonstrates that size-selective cfDNA enrichment boosts mean fetal fraction to 18.88% and achieves a 59.20% PPV for fetal copy number variants. However, 85.83% of CNVs showed size discrepancies, underscoring the mandatory role of confirmatory microarray testing.
Today
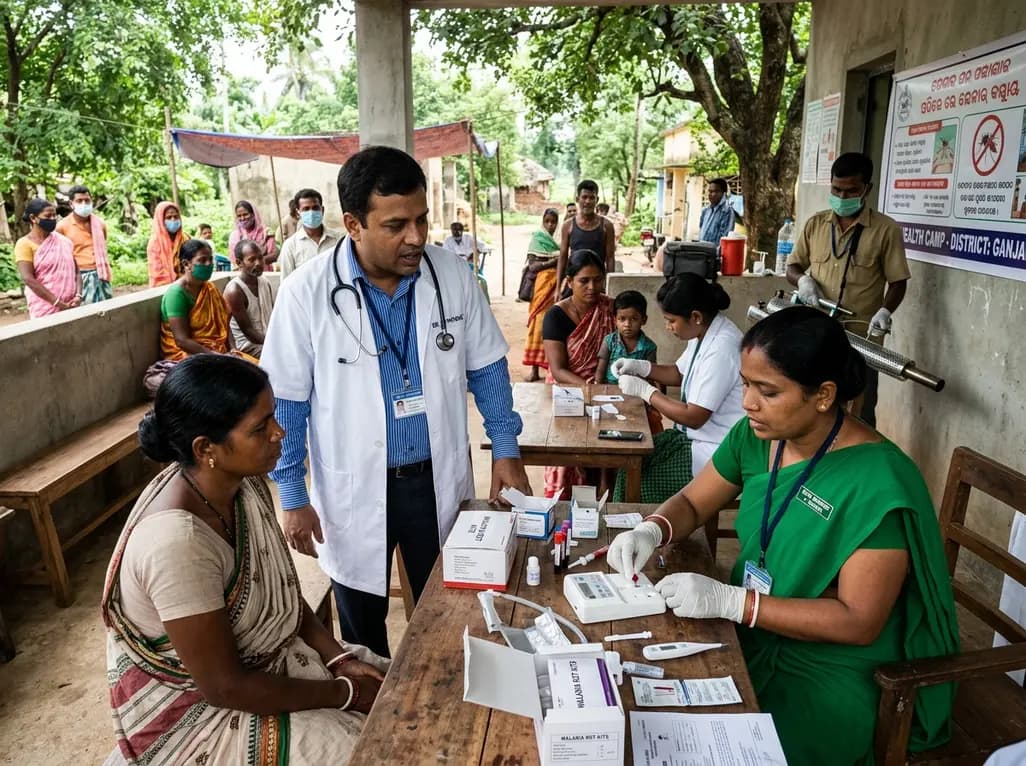
Following 37,899 reported cases and 9 deaths, Odisha has scaled up active case detection, rapid diagnostic testing, and vector control across high-burden districts. Here is a comprehensive clinical breakdown of the state's aggressive containment protocols, diagnostic pathways, and targeted field management.
Today
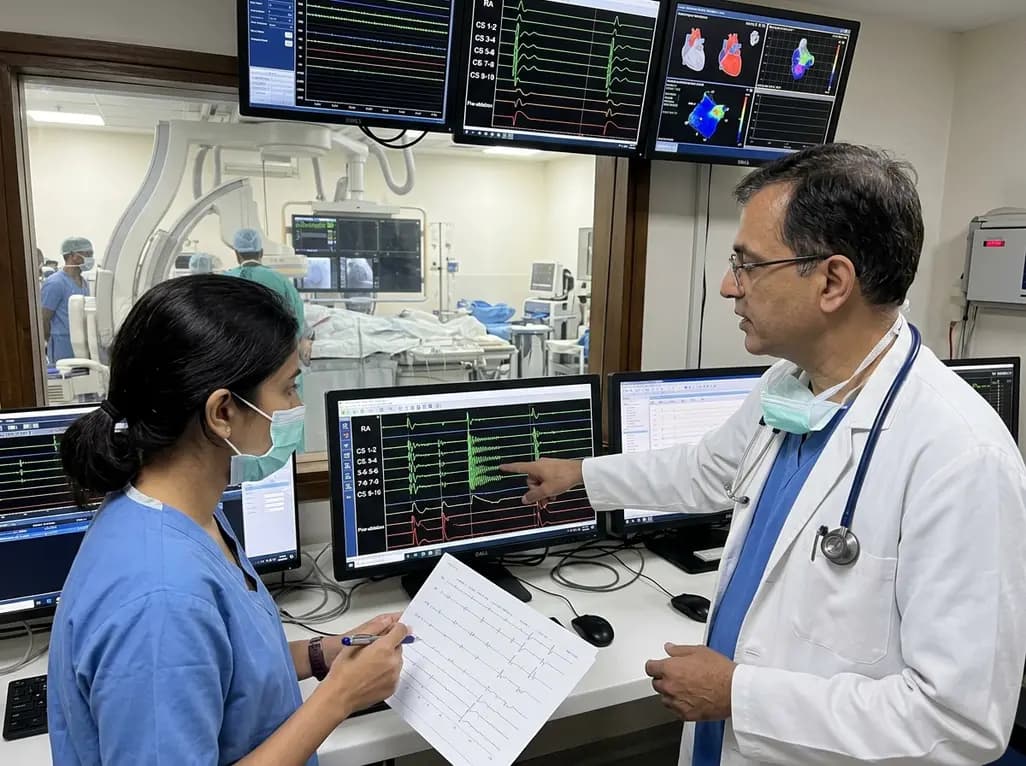
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today
A cross-sectional study demonstrates that increased BMI in adolescents significantly enhances mandibular length and alters salivary adipokines like adiponectin and resistin, providing novel insights into craniofacial growth and orthodontic planning.
Today
