

Loading, please wait...
Loading, please wait...

Pediatric obesity remains a critical global health concern that profoundly alters systemic physiology, skeletal maturation, and tissue metabolism. Clinicians routinely evaluate growth patterns to guide interceptive dentofacial therapies. Emerging evidence now demonstrates that elevated body weight directly influences craniofacial morphology during pubertal development. Specifically, recent findings highlight notable variations in mandibular length in adolescents presenting with increased body mass index. Understanding these craniofacial adaptations alongside endocrine shifts enables orthodontists, pediatricians, and endocrinologists to optimize diagnostic precision and treatment timing.
Craniofacial biologists have long recognized that biomechanical loading and systemic hormones regulate condylar cartilage proliferation. Consequently, investigators designed a rigorous cross-sectional trial to compare jaw dimensions across distinct weight categories. The study evaluated 50 adolescents with a mean age of 13.54 years, stratifying them into normal and increased body mass index groups. The investigators gathered standardized pre-treatment lateral cephalograms to calculate linear skeletal relationships. In addition, the team obtained hand-wrist radiographs and cervical vertebral assessments to quantify biological maturity. The primary anatomical focus centered on effective maxillary length and effective mandibular length. After applying false discovery rate adjustments, adolescents with higher weight exhibited an 8.13 mm greater effective mandibular length compared to normal-weight peers. Maxillary dimensions displayed a similar positive trend, whereas vertical facial dimensions and dental parameters remained statistically unchanged. Therefore, elevated weight status selectively influences sagittal mandibular dimensions without disrupting vertical craniofacial proportions.
Orthodontic diagnostics rely heavily on sagittal balance to manage class II and class III malocclusions effectively. Furthermore, clinicians often correlate mandibular position with condylar remodeling and neurocranial development. In this investigation, researchers measured the condylion-to-gnathion distance to evaluate lower jaw growth. The striking 8.13 mm divergence highlights accelerated or extended mandibular expansion among adolescents with increased weight. However, the study observed no meaningful discrepancies in soft tissue thickness, lip posture, or vertical anterior facial height. Similarly, skeletal maturation stages assessed via cervical vertebral maturation and the skeletal maturity index showed comparable distributions between cohorts. Consequently, this observation challenges the notion that accelerated chronological growth alone explains greater skeletal dimensions. Instead, accelerated local bone deposition and altered metabolic signaling likely drive sagittal skeletal enlargement. Dentists must acknowledge these distinct anatomical patterns when designing growth modification strategies in overweight children.
Saliva serves as an exceptional non-invasive diagnostic window into circulating endocrine activity. Therefore, researchers obtained unstimulated whole saliva samples to profile systemic endocrine and inflammatory molecules. They deployed multiplex immunoassays to quantify growth hormone, insulin-like growth factor-1, sex steroids, cortisol, and specific adipokines. The analysis uncovered distinct biochemical profiles in adolescents with excess weight. Notably, salivary cortisol levels were significantly lower in the higher weight group after rigorous false discovery rate corrections. Reduced cortisol may reflect dysregulated hypothalamic-pituitary-adrenal axis dynamics and altered glucocorticoid feedback sensitivity. Conversely, salivary resistin concentrations rose significantly among adolescents with elevated weight status. Resistin acts as a potent pro-inflammatory adipokine that mediates peripheral insulin resistance and promotes osteoclastogenesis. Thus, salivary fluid reflects both metabolic stress and systemic low-grade inflammation in growing pediatric cohorts.
Adipokines actively modulate bone turnover, chondrocyte differentiation, and skeletal remineralization. To isolate independent associations, researchers built multivariable linear regression models adjusting for patient age, biological sex, and race. Remarkably, salivary adiponectin emerged as a potent independent negative predictor of both maxillary and mandibular length. As circulating and salivary adiponectin levels declined, linear jaw measurements increased significantly. Adiponectin typically exerts anti-inflammatory, insulin-sensitizing, and osteoprotective effects throughout the body. Lower levels of this hormone accompany expanded adipose tissue depots in adolescents with increased weight. Consequently, reduced adiponectin concentration may alleviate inhibitory brakes on osteoblastogenesis and condylar cartilage expansion. In addition, altered adipokine profiles interact with local mechanosensory receptors within the temporomandibular joint complex. Hence, adiponectin serves as a critical biochemical bridge connecting adipose tissue expansion to accelerated sagittal mandibular growth.
These morphological and biochemical insights provide meaningful guidance for pediatric dentists and orthodontists. Historically, clinicians timed functional appliance therapy purely based on cervical vertebral maturation stages. However, excess adiposity alters mandibular dimensional development independently of cervical maturation scores. Orthodontists managing class II malocclusions must recognize that overweight patients may exhibit spontaneous mandibular elongation. Conversely, treating class III tendencies in adolescents with high body mass index demands extreme vigilance, because accelerated lower jaw expansion exacerbates prognathism. Furthermore, heightened resistin and lower adiponectin levels signify persistent systemic inflammation. This pro-inflammatory microenvironment can accelerate orthodontic tooth movement and alter alveolar bone remodeling rates during fixed appliance mechanics. Therefore, dental practitioners should integrate metabolic health markers and weight trajectories into comprehensive orthodontic treatment planning.
Increased body mass index correlates with significantly greater effective mandibular length, creating an average skeletal increase of 8.13 millimeters. Maxillary dimensions also show an upward trend, whereas vertical skeletal proportions and dental positions remain unaffected. Consequently, excess body weight selectively enhances sagittal jaw development during adolescent growth periods.
Current research shows no significant difference in cervical vertebral maturation stages or hand-wrist skeletal maturity indices between adolescents with normal and increased weight. Although linear bone dimensions expand substantially, biological maturation stages progress similarly, indicating that metabolic signaling directly drives skeletal expansion rather than advancing pubertal timing.
Salivary adiponectin acts as an independent negative predictor of both maxillary and mandibular lengths. Adiponectin regulates bone metabolism, chondrocyte proliferation, and local inflammation. Therefore, lower adiponectin levels observed during excess adiposity remove natural physiological suppression, which subsequently permits increased condylar growth and accelerated mandibular elongation.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Always consult a qualified healthcare provider for diagnosis and treatment of any health condition. The views and opinions expressed in this article are those of the authors and do not necessarily reflect the official policy or position of any affiliated organization. Refer to the latest local and national guidelines for clinical practice.
References
Michelogiannakis D et al. Jaw Dimensions, Skeletal Maturation, and Salivary Hormones in Adolescents With Normal and Increased Body Mass Index: A Cross-Sectional Study. Orthod Craniofac Res. 2026 Oct 04. doi: 10.1111/ocr.70191. PMID: 42829963.
Olszewska K. Craniofacial morphology in overweight and obese orthodontic adolescent patients. J Pre Clin Clin Res. 2017;11(1):42-45.
Karaman A, Genc E. Evaluation of facial soft-tissue values and craniofacial morphology in obese adolescent patients with different skeletal classes. APOS Trends Orthod. 2021;11:270-278.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A cross-sectional study demonstrates that increased BMI in adolescents significantly enhances mandibular length and alters salivary adipokines like adiponectin and resistin, providing novel insights into craniofacial growth and orthodontic planning.
Today
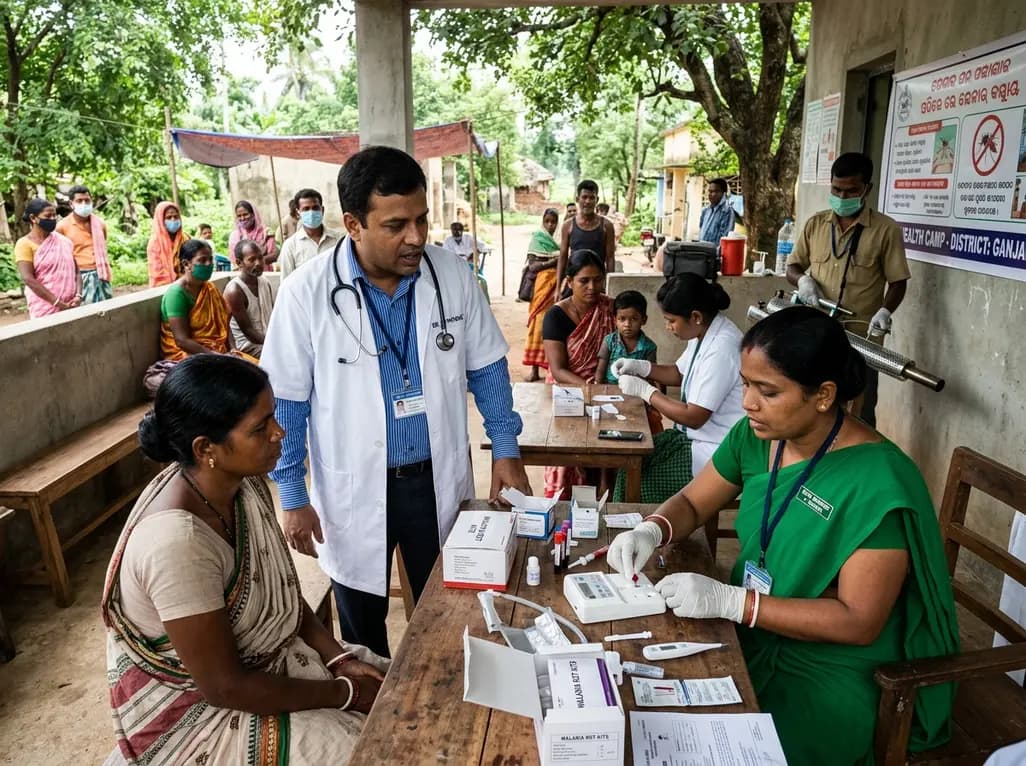
Following 37,899 reported cases and 9 deaths, Odisha has scaled up active case detection, rapid diagnostic testing, and vector control across high-burden districts. Here is a comprehensive clinical breakdown of the state's aggressive containment protocols, diagnostic pathways, and targeted field management.
Today
A retrospective study of 86,012 pregnancies demonstrates that size-selective cfDNA enrichment boosts mean fetal fraction to 18.88% and achieves a 59.20% PPV for fetal copy number variants. However, 85.83% of CNVs showed size discrepancies, underscoring the mandatory role of confirmatory microarray testing.
Today
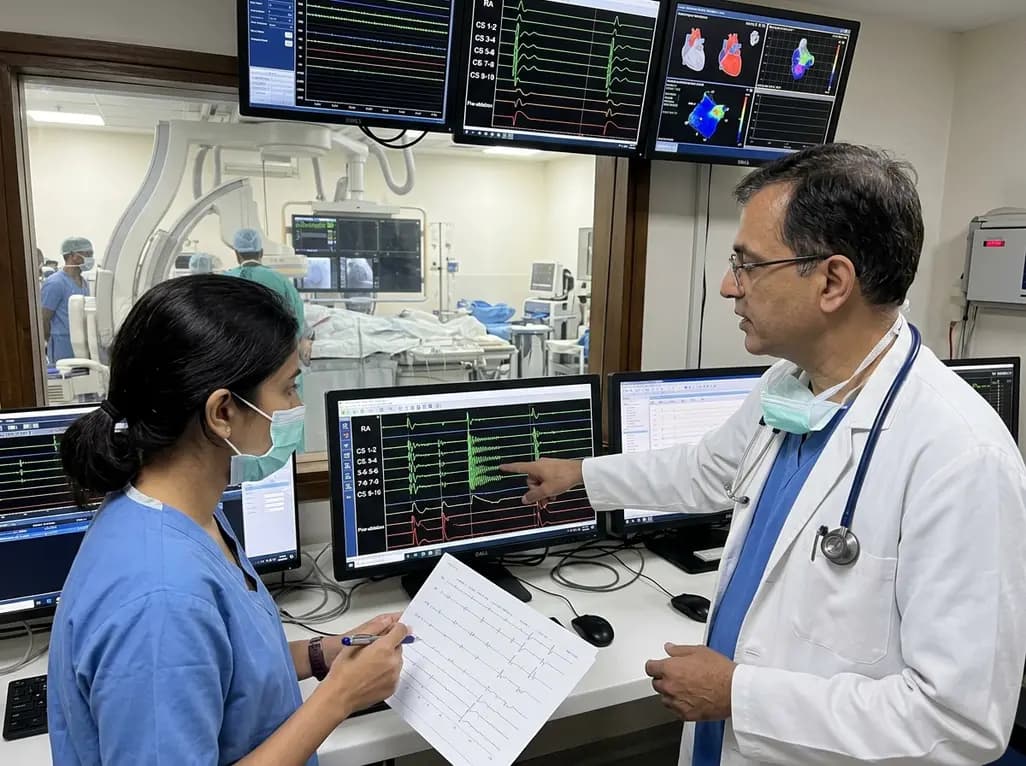
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today
