

Loading, please wait...
Loading, please wait...
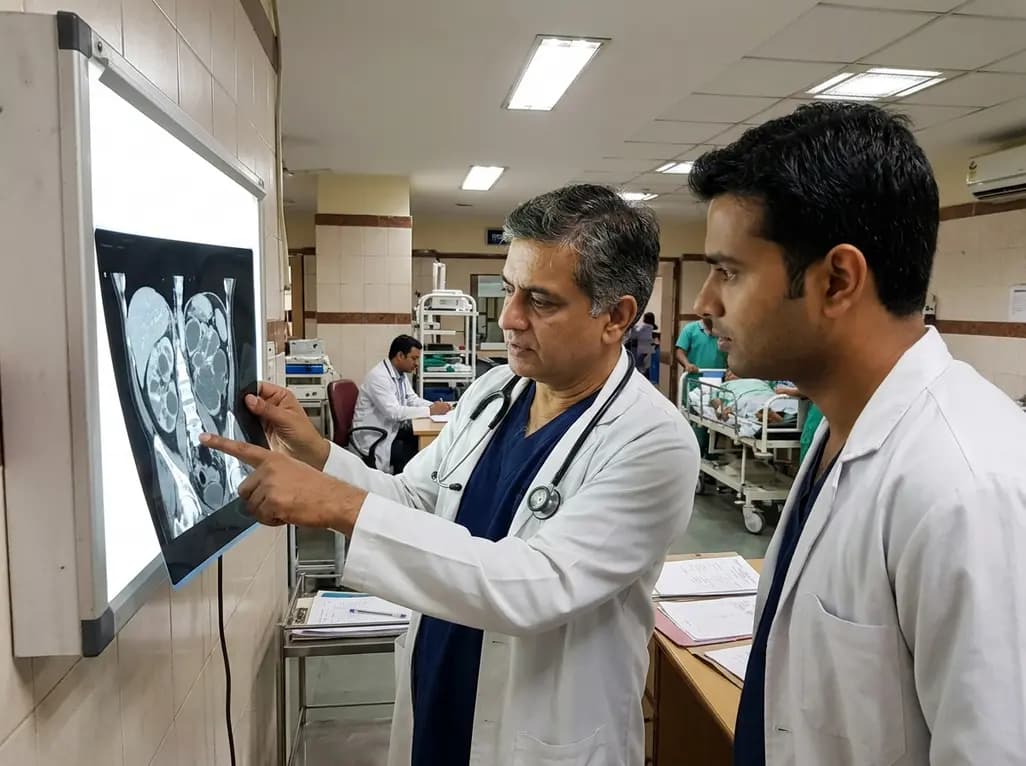
Managing end-stage renal disease in autosomal dominant polycystic kidney disease requires careful multidisciplinary surgical planning. Clinicians frequently debate the necessity and exact timing of native nephrectomy in ADPKD candidates awaiting kidney transplantation. Massive nephromegaly often compresses pelvic vessels and reduces the physical space required for graft implantation. Furthermore, chronic cyst-related infections, intractable pain, and hematuria frequently worsen recipient morbidity. However, removing large native kidneys introduces surgical complexity and substantial hemodynamic stress. Therefore, transplant teams must objectively weigh the procedural morbidity of nephrectomy against the functional benefits of graft preservation.
Surgical removal of enlarged polycystic kidneys remains a selective intervention rather than an empirical mandate. Recent retrospective data show that lack of intra-abdominal space represents the predominant indication for native nephrectomy before graft implantation. Marked nephromegaly frequently displaces bowel loops and encroaches upon the iliac fossa, thereby impeding vascular anastomosis. Consequently, surgeons must clear anatomical space to accommodate the allograft safely. In addition, recurrent cyst infections serve as another common indication for surgical extirpation. Intracystic abscesses rarely resolve with conservative antibiotic regimens alone because antimicrobial penetration into sealed cystic structures remains notoriously poor. Therefore, leaving infected parenchyma in place poses a grave risk for systemic sepsis under post-transplant immunosuppression. Severe intractable flank pain and recurrent intracystic hemorrhage also justify native nephrectomy in selected patients. Furthermore, sudden cyst rupture can induce significant hypovolemia and persistent microcytic anemia, which severely compromises transplant candidacy. Historically, clinicians feared occult malignant transformation within complex cysts. Fortunately, modern pathological analyses reveal that true renal neoplasms remain exceedingly rare in these patients. Thus, space restriction, persistent sepsis, and refractory mechanical pain remain the principal triggers guiding operative intervention.
Determining the optimal chronological window for native nephrectomy significantly influences recipient outcomes and graft longevity. In clinical practice, most procedures occur before transplantation as a staged operation. Pre-transplant nephrectomy guarantees an unobstructed pelvic field, allowing subsequent graft implantation without spatial limitation. Moreover, staging the operations prevents prolonged anesthesia times and diminishes the cumulative physiological trauma of simultaneous surgery. However, pre-transplant nephrectomy completely eliminates residual urine output, which forces patients to become entirely dialysis-dependent. Consequently, these individuals often experience difficult fluid restriction and accelerated cardiovascular calcification during their waitlist period. In contrast, postponing nephrectomy until after renal transplantation preserves endogenous erythropoietin production and residual fluid excretion. Nevertheless, performing post-transplant nephrectomy presents distinct surgical hazards. The surgical team must operate adjacent to a functional, immunosuppressed allograft, where accidental vascular injury or severe hypotension can jeopardize graft perfusion. Clinical data show that post-transplant nephrectomy is primarily reserved for delayed native kidney complications, such as unresolving pyelonephritis or persistent gross hematuria. Therefore, while pre-transplant intervention offers anatomical certainty for graft placement, it demands vigilant dialysis management while awaiting transplantation.
Transplant teams must carefully decide between unilateral and bilateral organ removal when planning native nephrectomy. Bilateral pre-transplant nephrectomy represents the most common historical approach in centers managing extreme nephromegaly. Performing bilateral resection creates ample bilateral iliac exposure, which allows flexible placement in either the right or left fossa. In addition, bilateral removal definitively eliminates future cyst infections and polycystic hemorrhage in both native kidneys. However, bilateral nephrectomy demands extensive dissection through large midline incisions or bilateral flank approaches. As a result, bilateral procedures carry substantial surgical trauma, prolonged operating times, and significant blood loss. Conversely, unilateral nephrectomy provides a less invasive alternative that targets only the ipsilateral side intended for graft implantation. By removing only the symptomatic or larger kidney, surgeons minimize intraoperative dissection and preserve contralateral residual filtration. Nonetheless, retaining a diseased contralateral kidney carries ongoing risks of secondary infection or progressive cyst enlargement. Transplant surgeons must therefore evaluate anatomical scans meticulously, choosing bilateral resection when massive volume expansion spans both sides and unilateral excision when localized space creation suffices.
Native nephrectomy carries substantial perioperative morbidity that requires proactive surgical and medical mitigation. Data confirm that postoperative complications occur frequently, particularly among patients undergoing bilateral pre-transplant procedures. Severe intraoperative or postoperative bleeding requiring blood transfusion represents one of the most prevalent adverse events. Dissecting massive polycystic kidneys often involves dividing numerous dilated collateral vessels and separating dense perinephric adhesions. In addition, patients frequently develop postoperative retroperitoneal fluid collections, including hematomas and seromas, which occasionally require percutaneous drainage. Surgical site complications, such as incisional hernias and wound dehiscence, also occur due to extensive abdominal wall incisions and poor muscle tone. Moreover, patients requiring reintervention experience prolonged hospitalizations and delayed rehabilitation. Despite these formidable operative hazards, comparative analyses indicate that overall complication rates between different staged surgical strategies remain statistically comparable. Histopathological examinations provide reassuring prognostic data, as true malignant degeneration into renal cell carcinoma remains remarkably rare in non-screened cohorts. Consequently, clinicians can counsel candidates that nephrectomy addresses compressive symptoms and infection risks without an overwhelming likelihood of underlying occult cancer.
In Indian transplant centers, tailoring the surgical approach to individual socioeconomic, anatomical, and logistic factors is paramount. Unlike Western centers with extensive deceased donor waitlists, living-related donor transplantation dominates the Indian landscape. Consequently, clinicians can accurately schedule native nephrectomy relative to planned living donor donation dates. Performing staged pre-transplant nephrectomy demands reliable, high-quality hemodialysis during the inter-surgical interval. However, in resource-limited rural or semi-urban settings, severe anuria increases the risk of life-threatening pulmonary edema and fluid overload between dialysis sessions. Therefore, Indian nephrologists must carefully determine whether staged unilateral nephrectomy or simultaneous unilateral nephrectomy provides a safer alternative. Modern laparoscopic and robotic-assisted techniques have gained significant momentum across major Indian tertiary transplant hospitals. These minimally invasive modalities markedly diminish postoperative wound infections, reduce incisional hernia rates, and shorten recovery intervals. Furthermore, comprehensive preoperative contrast-enhanced imaging helps surgeons map pelvic dimensions accurately. By restricting nephrectomy strictly to symptomatic candidates or those with indisputable pelvic crowding, clinicians avoid unnecessary procedural morbidities while safeguarding the incoming living donor allograft.
Clinicians strictly recommend native nephrectomy before transplantation when massive nephromegaly physically obstructs the iliac fossa, preventing safe vascular anastomosis and graft placement. Furthermore, pre-transplant extirpation is mandatory for persistent or recurrent upper urinary tract infections that fail antimicrobial therapy, severe chronic refractory flank pain, and recurrent debilitating cyst hemorrhage. In the absence of these specific mechanical or symptomatic indications, routine pre-transplant nephrectomy is generally avoided to preserve residual urine output and native erythropoiesis.
Bilateral pre-transplant nephrectomy carries substantial perioperative morbidity, including significant vascular injury and hemorrhage requiring blood transfusion. Additionally, patients frequently develop retroperitoneal fluid collections, hematomas, and post-surgical incisional hernias due to large abdominal incisions. Removing both native kidneys abruptly produces complete anuria, which elevates the risk of severe interdialytic volume overload and hyperkalemia. Consequently, patients require stringent dietary restrictions and intensive hemodialysis monitoring while awaiting allograft implantation to prevent cardiovascular complications.
Yes, deferring native nephrectomy until after kidney transplantation represents a safe, viable strategy when native kidneys do not compromise graft space. This approach preserves residual native kidney function, avoids complete anuria before transplantation, and simplifies early post-transplant fluid balance. However, post-transplant nephrectomy is strictly reserved for patients developing persistent cyst infections, refractory hematuria, or unmanageable compressive symptoms, because operating near an immunosuppressed functional allograft carries procedural risks to graft perfusion.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals must exercise independent clinical judgment and correlate findings with specific patient presentations. Dosage, indications, and surgical strategies should be verified against standard operating procedures, institutional policies, and manufacturer guidelines. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Evaluating native nephrectomy in ADPKD kidney transplant candidates reveals that spatial limitation, cyst infection, and pain drive surgical decisions. Staged bilateral nephrectomy remains common but carries bleeding and hernia risks, highlighting the importance of tailored clinical management.
last month

Psoriasis is a chronic systemic inflammatory condition requiring comprehensive clinical intervention beyond topical care. Explore evidence-based insights into systemic comorbidities, patient quality of life, and targeted biologic options such as IL-23 inhibitors for sustained disease control.
Today

A nationwide cohort study published in JAMA Pediatrics reveals that maternal exposure to wildfire fine particulate matter, especially in late pregnancy, is linked to an elevated risk of childhood autism. Clinicians should evaluate ambient air quality risks and provide proactive protective counseling to mothers.
Today

Annual health checks only offer static snapshots. Real-world evidence from 2.1 million insured Indians reveals that tracking dynamic biomarker trends over time enables clinicians to spot evolving cardiometabolic risks early, reverse borderline pathology, and deliver tailored preventive interventions.
Today

Modern 3D anthropometry reveals that pediatric leg growth ceases years before spinal elongation, exposing the clinical illusion of the classical Anderson-Green model. Learn how segmental growth dissociation improves surgical timing for epiphysiodesis in adolescent leg length discrepancy.
2 days back

With packaged goods giant HUL backing FSSAI's proposed front-of-pack red warning labels for foods high in fat, sugar, and salt, India takes a major step toward curbing non-communicable diseases. Learn how clearer nutrition disclosures empower clinicians, inform consumer choices, and drive dietary reform.
Today
