

Loading, please wait...
Loading, please wait...
Penetrating craniocerebral injuries represent some of the most complex, time-critical emergencies encountered in modern trauma surgery and neurocritical care. Recent wartime data from front-line neurotrauma centers in Ukraine have illuminated critical pathways for improving survival in these devastating injuries. Modern warfare produces high-velocity ballistic impacts and blast fragmentation that frequently damage both the cerebral parenchyma and the cerebral vasculature. Historically, clinicians prioritized immediate open debridement and decompressive craniectomy, often overlooking occult vascular trauma until catastrophic hemorrhage or pseudoaneurysm rupture supervened. However, modern multimodal workflows that combine rapid diagnostic angiography with tandem neurointerventional and microneurosurgical interventions are shifting this paradigm. By identifying vascular disruption early, neurotrauma teams can stabilize fragile lesions before proceeding to definitive cranial debridement. This coordinated approach prevents intraoperative exsanguination, mitigates delayed ischemic stroke, and optimizes tissue preservation. In civilian and conflict settings alike, establishing standardized pathways for vascular screening directly addresses preventable secondary brain injury. Consequently, trauma centers worldwide can adapt these wartime insights to elevate standard neurotrauma protocols.
Penetrating projectiles cause direct mural lacerations, arterial transections, and severe blast-induced shear forces along the intracranial arterial tree. Consequently, patients frequently develop traumatic intracranial aneurysms, pseudoaneurysms, direct carotid-cavernous fistulas, and traumatic dural arteriovenous fistulas. In high-energy trauma, traumatic pseudoaneurysms account for the majority of these arterial lesions because the projectile disrupts the internal elastic lamina and adventitia. Unlike true congenital aneurysms, these traumatic lesions lack a true epithelialized muscular wall, making them exceptionally fragile and prone to unpredictable rupture. Furthermore, high-velocity fragments can create abnormal arteriovenous shunts that compromise cerebral perfusion and produce severe venous hypertension. When bone fragments breach adjacent structures, such as the sphenoid or ethmoid sinuses, vascular lesions can bleed massively into the upper airway or orbit. Clinicians must maintain an elevated index of suspicion because neurological deficits may initially appear attributable solely to parenchymal destruction. Therefore, recognizing the broad pathological spectrum of vascular disruptions remains essential for every frontline trauma team dealing with complex ballistic head trauma.
Digital subtraction angiography remains the gold standard for detecting traumatic neurovascular pathology following penetrating cranial trauma. Although non-invasive computed tomography angiography provides rapid initial screening, small vessel dissections, distal pseudoaneurysms, and low-flow arteriovenous fistulas can easily escape detection on initial cross-sectional scans. Therefore, implementing early invasive digital subtraction angiography within hours of injury allows definitive vascular mapping before massive cerebral edema develops. Rapid diagnostic catheterization precisely delineates the projectile trajectory, identifies active contrast extravasation, and demonstrates collateral cross-filling pathways across the circle of Willis. In addition, early angiography provides crucial baseline visualization that guides both endovascular planning and open surgical skull base reconstruction. Because traumatic aneurysms can evolve rapidly over the initial 24 to 72 hours, early invasive imaging establishes a reliable roadmap for urgent intervention. When neurotrauma teams integrate immediate catheter angiography into their routine resuscitation protocols, they drastically reduce diagnostic delays that could otherwise lead to fatal re-bleeding episodes.
The contemporary management of wartime neurovascular trauma increasingly relies on hybrid neurointervention preceding or complementing open cranial surgery. Endovascular embolization offers targeted, minimally invasive occlusion of injured vessels or aneurysm sacs without adding mechanical trauma to already swollen brain parenchyma. Interventionalists employ microcoils, liquid embolic agents such as onyx or n-butyl cyanoacrylate, and covered stents to isolate bleeding vessels effectively. Once endovascular stabilization secures the fragile vascular lesion, neurosurgeons can safely execute open craniotomy, bullet tract debridement, and hematoma evacuation with significantly reduced risk of uncontrollable intraoperative hemorrhage. In many instances, immediate transition from the interventional radiology suite directly to the operating theater optimizes operating room logistics and patient stability. Moreover, parent vessel sacrifice or flow diversion can be customized based on instantaneous assessment of collateral circulation during catheterization. Combining these endovascular and open microsurgical techniques ensures that surgeons address both intracranial mass effect and high-risk vascular injuries simultaneously.
Penetrating head trauma frequently involves extensive comminuted fractures traversing the anterior skull base and paranasal sinuses. When projectiles violate the sphenoid, frontal, or ethmoid air cells, they create direct communications between the intracranial space and contaminated nasal cavities. Consequently, neurosurgeons must meticulously reconstruct the skull base to prevent persistent cerebrospinal fluid fistulas, tension pneumocephalus, and ascending intracranial infections. Autologous tissue grafts, including vascularized pericranial flaps, fascia lata, and temporalis muscle, serve as the primary reconstructive substrate in these contaminated wound beds. Using autologous tissue markedly reduces infection risk compared to synthetic reconstructive materials in the presence of blast debris and active sinus contamination. In addition, surgeons must carefully seal exposed neurovascular structures from adjacent sinus mucosal edges to prevent late pseudoaneurysm formation or erosion into aerated cavities. Meticulous multilayered closure combined with prolonged broad-spectrum antimicrobial coverage ultimately secures durable cranial integrity in severe penetrating trauma.
Evidence from frontline clinical experience demonstrates that rapid multimodal management directly translates to improved functional recovery and low mortality. Despite presenting with low Glasgow Coma Scale scores, a high percentage of patients achieve favorable functional independence on the Glasgow Outcome Scale. The primary driver of delayed mortality in surviving patients remains refractory post-traumatic cerebral vasospasm and secondary ischemic injury. Blast injuries induce intense, prolonged vasospasm through blood breakdown products, mechanical stretch, and severe neuroinflammatory cascades. Therefore, aggressive neurointensive care monitoring, transcranial Doppler surveillance, and targeted hemodynamic management are vital components of postoperative care. Translating these military insights into civilian practice underscores the importance of developing integrated hybrid trauma suites and rapid neurovascular response protocols. When emergency departments, interventional radiologists, and neurosurgeons collaborate seamlessly, survival rates and neurological outcomes improve substantially across all categories of severe penetrating neurotrauma.
Clinicians should perform invasive digital subtraction angiography as early as possible following initial hemodynamic stabilization and computed tomography scanning. Early imaging identifies occult arterial pseudoaneurysms, lacerations, and arteriovenous fistulas, allowing endovascular stabilization before definitive open surgical debridement or before fatal delayed hemorrhage occurs.
Endovascular options include endosaccular coiling, parent vessel occlusion with liquid embolics or microcoils, and covered stent placement. Flow-diverting stents and parent artery sacrifice are selected based on the lesion morphology, parent vessel caliber, patient anticoagulation tolerance, and the adequacy of collateral intracranial blood flow.
Autologous tissue, such as vascularized pericranium or fascia lata, provides superior resistance against bacterial infection in contaminated wound beds. Ballistic and blast injuries introduce foreign debris and breach paranasal sinuses, making synthetic implants prone to infection, extrusion, and persistent cerebrospinal fluid leakage.
Disclaimer: This content is for informational and educational purposes only and should not replace clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Wartime data demonstrates that early digital subtraction angiography and multimodal endovascular-neurosurgical interventions significantly improve survival and functional outcomes in penetrating craniocerebral injuries with concomitant vascular trauma.
4 weeks back
Following 37,899 reported cases and 9 deaths, Odisha has scaled up active case detection, rapid diagnostic testing, and vector control across high-burden districts. Here is a comprehensive clinical breakdown of the state's aggressive containment protocols, diagnostic pathways, and targeted field management.
Today

Endometriosis affects millions of women across India, yet diagnostic delays frequently exceed five years. Recent multi-centre genomic research has identified 21 novel genetic regions, notably on chromosome 13, establishing crucial population-specific insights to transform clinical screening and therapeutic strategies.
Today
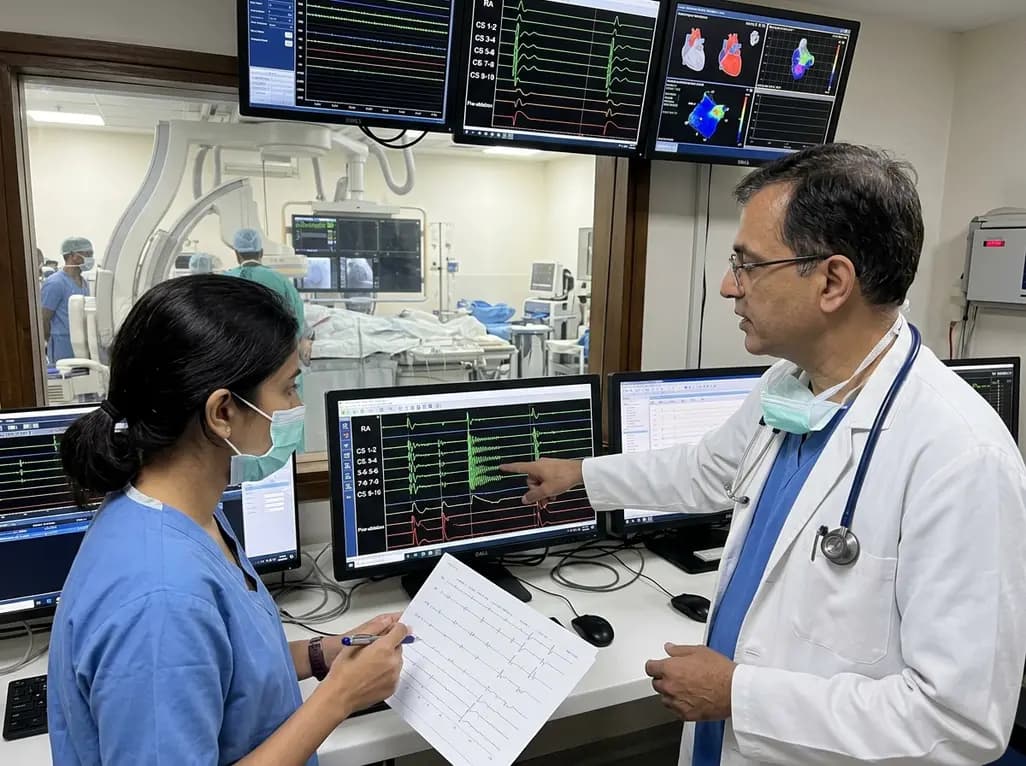
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today
Discover how to identify superimposed entrapment neuropathy in diabetic patients. This review details clinical evaluation, surgical decompression evidence, and a structured algorithm for primary care referrals to prevent ulcers and preserve limb function.
Yesterday
