

Loading, please wait...
Loading, please wait...

Endometriosis presents a major diagnostic dilemma for clinicians across India. Affecting nearly fifty million Indian women, this chronic condition frequently eludes timely clinical recognition. Recent nationwide research has illuminated the underlying endometriosis genetic risk, providing crucial biological insights into this complex disease. Consequently, this scientific milestone creates new avenues for non-invasive risk stratification and tailored gynecological intervention.
For decades, clinicians recognized familial clustering during patient evaluations. However, doctors lacked population-specific genomic data to substantiate these hereditary patterns. This landmark multi-centre investigation now bridges that long-standing scientific gap. Furthermore, the findings promise to shorten diagnostic pathways significantly.
Globally, endometriosis affects roughly ten percent of reproductive-age women. In India, the clinical burden is exceptionally high, accounting for nearly twenty percent of worldwide cases. Despite this massive prevalence, patients routinely endure excruciating diagnostic intervals of three to seven years. During this prolonged delay, women often suffer from severe dysmenorrhea, chronic pelvic pain, and deep dyspareunia. Moreover, the disorder represents a major cause of female subfertility.
Unfortunately, societal taboos and the normalization of debilitating menstrual cramps hinder early presentation. When patients finally seek specialized care, the disease has frequently progressed to advanced stages. Deep Infiltrative Endometriosis poses severe surgical challenges, invading the rectum, bladder, ureters, and pelvic nerves. Operating surgeons must perform delicate retroperitoneal dissections, which carry risks of visceral injury and denervation. In addition, chronic pelvic inflammation promotes ovarian endometriomas that compromise ovarian reserve. Therefore, identifying accurate molecular markers before irreversible anatomical distortion occurs remains an urgent clinical priority.
To evaluate endometriosis genetic risk accurately, the Indian Council of Medical Research organized a nationwide consortium. Investigators established the Endometriosis Clinical and Genetic Research in India network across eighteen tertiary academic and private centers. This ambitious initiative recruited 2,523 women from diverse geographic territories and ancestral backgrounds nationwide.
The research protocol enforced stringent phenotyping criteria. Clinicians categorized participants through laparoscopic confirmation or rigorous clinical control protocols. Tertiary centers, including AIIMS Jodhpur and AIIMS Raipur, contributed sizable cohorts of surgically verified cases. Furthermore, investigators collaborated closely with international geneticists from the University of Queensland. This partnership allowed the team to conduct high-density Genome-Wide Association Studies comparing Indian patient profiles against global databases.
Historically, reproductive genomic databases focused almost entirely on cohorts of European ancestry. Consequently, reproductive specialists lacked validated molecular tools suitable for South Asian women. This multi-centre effort directly corrects that historical underrepresentation. By gathering detailed clinical phenotypes alongside blood samples, investigators established the first comprehensive molecular biobank specifically designed for Indian gynecological research.
The genome-wide association study yielded groundbreaking insights into disease susceptibility. Specifically, researchers discovered 21 suggestive novel genetic regions uniquely associated with endometriosis in Indian cohorts. Among these newly identified signals, the most robust statistical association localized to chromosome 13, adjacent to the LINC00415 and SHISA2 locus.
Simultaneously, researchers observed significant overlap with loci previously cataloged in Western studies. For instance, the team confirmed known genetic signals around the WNT4 and CDKN2B-AS1 regulatory regions. These shared molecular signatures affirm that core biological pathways govern endometriosis across diverse human populations. Nevertheless, the study revealed significant population-specific allele frequencies that distinguish Indian women from other ancestral cohorts.
Additionally, the research team analyzed polygenic risk scores derived from European populations. While these risk scores demonstrated partial predictive validity, they missed distinct local susceptibility markers. The newly identified genetic loci appear to influence steroid hormone metabolism, peritoneal immune evasion, and cell proliferation pathways. Therefore, these molecular findings lay an empirical foundation for dissecting how specific genetic variants orchestrate chronic pelvic inflammation.
Currently, diagnostic laparoscopy remains the gold standard for definitive confirmation of peritoneal implants. However, surgical intervention involves general anesthesia, procedural risks, and significant financial expenditure. Because non-invasive diagnostic tools remain limited, primary care physicians often hesitate to refer patients promptly. The discovery of these twenty-one genetic loci offers tremendous promise for developing non-invasive molecular assays.
In the near future, clinicians may utilize peripheral blood panels to compute individualized genomic risk profiles. When combined with specialized transvaginal sonography and magnetic resonance imaging, genetic screening could identify high-risk adolescents before irreversible pelvic fibrosis develops. Furthermore, earlier recognition allows for timely medical suppression using combined oral contraceptives, progestins, or GnRH modulators. Consequently, practitioners can arrest disease progression, preserve fallopian tubal patency, and optimize ovarian reserve before extensive endometriomas form.
Although these findings require validation through larger replication cohorts, they represent a decisive shift toward precision gynecology. Primary care physicians and gynecologists can soon utilize these emerging biomarkers to stratify symptomatic women. Thus, clinical teams will no longer normalize pelvic distress.
Addressing severe disease manifestations requires cohesive, multidisciplinary medical infrastructure. Deep Infiltrative Endometriosis demands specialized surgical units with high-volume pelvic expertise. AIIMS Jodhpur has emerged as a national leader in this domain, completing over 150 complex reconstructive surgeries since 2018. To build upon this surgical success, institutional leaders are establishing a dedicated Centre for Advanced Research for endometriosis.
This advanced facility aims to unite minimally invasive gynecologic surgeons, colorectal specialists, urologists, geneticists, and pain rehabilitation experts under one collaborative umbrella. When complex disease infiltrates the bowel muscularis or ureteral adventitia, joint surgical teams achieve complete lesion excision while preserving visceral function. Moreover, integrating genetic diagnostics into tertiary surgical referral networks enables longitudinal follow-up of postoperative recurrence patterns.
Ultimately, translating molecular insights into standard hospital practice requires coordinated national investments. Institutions like AIIMS Jodhpur and the ICMR network provide the clinical blueprint for regional referral hubs throughout India. By merging cutting-edge genomic research with meticulous surgical excision, Indian healthcare institutions can substantially alleviate chronic morbidity. Hence, patients will receive compassionate, evidence-based care.
Q1: Why does endometriosis often take three to seven years to diagnose in India?
Diagnostic delays occur because societal norms frequently dismiss debilitating menstrual pain as ordinary discomfort. Additionally, early peritoneal lesions do not appear on standard pelvic ultrasounds. Because definitive confirmation historically required surgical laparoscopy, primary care physicians often defer specialized referral. A lack of validated, non-invasive molecular biomarkers has further prolonged this diagnostic window. Identifying population-specific genetic markers provides clinicians with objective tools to suspect and investigate the condition much earlier.
Q2: What is the clinical significance of the newly identified chromosome 13 locus?
The landmark Indian study discovered its strongest genomic signal on chromosome 13, located near the LINC00415 and SHISA2 genetic region. This locus represents a population-specific susceptibility marker that influences cellular proliferation and tissue signaling pathways. While earlier Western studies highlighted other chromosomes, this finding demonstrates unique genetic architecture in Indian women. Understanding this specific region helps researchers uncover unique pathological mechanisms and design targeted diagnostic assays tailored specifically for South Asian populations.
Q3: How will genetic findings improve the management of Deep Infiltrative Endometriosis?
Deep Infiltrative Endometriosis causes severe tissue invasion into the rectum, bladder, and pelvic nerves, demanding high-precision surgery. Early genetic risk screening enables physicians to identify vulnerable women before deep lesions develop. Consequently, gynecologists can initiate targeted medical therapy promptly, slowing disease progression and preserving organ function. Furthermore, multidisciplinary centers can monitor genetically predisposed individuals closely, optimizing surgical timing and reducing the risk of catastrophic visceral complications or postoperative pelvic recurrence.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Endometriosis affects millions of women across India, yet diagnostic delays frequently exceed five years. Recent multi-centre genomic research has identified 21 novel genetic regions, notably on chromosome 13, establishing crucial population-specific insights to transform clinical screening and therapeutic strategies.
Today
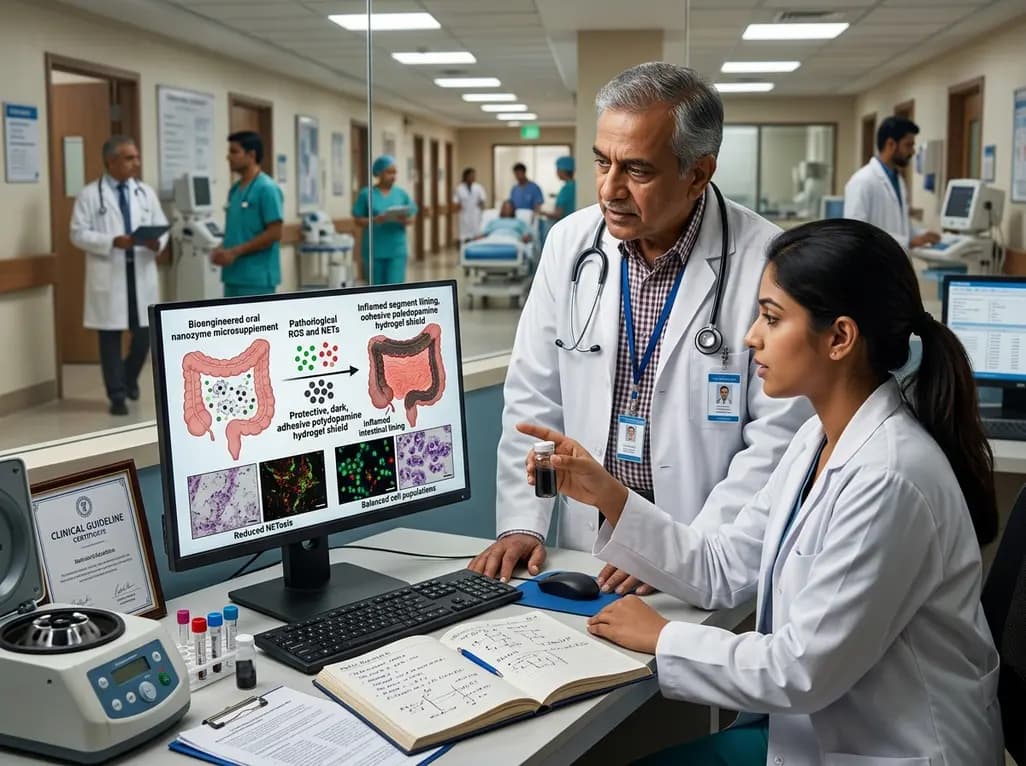
A bioengineered oral nanozyme microsupplement converts pathological ROS into a protective polydopamine hydrogel shield. By curbing neutrophil extracellular traps and balancing T cells, this platform outperforms standard 5-ASA in preclinical colitis models, opening new paths for sustained remission.
Today
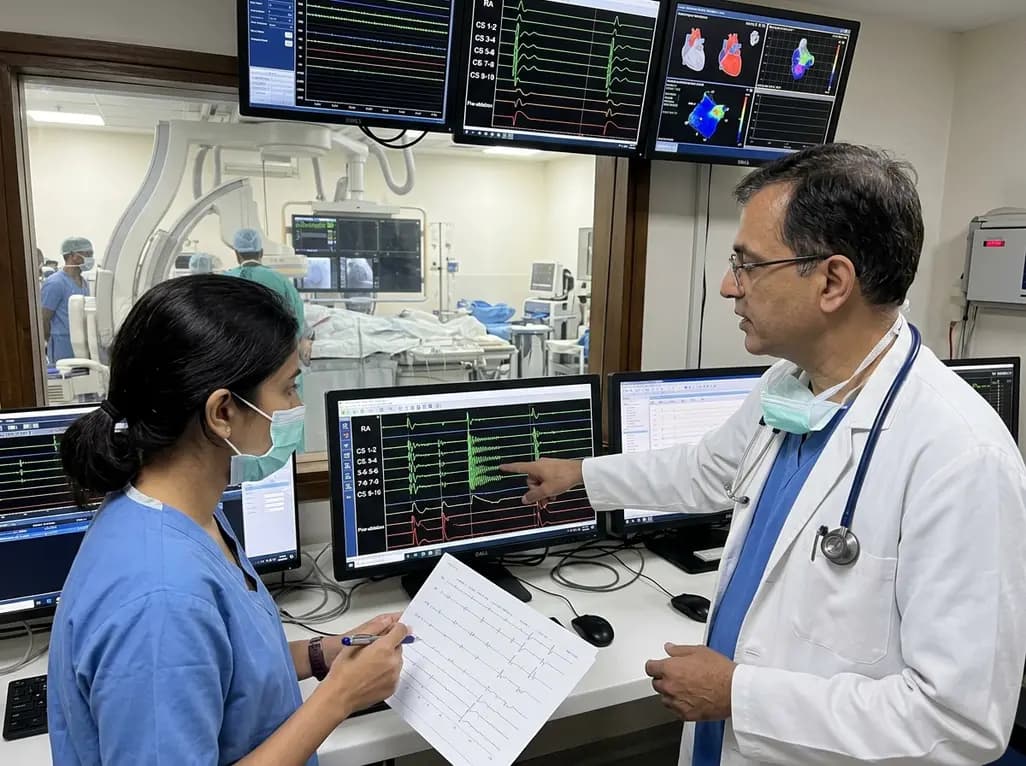
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today

A breakthrough study leverages natural language processing to accurately identify incident medication-related osteonecrosis of the jaw and track antiresorptive drug holidays from clinical narratives in electronic health records, advancing osteoporosis pharmacovigilance and dental safety.
Yesterday
