

Loading, please wait...
Loading, please wait...
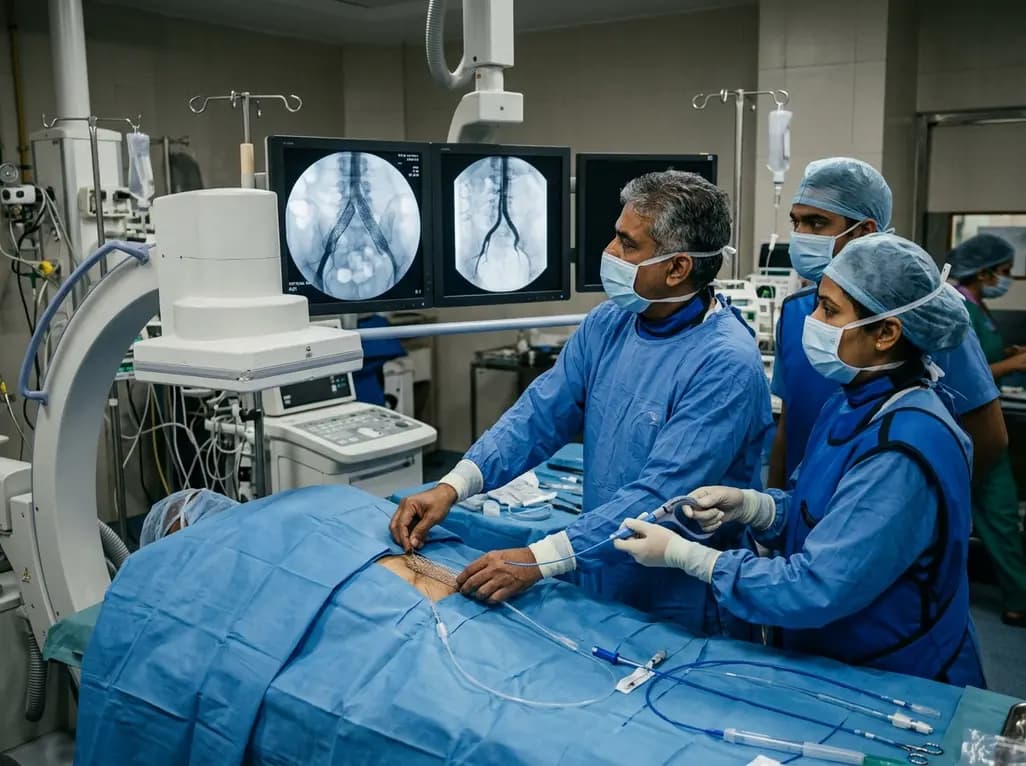
May-Thurner syndrome stenting has transformed the therapeutic paradigm for patients suffering from non-thrombotic iliofemoral venous outflow obstruction. In this anatomical condition, the right common iliac artery persistently compresses the left common iliac vein against the lumbar spine. Over time, repetitive arterial pulsations produce intraluminal fibrotic bands and obstructive spurs. Consequently, patients develop severe venous hypertension, refractory lower limb swelling, and painful venous stasis ulcers. Conservative therapy frequently fails because elastic vessel recoil resists balloon angioplasty alone. Therefore, endovascular reconstruction with self-expanding metal stents provides the definitive structural solution.
Clinicians widely utilize the braided stainless steel Wallstent for iliocaval reconstruction due to its high radial force and flexibility. However, this braided architecture introduces notable biomechanical dynamics during delivery. When interventionalists deploy the device, its longitudinal dimensions change substantially. Operators frequently encounter unpredictable friction and vessel resistance within the diseased segment. Accordingly, treating physicians must understand these intrinsic mechanical properties to optimize procedural accuracy. Furthermore, recognizing predictable physical forces allows specialists to maintain procedural control.
During endovascular procedures, the braided design of the Wallstent produces substantial longitudinal foreshortening upon deployment. As the stent diameter expands against the venous wall, its total length contracts dramatically. In clinical practice, operators consistently observe this phenomenon across virtually every case. In addition, device slipping frequently occurs as the stent interacts with tortuous venous segments and rigid spurs. Rather than treating these events as adverse complications, interventionalists should classify them as predictable mechanical actions.
Consequently, failing to anticipate foreshortening can lead to incomplete lesion coverage or geographic miss. Operators must therefore account for this length reduction during pre-procedural planning. Specifically, accurate sizing and multiplanar venography help teams estimate the exact degree of shortening. Interventionalists generally select a stent diameter that oversizes the reference vein by ten to twenty percent. Furthermore, the operator should initiate deployment approximately three centimeters cranial to the intended landing zone. This cranial starting point compensates for shortening as the constrained wires expand. When the stent slips slightly, controlled release techniques permit prompt repositioning. Thus, anticipation ensures precise ostial coverage.
Although modern deployment techniques achieve high procedural success, complications can occasionally arise. In a prospective cohort evaluating forty-one stent deployments, proximal stent compression occurred in 5.3% of patients. Furthermore, cranial and caudal stent migrations each occurred in 2.6% of cases. Stent migration represents an uncommon yet serious event that demands immediate recognition. It often stems from a mismatch between vessel diameter and device caliber. In addition, severe dynamic pulsatility from the overlying right iliac artery can dislodge an unstable stent.
Fortunately, interventional teams can manage migration events entirely through endovascular approaches without open surgical conversion. For instance, operators utilize endovascular snares to capture the displaced stent securely. Clinicians can then reposition the device within the inferior vena cava or pull it into a stable landing zone. In caudal migration, the interventionalist can deploy a second overlapping stent proximally to secure the lesion. Recent data demonstrated successful endovascular management entirely within the vena cava. Consequently, familiarity with endovascular rescue tools provides operators with confidence to handle rare displacement events efficiently.
Achieving consistent outcomes during iliocaval reconstruction requires strict adherence to standardized deployment steps. First, operators should utilize multiplanar venography to delineate the exact margins of the compressed vein. Intravascular ultrasound can also measure the lumen accurately and identify internal webs. Second, clinicians must position the proximal edge of the stent so that it extends several millimeters into the inferior vena cava. Complete lesion coverage across the iliocaval junction prevents recurrent ostial narrowing. However, operators must avoid excessive extension into the vena cava lumen, which could compromise contralateral iliac flow.
Third, balloon post-dilatation demands careful execution. Interventionalists should perform post-stent dilatation in a strict distal-to-proximal sequence. Dilating from the peripheral vein toward the inferior vena cava prevents device displacement into the central circulation. Moreover, this direction allows the stent to anchor firmly against the distal vein wall before expanding the proximal stenosis. High-pressure non-compliant balloons help overcome rigid spurs without tearing the venous wall. Therefore, combining proper sizing, controlled release, precise positioning, and sequential post-dilatation ensures durable structural recanalization.
Despite mechanical nuances during deployment, endovenous stenting for non-thrombotic May-Thurner syndrome delivers exceptional clinical outcomes. In a recent cohort, investigators achieved one hundred percent technical success across all thirty-eight patients. More importantly, symptomatic relief followed rapidly after stent expansion. Visual analog scale pain scores improved completely or partially in all symptomatic individuals. Patients experienced prompt reduction in lower extremity heaviness, chronic edema, and venous claudication.
Furthermore, the intervention produced remarkable benefits for patients with advanced chronic venous disease. All venous stasis ulcers healed completely, with a mean healing duration of only 2.5 months. During the twelve-month follow-up period using duplex ultrasonography, researchers observed no cases of stent thrombosis or recurrent occlusion. In addition, no patient required secondary reintervention during the one-year surveillance window. These outstanding findings confirm that mechanical challenges like foreshortening and slipping do not compromise therapeutic efficacy. When operators understand device behavior and implement structured protocols, endovenous stenting restores normal iliofemoral hemodynamics safely. Consequently, this behavior-based approach establishes endovascular reconstruction as the premier therapy for non-thrombotic iliofemoral compression.
The braided wire design of the Wallstent inherently contracts in length as its diameter expands within the vein. Consequently, operators must anticipate significant longitudinal foreshortening during deployment. Because this change occurs reliably across all procedures, specialists view it as a normal device-specific characteristic rather than a technical failure. Therefore, interventionalists can easily compensate for this dimensional shift by selecting adequate stent lengths and initiating deployment slightly higher than the target landing zone.
Interventionalists should extend the proximal margin of the Wallstent a few millimeters into the inferior vena cava. Because the right common iliac artery compresses the ostium of the left common iliac vein, complete lesion coverage remains critical. Furthermore, this deliberate positioning prevents stent collapse and secondary ostial recoil. Operators must simultaneously evaluate multiplanar imaging during release. Consequently, they avoid jailing the contralateral iliac vein while ensuring durable hemodynamic inflow into the systemic circulation.
If migration occurs, operators can successfully recapture or reposition the displaced stent using endovascular snares or balloon-assisted maneuvers. For instance, clinicians can manipulate a migrated stent entirely within the inferior vena cava without requiring open surgical conversion. Furthermore, teams can place a second overlapping stent across the target venous lesion to achieve complete decompression. Consequently, endovascular retrieval preserves technical success and prevents cardiopulmonary complications while allowing the planned revascularization procedure to conclude smoothly.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or another qualified healthcare provider with any questions you may have regarding a medical condition or treatment. Never disregard professional medical advice or delay in seeking it because of something you have read here. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Discover key insights into Wallstent deployment for non-thrombotic May-Thurner syndrome. Learn how anticipating foreshortening, managing migration, and utilizing structured endovascular techniques achieve 100% technical success and durable long-term iliofemoral venous patency.
last month

Momelotinib offers unique clinical benefits for myelofibrosis patients with moderate-to-severe anemia via dual JAK and ACVR1 inhibition. While registration trials show positive hematologic outcomes, emerging real-world data underscore the need for vigilant surveillance of renal function and peripheral neuropathy.
Today

Delhi is undergoing a major healthcare overhaul with enhanced Ayushman Bharat insurance up to ₹10 lakh, increased MBBS and PG medical training seats, expanded primary network mandirs, new tertiary neuro-ICUs, and public-private reproductive technology initiatives to build a resilient, preventative healthcare model.
Today
A 78-year-old patient with high-grade aneurysmal subarachnoid hemorrhage complicated by refractory Takotsubo cardiogenic shock achieved full recovery following microaxial flow pump (Impella 5.5) rescue, demonstrating the safety and feasibility of advanced mechanical circulatory support during dual antiplatelet therapy.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Yesterday

The randomized HOBIT-AF trial reveals that while structured weight loss after catheter ablation significantly improves cardiometabolic health in obese patients with paroxysmal atrial fibrillation, it does not reduce arrhythmia recurrence compared to standard care.
Today
