

Loading, please wait...
Loading, please wait...

Clinical practice increasingly acknowledges that psychological interventions can produce adverse effects. While psychological therapies provide proven clinical benefits, patients frequently report negative experiences in psychotherapy that impair recovery. Historically, clinicians prioritized positive outcomes and neglected therapeutic side effects. Consequently, unmonitored treatment strains often culminated in premature termination or severe clinical deterioration. The Negative Effects Questionnaire provides a standardized psychometric framework to identify adverse events during psychological interventions. By classifying unwanted occurrences into distinct thematic domains, clinicians can systematically quantify non-response and psychological distress. Moreover, psychiatric care in modern outpatient settings requires robust mechanisms to distinguish baseline distress from treatment-induced setbacks. When clinicians overlook emergent difficulties, patients often feel misunderstood or alienated. Therefore, recognizing adverse therapeutic responses early represents a vital component of safe mental healthcare. Recent network analytical techniques offer fresh perspectives on how these distinct adverse phenomena interact dynamically within outpatient cohorts. Consequently, psychiatrists and psychotherapists can better identify vulnerable individuals and safeguard therapeutic progress across diverse mental healthcare settings. This proactive stance prevents unnecessary distress and optimizes patient outcomes.
To decipher the complex architecture of adverse therapy events, investigators utilized a Gaussian graphical model. The study evaluated an outpatient cohort comprising 439 adults who were actively attending or had previously concluded psychotherapy. Rather than treating unwanted events in isolation, network analysis conceptualizes clinical symptoms as mutually reinforcing nodes within an interconnected system. Edge weights represent regularized partial correlations between specific clinical domains, which controls for spurious relationships among variables. Furthermore, the investigators conducted network comparison tests to examine whether network topologies differed across exploratory clinical subgroups. Traditional psychometric evaluations frequently rely on aggregate summary scores that obscure granular interactions between individual symptoms. Conversely, Gaussian graphical models illuminate the precise pathways through which distress propagates through the therapeutic system. In this clinical cohort, researchers examined relationships between symptom deterioration, stigma, dependency, therapeutic relationship strains, and negative self-appraisals. Importantly, the overall connectivity of the central cluster remained stable across diverse patient subgroups. This topological consistency suggests that specific core mechanisms reliably govern treatment strain regardless of individual demographic variations. As a result, network analysis provides mental health practitioners with an actionable roadmap of clinical vulnerabilities.
The mathematical model revealed that hopelessness occupied the most central position within the network. In network theory, a central node exhibits strong connections to multiple surrounding domains and influences overall network stability. Specifically, hopelessness displayed direct and potent connections to symptom deterioration, negative self-evaluation, and negative appraisals of the therapeutic process. When patients develop a sense of hopelessness during treatment, this demoralization rapidly activates parallel psychological burdens. For example, individuals often interpret their lack of immediate improvement as personal failure, which deepens negative self-evaluation. Subsequently, this negative self-appraisal exacerbates anxiety and depressive symptoms, leading directly to clinical deterioration. Furthermore, persistent hopelessness degrades the patient's faith in the therapeutic process itself. Patients begin to view therapeutic interventions as ineffective or futile, which weakens collaborative engagement and treatment adherence. Therefore, hopelessness does not function merely as an isolated symptom or an inert byproduct of chronic illness. Instead, it operates as a potent amplifier that sustains the broader cascade of therapeutic harm. Addressing hopelessness early in treatment can dismantle this interconnected cycle before irreversible disengagement occurs.
While hopelessness emerged as the central driver of distress, other clinical domains demonstrated comparatively low network centrality. Notably, care dependency and social stigma occupied peripheral positions in the estimated graphical model. Care dependency describes the patient's fear of functioning independently without perpetual therapeutic support. Meanwhile, stigma involves perceived social devaluation or internal embarrassment associated with seeking professional mental health services. Although clinicians frequently express concern regarding therapeutic dependency, the network data demonstrate that dependency does not directly drive widespread symptom exacerbation. Similarly, perceived social stigma, while undoubtedly burdensome, does not serve as a primary engine for acute treatment failure. Instead, peripheral nodes operate relatively independently of the core cluster. Consequently, an outpatient who feels embarrassed about therapy may still achieve positive clinical outcomes, provided their internal hope remains intact. Conversely, a patient without any stigma or dependency concerns will still deteriorate if profound hopelessness takes root. Clinicians must certainly address dependency and stigma during ongoing care. Nevertheless, therapeutic resources must focus primarily on high-centrality hubs that threaten treatment integrity.
These empirical findings carry urgent clinical relevance for psychiatrists, clinical psychologists, and primary care physicians. In many outpatient settings, clinicians track symptom severity using standard scales while overlooking the patient's subjective appraisal of therapy. However, tracking only DSM-defined symptoms overlooks critical shifts in cognitive demoralization. If a practitioner notices escalating despair, they must actively explore whether the therapeutic encounter itself inadvertently fuels the problem. For instance, rigid therapeutic frameworks or unaddressed alliance ruptures frequently generate intense frustration. Patients may conclude that their inability to benefit from evidence-based techniques proves their disorder is untreatable. To prevent this destructive trajectory, clinicians should conduct regular check-ins regarding therapeutic expectations and treatment satisfaction. Psychiatrists collaborating with allied psychotherapists should explicitly discuss subjective therapeutic experiences during medication reviews. When negative experiences in psychotherapy emerge, clinicians must validate the patient's emotional struggle rather than labeling them as resistant. Furthermore, adjusting intervention pacing or modifying therapeutic modalities can restore self-efficacy and prevent catastrophic drops in therapeutic engagement. Ultimately, proactive collaboration fosters a transparent therapeutic environment that protects vulnerable individuals from treatment-associated harm.
Negative experiences in psychotherapy encompass diverse unwanted events that emerge during psychological care. These events include clinical symptom deterioration, emergence of novel symptoms, strains in the therapeutic relationship, and heightened self-stigma. Additionally, patients may experience excessive dependency on their therapist or intense feelings of personal failure when therapeutic progress stalls. Standardized tools like the Negative Effects Questionnaire help clinicians systematically categorize and evaluate these adverse occurrences during routine psychiatric care.
Network analysis demonstrates that hopelessness functions as a central hub because it directly connects to multiple detrimental clinical domains. When a patient experiences treatment-related hopelessness, this belief triggers severe negative self-evaluation and profound dissatisfaction with the therapeutic process. Consequently, this cognitive demoralization accelerates objective symptom deterioration and prompts therapeutic disengagement. Because hopelessness exerts strong downstream effects across the entire clinical network, addressing it promptly helps dismantle broader patterns of therapeutic harm.
Clinicians should implement measurement-based monitoring using validated instruments such as the Negative Effects Questionnaire at regular treatment intervals. Rather than relying entirely on unprompted patient disclosures, practitioners must proactively inquire about emerging hopelessness, dissatisfaction, and symptom worsening. Creating a safe, non-judgmental dialogue allows individuals to voice concerns without fear of disappointing their provider. When therapists detect adverse effects early, they can renegotiate therapeutic goals, repair relational ruptures, and prevent premature treatment dropout.
Disclaimer: This content is for informational and educational purposes only and does not substitute professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider for specific clinical decisions. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A novel network analysis reveals that hopelessness acts as a central hub for negative experiences in psychotherapy. It directly links symptom deterioration, negative self-evaluation, and treatment dissatisfaction, emphasizing the need for proactive psychiatric monitoring to prevent clinical worsening.
last month

A multicenter study validates a machine learning-guided recalibrated SOFA score, demonstrating significantly improved ICU mortality discrimination while preserving the simple, additive, point-based structure critical for bedside decision-making.
Today

A landmark study reveals that lipid-rich malignant ascites alters the T-cell metabolic transcriptome, causing cholesterol efflux and impaired fatty acid oxidation. This suppresses TCR signalling and blocks BiTE immunotherapy, while lipid depletion restores antitumour cytotoxicity in ovarian cancer.
Today
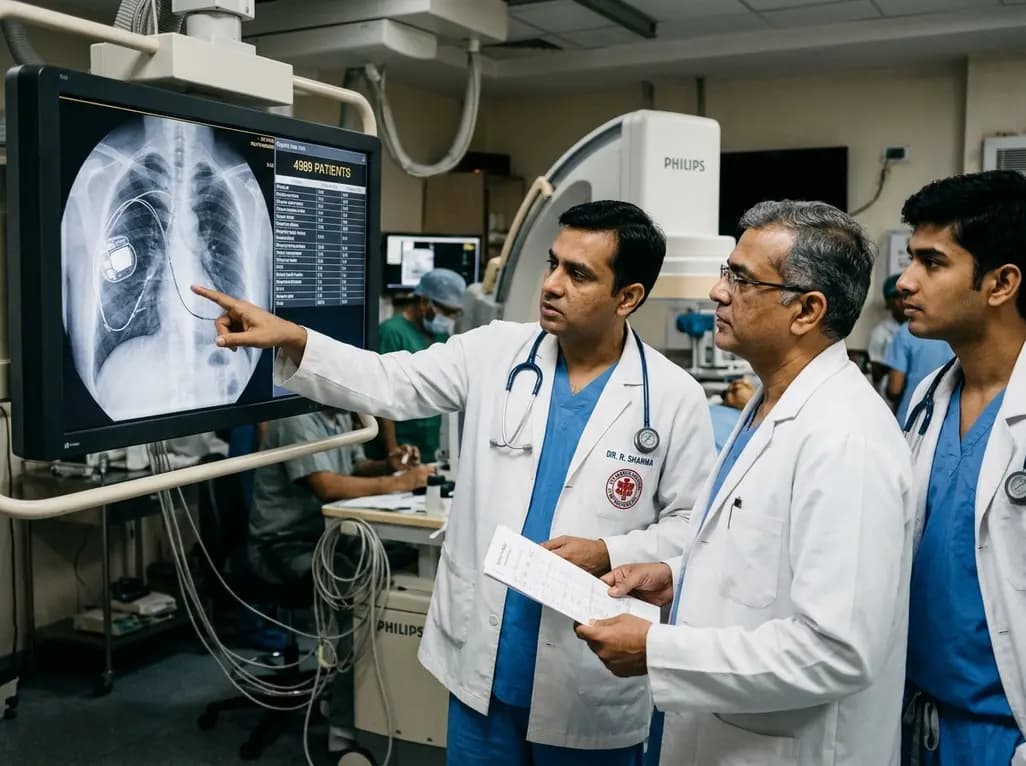
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today
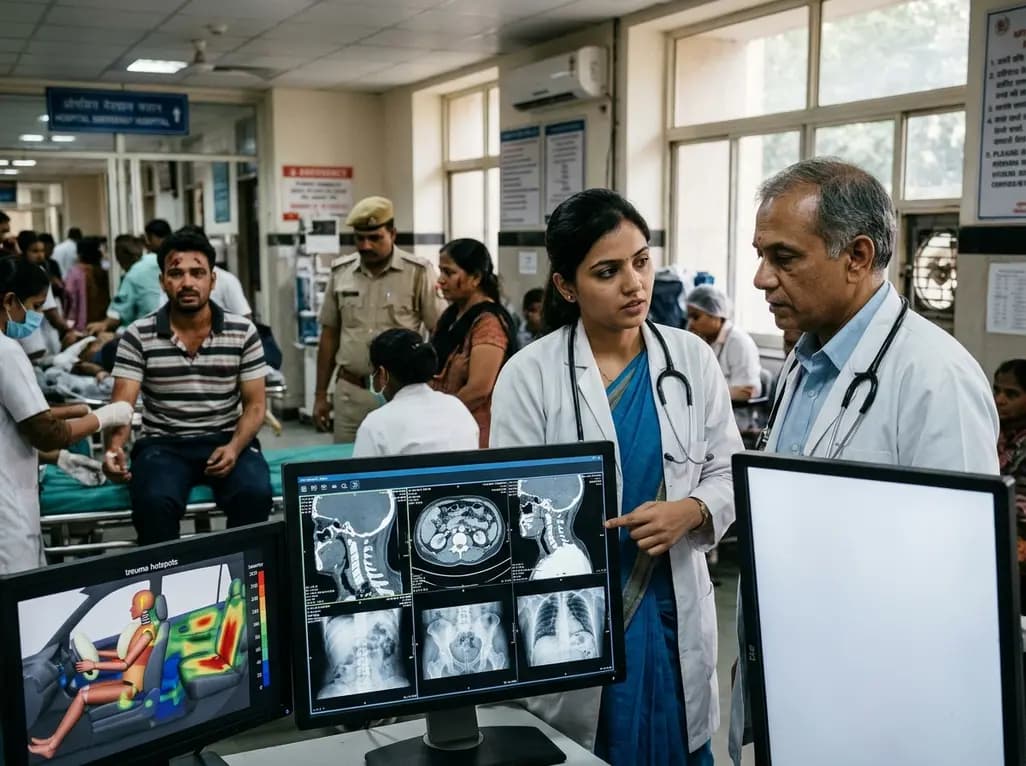
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
