

Loading, please wait...
Loading, please wait...

Evaluating lactate in AKI represents a common yet complex dilemma in critical care medicine and nephrology. Circulating lactate is frequently measured during acute illness to detect systemic hypoperfusion. However, elevated levels fundamentally reflect global metabolic stress and cellular reprogramming rather than isolated structural nephron injury. Clinicians often misinterpret hyperlactatemia solely as an indicator of tissue hypoxia. In contrast, renal dysfunction disrupts intrinsic clearance pathways, cellular respiration, and acid-base homeostasis. Therefore, high serum values demand a thorough evaluation of whole-body metabolic status. The kidney directly participates in systemic lactate turnover by clearing circulating anions and providing essential fuel for tubular transport. Consequently, an abrupt decline in functional filtration and tubular metabolism shifts systemic equilibrium toward rapid accumulation. In addition, hemodynamic instability and microvascular shunting worsen systemic oxygen delivery in septic shock. Thus, circulating lactate functions as a dynamic metabolic barometer rather than a kidney-specific biomarker. Understanding this physiological distinction prevents inappropriate fluid loading and guides timely diagnostic decisions in critically ill patients.
Under normal physiological conditions, the human kidneys maintain systemic acid-base equilibrium and carbohydrate economy. The renal cortex serves as an essential gluconeogenic powerhouse, generating roughly twenty percent of systemic endogenous glucose release. Specifically, proximal tubular epithelial cells consume circulating lactate as their primary carbon substrate for renal gluconeogenesis. These specialized tubular cells express key regulatory enzymes, including phosphoenolpyruvate carboxykinase and fructose-1,6-bisphosphatase. Consequently, the healthy kidney clears substantial amounts of circulating lactate daily through cellular oxidation and conversion. Furthermore, normal glomeruli freely filter lactate across the filtration barrier, while proximal tubules reabsorb virtually the entire filtered load through sodium-coupled monocarboxylate transporters. However, this reabsorption process exhibits a definite tubular transport threshold. When circulating levels exceed five millimoles per liter, tubular transporters become saturated, and urinary excretion begins to assist elimination. Therefore, intact renal parenchyma plays an indispensable role in preventing severe metabolic acidosis. When functional nephron mass diminishes, the loss of these active enzymatic pathways directly compromises global lactate clearance capacity.
During acute kidney injury, cellular metabolic pathways undergo profound remodeling that accelerates systemic hyperlactatemia. Ischemic, toxic, and septic insults trigger severe mitochondrial injury within energy-dependent tubular segments. Consequently, oxidative phosphorylation falters, forcing tubular cells to shift toward aerobic glycolysis to generate baseline energy. This metabolic reprogramming, analogous to the Warburg effect, markedly increases local lactate production. Moreover, damaged tubular mitochondria release reactive oxygen species that inhibit pyruvate dehydrogenase. As a result, cellular pyruvate shunts directly into lactate via lactate dehydrogenase. In addition, persistent metabolic stress triggers post-translational protein lactylation. Lactylation alters histones and non-histone proteins, which suppresses gluconeogenic transcription while promoting persistent inflammatory cascades and fibrotic signaling. Furthermore, microvascular rarefaction and capillary congestion create localized cortical hypoxia, even when global hemodynamics appear adequate. Thus, the injured kidney transitions from an efficient lactate consumer into an active lactate producer that drives systemic metabolic disarray. Clinicians must recognize that this metabolic switch impairs cellular repair, exacerbating tubular apoptosis and prolonging organ failure.
In critically ill patients, elevated serum lactate provides valuable prognostic information regarding organ failure and mortality. However, a single static measurement cannot distinguish evolving tissue dysoxia from established clearance failure. Therefore, clinicians must prioritize dynamic lactate clearance kinetics over time. Serial measurements taken over six to twenty-four hours reveal whether therapeutic interventions effectively restore tissue perfusion. For example, failing to clear elevated lactate within twelve hours strongly predicts renal replacement therapy requirement and hospital mortality. Furthermore, combining admission lactate with serum creatinine into ratios enhances early predictive discrimination after cardiac arrest or severe trauma. Nevertheless, physicians must avoid treating numbers in isolation without examining systemic hemodynamics. If lactate levels persist despite adequate mean arterial pressure, clinicians should suspect cellular metabolic shutdown rather than simple hypovolemia. Accordingly, tracking dynamic clearance trajectories guides resuscitation endpoints and prevents excessive crystalloid administration in oliguric patients. Ultimately, this approach facilitates timely escalation to specialized renal replacement before irreversible multiorgan dysfunction develops. Serial monitoring prevents premature fluid cessation in genuinely under-resuscitated patients.
Interpreting lactate in complex critical care environments requires vigilance against pervasive clinical confounders. For instance, advanced hepatic cirrhosis drastically reduces baseline clearance, compounding the metabolic effects of concurrent hepatorenal syndrome. Similarly, high-dose beta-adrenergic agonists stimulate aerobic glycolysis and drive benign type B hyperlactatemia. In addition, extracorporeal membrane oxygenation introduces unique hemodynamic perturbations that alter regional microcirculatory perfusion. In these complex circuits, rising lactate frequently reflects recirculation or cannula malposition rather than worsening nephron injury. Furthermore, continuous renal replacement therapy clearance of lactate varies with effluent flow rates and regional citrate anticoagulation protocols. Citrate metabolism requires hepatic and skeletal muscle oxidation; consequently, citrate accumulation produces metabolic acidosis that mimics lactic acidosis. Therefore, clinicians must carefully evaluate echocardiography and hepatic function before attributing elevated lactate purely to renal failure. Furthermore, choosing bicarbonate-buffered replacement fluids during dialysis prevents compounding systemic metabolic burden. Ultimately, integrating serial lactate kinetics into a multiparametric diagnostic approach protects fragile renal microvasculature while minimizing complications from over-resuscitation. Careful evaluation ensures accurate clinical decision-making.
The kidneys normally clear approximately twenty percent of circulating lactate through cortical gluconeogenesis and tubular oxidation. When acute tubular necrosis or ischemia occurs, proximal tubular cells suffer structural damage and mitochondrial injury. Consequently, the expression of key gluconeogenic enzymes falls dramatically. Furthermore, impaired glomerular filtration prevents urinary excretion when systemic levels exceed physiological thresholds. Therefore, the loss of functioning renal parenchyma directly compromises systemic elimination, causing lactate to accumulate rapidly.
A single static lactate measurement indicates metabolic stress but cannot determine whether the patient is improving or deteriorating. In contrast, serial monitoring calculates lactate clearance kinetics over consecutive six- to twelve-hour intervals. A rising or persistently high trajectory signals ongoing cellular hypoxia, uncorrected microcirculatory failure, or severe mitochondrial dysfunction. Conversely, rapid clearance confirms adequate tissue perfusion and resuscitation responsiveness, providing superior predictive discrimination for survival and renal recovery compared to isolated baseline values.
Continuous renal replacement therapy efficiently filters circulating lactate across high-flux membranes via convective and diffusive clearance mechanisms. However, the overall impact on circulating levels depends heavily on the chosen replacement and dialysate fluid buffers. Using lactate-buffered fluids in patients with concurrent hepatic or severe renal dysfunction can precipitate severe iatrogenic hyperlactatemia. Therefore, intensive care protocols strongly recommend using bicarbonate-buffered solutions, which clear endogenous lactate while correcting systemic metabolic acidosis without overloading metabolic pathways.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Interpreting lactate in AKI requires distinguishing systemic hypoperfusion from impaired renal clearance and metabolic remodeling. Learn how dynamic kinetics, tubular gluconeogenesis, and extracorporeal therapies influence risk stratification and bedside management in critical illness.
Today
Elder abuse education is essential for empowering clinicians to detect mistreatment, recognize forensic indicators, and navigate legal mandates. Enhancing interprofessional training and institutional policies ensures earlier intervention, protects patient dignity, and reduces preventable harm in aging populations.
Today
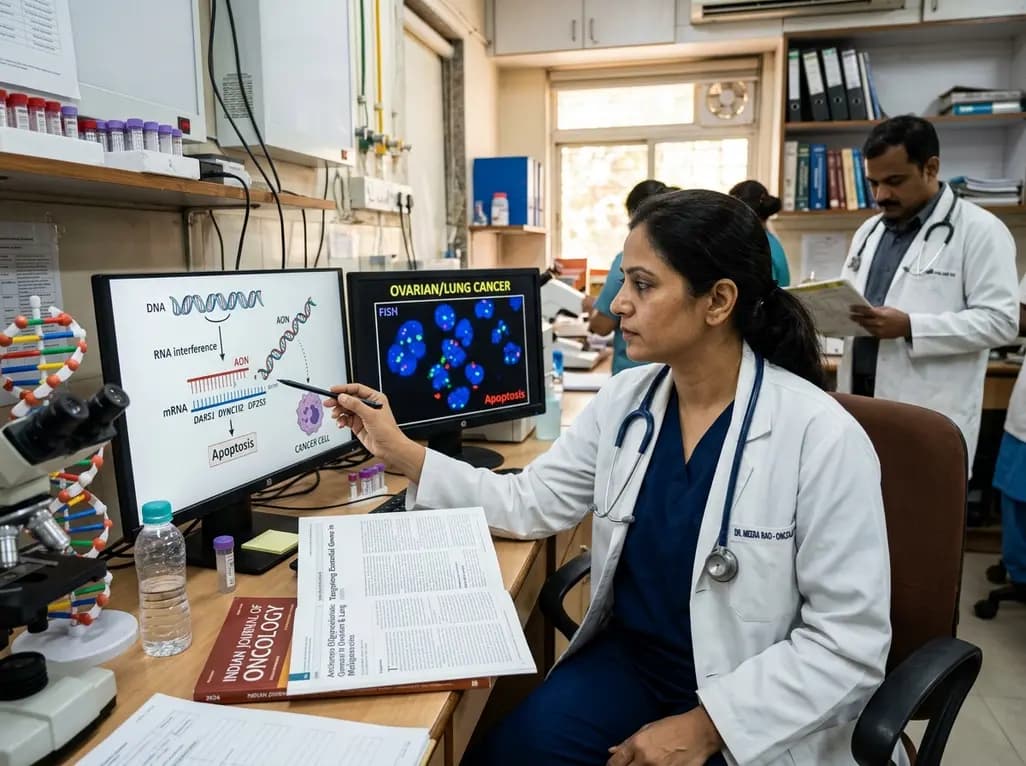
Novel preclinical research demonstrates that antisense oligonucleotides targeting essential genes such as DARS1, DYNC1I2, and EIF2S3 selectively induce apoptosis in ovarian and lung cancer cells. Conditional biomarker activation provides a viable strategy to spare normal tissue while overcoming therapy resistance.
Today
A recent study evaluates the impact of mean arterial pressure on cardiac output, pulmonary artery pulsatility index, and acute kidney injury during the first 24 hours after HeartMate 3 implantation, highlighting key hemodynamic targets for intensive care management.
Today

A 10-year Markov state-transition model shows minimally invasive tubular decompression dominates open laminectomy for pure lumbar spinal stenosis, yielding 5.95 vs 5.91 QALYs and saving $4,167 per patient through reduced complications and lower index costs.
Today
A systematic review evaluates the feasibility and safety of thyroidectomy after thermal ablation for thyroid nodules. Although procedures encounter significant fibrosis and surgical adhesions, permanent complication rates remain remarkably low in experienced centers.
Today
