

Loading, please wait...
Loading, please wait...

Managing mechanical circulatory support requires precise physiological titration during the immediate postoperative window. Understanding HeartMate 3 hemodynamics is crucial for intensivists and cardiothoracic teams caring for advanced heart failure patients in the intensive care unit. Historically, clinicians extrapolated blood pressure targets from earlier axial-flow devices or ambulatory settings. However, centrifugal continuous-flow pumps alter right ventricular afterload and organ perfusion in distinct ways. A recent investigation now provides critical insights into how early mean arterial pressure correlates with forward flow, right ventricular mechanics, and acute renal function.
Historically, clinicians managed left ventricular assist device recipients using standardized pressure targets derived from older technology. However, the fully magnetically levitated HeartMate 3 pump functions with unique pressure-flow relationships. Consequently, earlier protocols that targeted strict mean arterial pressures between 70 and 80 mmHg during ambulatory recovery might not address the acute physiological shifts of the initial 24 hours. During this fragile phase, anesthesia emergence, vasoplegia, and systemic inflammatory responses drastically modify vascular resistance. In addition, the native right ventricle must rapidly adapt to increased venous return generated by left ventricular decompression. Because previous guidelines relied on chronic outpatient registries, intensive care teams lacked granular, hourly hemodynamic evidence for early post-implantation care. Therefore, researchers evaluated continuous monitoring records to understand the complex interactions among arterial pressure, right heart mechanics, and end-organ perfusion. Their findings challenge conventional assumptions and emphasize the necessity of individualized hemodynamic targets rather than uniform thresholds. Consequently, clinicians must evaluate how pressure dynamics directly govern right ventricular performance and systemic perfusion in real time.
Clinicians often presume that altering arterial pressure produces dramatic, linear shifts in pump flow and systemic delivery. In this recent cohort study, investigators examined hourly pulmonary artery catheter data and invasive pressure lines across 25 hours. Interestingly, cardiac output curves demonstrated a broad mid-range plateau rather than a sharp peak. Furthermore, formal statistical testing failed to support significant nonlinearity or an interaction between mean arterial pressure and time. Thus, forward cardiac output remained remarkably resilient across moderate variations in arterial pressure. This resilience occurs because modern centrifugal pumps maintain continuous flow through magnetic levitation, reducing afterload sensitivity compared to earlier pulsatile or axial devices. Nevertheless, extreme hypertension increases left ventricular afterload, which can reduce forward output and promote aortic valve closure. Conversely, profound hypotension compromises systemic microvascular perfusion despite acceptable pump flow values. Therefore, intensive care physicians should avoid chasing a narrow blood pressure target solely to optimize forward flow. Instead, teams should integrate arterial pressure with metabolic indicators like arterial lactate, mixed venous saturation, and clinical urine output.
Although systemic flow remains relatively stable across pressure ranges, right-sided hemodynamics exhibit profound sensitivity to arterial pressure fluctuations. Specifically, the pulmonary artery pulsatility index, or PAPi, served as a primary metric of right ventricular contractile reserve in the investigation. The data revealed that higher mean arterial pressure correlated significantly with lower PAPi values. Moreover, this negative association varied dynamically over the first postoperative day. When systemic vascular resistance rises, the left ventricle faces higher afterload, potentially leading to incomplete decompression and increased left atrial pressure. Consequently, elevated backward pressure transmits across the pulmonary vascular bed, abruptly augmenting right ventricular afterload. Because the right ventricle lacks the muscular architecture to tolerate acute afterload spikes, contractility diminishes quickly. Clinicians frequently misinterpret early right ventricular dysfunction as primary pump failure or hypovolemia. However, these findings demonstrate that excessive systemic afterload directly impedes right-sided performance. Therefore, aggressive afterload reduction using balanced vasodilators protects right ventricular geometry and maintains optimal interventricular septal positioning during critical recovery.
Acute kidney injury represents one of the most frequent and debilitating complications following durable mechanical circulatory support. In the analyzed cohort, acute kidney injury developed in nearly thirty percent of patients within 72 hours, with most events occurring during the initial 24 hours. Importantly, researchers discovered that kidney injury correlated strongly with the duration of diminished mean perfusion pressure. They defined mean perfusion pressure as mean arterial pressure minus central venous pressure. For every ten-percentage-point increase in monitored time below a mean perfusion pressure of 60 mmHg, renal injury risks escalated considerably. This finding underscores that mean arterial pressure alone does not reflect true renal perfusion. When right ventricular dysfunction causes elevated central venous pressure, renal venous congestion drastically reduces the transrenal pressure gradient. Thus, maintaining an adequate systemic pressure fails to preserve glomerular filtration if venous congestion simultaneously opposes capillary outflow. As a result, critical care teams must simultaneously mitigate central venous congestion and support arterial pressure to maintain an adequate net perfusion gradient.
These physiological insights offer practical guidance for bedside clinicians managing patients in cardiovascular intensive care units. First, practitioners should move away from rigid, one-size-fits-all mean arterial pressure targets during the early postoperative window. Instead, teams must titrate vasopressors and vasodilators to sustain a mean perfusion pressure above 60 mmHg while preventing systemic hypertension. Second, intensive monitoring of right ventricular performance remains imperative. Because elevated arterial pressure impairs right ventricular pulsatility, clinicians should actively employ pulmonary artery catheters to track PAPi and central venous pressure. If right ventricular strain develops alongside rising systemic pressure, clinicians should promptly introduce pulmonary or systemic vasodilators rather than inotropic escalation alone. Third, maintaining decongestion protects renal autoregulation far more effectively than isolated blood pressure elevation. In Indian tertiary centers where mechanical circulatory support programs continue to expand, implementing these nuanced hemodynamic strategies can reduce acute kidney injury and improve overall survival. By synchronizing pump speed adjustments with meticulous pharmacological management, clinical teams ensure balanced biventricular function and optimal organ recovery.
Clinicians generally aim for a mean arterial pressure between 70 and 80 mmHg during chronic left ventricular assist support. However, during the first 24 hours, practitioners should prioritize individualized targets rather than rigid thresholds. Maintaining a mean perfusion pressure above 60 mmHg while preventing systemic hypertension protects renal filtration and avoids excessive right ventricular afterload. Therefore, bedside teams must titrate therapy using invasive hemodynamic metrics and metabolic markers rather than pressure alone.
Elevated mean arterial pressure increases left ventricular afterload, which can reduce forward pump efficiency and elevate left atrial filling pressures. Consequently, this retrograde pressure transmits into the pulmonary circulation, increasing right ventricular afterload. Because the right ventricle is highly sensitive to afterload changes, contractile performance diminishes, leading to lower pulmonary artery pulsatility index values. Thus, excessive systemic vasoconstriction directly impairs right ventricular mechanics and exacerbates venous congestion during early recovery.
Mean perfusion pressure, calculated as mean arterial pressure minus central venous pressure, represents the true driving gradient across the renal microvasculature. Relying solely on mean arterial pressure overlooks elevated central venous pressure caused by right ventricular dysfunction or volume overload. Persistent venous congestion impedes renal venous outflow and drops glomerular filtration. Therefore, sustaining mean perfusion pressure above 60 mmHg through simultaneous arterial support and active venous decongestion effectively protects postoperative renal function.
Disclaimer: This content is for informational and educational purposes only and should not be taken as professional medical advice. Always consult a qualified healthcare provider for personal health concerns. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent study evaluates the impact of mean arterial pressure on cardiac output, pulmonary artery pulsatility index, and acute kidney injury during the first 24 hours after HeartMate 3 implantation, highlighting key hemodynamic targets for intensive care management.
Today
Elder abuse education is essential for empowering clinicians to detect mistreatment, recognize forensic indicators, and navigate legal mandates. Enhancing interprofessional training and institutional policies ensures earlier intervention, protects patient dignity, and reduces preventable harm in aging populations.
Today
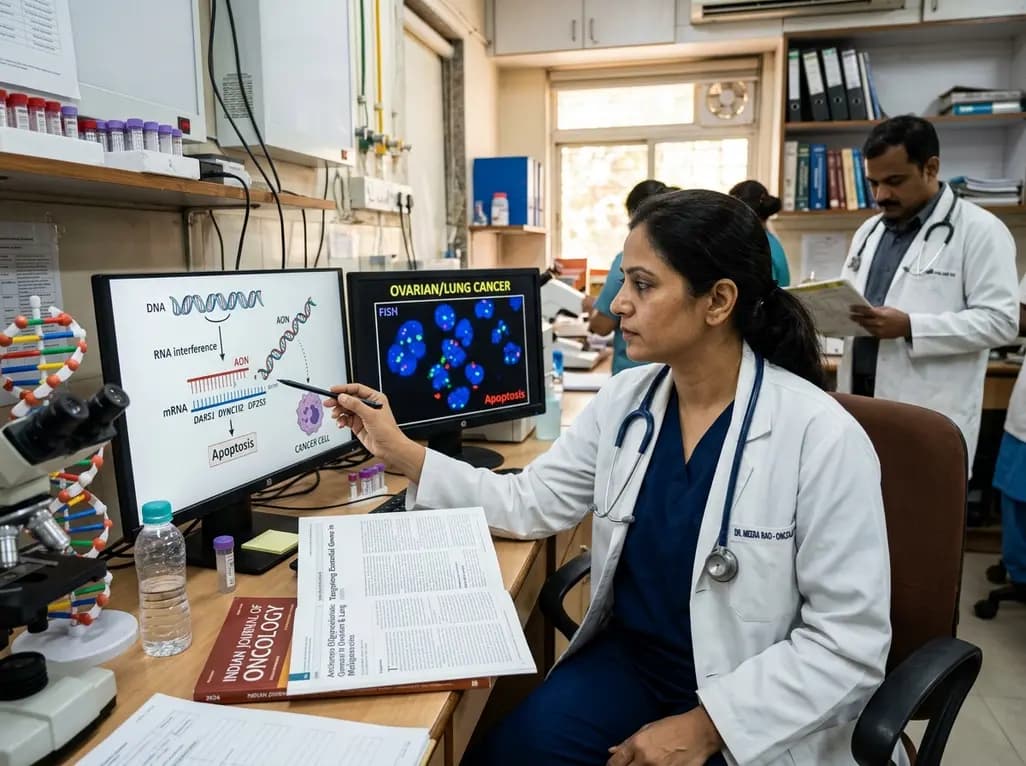
Novel preclinical research demonstrates that antisense oligonucleotides targeting essential genes such as DARS1, DYNC1I2, and EIF2S3 selectively induce apoptosis in ovarian and lung cancer cells. Conditional biomarker activation provides a viable strategy to spare normal tissue while overcoming therapy resistance.
Today

A 10-year Markov state-transition model shows minimally invasive tubular decompression dominates open laminectomy for pure lumbar spinal stenosis, yielding 5.95 vs 5.91 QALYs and saving $4,167 per patient through reduced complications and lower index costs.
Today
A systematic review evaluates the feasibility and safety of thyroidectomy after thermal ablation for thyroid nodules. Although procedures encounter significant fibrosis and surgical adhesions, permanent complication rates remain remarkably low in experienced centers.
Today
