

Loading, please wait...
Loading, please wait...

Proactive surveillance of intellectual disability mortality remains an essential clinical tool for addressing profound health inequities across modern healthcare systems. Individuals with intellectual disabilities and autism frequently encounter severe physical multimorbidity, yet systemic diagnostic challenges obscure acute clinical decline. Consequently, systematic mortality reviews provide vital clinical intelligence regarding preventable causes of death. Medical professionals must understand these underlying systemic factors to improve patient safety, enhance care coordination, and eliminate avoidable clinical mortality.
Recent evidence emphasizes that adults with neurodevelopmental conditions experience a substantially shortened life expectancy compared to the general population. In fact, many individuals die several decades prematurely from treatable physical illnesses. Furthermore, national mortality surveillance systems systematically capture preventable clinical factors that standard hospital death certificates routinely overlook. When healthcare authorities dismantle or dilute dedicated mortality review frameworks, critical visibility into preventable clinical failures vanishes.
Therefore, structured mortality surveillance serves as an indispensable epidemiological safeguard for vulnerable populations. Clinicians frequently lack comprehensive longitudinal visibility across fragmented primary, community, and secondary care settings. As a result, subtle warning signs of deterioration often go unrecorded in standard health records. Standardized mortality audit frameworks overcome this communication gap by rigorously analyzing the entire clinical pathway leading to death. Consequently, healthcare organizations gain actionable data to redesign clinical pathways, address prescribing hazards, and mandate targeted clinician training. By preserving national and institutional mortality surveillance, healthcare systems can hold clinical teams accountable while proactively protecting vulnerable individuals from recurring, predictable harm.
Clinical investigations consistently reveal that respiratory infections, severe gastrointestinal complications, and uncontrolled epilepsy represent the leading causes of avoidable mortality in people with intellectual disabilities. In particular, aspiration pneumonia occurs with alarming frequency because underlying dysphagia, impaired swallow reflexes, and sedative medications often co-exist. Clinicians must therefore screen regularly for swallowing difficulties and implement posture-adapted feeding strategies to minimize microaspiration risks.
Moreover, gastrointestinal dysmotility and severe chronic constipation present insidious yet life-threatening risks. Antipsychotic medications, anticholinergics, and limited physical mobility frequently compound chronic constipation, progressing unnoticed toward fecal impaction, stercoral ulceration, bowel ischemia, or fatal sepsis. Similarly, clinicians must maintain proactive vigilance regarding sudden unexpected death in epilepsy, especially because seizure disorders affect this cohort disproportionately. Routine medication reviews, structured epilepsy management plans, and dedicated nocturnal monitoring substantially decrease seizure-related fatalities. Therefore, treating physicians must not regard physical complaints as minor background symptoms. Instead, primary care physicians and hospital specialists should aggressively identify, treat, and monitor these three major preventable clinical drivers before catastrophic organ failure or systemic collapse develops.
Diagnostic overshadowing represents one of the most perilous cognitive biases in contemporary clinical medicine. Specifically, healthcare providers frequently attribute acute changes in behavior, agitation, or reduced engagement to a patient's baseline intellectual disability or autism spectrum disorder rather than investigating an underlying acute medical illness. Consequently, severe physical conditions such as acute appendicitis, bacteremia, fractures, or bowel obstruction remain undiagnosed until life-threatening sepsis or shock intervenes.
To counter this diagnostic pitfall, clinicians must recognize that atypical presentations of distress frequently signify physical pain. Non-verbal patients or individuals with limited communication cannot always articulate localized somatic discomfort. Instead, they may manifest acute distress through self-injury, withdrawal, restlessness, or refusal to eat. Therefore, healthcare teams must conduct structured head-to-toe physical examinations and objective physiological assessments whenever an abrupt behavioral change occurs. Furthermore, clinicians should actively involve family members and familiar caregivers who understand the patient's individual baseline functioning. By listening attentively to caregiver concerns and adopting an investigative clinical approach, medical professionals can dismantle diagnostic overshadowing and deliver timely, lifesaving interventions across emergency and inpatient departments.
Beyond acute respiratory and neurological emergencies, cardiovascular and metabolic diseases contribute substantially to premature mortality among individuals with intellectual disabilities. Patients with intellectual and developmental conditions exhibit significantly higher rates of obesity, type 2 diabetes mellitus, and ischemic heart disease. Nevertheless, routine preventative health screening, including lipid profiles, glycemic monitoring, and blood pressure surveillance, remains poorly executed in this population.
In addition, long-term psychotropic polypharmacy exacerbates these metabolic risks. Specialists frequently prescribe antipsychotics, mood stabilizers, and sedatives off-label to manage challenging behaviors, leading to rapid weight gain, insulin resistance, and accelerated atherosclerosis. Therefore, physicians must institute regular metabolic monitoring protocols for every patient receiving psychotropic pharmacotherapy. Clinicians must perform annual physical health checks that incorporate structured cardiovascular risk stratification, electrocardiography, and dietary reviews. Moreover, medical teams should actively pursue deprescribing initiatives to eliminate unnecessary sedatives and anticholinergic burdens. By integrating preventive cardiology and endocrinology into routine primary care consultations, clinicians can substantially mitigate the long-term vascular morbidity that curtails life expectancy in these individuals.
Translating epidemiological mortality data into clinical practice requires hospitals and health networks to institutionalize structured mortality and morbidity reviews. When a patient with an intellectual disability dies in an inpatient or community setting, multidisciplinary teams must convene to conduct a comprehensive root-cause analysis. This review must critically examine diagnostic timelines, medication administration, caregiver communication, and adherence to reasonable adjustments during hospital admission.
Furthermore, healthcare leadership must ensure that mortality audits foster a transparent learning culture rather than assigning individual culpability. Multi-professional panels, including psychiatrists, internists, pediatricians, pharmacists, and specialist disability nurses, should review clinical decision-making across all touchpoints of care. Subsequently, clinical audit committees must disseminate findings across institutional departments to rectify identified operational defects. For instance, hospitals can implement standardized dysphagia screening tools in acute wards, mandate sepsis alert protocols tailored to atypical presentations, and establish hospital liaison nurse roles. Ultimately, robust clinical reviews generate actionable institutional memory. By embedding systematic mortality audits within standard quality-improvement frameworks, healthcare organizations uphold ethical equity and protect vulnerable patients from preventable clinical harm.
The most frequent preventable causes of death include aspiration pneumonia, severe gastrointestinal obstruction or perforation from chronic constipation, and sudden unexpected death in epilepsy. In addition, bacterial sepsis following unrecognized urinary or chest infections contributes significantly to early mortality. These clinical conditions often progress rapidly because patients may display atypical symptoms, preventing timely clinical diagnosis and urgent medical intervention before severe physiological collapse occurs.
Diagnostic overshadowing occurs when clinicians mistakenly ascribe physical symptoms or altered behaviors to a pre-existing intellectual or developmental condition. Consequently, acute surgical emergencies, systemic infections, and fractures frequently escape detection during early hospital presentations. Clinicians must maintain high diagnostic suspicion, perform comprehensive physical examinations, and actively consult regular caregivers whenever non-verbal patients exhibit sudden behavioral distress or acute changes in baseline functioning.
Multidisciplinary mortality audits bring together general physicians, psychiatrists, pediatricians, pharmacists, and nursing specialists to systematically analyze root causes of preventable deaths. By identifying prescribing errors, diagnostic omissions, and systemic communication breakdowns, clinical teams can rectify operational vulnerabilities across acute and primary care pathways. Furthermore, these collaborative reviews foster an institutional safety culture, ensuring health organizations implement targeted evidence-based clinical adjustments that directly protect future patients.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Shankar R et al. Learning from deaths to improve lives: why England still needs a national LeDeR programme. Br J Psychiatry. 2026 Nov 03. doi: 10.1192/bjp.2026.10832. PMID: 42973441.
Heslop P et al. The Learning Disabilities Mortality Review (LeDeR) Programme: Annual Report. King's College London and NHS England; 2023.
O'Dwyer M et al. Physical health and multimorbidity in individuals with intellectual disabilities. Lancet Psychiatry. 2022;9(6):489-502.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





National mortality reviews offer vital clinical lessons to reduce preventable deaths in people with intellectual disability and autism, highlighting the need for structured audits and proactive physical care.
Today
New qualitative research explores stakeholder views across human and animal health to contextualize appropriate antimicrobial use. Defining clear, practical stewardship standards across sectors is critical to combat global antimicrobial resistance and improve prescribing practices.
Today

A major ABCD study analysis reveals that prenatal co-exposure to cannabis and tobacco significantly impairs fluid cognitive abilities in middle childhood, whereas crystallized intelligence remains unaffected. The findings highlight urgent needs for targeted antenatal screening and intervention.
Today
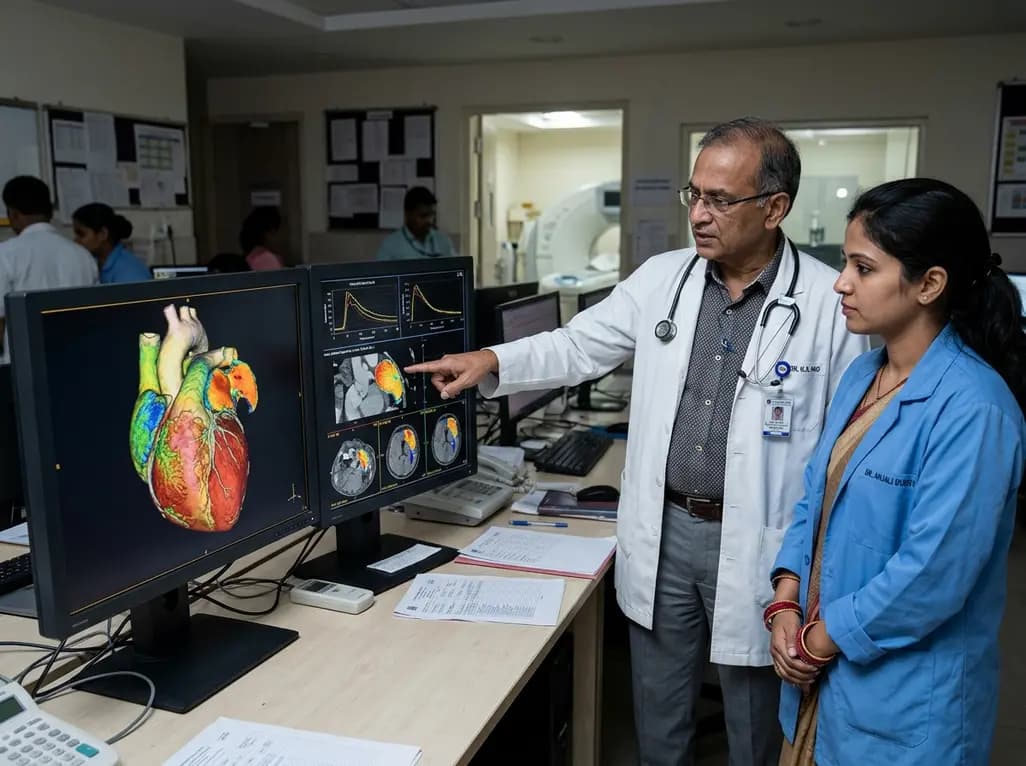
Dynamic contrast 4DCT enables precise mapping of left atrial appendage blood transport in atrial fibrillation. By quantifying regional stasis, wash-in kinetics, and residence time, this imaging advance offers clinician-tailored thromboembolic risk stratification beyond standard clinical scores.
Today

A systematic review and meta-analysis highlights the substantial impact of plyometric jump training on jump performance, reactive strength, and landing kinematics in female team-sport athletes, providing evidence-based programming guidelines for sports medicine and orthopedics.
Today

India is poised to transform chronic disease management through wearable health technology. Discover how continuous remote monitoring and predictive algorithms empower clinicians to detect early cardiovascular signals, personalize metabolic interventions, and deliver equitable preventive care across populations.
Today
