

Loading, please wait...
Loading, please wait...

Incretin-based therapeutics have revolutionized modern metabolic medicine by enabling unprecedented reductions in body weight and cardiovascular risk. However, real-world clinical adherence remains challenging, and emerging evidence highlights the profound impact of GLP-1 weight regain following drug cessation. A reconstructed aggregate-data Bayesian longitudinal meta-analysis evaluated post-discontinuation trajectories among patients treated with semaglutide and tirzepatide. Consequently, these findings offer vital guidance for clinicians navigating chronic obesity management.
Researchers conducted a hierarchical Bayesian longitudinal re-analysis using published aggregate timepoint data. The investigation pooled findings from six clinical studies comprising ten discrete intervention arms and 1,776 participants. Furthermore, observed trial follow-up periods ranged from 4 to 52 weeks following treatment cessation. The statistical framework modeled several critical milestones, including absolute weight loss at treatment cessation, monthly rate of rebound, time to 50% rebound, and projected time to full baseline weight restoration. Additionally, Bayesian meta-regression explored whether specific drug classes, initial weight loss magnitude, or structured post-treatment behavioral support influenced rebound trajectories. Ultimately, this approach provides robust longitudinal estimates that help clinicians anticipate post-therapy outcomes accurately.
At the point of drug cessation, participants achieved an estimated mean weight loss of 15.35 kg. However, cessation triggered an immediate rebound trajectory averaging 1.04 kg regained per month. Based on the linear Bayesian model, patients regained 50% of their lost weight within just 7.50 months. Moreover, the model projected a complete return to baseline weight by 15.00 months post-discontinuation. Although unadjusted analyses showed numerically faster rebound with tirzepatide compared to semaglutide, multivariable adjustment removed independent drug-specific differences. Consequently, clinicians must recognize that rapid rebound represents a general incretin class phenomenon rather than an agent-specific failure.
The meta-regression identified notable predictors governing rebound speed. Specifically, a greater magnitude of initial weight loss exhibited the strongest directional association with faster rebound velocity. Although its credible interval crossed zero, this finding aligns with established metabolic adaptation principles. Furthermore, severe caloric deficit and substantial adipose tissue loss trigger compensatory neurohormonal pathways, such as elevated ghrelin and reduced leptin secretion. Conversely, concurrent post-discontinuation behavioral and lifestyle support demonstrated a directional association with slower rebound rates. However, statistical imprecision underscores that lifestyle interventions alone rarely counterbalance the physiological drive to restore lost fat mass.
The biological mechanisms driving rapid weight regain reflect evolutionary survival adaptations. When clinicians withdraw glucagon-like peptide-1 or dual GIP/GLP-1 receptor agonists, central appetite suppression and delayed gastric emptying dissipate rapidly. Consequently, patients experience intense appetite resurgence, diminished satiety, and increased food cravings. Additionally, resting metabolic rate declines during active weight loss and remains suppressed post-treatment. Therefore, when individuals resume higher caloric intake in the presence of reduced energy expenditure, positive energy balance accelerates adipose accumulation. Recognizing these neuroendocrine drivers reinforces the concept that obesity is a relapsing, chronic metabolic disease.
These findings carry profound implications for routine clinical practice. First, physicians must counsel patients before initiating therapy that anti-obesity medications require long-term, potentially indefinite use. Abrupt discontinuation invariably exposes patients to metabolic recidivism and cardiometabolic risk reversal. Second, when financial constraints, adverse effects, or patient preference necessitate deprescribing, clinicians should implement proactive tapering schedules rather than sudden cessation. Additionally, healthcare providers must intensify medical nutrition therapy, resistance exercise, and behavioral monitoring during the transition period. Structured follow-up visits within the first three months remain essential to detect early weight gain and intervene promptly.
Because projections beyond 52 weeks rely on model-based extrapolations, long-term prospective trials must evaluate extended real-world trajectories. Researchers must explore low-dose maintenance strategies, intermittent dosing regimens, and combination approaches with oral anti-obesity agents. Moreover, health systems and insurance payers must align policies with obesity biology. Treating obesity as an episodic condition requiring short courses of therapy undermines clinical investments and worsens long-term cardiovascular outcomes. Instead, policy frameworks must support sustainable, uninterrupted access to evidence-based metabolic therapies.
Patients regain weight at an average rate of 1.04 kg per month after discontinuing semaglutide or tirzepatide. Longitudinal Bayesian modeling indicates that individuals regain 50% of their initial weight loss within 7.5 months. Furthermore, patients typically return to their pre-treatment baseline weight within 15 months unless effective alternative maintenance interventions are instituted immediately.
Unadjusted statistical models showed numerically faster weight regain with tirzepatide compared to semaglutide. However, this difference disappeared after adjusting for the total amount of initial weight lost during treatment. Therefore, faster regain reflects greater initial weight reduction rather than an intrinsic drug-specific characteristic, confirming that both incretin therapies follow similar post-discontinuation trajectory patterns.
Structured behavioral and lifestyle support shows a directional association with slower weight regain, but it rarely prevents rebound completely. Because stopping incretin therapy removes strong neuroendocrine appetite suppression while adaptive thermogenesis persists, lifestyle modifications alone struggle to overcome the body's biological drive to restore lost weight over the long term.
Disclaimer: This content is for informational and educational purposes only. It is not intended to substitute for professional medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References
Kow CS et al. Weight Regain Trajectories After Discontinuation of Semaglutide or Tirzepatide: A Reconstructed Aggregate-Data Bayesian Longitudinal Meta-Analysis. Endocrinol Diabetes Metab. 2026 Sep undefined. doi: 10.1002/edm2.70325. PMID: 42673571.
West S et al. Weight regain after cessation of medication for weight management: systematic review and meta-analysis. BMJ. 2026;388:e081977.
Wilding JPH et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. Diabetes Obes Metab. 2022;24(8):1553-1564.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A Bayesian meta-analysis reveals that patients stopping semaglutide or tirzepatide regain weight rapidly at 1.04 kg per month, returning to baseline within 15 months. Clinicians must view obesity as a chronic disease requiring proactive long-term maintenance strategies.
4 weeks back
Following 37,899 reported cases and 9 deaths, Odisha has scaled up active case detection, rapid diagnostic testing, and vector control across high-burden districts. Here is a comprehensive clinical breakdown of the state's aggressive containment protocols, diagnostic pathways, and targeted field management.
Today

Endometriosis affects millions of women across India, yet diagnostic delays frequently exceed five years. Recent multi-centre genomic research has identified 21 novel genetic regions, notably on chromosome 13, establishing crucial population-specific insights to transform clinical screening and therapeutic strategies.
Today
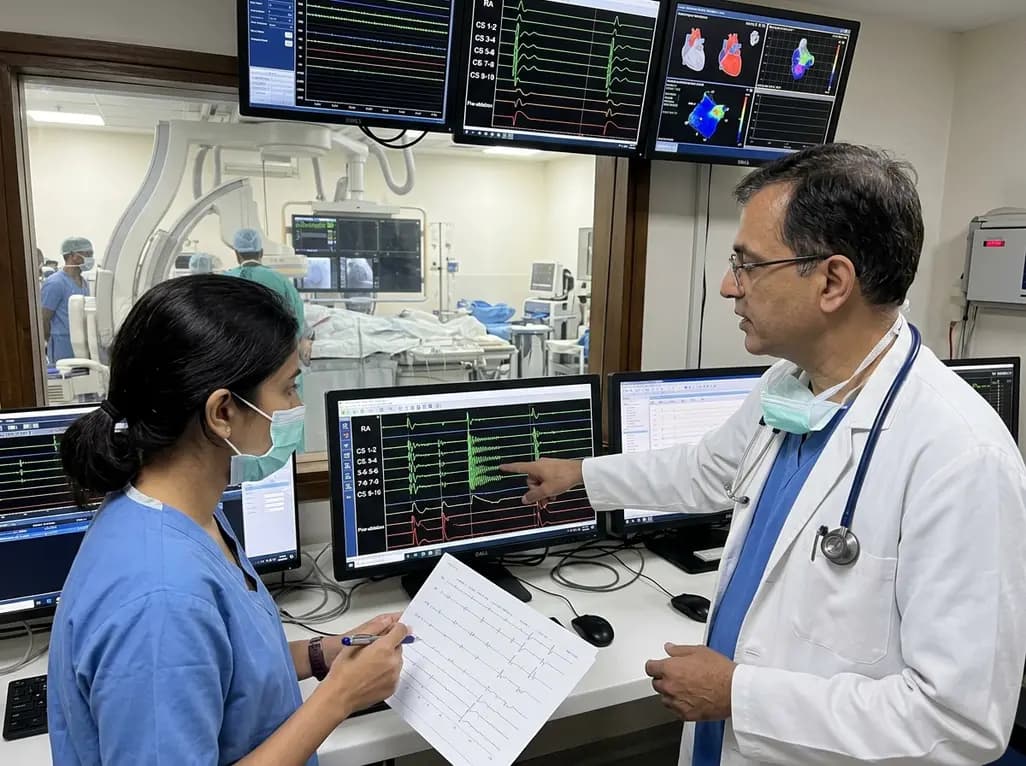
Radiofrequency catheter ablation of the cavotricuspid isthmus successfully terminates typical atrial flutter. This article reviews the mechanisms driving coronary sinus electrogram changes, wavefront activation pathways, and clinical criteria to verify bidirectional block during electrophysiology studies.
Today

A study comparing four knee flexion strength tests after ACL reconstruction using hamstring tendon autografts reveals marked variability in limb symmetry indices. Clinicians must recognize that different strength testing modalities yield divergent return-to-sport clearance rates.
Today
Discover how to identify superimposed entrapment neuropathy in diabetic patients. This review details clinical evaluation, surgical decompression evidence, and a structured algorithm for primary care referrals to prevent ulcers and preserve limb function.
Yesterday
