

Loading, please wait...
Loading, please wait...
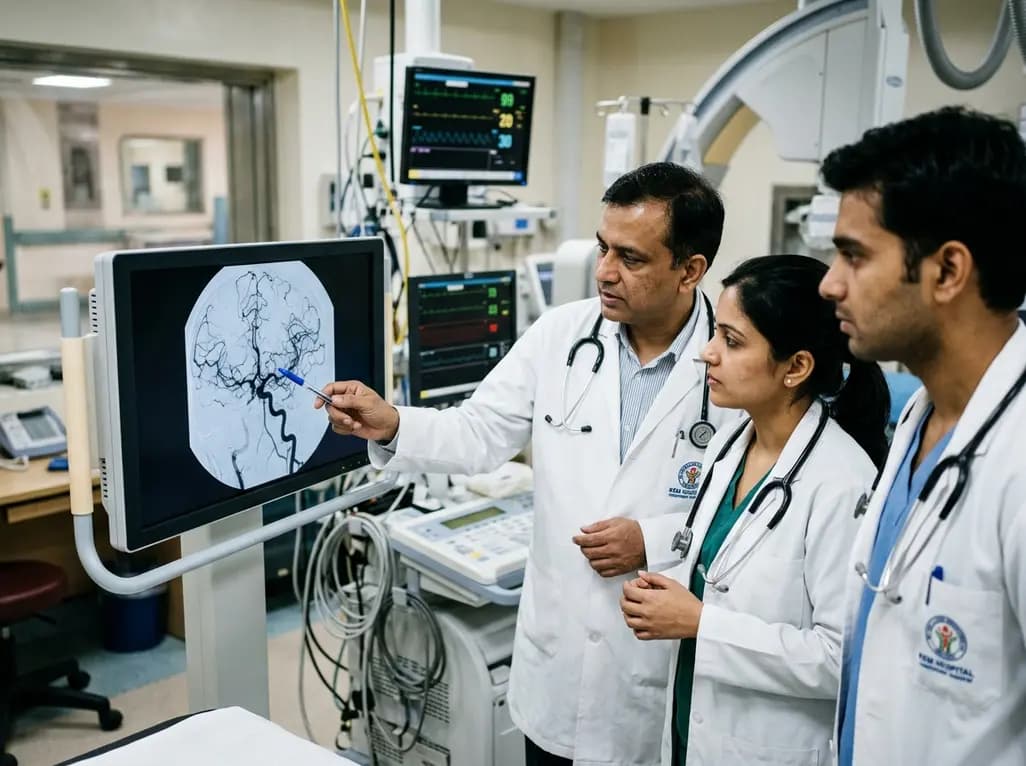
Endovascular thrombectomy revolutionized acute ischemic stroke management across modern neurovascular centers. However, patient outcomes after mechanical recanalization for anterior-circulation large-vessel occlusion remain remarkably heterogeneous. Pretreatment vascular anatomy strongly influences how rapidly penumbral brain tissue converts into irreversible core infarction. In this setting, collateral circulation in stroke provides crucial retrograde arterial perfusion to vulnerable neural parenchyma. Clinicians often observe divergent trajectories among individuals who present with identical initial neurological deficit scores. Consequently, evaluating retrograde vascular pathways prior to mechanical intervention has emerged as a fundamental diagnostic priority. Pretreatment digital subtraction angiography allows neurointerventionalists to grade these collateral pathways with exceptional precision. The American Society of Interventional and Therapeutic Neuroradiology and Society of Interventional Radiology scale standardizes this angiographic appraisal. Robust collateral recruitment preserves microvascular architecture while the interventional team prepares the catheterization laboratory. Conversely, inadequate retrograde flow accelerates cytotoxic edema and irreversible tissue necrosis. A recent cohort study evaluated 718 acute stroke patients undergoing mechanical revascularization. The investigators systematically measured the multidimensional clinical effects of pretreatment collateral channels. Their findings highlight the indispensable prognostic value of angiographic collateral assessments in real-world clinical care.
Neurovascular specialists classify retrograde leptomeningeal channels using the standardized ASITN/SIR collateral grading system. This scale categorizes collateral flow from grade 0, representing absent collateral reconstitution, to grade 4, which demonstrates complete and rapid arterial filling. In the evaluated anterior-circulation cohort, intermediate collateral recruitment predominated, appearing in more than half of all evaluated patients. Specifically, 55.2% of individuals demonstrated moderate grade 2 vessel filling, whereas severe collateral deficits occurred in substantial subsets. Grade 0 collateralization affected 21.4% of patients, and grade 1 represented 20.2% of the study cohort. In contrast, robust retrograde perfusion corresponding to grade 3 developed in only 3.2% of individuals. These baseline distributions underscore that severe vascular compromise frequently challenges mechanical thrombectomy teams. Furthermore, anatomical variations within the Circle of Willis strongly influence collateral recruitment capacity. Primary collateral pathways, including anterior and posterior communicating arteries, recruit immediately during acute carotid or middle cerebral artery occlusions. Secondary leptomeningeal anastomoses subsequently recruit to rescue peripheral cortical areas. Therefore, precise angiographic classification reveals critical differences in baseline ischemic vulnerability before mechanical catheter manipulation begins. Consequently, understanding these baseline anatomic distributions enables neurointerventionists to anticipate technical hurdles and procedural timelines during clot retrieval.
The presence of robust collateral pathways directly translates into superior long-term functional recovery. In this cohort, favorable 90-day functional outcome, defined as a modified Rankin Scale score between 0 and 2, surged from 31.2% in poor collaterals to 63.6% in robust grades. Concurrently, 90-day mortality plummeted from 51.8% among patients with absent flow down to 18.2% among those with robust compensation. Even after clinicians adjusted for internal carotid artery occlusions, each single-grade increase maintained an independent association with functional independence. Specifically, every increment yielded an adjusted odds ratio of 1.283 for favorable outcomes. Similarly, each step up lowered the odds of all-cause mortality to 0.697. Furthermore, ordinal shift analyses demonstrated a marked movement toward lower overall disability scores across the entire cohort. Nevertheless, researchers observed that additional adjustments for post-procedural parameters and systemic inflammatory markers attenuated these direct associations. Experts believe that collaterals exert their protective benefits through complex intermediary pathways, including successful microvascular reperfusion. Therefore, evaluating baseline retrograde vessel architecture provides vital prognostic reassurance for treating teams and families alike.
Reperfusion injury and blood-brain barrier disruption represent two catastrophic complications following mechanical recanalization. Fortunately, robust leptomeningeal vessels provide continuous nutritive flow that stabilizes capillary endothelial integrity during acute arterial occlusion. The study revealed that each incremental collateral grade significantly protected patients against malignant brain edema, demonstrating an adjusted odds ratio of 0.483. Similarly, higher collateral scores significantly decreased the risk of hemorrhagic transformation, producing an adjusted odds ratio of 0.770. When collateral flow fails, prolonged hypoperfusion destabilizes basal lamina proteins and promotes enzymatic matrix degradation. Consequently, sudden arterial reperfusion into fragile capillary beds induces extensive petechial extravasation and parenchymal hematomas. In addition, severely ischemic tissue shifts rapidly toward anaerobic glycolysis, driving cytotoxic cellular swelling. If collateral supply remains poor, massive swelling precipitates transtentorial herniation and rapid death. These clinical findings demonstrate that angiographic collaterals protect far more than just the ischemic penumbra. In fact, robust retrograde flow actively maintains cerebral microvascular stability, substantially reducing devastating intracranial complications after successful mechanical revascularization. Accordingly, identifying poor collateralization alerts clinicians to initiate osmotic therapies early and consider decompressive hemicraniectomy without unnecessary delay.
Early neurological deterioration presents a formidable clinical dilemma during the critical hours following endovascular therapy. Patients often deteriorate despite technically successful large-vessel recanalization, an outcome termed futile reperfusion. In this cohort, each incremental rise in collateral grade significantly reduced early neurological deterioration, yielding an adjusted odds ratio of 0.788. Weak retrograde flow often leads to microvascular no-reflow phenomena, where capillary bed thrombosis persists despite macrovascular patency. Furthermore, poor collateral flow permits rapid ischemic core expansion during unavoidable transfer delays. When interventionalists encounter inferior collateral channels, they must anticipate sudden peri-procedural neurological decline. Accordingly, neurocritical care teams should tailor hemodynamics and blood pressure targets to sustain collateral perfusion pressure. Clinicians must maintain mean arterial pressure aggressively before complete recanalization occurs. Post-procedure monitoring protocols must also focus on detecting subtle neurological fluctuations promptly. Ultimately, recognizing deficient collateral channels enables intensive care specialists to preempt microvascular failure and optimize intensive care resource utilization. In conclusion, pretreatment angiographic collateral grading provides essential multidimensional insight that shapes procedural expectations, post-thrombectomy management, and accurate patient prognostication.
Collateral circulation delivers retrograde blood supply to ischemic brain tissue, sustaining the vulnerable penumbra before revascularization. Robust collaterals preserve neural tissue integrity, lower 90-day mortality, and double the chances of functional independence. Furthermore, adequate flow prevents microvascular collapse and reduces catastrophic reperfusion complications.
The ASITN/SIR system grades retrograde angiographic collateral flow from 0 to 4. Grade 0 indicates no collateral blood flow to the ischemic zone. Conversely, grade 4 represents complete, rapid retrograde arterial reconstitution. Clinicians utilize this grading system during initial diagnostic angiography to evaluate baseline tissue viability and guide prognostication.
Severe hypoperfusion starves microvascular endothelial cells of oxygen and essential nutrients, which disrupts the blood-brain barrier. Consequently, cellular ion pumps fail, accelerating cytotoxic and vasogenic edema formation. Following arterial reperfusion, damaged capillary beds leak fluid extensively into surrounding neural parenchyma, which precipitates life-threatening malignant cerebral edema.
Disclaimer: This content is for informational and educational purposes only and does not substitute professional medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Pretreatment angiographic collateral grade strongly predicts 90-day functional recovery, lower mortality, and reduced risks of malignant brain edema and hemorrhage following endovascular thrombectomy in anterior-circulation acute ischemic stroke.
last month

A qualitative study investigates whether traditional bedside clinical examinations still mirror contemporary physician practice. Findings support retaining long cases while reforming short cases toward hypothesis-driven assessments.
Yesterday

A pilot study evaluated WearDOXXN, a capillary microfluidic sweat patch, for noninvasive breast cancer monitoring by comparing sweat and serum CEA and PIP/GCDFP-15 levels.
Yesterday

India faces a massive diabetes burden with over 89 million adults affected. Managing blood sugar in isolation fails to prevent severe cardiorenal complications. Clinicians must adopt an integrated metabolic ecosystem that prioritizes early detection, multifactorial risk assessment, and personalized therapies.
Yesterday

The Gross Motor Function Classification System (GMFCS) stops its validated age bands at 18. Recent evidence emphasizes that evaluating adult cerebral palsy requires purpose-sensitive documentation combining adolescent ratings with dynamic profiles of mobility, fatigue, pain, and community participation.
Yesterday

A breakthrough 3D-printed piezoelectric collagen hydrogel activated by ultrasound accelerates diabetic wound repair, demonstrating 98.5% wound closure, robust antibacterial action, and enhanced vascularization without toxic chemical crosslinkers.
Yesterday
