

Loading, please wait...
Loading, please wait...
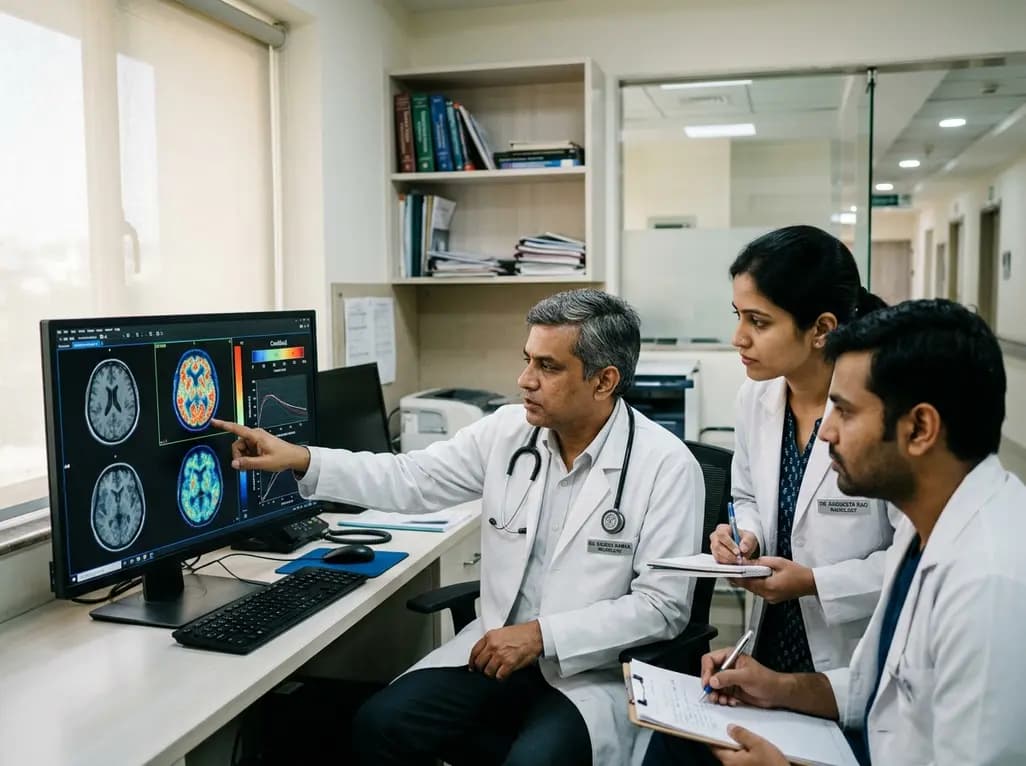
The clinical management of Alzheimer's disease has entered an era defined by disease-modifying therapies. Consequently, clinical workflows are shifting rapidly from syndromic suspicion to biological confirmation and targeted molecular interventions. In this evolving landscape, amyloid PET imaging has emerged as an indispensable cornerstone for diagnostic precision, patient selection, and therapeutic governance. Furthermore, molecular imaging allows clinicians to confirm amyloid pathology with high specificity before starting monoclonal antibodies. As these therapies expand worldwide, healthcare teams must design sustainable pathways to integrate advanced neuroimaging efficiently.
Historically, clinicians diagnosed Alzheimer's disease through bedside cognitive examinations and exclusion of secondary dementias. However, modern clinical practice demands objective confirmation of neuropathological hallmarks. Anti-amyloid monoclonal antibodies specifically require documented evidence of cortical fibrillar amyloid plaques before treatment initiation. Consequently, biomarker discovery has redefined the diagnostic pathway. Plasma biomarkers, such as phosphorylated tau species, provide scalable and accessible triage options. Nevertheless, blood tests may yield inconclusive or discordant results in atypical presentations. In such challenging cases, amyloid PET imaging delivers definitive confirmation of underlying disease. Furthermore, visualizing amyloid plaques eliminates diagnostic ambiguity and ensures therapy appropriateness. By confirming fibrillar amyloid deposits, clinicians avoid misdiagnosis and unwarranted therapeutic exposure. In addition, baseline scans verify that cognitive impairment stems from Alzheimer's disease rather than alternative neurodegenerative disorders. Therefore, integrating confirmatory PET protects patient safety while maximizing therapeutic efficacy across diverse clinical settings.
Visual interpretation of amyloid scans historically caused inter-reader variability among interpreting radiologists. To eliminate this inconsistency, nuclear medicine experts established the Centiloid scale as a standardized quantitative metric. The Centiloid scale rescales tracer uptake linearly, assigning zero to amyloid-negative controls and one hundred to typical Alzheimer's dementia. Consequently, this standardization allows direct comparisons across distinct radiotracers, such as florbetapir, florbetaben, and flutemetamol. Moreover, quantitative Centiloid metrics establish reproducible numerical thresholds for treatment eligibility and monitoring. Clinicians can accurately identify early amyloid accumulation and track cortical plaque burden across serial visits. In addition, quantitative cut-offs help physicians differentiate true-positive plaque deposition from non-specific white matter retention. As a result, memory clinics achieve uniform diagnostic criteria across varied imaging systems. Furthermore, imaging specialists can communicate objective numerical values to referring neurologists and geriatricians. This quantitative standard substantially elevates diagnostic accuracy and reinforces consistent therapeutic governance across hospital networks.
Patient selection for disease-modifying monoclonal antibodies demands rigorous multidimensional risk evaluation. Therefore, clinicians must interpret baseline molecular scans alongside structural magnetic resonance imaging and genetic testing. Amyloid-related imaging abnormalities, commonly termed ARIA, represent the most critical complication associated with anti-amyloid therapies. Specifically, ARIA presents as brain edema or sulcal effusions, alongside microhemorrhages and superficial siderosis. Apolipoprotein E epsilon 4 carriers face elevated ARIA risk, especially homozygous individuals. Consequently, baseline MRI protocols must rigorously evaluate pre-existing microbleeds, white matter hyperintensities, and siderosis. When neurologists combine amyloid quantification with structural MRI and APOE genotyping, they establish a reliable individualized risk-benefit profile. Furthermore, this comprehensive baseline profiling supports transparent shared decision-making with patients and families. Clinicians can clearly explain expected therapeutic benefits alongside potential radiological adverse events. Thus, multimodal baseline evaluation ensures that only properly stratified candidates proceed to active therapeutic infusions.
Beyond initial patient selection, molecular imaging provides unique utility for longitudinal therapeutic governance. Historically, Alzheimer's medications required continuous, indefinite administration without objective endpoints. In contrast, modern anti-amyloid monoclonal antibodies produce quantifiable plaque removal from the cerebral cortex. Consequently, serial molecular imaging provides objective visual and quantitative evidence of target engagement. When follow-up scans demonstrate plaque clearance below established Centiloid thresholds, clinicians can adopt response-adapted regimens. For instance, treatment discontinuation or dosing interval extension becomes viable once target pathology resolves. Moreover, structured therapy cessation reduces cumulative drug exposure and minimizes healthcare expenditure. Patients also face lower risk of delayed adverse events, such as persistent microvascular alterations. Furthermore, monitoring amyloid clearance enables clinicians to identify non-responders who may require alternative interventions. Therefore, longitudinal scans transform Alzheimer's care from static chronic prescribing into dynamic, biomarker-guided disease management.
Universal PET imaging for every cognitively impaired patient remains economically unsustainable for healthcare systems. Consequently, expert panels strongly recommend structured, stepwise diagnostic pathways. In this tiered framework, primary care physicians conduct initial cognitive evaluations and order blood-based biomarker tests. Scalable plasma biomarkers, such as phosphorylated tau, function as efficient frontline screening tools. Patients showing concordant abnormal fluid biomarkers and typical symptoms can advance smoothly through established care protocols. Conversely, clinicians reserve specialized amyloid PET for cases with borderline blood results or diagnostic discordance. Similarly, patients presenting with atypical symptoms, early symptom onset, or suspected mixed pathologies warrant advanced molecular imaging. To overcome regional access disparities, healthcare leaders should establish coordinated hub-and-spoke networks. Under this model, community clinics function as spokes that conduct initial evaluations and blood screening, referring candidates to centralized imaging hubs. Consequently, sustainable biomarker-driven treatment becomes accessible across diverse patient populations.
Amyloid PET imaging provides direct in vivo visualization of cortical amyloid plaques with high specificity. Because novel monoclonal antibodies exclusively target amyloid pathology, confirming plaque deposition is clinically mandatory. Furthermore, baseline imaging eliminates diagnostic uncertainty in atypical presentations and prevents inappropriate treatment exposure in patients lacking cerebral amyloid plaques.
The Centiloid scale provides an objective, 100-point standardized quantitative framework that normalizes differences among various amyloid radiotracers. Consequently, it eliminates visual interpretation bias and allows consistent longitudinal tracking. This numerical standardization helps clinicians define precise eligibility cut-offs and establish clear biological thresholds for therapeutic discontinuation.
Blood biomarkers provide an exceptional, accessible frontline screening tool, but they cannot entirely replace molecular PET imaging. In indeterminate or discordant clinical scenarios, molecular scans remain necessary for definitive confirmation. Additionally, amyloid PET uniquely quantifies regional cortical burden and evaluates post-treatment plaque clearance to guide treatment cessation.
Disclaimer: This content is for informational and educational purposes only and should not replace clinical judgment. Healthcare providers must exercise independent clinical decision-making. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The arrival of anti-amyloid therapies transforms Alzheimer's disease management into a biologically confirmed model. Learn how amyloid PET imaging enables accurate patient selection, standardized Centiloid staging, safety governance, and sustainable diagnostic pathways.
last month

A qualitative study investigates whether traditional bedside clinical examinations still mirror contemporary physician practice. Findings support retaining long cases while reforming short cases toward hypothesis-driven assessments.
Yesterday

A pilot study evaluated WearDOXXN, a capillary microfluidic sweat patch, for noninvasive breast cancer monitoring by comparing sweat and serum CEA and PIP/GCDFP-15 levels.
Yesterday

India faces a massive diabetes burden with over 89 million adults affected. Managing blood sugar in isolation fails to prevent severe cardiorenal complications. Clinicians must adopt an integrated metabolic ecosystem that prioritizes early detection, multifactorial risk assessment, and personalized therapies.
Yesterday

The Gross Motor Function Classification System (GMFCS) stops its validated age bands at 18. Recent evidence emphasizes that evaluating adult cerebral palsy requires purpose-sensitive documentation combining adolescent ratings with dynamic profiles of mobility, fatigue, pain, and community participation.
Yesterday

A breakthrough 3D-printed piezoelectric collagen hydrogel activated by ultrasound accelerates diabetic wound repair, demonstrating 98.5% wound closure, robust antibacterial action, and enhanced vascularization without toxic chemical crosslinkers.
Yesterday
