

Loading, please wait...
Loading, please wait...

Epidemiological evidence confirms a profound relationship between systemic metabolic dysfunction and progressive neurodegenerative decline. Specifically, evaluating the Alzheimer's risk in diabetes reveals a substantial escalation in cognitive vulnerability among affected individuals. As global diabetes rates increase rapidly, understanding these neurological implications is essential for clinical practice. Consequently, healthcare providers must expand conventional diabetes management beyond glycemic targets to protect long-term brain health.
A landmark meta-analysis led by researchers at Curtin University evaluated forty international cohort and case-control studies. Together, these investigations analyzed an extensive dataset encompassing over 27 million participants. The authors resolved previous ambiguities that stemmed from heterogeneous diabetes and dementia definitions. Therefore, their methodology isolated type 2 diabetes and clinically verified Alzheimer's disease cases with rigorous diagnostic precision.
Their pooled data demonstrated that individuals with type 2 diabetes face a 53 percent higher risk of developing Alzheimer's disease. Furthermore, the analysis calculated an absolute incidence rate of 4.71 cases per 1,000 person-years among diabetic cohorts. In practical terms, approximately five out of every 1,000 diabetic individuals will develop Alzheimer's disease annually.
Moreover, relative risk alone fails to capture the true clinical burden confronting aging populations. By pairing relative risk with incidence data, researchers have established the exact epidemiological impact facing healthcare systems worldwide. Subgroup evaluations confirmed that this elevated vulnerability persists across diverse populations regardless of sample size or geographic region. Consequently, proactive education empowers patients and families to identify subtle symptoms early. Thus, clinicians now possess reliable empirical benchmarks to guide early patient education and preventive planning.
Several biological pathways explain how dysregulated glucose metabolism damages cerebral architecture. Chronic peripheral insulin resistance directly impairs neuronal insulin receptor signaling across the central nervous system. Under normal physiological conditions, cerebral insulin supports synaptic plasticity, neuronal survival, and neurotransmitter balance. However, chronic hyperinsulinemia down-regulates blood-brain barrier transport mechanisms, ultimately reducing brain insulin availability.
Consequently, blunted cerebral insulin signaling accelerates the hyperphosphorylation of tau proteins. These abnormal tau structures form neurofibrillary tangles, which drive cortical synaptic destruction. Additionally, insulin-degrading enzyme clears both monomeric insulin and circulating amyloid-beta peptides. Because excessive circulating insulin competitively binds this enzyme, cerebral amyloid-beta clearance decreases significantly. As a result, toxic amyloid plaques accumulate within vulnerable brain regions such as the hippocampus.
Furthermore, persistent hyperglycemia triggers advanced glycation end-products that bind to microglial receptors. This interaction stimulates sustained neuroinflammation and increases reactive oxygen species production. In addition, defective glucose transport starves brain networks of fundamental cellular energy substrates. Therefore, these synchronized metabolic insults create an ideal microenvironment for accelerated neurodegenerative pathology. Ultimately, this destructive biological cascade converts silent metabolic injury into progressive, irreversible cognitive decline.
Beyond direct parenchymal amyloid pathology, microvascular injury plays a crucial role in accelerating cognitive decline. Diabetes frequently induces diffuse cerebral microangiopathy and endothelial cell dysfunction. Consequently, compromised vessel elasticity limits autoregulatory cerebral perfusion during fluctuating metabolic demands. Chronic hypoperfusion deprives white matter tracts of vital oxygen and essential nutrients.
Furthermore, disruption of the blood-brain barrier allows circulating inflammatory cytokines to enter cerebral tissue. This barrier breakdown causes localized microbleeds and accelerates lacunar infarct formation. Although pure Alzheimer's disease features distinct amyloid pathology, most elderly diabetic patients exhibit mixed dementia. In fact, subclinical cerebrovascular lesions synergize with neurofibrillary tangles to lower the threshold for clinical dementia expression.
Moreover, recurrent episodes of severe hypoglycemia exacerbate acute vascular and parenchymal damage. Brain tissue relies entirely on steady glucose delivery to sustain membrane electrical potentials. When circulating glucose drops precipitously, vulnerable hippocampal neurons undergo excitotoxic cell death. Consequently, structural white matter rarefaction accelerates functional disconnection across distant cortical regions. Therefore, glycemic volatility damages cerebral architecture through combined osmotic stress and ischemic injury. Additionally, persistent hypertension and dyslipidemia compound this vascular vulnerability. Hence, multi-target vascular stabilization is imperative for preserving long-term cerebral health.
These meta-analytic findings carry immediate ramifications for ambulatory care and chronic disease management. Traditionally, diabetic consultations focus heavily on peripheral neuropathy, nephropathy, and retinopathy. However, clinicians must expand this classic microvascular triad to include the central nervous system. Cognitive decline directly undermines a patient's capacity to execute complex self-care regimens.
For instance, impaired executive function compromises precise insulin dosing, dietary discipline, and scheduled clinic visits. Consequently, deteriorating cognition frequently manifests as unexplained glycemic instability or recurrent hypoglycemic episodes. Clinicians might mistakenly attribute poor glycemic control to behavioral non-compliance rather than recognizing early cognitive impairment. Therefore, routine surveillance protects patient safety and improves overarching metabolic control.
Furthermore, pharmacotherapy choices warrant careful reassessment in patients showing signs of cognitive vulnerability. Modern antidiabetic agents offer intriguing neuroprotective potential beyond glycemic control. Specifically, glucagon-like peptide-1 receptor agonists and sodium-glucose cotransporter-2 inhibitors demonstrate clear neurovascular benefits in clinical trials. In contrast, providers must prescribe sulfonylureas cautiously in older adults due to severe hypoglycemia risks. Consequently, tailored regimens minimize adverse events while optimizing neurological protection. Thus, individualized pharmacotherapy helps clinicians optimize both glycemic targets and cerebral health. Additionally, caregiver involvement reinforces medication safety and treatment adherence.
Integrating cognitive risk reduction into standard diabetes protocols requires pragmatic clinical workflows. First, providers should institute baseline cognitive evaluations for diabetic patients aged sixty and older. Brief validated instruments, such as the Montreal Cognitive Assessment or the Mini-Cog, fit smoothly into annual reviews. Early detection enables timely intervention before severe structural brain damage becomes irreversible.
Moreover, clinicians must aggressively address comorbid modifiable cardiovascular risk factors. Rigorous control of hypertension, dyslipidemia, and central obesity preserves cerebral microvascular perfusion. Simultaneously, lifestyle interventions deliver profound neuroprotective benefits. Structured aerobic exercise stimulates brain-derived neurotrophic factor, enhancing hippocampal neurogenesis and synaptic resilience. Furthermore, adopting the Mediterranean-DASH Intervention for Neurodegenerative Delay diet supplies essential polyphenols and reduces systemic inflammatory tone.
In addition, smoking cessation and adequate sleep hygiene play essential roles in maintaining glymphatic clearance. Clinicians should also involve family members early to recognize subtle alterations in executive capacity and spatial orientation. When physicians treat type 2 diabetes as an integrated systemic disorder, they safeguard both endocrine and cognitive longevity. Consequently, comprehensive preventive care transforms modern metabolic management into a potent shield against dementia. Therefore, routine clinical workflows must elevate brain health alongside cardiac and renal markers. Ultimately, bridging diabetes therapy with brain health safeguards independence and cognitive vitality.
Q1: Why does type 2 diabetes significantly increase the risk of Alzheimer's disease?
Type 2 diabetes elevates Alzheimer's risk through multiple biological pathways, including chronic neuroinflammation, cerebral microvascular disease, and impaired brain insulin signaling. When systemic insulin resistance develops, central insulin delivery declines, which accelerates tau protein hyperphosphorylation and prevents normal amyloid-beta clearance. Furthermore, persistent hyperglycemia generates harmful advanced glycation end-products and reactive oxygen species. Consequently, these combined metabolic insults accelerate neuronal apoptosis and cause progressive synaptic dysfunction within memory networks.
Q2: How frequently should clinicians screen diabetic patients for early cognitive impairment?
Clinical guidelines recommend initiating annual cognitive evaluations for patients with type 2 diabetes beginning at age sixty. Clinicians should employ validated, rapid assessment tools such as the Montreal Cognitive Assessment or the Mini-Cog during routine yearly reviews. However, if a patient experiences frequent unexplained hypoglycemia, deteriorating medication adherence, or sudden glycemic fluctuations, immediate cognitive testing is warranted. Early detection enables prompt intervention, preventing dangerous regimen non-adherence and supporting timely neuroprotective strategies.
Q3: Which antidiabetic medications offer potential neuroprotective benefits against dementia?
Emerging research indicates that glucagon-like peptide-1 receptor agonists and sodium-glucose cotransporter-2 inhibitors provide promising neuroprotective benefits. These modern agents reduce vascular inflammation, attenuate cerebral oxidative stress, and enhance blood-brain barrier integrity beyond their glucose-lowering actions. Conversely, clinicians should use sulfonylureas and older insulin regimens with heightened caution in vulnerable older individuals. Severe hypoglycemia sharply increases acute neuronal injury and accelerates cognitive decline. Therefore, therapy must balance optimal glycemic targets against hypoglycemic avoidance.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive systematic review of 40 studies covering 27 million participants confirms that individuals with type 2 diabetes face a 53% higher risk of Alzheimer's disease. Clinicians must actively prioritize early cognitive screening, glycemic stability, and neuroprotective interventions in routine metabolic care.
Today

A review of the evolution of maternal and pediatric therapeutics over two decades, examining developmental pharmacokinetics, lactation pharmacology, pediatric formulations, and evidence-based guidance for clinicians managing pregnancy and childhood diseases.
Today

New PEX-NET registry data reveal that the right atrial pressure to cardiac output (RAP/CO) slope during exercise right heart catheterization is an independent predictor of long-term mortality in pulmonary hypertension, outperforming conventional resting measures.
Today
Chronic nonbacterial osteomyelitis (CNO) is a pediatric autoinflammatory bone disorder. This review covers the French protocol, emphasizing whole-body MRI as the diagnostic gold standard, prudent biopsy avoidance, first-line NSAID treatment, and second-line biologic or bisphosphonate therapies for spinal lesions.
Today
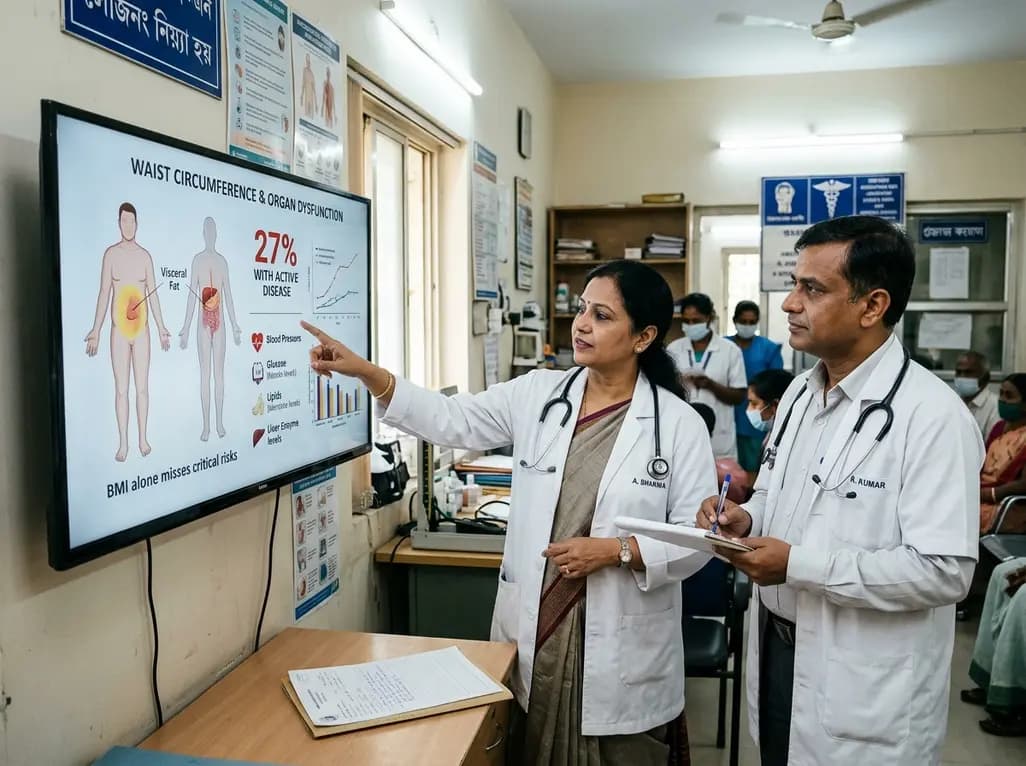
A landmark Nature study reveals that only 27% of individuals with obesity have active clinical disease. By incorporating waist circumference and organ dysfunction, this new diagnostic framework moves beyond BMI to prevent widespread misclassification and guide personalized metabolic intervention.
Today
