

Loading, please wait...
Loading, please wait...
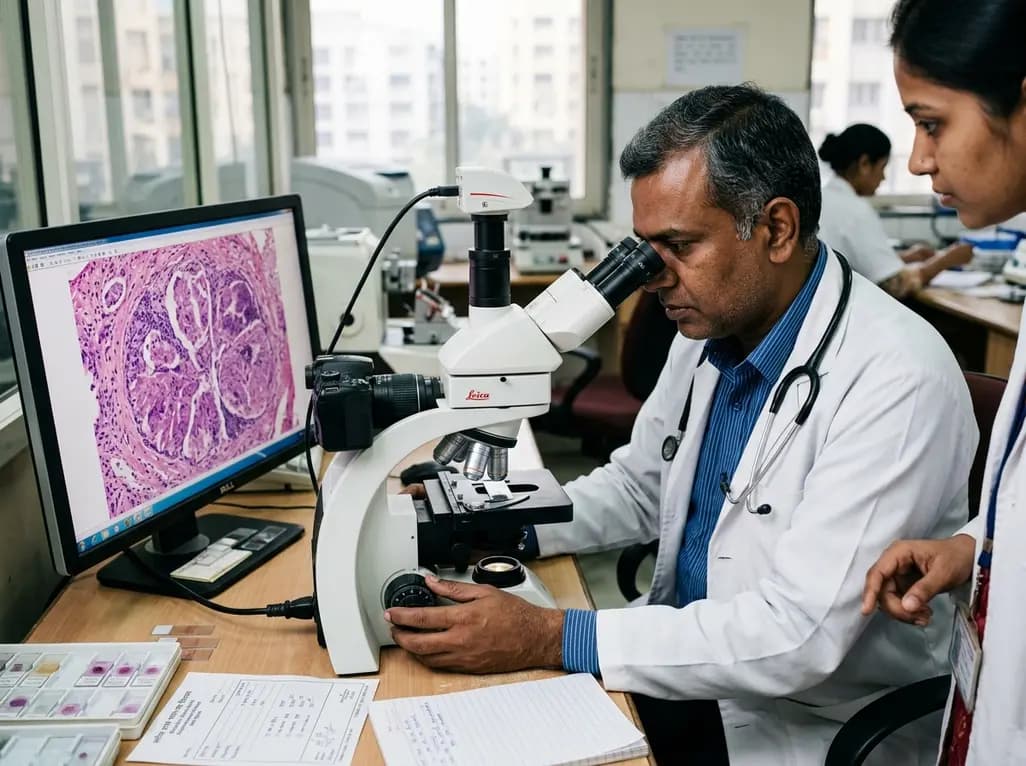
In diagnostic breast pathology, evaluating regional lymph node status remains vital for staging and treatment planning. Pathologists generally recognize metastatic invasive ductal carcinoma by its infiltration into lymphoid parenchyma without native architecture. However, recent observations reveal an intriguing histological presentation known as DCIS-like morphology within nodal deposits. In these instances, metastatic tumor nests simulate intraductal proliferations. They exhibit circumscribed borders, rounded contours, and occasional central necrosis resembling true ductal carcinoma in situ. Historically, clinicians assumed that benign epithelial transport or inadvertent displacement explained in situ-like lesions in lymph nodes. In contrast, modern molecular and immunohistochemical investigations prove that these structures represent true metastatic clones that actively adopt a pseudo-ductal architecture. Researchers analyzed 101 lymph node metastasis specimens from breast invasive ductal carcinoma patients to clarify this biological phenomenon. Strikingly, DCIS-like morphology appeared in nearly twenty-five percent of evaluated cases. Consequently, this high prevalence establishes that pseudo-in-situ growth patterns represent a recurrent phenomenon rather than an isolated histological artifact. Therefore, oncologists and surgical pathologists must recognize this deceptive entity to ensure accurate evaluation and appropriate clinical decision-making.
Distinguishing genuine non-invasive ductal proliferations from invasive carcinoma requires careful immunohistochemical profiling. Normally, myoepithelial markers like P63, Calponin, and smooth muscle actin delineate preserved ductal boundaries. However, in metastatic lymph node deposits displaying DCIS-like morphology, the peripheral cell layer demonstrates a peculiar immunophenotype. The investigative team evaluated classic basal and myoepithelial markers across all specimens. Notably, peripheral cells in a subset of metastatic nests expressed P63, cytokeratin 5/6, and smooth muscle actin. Conversely, none of the evaluated specimens demonstrated Calponin expression. This selective expression pattern proves that these peripheral cells are transformed carcinoma cells acquiring basal traits rather than normal trapped myoepithelium. Furthermore, researchers identified a statistically significant positive correlation between cytokeratin 5/6 positivity and the presence of these distinctive circumscribed nests. Because true nodal inclusions or displaced non-malignant tissues exhibit complete myoepithelial complements, finding incomplete or aberrant marker expression resolves diagnostic dilemmas. Pathologists must therefore employ comprehensive marker panels when encountering well-delineated metastatic nests. Consequently, evaluating basal cytokeratins prevents dangerous understaging and helps teams avoid mistaking an aggressive metastatic deposit for an indolent, benign ectopic inclusion.
Why do metastatic cancer cells form organized, duct-like nests inside distant lymphoid tissue? The biological basis appears closely tied to cancer stem cell plasticity. To investigate this pathway, researchers examined key stemness markers, including ALDH1A1, CD44, and SOX2, across metastatic breast cancer cohorts. Their findings demonstrated robust correlations between stemness marker upregulation and aggressive pathological indices. Specifically, elevated stemness marker expression occurred predominantly in tumors displaying higher histological grades, advanced pTNM stages, and substantial nodal burdens. Crucially, the presence of circumscribed pseudo-ductal nests strongly correlated with high stemness marker expression and basal-like differentiation. Cancer stem cells possess remarkable self-renewal capacity, multipotent differentiation potential, and therapeutic resistance. In lymph node microenvironments, these plastic tumor cells likely initiate localized redifferentiation programs. Consequently, they recreate pseudo-glandular structures that mimic normal mammary ductal architecture. Furthermore, this plastic transition equips tumor cells with superior survival advantages against host immunity and cytotoxic therapies. Therefore, identifying these distinct morphological nests in nodal specimens signals enhanced biological plasticity and systemic resilience.
The identification of pseudo-ductal patterns in nodal metastases carries substantial prognostic significance for clinicians managing breast cancer. In the comprehensive study cohort, these distinctive metastatic architectures correlated strongly with non-luminal breast cancer biology. Specifically, HER2-enriched and triple-negative breast cancer subtypes demonstrated an overrepresentation of these structured nodal nests. Because these non-luminal subtypes already present aggressive natural courses, the co-occurrence of unusual metastatic patterns further compounds patient risk. Furthermore, patients presenting with these nodal features suffered significantly higher disease recurrence rates compared to those with conventional infiltrative nodal metastases. Higher overall nodal burdens also tracked closely with this histology, pointing toward robust lymphatic dissemination potential. In routine clinical workflows, clinicians often treat nodal involvement uniformly according to absolute node counts and macrometastatic dimensions. Nevertheless, these latest findings suggest that qualitative morphological details within nodal deposits convey independent biological intelligence. Recognizing that structured nests portend elevated recurrence encourages clinicians to re-evaluate surveillance intervals and systemic treatment aggressiveness.
Integrating histological nuances into modern multidisciplinary breast cancer workflows optimizes patient risk stratification and post-surgical management. When pathologists identify circumscribed pseudo-in-situ growth in lymph nodes, they must communicate this feature clearly to treating oncologists. Given the heightened recurrence risk and elevated stemness features, these patients warrant rigorous post-operative monitoring. Furthermore, oncologists should consider whether standard adjuvant chemotherapy and targeted biological regimens adequately suppress residual stem-like clones. Because cancer stem cells frequently resist conventional cytotoxic drugs, ongoing research must explore therapeutic agents that target ALDH1A1, SOX2, and basal developmental pathways. In resource-conscious healthcare environments, utilizing routine immunohistochemical stains such as cytokeratin 5/6 and P63 provides accessible, cost-effective prognostic enrichment. Combining digital pathology with standardized immunohistochemistry helps hospital teams stratify patients into tailored risk categories without incurring prohibitive genomic sequencing expenses. Ultimately, recognizing atypical metastatic morphology bridges microscopic observations and individualized patient outcomes.
Pathologists differentiate these entities using targeted immunohistochemistry and architectural assessment. Benign inclusions typically show bland cytology, lack mitotic activity, and feature a complete outer layer expressing calponin, smooth muscle actin, and p63. In contrast, metastatic deposits showing pseudo-in-situ growth feature malignant cytologic atypia, lack true basement membranes, and show incomplete basal marker expression. Crucially, metastatic cells lack calponin entirely, confirming their malignant origin and ruling out benign transport.
The elevated recurrence risk stems directly from heightened cancer stem cell activity and aggressive tumor biology. Metastatic nests displaying this phenotype express high levels of stemness regulators, including ALDH1A1, CD44, and SOX2. Furthermore, these tumors strongly correlate with non-luminal subtypes like triple-negative and HER2-enriched cancers. These stem-like properties confer significant resistance to chemotherapy and radiation, enabling residual micrometastatic clones to survive adjuvant therapies and cause systemic relapse over time.
Currently, systemic therapy choices depend on primary tumor biology, hormone receptor status, HER2 expression, and overall TNM anatomical staging. While guidelines do not yet mandate separate drug regimens solely for pseudo-in-situ nodal patterns, detecting this histology highlights elevated recurrence potential. Clinicians should maintain high clinical vigilance, ensure optimal dosing of standard systemic regimens, avoid treatment de-escalation, and recommend closer post-treatment surveillance to detect early locoregional or distant disease recurrence.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Always consult a qualified healthcare provider for diagnosis and treatment decisions. Refer to the latest local and national guidelines for clinical practice.
References
Lin X et al. The clinical significance and mechanism of DCIS-like morphology of lymph node metastasis in breast cancer. Histol Histopathol. 2026 Sep 30. doi: 10.14670/HH-25-145. PMID: 42812127.
Harada S, et al. Ductal carcinoma in situ of the breast: morphological and molecular features implicated in progression. Biosci Rep. 2013;33(2):e00077.
Morrow M, et al. American Society of Clinical Oncology-Society of Surgical Oncology consensus guideline on margins for breast-conserving surgery with whole-breast irradiation in stages I and II invasive breast cancer. J Clin Oncol. 2014;32(14):1507-1515.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study reveals that DCIS-like morphology in breast invasive ductal carcinoma lymph node metastases occurs in 24.8% of cases and correlates with non-luminal subtypes, basal differentiation, enhanced tumor stemness, and elevated recurrence risk, providing critical prognostic insights for multidisciplinary teams.
3 weeks back

Failing to account for competing events like mortality in longitudinal geriatric studies produces biased risk estimates and misleading inferences. This review highlights key methodological principles, insights from the Precipitating Events Project, and practical approaches for clinical research appraisal.
Today

A study in JAMIA Open shows lightweight open-source reasoning LLMs achieve up to 95% sensitivity and accelerate evidence synthesis screening by nearly twentyfold, presenting a cost-effective, scalable AI solution for biomedical research and systematic reviews.
Today

A landmark study details how an enterprise pediatric remote patient management model expanded from a single cardiology pilot to 16 diverse specialty programs by combining centralized digital operations with specialty clinical leadership.
Today

A comparative review of tension band wiring and intramedullary screw fixation in thumb metacarpophalangeal arthrodesis, evaluating union rates, hardware complications, and clinical outcomes.
Today

A breakthrough ultrathin multimodal sensor decouples physical hemodynamic monitoring from disposable electrochemical calibration, achieving long-term wearable glucose prediction with 81.36% accuracy and a 9.12% MARD. This offers a robust, drift-free solution for outpatient metabolic surveillance.
Today
