

Loading, please wait...
Loading, please wait...

Managing treatment resistant schizophrenia represents one of the most formidable and pressing challenges in modern clinical psychiatry. Approximately thirty percent of individuals living with schizophrenia experience minimal or inadequate therapeutic response to standard non-clozapine antipsychotics. Consequently, these vulnerable individuals face unrelenting positive symptoms, persistent cognitive impairment, progressive psychosocial decline, and recurrent hospitalizations. In routine practice, clinicians establish treatment resistance retrospectively after evaluating multiple failed medication trials over protracted periods spanning months or years. Therefore, patients frequently endure debilitating therapeutic delays before receiving clozapine, the only evidence-based pharmacotherapy specifically approved for refractory disease. Recent advancements in multimodal neuroimaging provide crucial clinical opportunities to identify objective, reproducible biological markers much earlier in the disease trajectory. A comprehensive systematic review critically appraised structural, functional, and metabolic neuroimaging findings across ninety-four peer-reviewed clinical investigations. This landmark synthesis evaluated forty-four structural, eighteen functional, and thirty-two metabolic studies to delineate the pathophysiology of therapy resistance. Ultimately, the cumulative evidence reveals that refractory psychosis constitutes a distinct biological subtype rather than a mere severe extension of drug-responsive schizophrenia. Establishing reliable neuroimaging correlates will assist clinicians in initiating timely therapies.
Structural magnetic resonance imaging studies consistently demonstrate extensive morphometric abnormalities distinguishing treatment-resistant from treatment-responsive cohorts. Specifically, patients with refractory illness exhibit pronounced gray matter volume deficits within frontal cortical territories, limbic regions, and basal ganglia subregions. Furthermore, worldwide neuroimaging consortia identify robust bilateral hippocampal volume reductions alongside significant cortical surface area contraction in the left superior frontal gyrus. Importantly, these anatomical reductions correlate with illness severity and poor premorbid functioning. Longitudinal analyses indicate that cumulative lifetime exposure to typical or atypical antipsychotics does not solely drive these progressive structural anomalies. Instead, widespread prefrontal cortical thinning and lateral ventricular enlargement signify an intrinsic neurodevelopmental disturbance underpinning medication unresponsiveness. Moreover, subcortical investigations highlight distinct alterations in the putamen and thalamic nuclei that clearly separate non-responders from treatment-responsive individuals. Thus, structural neuroimaging demonstrates that refractory disease involves widespread fronto-striatal and limbic volume loss rather than circumscribed regional damage. Recognizing these anatomical patterns assists clinicians in conceptualizing treatment resistance as an extensive neurostructural phenotype that requires early identification. These structural deviations likely stem from early neurodevelopmental disturbances, explaining why standard therapies fail to halt disease progression.
Molecular imaging investigations provide compelling evidence regarding the biochemical mechanisms that separate treatment responders from non-responders. Standard schizophrenia pathophysiology classically features elevated presynaptic striatal dopamine synthesis capacity and elevated dopamine turnover. However, positron emission tomography and single-photon emission computed tomography demonstrate a conspicuous absence of striatal dopaminergic elevation in treatment-resistant patients. In fact, refractory individuals exhibit normal or diminished dopamine synthesis capacity relative to treatment-responsive controls. This biological divergence explains why standard antipsychotic medications, which primarily antagonize dopamine D2 receptors, fail to resolve positive psychotic symptoms in refractory cohorts. In contrast, emerging proton magnetic resonance spectroscopy studies demonstrate significant glutamatergic abnormalities in treatment resistance. Specifically, investigators observe elevated glutamate and combined glutamate-glutamine concentrations in the anterior cingulate cortex and medial prefrontal regions. Consequently, researchers hypothesize that cortical N-methyl-D-aspartate receptor hypofunction triggers downstream glutamatergic excitotoxicity and synaptic disconnectivity. These metabolic insights strongly support a non-dopaminergic, glutamatergic etiology in treatment-resistant illness. Therefore, developing novel pharmacological agents that directly modulate glutamatergic neurotransmission represents a promising avenue for refractory patients. Additionally, tracking these neurochemical shifts through spectroscopic imaging may soon help clinicians predict medication responsiveness early.
Functional neuroimaging investigations illustrate profound functional dysregulation across distributed brain circuits in refractory cohorts. Functional magnetic resonance imaging studies reveal marked alterations in resting-state functional connectivity, especially within default mode, salience, and frontoparietal networks. Furthermore, task-based functional studies demonstrate severe prefrontal hypoactivation alongside disorganized cortico-striatal and fronto-temporal connectivity during executive and working-memory tasks. Diffusion tensor imaging corroborates these functional breakdowns by documenting extensive microstructural white matter degradation. Specifically, fractional anisotropy reductions affect major cerebral tracts, including the corpus callosum, superior longitudinal fasciculus, uncinate fasciculus, and anterior corona radiata. Consequently, impaired structural tract integrity restricts efficient neural communication between executive prefrontal cortex regions and deeper subcortical hubs. These widespread connectivity breakdowns undermine cognitive performance, emotional salience processing, and affective control. As a result, patients experience persistent negative and cognitive symptoms that resist conventional dopamine blockade. Therefore, contemporary neuroimaging frames treatment resistance as an extensive system-level connectopathy rather than a localized neuroanatomical deficit. In addition, white matter tract disruptions correlate with illness chronicity, highlighting the urgent clinical need for neuroprotective therapeutic interventions. Consequently, restoring functional synchrony across these dysregulated pathways remains a key therapeutic target.
Although clozapine represents the gold standard pharmacotherapy for refractory psychosis, clinicians routinely delay its administration in day-to-day psychiatric care. In fact, clinical audits reveal that patients often endure diagnostic and therapeutic delays of three to five years before receiving clozapine. During this prolonged delay, patients experience recurrent psychotic relapses, progressive socio-occupational impairment, cognitive decline, and secondary neurobiological deterioration. Implementing neuroimaging biomarkers could eliminate these lengthy trial-and-error paradigms by identifying non-responders during their initial presentation. For example, demonstrating normal striatal dopamine synthesis or elevated cortical glutamate can confirm the refractory phenotype early. Consequently, psychiatrists can introduce clozapine promptly, stabilizing dysregulated neural networks and mitigating progressive gray matter loss. Furthermore, functional studies show that clozapine uniquely modulates aberrant fronto-striatal circuits and normalizes subcortical metabolic hyperactivity compared to other agents. Clinicians must also recognize ultra-treatment-resistant schizophrenia, where patients fail even clozapine, necessitating tailored augmentation approaches. Proactively identifying resistance signatures empowers healthcare providers to optimize clozapine dosing, monitor adverse effects, and incorporate comprehensive psychosocial rehabilitation without harmful therapeutic delays. Ultimately, proactive intervention improves long-term functional independence, social functioning, and overall quality of life.
In treatment-responsive schizophrenia, patients typically exhibit marked presynaptic dopamine synthesis capacity and elevated dopamine release within the associative striatum. Conversely, individuals with treatment-resistant illness demonstrate normal or even diminished striatal dopamine synthesis capacity. Because their psychosis does not stem from classic dopaminergic hyperactivity, conventional dopamine D2 receptor antagonist medications provide little therapeutic relief. This biological divergence underscores why alternative neurochemical pathways, notably glutamatergic dysregulation, drive the refractory phenotype.
Clinicians frequently delay clozapine administration because international treatment guidelines require sequential trials of at least two different antipsychotics at adequate doses and durations. Consequently, confirming treatment failure often takes several years. Furthermore, physician apprehension regarding severe adverse events, including agranulocytosis, myocarditis, severe constipation, and seizures, fosters clinical inertia. Routine hematological monitoring requirements also create administrative barriers. These prolonged delays subject patients to persistent psychosis and ongoing socio-occupational decline before receiving effective therapy.
Currently, neuroimaging tools cannot definitively diagnose treatment resistance at first presentation in routine clinical practice. Although research demonstrates robust group-level differences in cortical thickness, frontal glutamate concentrations, and striatal dopamine uptake, individual-level predictive accuracy remains insufficient for standalone clinical diagnosis. Nonetheless, integrating machine learning algorithms with structural MRI and spectroscopic data shows immense promise. Standardized imaging protocols will likely enable early biomarker-guided stratification in the near future, drastically reducing empirical treatment delays.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review indicates that treatment resistant schizophrenia exhibits distinct structural, functional, and metabolic neuroimaging alterations. Refractory illness lacks classic striatal dopaminergic hyperactivity, implicating glutamatergic pathways and highlighting the need for earlier clozapine intervention.
Today
A cross-sectional study of 543 patients evaluated the clinical and economic impact of hemophilia inhibitors, revealing higher annual bleeding rates, increased treatment complexity, and severe orthopedic disability, highlighting the need for routine inhibitor screening and modern prophylactic strategies.
Today

Doctors at AIIMS New Delhi have achieved a historic milestone by performing India's first open prenatal myelomeningocele repair on a 25-week unborn fetus. This landmark multidisciplinary procedure provides vital neuroprotective benefits, lowers hydrocephalus risks, and transforms maternal-fetal medicine nationwide.
Today

A randomized crossover trial reveals that daily fresh watermelon consumption significantly reduces baseline TMAO levels and favorably modulates lipid profiles, lowering triglycerides and LDL cholesterol in adults with overweight and obesity.
Today
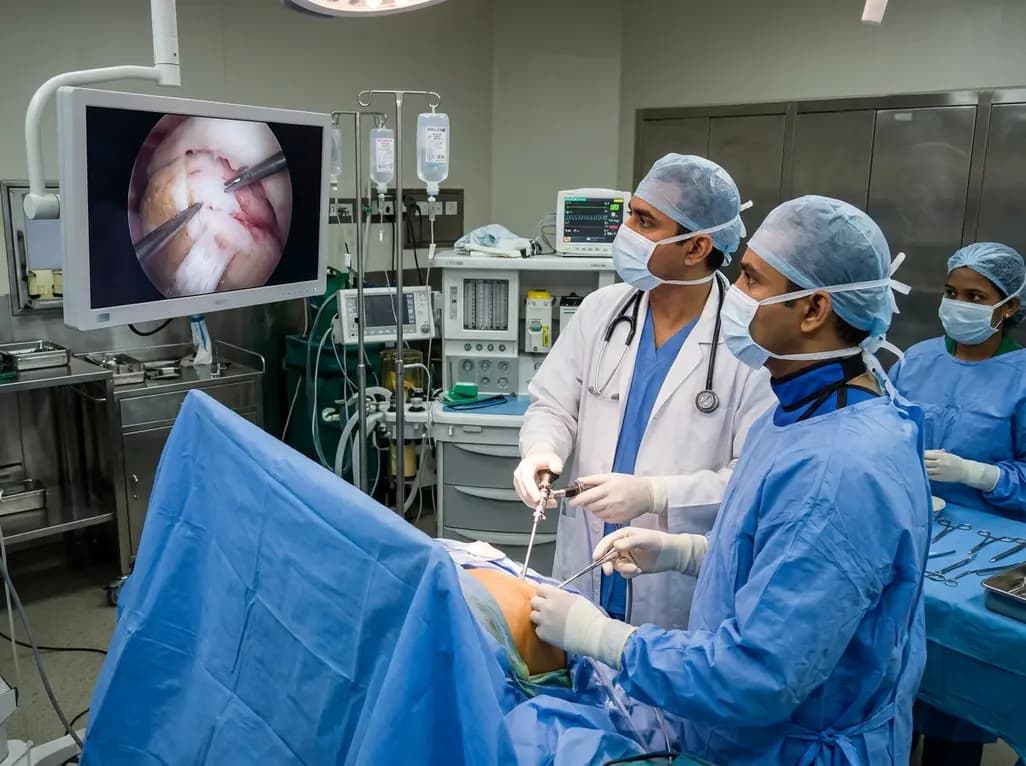
Discover how all-arthroscopic repair using a resorbable bioinductive bovine collagen implant offers a reproducible biologic solution for partial-thickness upper border subscapularis tears, enhancing healing while preserving native tendon architecture.
Today

A large-scale retrospective cohort study demonstrates that GLP-1 receptor agonists significantly reduce all-cause hospitalizations, alcohol-related admissions, major cardiovascular events, and mortality in patients with overweight or obesity and alcohol use disorder, providing profound clinical insights.
Today
