

Loading, please wait...
Loading, please wait...

Managing congenital bleeding disorders requires lifelong clinical vigilance and precise therapeutic monitoring. Among all treatment complications, the emergence of hemophilia inhibitors presents the most formidable obstacle for clinicians and patients. Inhibitors represent neutralizing alloantibodies that target exogenous clotting factor concentrates. Consequently, these antibodies render conventional replacement regimens largely ineffective. A comprehensive cross-sectional study led by He and colleagues evaluated 543 Chinese patients with hemophilia. Their research investigated real-world disease burden and economic outcomes linked to inhibitor development. Notably, the study revealed marked clinical disparities between patient cohorts. Inhibitors significantly exacerbate hemorrhage rates, accelerate joint damage, and inflate healthcare expenditures. For clinicians in India and other developing nations, these real-world data offer vital practical guidance. Specifically, the findings underline the urgency of regular screening and proactive intervention.
The investigation evaluated 543 individuals diagnosed with hemophilia across medical facilities in China through December 2022. Overall, the participant cohort had a mean age of 26.0 ± 14.8 years, and 99.63% were male. Importantly, researchers detected marked differences in underlying disease severity between the cohorts. The inhibitor-positive cohort exhibited a significantly higher proportion of severe baseline hemophilia than the inhibitor-negative group. Specifically, severe hemophilia affected 93.64% of inhibitor-positive patients compared to 76.56% of non-inhibitor patients (p < 0.001). This stark disparity reflects a clear pathophysiological mechanism. Patients with severe genetic deletions lack endogenous circulating factor protein. Consequently, their immune systems readily perceive infused factor concentrates as foreign antigens. Furthermore, intensive early treatment episodes during childhood amplify inflammatory danger signals. As a result, neutralizing alloantibodies develop rapidly during the first fifty exposure days. Therefore, hematologists must prioritize frequent antibody surveillance in all newly diagnosed severe hemophilia patients. Early identification enables prompt therapeutic adjustments before clinical joint destruction accelerates.
Neutralizing alloantibodies severely impair hemostatic function, leading to frequent spontaneous hemorrhage into synovial joints and soft tissues. In this cross-sectional cohort, inhibitor-positive individuals experienced a markedly higher bleeding burden. Specifically, the median annual bleeding rate reached 20 episodes among inhibitor-positive patients versus 12 episodes in inhibitor-negative controls (p = 0.008). Consequently, recurrent joint bleeds trigger relentless chronic synovial inflammation and progressive cartilage degradation. The study uncovered alarming levels of cumulative musculoskeletal disability throughout the surveyed population. Overall, 54.88% of all participants possessed official government disability certificates. Moreover, physical disability rates escalated dramatically with advancing age. Remarkably, nearly 90% of hemophilia patients older than 30 years carried verified disability status. This striking finding demonstrates that uncontrolled bleeding produces severe, lifelong functional impairment. In addition, chronic hemophilic arthropathy causes persistent debilitating pain and severe mobility restrictions. Clinicians must therefore implement aggressive bleeding management early in life. Preventing intra-articular bleeding remains the only definitive way to preserve long-term joint function and maintain patient independence.
Managing patients with neutralizing inhibitors demands complex, labor-intensive clinical strategies. The study documented heavy treatment burdens among individuals attempting regular factor administration. In the surveyed cohort, the mean annual prophylaxis infusion frequency reached 127.71 ± 54.11 infusions per year. This frequency corresponds to approximately 2.5 intravenous infusions each week. Furthermore, average clotting factor consumption per infusion measured 21.16 ± 8.28 IU per kilogram. Maintaining such frequent intravenous therapy poses substantial practical challenges for patients and their families. Specifically, young children often develop peripheral venous access complications, requiring surgical central line placement. In addition, frequent home infusions demand considerable parental time, causing caregiver strain and lost employment hours. When traditional factor therapy fails to stop acute bleeds, physicians must administer bypassing agents promptly. However, bypassing agents require meticulous dosing schedules and close clinical supervision. As a result, treatment fatigue frequently undermines patient compliance over time. Clinical teams must therefore offer continuous education and comprehensive psychological support to sustain treatment adherence.
Inhibitor development creates massive financial strains on healthcare infrastructure and family finances. The Chinese survey revealed that the average annual per-patient medical cost reached CNY 520,415 ± 773,627. Crucially, direct factor concentrate acquisition represented the single largest cost component. The mean annual expenditure for factor therapy alone totaled CNY 279,402 ± 627,427 per patient. Consequently, families facing high out-of-pocket costs experience profound financial distress. Moreover, inhibitor-positive patients require expensive bypassing concentrates, prolonged hospitalizations, and specialized orthopedic interventions. These cumulative expenses quickly overwhelm standard health insurance coverage in developing healthcare systems. In addition, families face indirect financial losses due to reduced workplace productivity and lost wages. Therefore, healthcare administrators must recognize that inadequate early prophylaxis produces far higher long-term clinical and economic costs. Proactive management protocols reduce catastrophic bleeding episodes and prevent costly emergency hospital admissions. Ultimately, health economists and policymakers must design sustainable reimbursement frameworks that ensure continuous therapy for vulnerable hemophilia cohorts.
The clinical observations from this registry offer direct lessons for hematology practice across India and similar emerging economies. In India, hemophilia remains underdiagnosed in rural communities, where diagnostic laboratory access remains restricted. Furthermore, many patients receive episodic, on-demand replacement therapy rather than structured primary prophylaxis. As factor availability increases through government procurement programs, clinicians must anticipate a rising incidence of inhibitor formation. Consequently, establishing decentralized diagnostic facilities equipped with the Nijmegen-modified Bethesda assay is critical. Clinicians should test pediatric patients regularly during their initial fifty exposure days to catch low-titer inhibitors early. Additionally, non-factor therapies like emicizumab represent transformative options for patients with persistent factor VIII inhibitors. Emicizumab provides subcutaneous, low-frequency prophylaxis that effectively bypasses inhibitor antibodies without requiring intravenous access. While initial medication acquisition requires dedicated funding, preventing hemarthroses averts catastrophic orthopedic surgery and emergency admissions. Finally, multidisciplinary care centers combining hematologists, physical therapists, and orthopedic specialists are essential to optimize long-term clinical outcomes.
Inhibitor antibodies develop when the patient's immune system identifies infused exogenous clotting factors as foreign proteins. Consequently, plasma cells produce neutralizing alloantibodies, predominantly IgG4 and IgG1 subclasses, targeting functional epitopes on factor VIII or IX. Genetic mutations, particularly large deletions and nonsense mutations, significantly elevate this immune risk. Furthermore, early intensive treatment courses, frequent surgical interventions, and severe tissue trauma amplify inflammatory signals that drive alloantibody production.
Clinicians perform routine screening using the Nijmegen-modified Bethesda assay to measure neutralizing antibody titers accurately. World guidelines advocate testing after every five to ten exposure days during initial replacement therapy. Additionally, hematologists test patients immediately before elective surgical procedures or whenever a patient exhibits diminished clinical response to usual factor doses. Prompt detection ensures timely escalation to bypassing agents or bispecific monoclonal therapy, which prevents irreversible joint hemorrhage and life-threatening bleeding episodes.
Modern management combines bypassing agents, such as recombinant activated factor VII and activated prothrombin complex concentrates, to treat acute hemarthroses. Additionally, clinicians prescribe emicizumab, a bispecific monoclonal antibody bridging factors IXa and X, for highly effective bleed prophylaxis regardless of inhibitor status. Meanwhile, immune tolerance induction protocols administer daily high-dose clotting factors to suppress neutralizing antibodies permanently. Multidisciplinary care teams integrate comprehensive physiotherapy and orthopedic rehabilitation to protect musculoskeletal integrity throughout therapy.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A cross-sectional study of 543 patients evaluated the clinical and economic impact of hemophilia inhibitors, revealing higher annual bleeding rates, increased treatment complexity, and severe orthopedic disability, highlighting the need for routine inhibitor screening and modern prophylactic strategies.
Today

Doctors at AIIMS New Delhi have achieved a historic milestone by performing India's first open prenatal myelomeningocele repair on a 25-week unborn fetus. This landmark multidisciplinary procedure provides vital neuroprotective benefits, lowers hydrocephalus risks, and transforms maternal-fetal medicine nationwide.
Today

A randomized crossover trial reveals that daily fresh watermelon consumption significantly reduces baseline TMAO levels and favorably modulates lipid profiles, lowering triglycerides and LDL cholesterol in adults with overweight and obesity.
Today
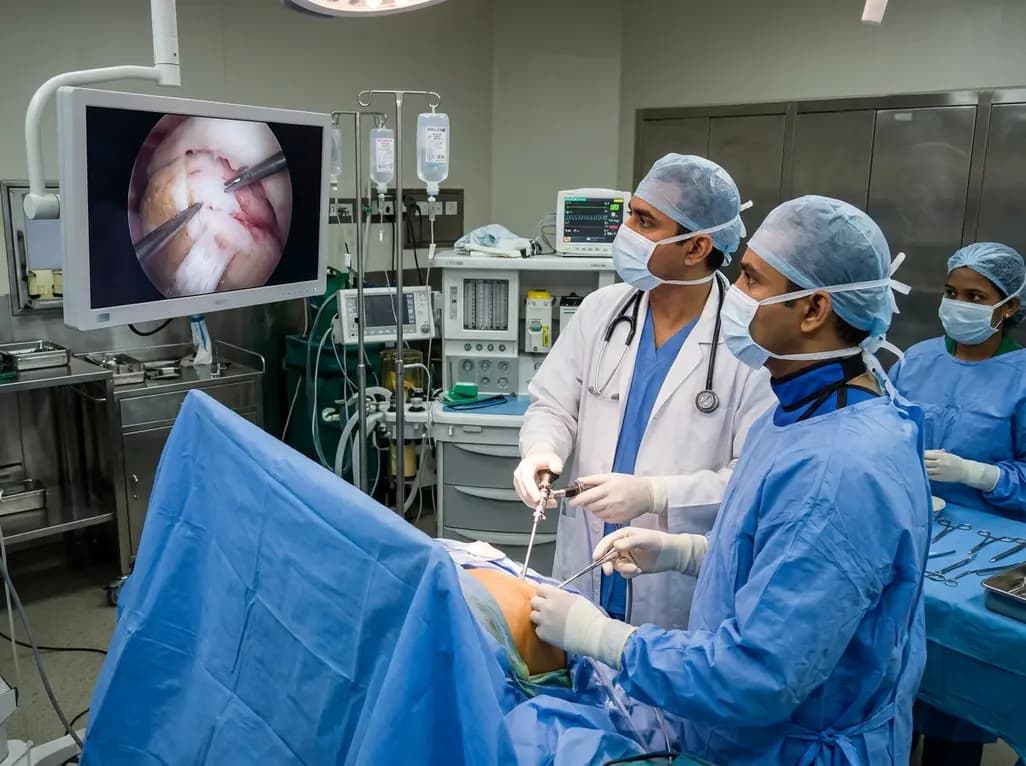
Discover how all-arthroscopic repair using a resorbable bioinductive bovine collagen implant offers a reproducible biologic solution for partial-thickness upper border subscapularis tears, enhancing healing while preserving native tendon architecture.
Today

A large-scale retrospective cohort study demonstrates that GLP-1 receptor agonists significantly reduce all-cause hospitalizations, alcohol-related admissions, major cardiovascular events, and mortality in patients with overweight or obesity and alcohol use disorder, providing profound clinical insights.
Today
