

Loading, please wait...
Loading, please wait...

Multiple sclerosis frequently presents during peak reproductive years, introducing complex physical and psychosocial burdens. Among these challenges, sexual dysfunction in MS remains remarkably prevalent, affecting up to eighty percent of women. Despite this profound impact on overall quality of life, clinicians rarely address intimate health during routine outpatient evaluations. Consequently, female patients often endure persistent silence, distress, and compromised relationship stability. Healthcare professionals must proactively acknowledge sexual well-being as a cornerstone of holistic neurological care. Therefore, understanding the intersection between neuroimmunology, intimate wellness, and family planning is critical for optimizing patient outcomes across the reproductive lifespan.
Clinicians categorize sexual impairment in female patients into primary, secondary, and tertiary manifestations. Specifically, primary dysfunction stems directly from demyelinating lesions along the central nervous system pathways that govern sexual response. Demyelination within spinal tracts and cerebral networks impairs genital sensation, dampens orgasmic capacity, and reduces physiologic lubrication. In addition, secondary dysfunction arises from general physical symptoms related to the disease course. For example, debilitating fatigue, spasticity of the adductor muscles, muscle weakness, and neurogenic bladder or bowel symptoms severely impede sexual expression. Many patients experience substantial urinary urgency or fear involuntary incontinence during intimacy, which markedly elevates performance anxiety. Furthermore, chronic central neuropathic pain and medication-induced side effects, notably from selective serotonin reuptake inhibitors, exacerbate these physical barriers. Finally, tertiary dysfunction encompasses the profound emotional and psychological repercussions of a chronic illness. Mood disturbances, including clinical depression and generalized anxiety, commonly impair self-esteem. Additionally, perceived loss of bodily autonomy, altered body image, and chronic fatigue can disrupt interpersonal communication with partners. Because these three tiers continuously interact, clinicians must recognize that sexual health concerns rarely emerge from a single isolated trigger.
Although sexual symptoms occur frequently, patients often hesitate to initiate conversations regarding intimate concerns. Similarly, many clinicians avoid these topics due to time constraints, lack of formal training, or personal embarrassment. Therefore, healthcare teams must normalize discussions surrounding intimacy early in the disease trajectory. Incorporating brief screening questions into routine clinical consultations helps overcome these communication hurdles. For instance, asking simple, open-ended questions during standard neurological visits provides patients with permission to disclose intimate difficulties. Moreover, validated patient-reported outcome measures offer objective insights into specific symptom patterns. Clinicians frequently utilize the Female Sexual Function Index to evaluate desire, arousal, lubrication, orgasm, satisfaction, and pain. In addition, the Multiple Sclerosis Intimacy and Sexuality Questionnaire provides targeted assessment across primary, secondary, and tertiary domains. Utilizing these structured tools facilitates longitudinal monitoring and helps clinicians gauge the success of targeted therapeutic interventions. Furthermore, comprehensive evaluations must systematically document concurrent pharmacotherapy, bladder function, and psychological well-being. Ultimately, standardized clinical screening bridges the gap between patient suffering and proactive medical management, ensuring that subtle complaints receive timely clinical intervention.
Because multiple sclerosis predominantly affects women during childbearing years, family planning demands thoughtful, proactive clinical coordination. Preconception counseling must evaluate disease stability, optimize disease-modifying therapies, and explicitly address sexual function. Unfortunately, intimate dysfunction often directly impairs natural conception by reducing intercourse frequency and inducing severe coital pain. Furthermore, heightened levels of disability, chronic exhaustion, and fears regarding disease inheritance create substantial psychological barriers to starting a family. Consequently, fertility evaluations should carefully distinguish between physiologic subfertility and intimacy-related conception challenges. Clinicians should educate patients that multiple sclerosis does not inherently diminish ovarian reserve or female biological fertility. Nevertheless, uncontrolled spasticity, pelvic floor hypertonicity, and severe dyspareunia can make timed intercourse physically challenging or impossible. Additionally, the strategic timing of disease-modifying therapies requires detailed discussions regarding contraceptive choices and planned pregnancy windows. Multidisciplinary teams must balance maternal neurological stability with fetal safety during conception attempts. Therefore, addressing sexual wellness during preconception visits preserves patient autonomy, minimizes unnecessary reproductive distress, and supports couples throughout their reproductive journey.
Effective clinical management of intimate dysfunction requires an individualized, multimodal therapeutic framework. First, clinicians must aggressively optimize secondary neurological symptoms that interfere with physical intimacy. For instance, prescribing appropriate antispasmodic agents or local botulinum toxin injections can alleviate severe adductor muscle spasticity. Similarly, scheduling sexual activity during peak energy hours effectively counters debilitating daily fatigue. Moreover, managing neurogenic lower urinary tract symptoms with scheduled voiding or anticholinergic therapy prevents disruptive coital incontinence. Pelvic floor physical therapy represents another highly effective intervention for women experiencing hypertonicity or dyspareunia. Targeted myofascial release, biofeedback, and specialized pelvic muscle training significantly decrease intercourse-related discomfort while restoring local tissue flexibility. In addition, topical lubricants and localized vaginal estrogen formulations successfully combat mucosal dryness and genital atrophy. When orgasmic difficulties or sensory loss dominate, clinicians can recommend mechanical stimulation devices or clitoral vacuum therapy to enhance blood flow. Furthermore, couples-based psychological counseling and cognitive behavioral therapy effectively address performance anxiety and relationship strain. Ultimately, combining pharmacologic adjustments with physical rehabilitation delivers the greatest improvements in intimate well-being.
The transition through pregnancy and the postpartum period introduces dynamic physiological shifts for women with multiple sclerosis. During pregnancy, systemic immune tolerance often confers a natural reduction in neuroinflammatory disease activity. However, mechanical changes, lumbar strain, and advancing gestational fatigue can compound baseline neuromuscular deficits, creating novel intimacy hurdles. In contrast, the postpartum phase carries a well-established vulnerability to disease relapses and worsening emotional distress. Sleep fragmentation, infant care demands, and hormonal changes exacerbate vaginal dryness and pelvic floor pain. Consequently, postpartum sexual health frequently deteriorates if clinicians fail to provide scheduled follow-up assessments. Furthermore, substantial gaps persist in the scientific literature regarding longitudinal sexual trajectories across the perinatal timeline. Most published studies remain cross-sectional, offering limited insight into preventative strategies for young mothers. Prospective clinical registries and randomized controlled trials evaluating multidisciplinary interventions are desperately needed. Hence, future research must examine how novel neuroprotective regimens and structured pelvic rehabilitation preserve intimacy throughout motherhood. Establishing integrated care models will ultimately guarantee that women receive continuous, evidence-based support through every reproductive phase.
Female sexual dysfunction affects approximately forty to eighty percent of women living with multiple sclerosis. Prevalence rates remain substantially higher than those observed in the general population. This widespread dysfunction occurs because demyelinating lesions disrupt neural pathways that control genital sensation and vascular arousal. Additionally, secondary symptoms like extreme exhaustion, muscle spasticity, and bladder dysfunction significantly exacerbate intimate difficulties, leaving many young women with chronic, unaddressed physical and emotional challenges.
Clinicians frequently utilize validated instruments to measure intimate health in multiple sclerosis. The Female Sexual Function Index serves as a widely accepted tool evaluating desire, lubrication, orgasm, and pain. In addition, the Multiple Sclerosis Intimacy and Sexuality Questionnaire specifically assesses primary, secondary, and tertiary disease complications. Incorporating these standardized questionnaires into routine clinical reviews helps providers identify hidden symptoms, track therapeutic progress, and tailor multifaceted interventions to individual patient needs.
Managing dyspareunia requires a multifaceted treatment approach tailored to the underlying pathology. Clinicians routinely recommend high-quality silicone or water-based lubricants to alleviate friction during sexual activity. Furthermore, topical vaginal estrogen therapies effectively restore mucosal elasticity and moisture in hypoestrogenic tissues. When pelvic hypertonicity causes persistent intercourse pain, targeted pelvic floor physical therapy and biofeedback successfully relax hypertonic musculature. Additionally, optimizing antispasmodic medications helps mitigate involuntary adductor muscle contractions during intimacy.
Disclaimer: This content is for informational and educational purposes only and should not be construed as medical advice or replace professional healthcare judgment. Clinical practices, treatment protocols, and regulatory approvals vary globally; healthcare providers must exercise independent clinical discretion. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Sexual dysfunction affects a high proportion of reproductive-age females with multiple sclerosis. This comprehensive review highlights multi-tier etiologies, proactive clinical screening tools, preconception counseling considerations, and integrated therapeutic options across multidisciplinary care pathways.
Today
A recent cross-sectional study reveals that prolonged residence at high altitude significantly escalates foot frostbite risk among lowland migrants, with chronic mountain sickness acting as a significant physiological mediator through hyperviscosity and microcirculatory stasis.
Today
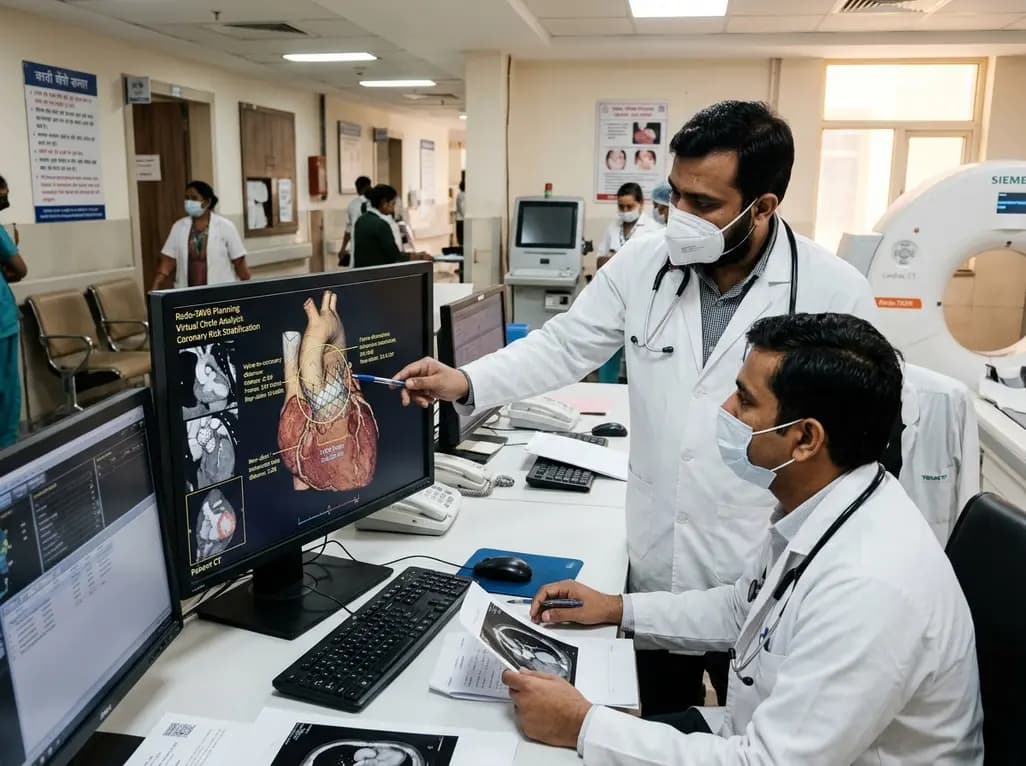
A multicenter study evaluating paired cardiac CT scans reveals that the virtual circle method reliably predicts index transcatheter valve frame expansion and changes in valve-to-aorta distance during redo-TAVR, offering accurate or conservative coronary risk stratification in 85% of cases.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Today

India is poised to transform chronic disease management through wearable health technology. Discover how continuous remote monitoring and predictive algorithms empower clinicians to detect early cardiovascular signals, personalize metabolic interventions, and deliver equitable preventive care across populations.
Today
