

Loading, please wait...
Loading, please wait...

Predicting long-term treatment retention remains a major challenge when managing seropositive rheumatoid arthritis. Clinicians frequently evaluate serological markers to guide disease prognosis and therapeutic strategies. Therefore, recent multicentre evidence demonstrates that baseline autoantibody titres profoundly influence rheumatoid factor biologic persistence across targeted drug classes. While autoimmune serology dictates general systemic inflammation, specific molecular interactions between circulating antibodies and therapeutic molecules govern therapeutic survival. Consequently, rheumatologists must re-examine how high baseline autoantibodies alter real-world biologic durability over time.
Rheumatoid factors predominantly comprise pentameric IgM antibodies directed against the crystalline fragment of human IgG. Because therapeutic monoclonal antibodies frequently feature standard IgG1 constant regions, high circulating autoantibodies can cross-react with these biologic drugs. This interaction forms high-molecular-weight immune complexes that stimulate rapid hepatic and reticuloendothelial clearance. As a result, circulating drug concentrations drop below effective therapeutic thresholds. In contrast, bioengineers designed certolizumab pegol as a recombinant Fab fragment lacking any Fc domain. Instead, the molecule utilizes a forty kilodalton polyethylene glycol chain to prolong plasma half-life. Because certolizumab pegol completely lacks the target epitope for rheumatoid factor, it completely evades Fc-mediated immune complex clearance. Complete monoclonal antibodies, such as standard TNF blockers and interleukin antagonists, remain inherently vulnerable to this targeted clearance mechanism. Therefore, high rheumatoid factor concentrations can accelerate drug elimination. Additionally, this accelerated clearance often promotes the formation of neutralizing anti-drug antibodies. Thus, understanding molecular structural differences clarifies why biologic survival varies substantially across distinct biologic classes in seropositive cohorts. Clinicians must consider these biochemical properties when selecting long-term targeted therapies.
The multicentre observational study evaluated five hundred forty-one patients with rheumatoid arthritis across multiple tertiary centres. Investigators followed patients receiving certolizumab pegol, rituximab, tocilizumab, or abatacept within their first three biologic lines. Furthermore, four hundred thirty-six individuals possessed verifiable baseline rheumatoid factor measurements and comprised the primary analytical group. Investigators stratified participants using an established high-titre threshold of greater than two hundred three international units per millilitre. High baseline titres appeared in thirty-one percent of these stratified patients. The researchers utilized robust Kaplan-Meier survival curves and competing-risk regression models to evaluate drug discontinuation specifically due to secondary inefficacy. Strikingly, shorter drug retention occurred almost exclusively within the tocilizumab cohort. Patients on tocilizumab with elevated autoantibodies achieved a median persistence of only 1.18 years compared to 2.03 years in patients with lower titres. Conversely, high serological titres did not compromise treatment survival among patients receiving certolizumab pegol or rituximab. Therefore, this observational dataset provides compelling clinical proof that serological burden exerts agent-specific influences on biologic durability. Furthermore, these findings emphasize that autoantibody levels do not affect all targeted therapies uniformly.
Multivariable competing-risk analyses revealed a dramatic association between elevated serological titres and tocilizumab treatment failure. Specifically, baseline rheumatoid factor exceeding two hundred three units independently predicted tocilizumab discontinuation caused by secondary inefficacy, yielding an adjusted hazard ratio of 4.92. This nearly fivefold risk elevation underscores a critical clinical vulnerability during long-term interleukin-6 receptor blockade. Interestingly, baseline autoantibody status did not impair early clinical responses at six or twelve months. Patients achieved comparable disease activity scores regardless of baseline titres during early treatment. However, secondary non-response emerged progressively as therapy continued beyond the first year. Accelerated clearance of the intact IgG1 monoclonal antibody over time likely leads to trough drug concentrations dipping below therapeutic levels. Consequently, subtherapeutic drug exposure may facilitate immunological breakthrough and loss of anti-inflammatory control. In contrast, abatacept cohorts exhibited too few discontinuation events to permit precise multivariable estimations. Nevertheless, the pronounced hazard observed with tocilizumab demands proactive vigilance from treating physicians. Rheumatologists must anticipate delayed secondary failure when deploying intact monoclonal antibodies in seropositive cohorts. Therefore, routine monitoring beyond the first year becomes paramount.
The contrasting retention patterns of certolizumab pegol and rituximab offer vital reassurance for clinical practice. Certolizumab pegol demonstrated stable persistence regardless of baseline autoantibody levels. Because certolizumab pegol lacks an Fc domain, high-titre autoantibodies cannot accelerate its clearance or trigger immune complex destruction. Furthermore, clinical trials confirm that certolizumab pegol maintains consistent pharmacokinetic parameters and clinical efficacy across all autoantibody quartiles. Similarly, rituximab demonstrated sustained durability that was entirely unaffected by high baseline titres. Because rituximab targets CD20-positive B cells, it eliminates the cellular precursors responsible for producing rheumatoid factor. Consequently, circulating autoantibody levels decline rapidly following B-cell depletion, eliminating potential neutralizing autoantibodies. Rituximab thereby systematically suppresses the very immunological machinery that might otherwise accelerate drug clearance. Therefore, both agents exhibit distinct biological immunity against the detrimental clearance mechanisms driven by rheumatoid factor. In daily practice, clinicians can reliably select either agent without fearing accelerated secondary attrition due to elevated serological markers. Moreover, this biological stability provides clinicians with predictable treatment courses for challenging seropositive patients. Thus, structural design and therapeutic mechanism together ensure long-term stability.
These findings carry profound implications for rheumatology care across India, where cost considerations and biologic access heavily influence treatment decisions. When patients experience secondary failure in private or state-funded healthcare, switching biologics entails immense financial and psychological stress. Therefore, baseline serological stratification represents an accessible, cost-effective tool for personalizing biologic selection. Indian clinicians managing patients with markedly elevated rheumatoid factor titres should approach tocilizumab therapy with careful vigilance. If physicians prescribe tocilizumab in high-titre patients, they should schedule regular clinical monitoring beyond the first year to detect emerging secondary inefficacy early. Alternatively, initiating therapy with certolizumab pegol or rituximab may offer superior long-term persistence and lower switching probabilities. Furthermore, rituximab often represents a highly cost-effective biosimilar option within Indian rheumatology practices. Incorporating baseline autoantibody quantification into pre-treatment algorithms helps clinicians mitigate avoidable drug failure. In addition, this strategy prevents unnecessary out-of-pocket expenditure for families facing lifelong chronic therapy. Ultimately, tailoring biologic choice to serological status optimizes clinical outcomes, prevents financial toxicity, and enhances sustained disease remission for seropositive patients.
Tocilizumab is a complete monoclonal antibody containing a standard human IgG1 Fc region. Rheumatoid factor consists of autoantibodies that bind directly to IgG Fc domains, forming circulating immune complexes. Consequently, this binding accelerates hepatic and reticuloendothelial drug clearance, lowering circulating drug concentrations over time. As trough levels decline, patients become vulnerable to secondary inefficacy and loss of response, leading to premature therapy discontinuation.
Certolizumab pegol features an engineered structure comprising a recombinant Fab fragment attached to a forty kilodalton polyethylene glycol molecule. Because it completely lacks an Fc crystallizable domain, rheumatoid factor cannot bind to the drug. Consequently, circulating autoantibodies cannot form immune complexes or accelerate hepatic elimination. This molecular design preserves stable pharmacokinetics and therapeutic persistence even in patients exhibiting extremely high baseline rheumatoid factor concentrations.
Clinicians do not need to avoid tocilizumab entirely, because the medication provides robust initial disease control across seropositive populations. However, physicians should exercise heightened vigilance when treating patients with rheumatoid factor titres exceeding two hundred units per millilitre. In these individuals, close monitoring for secondary loss of efficacy after the first year is essential. Alternatively, selecting Fc-free agents or rituximab may offer more predictable long-term retention.
Disclaimer: This content is for informational and educational purposes only, specifically targeted towards certified medical professionals, and does not constitute formal medical advice. Clinical decisions must always be tailored to individual patient profiles, confirmed against real-time diagnostic outcomes, and aligned with standard clinical guidelines. Healthcare practitioners should independently verify all medication details and treatment approaches before implementation. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multicentre study reveals that high baseline rheumatoid factor (>203 IU/mL) independently predicts secondary failure and shorter retention for tocilizumab, but not for certolizumab pegol or rituximab, informing personalized biologic selection in rheumatoid arthritis.
Today
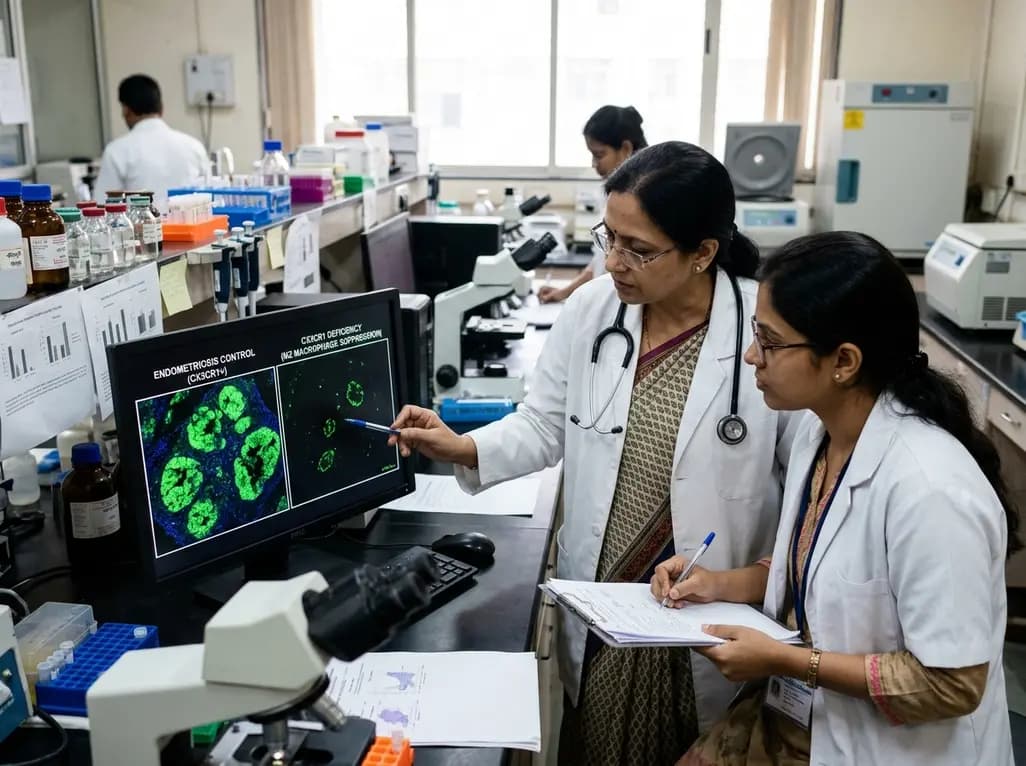
Groundbreaking experimental research demonstrates that CX3CR1 deficiency significantly attenuates endometriotic lesion growth by suppressing pro-repair M2 macrophage polarization. This discovery identifies the CX3CL1-CX3CR1 chemokine axis as a promising non-hormonal target for managing chronic endometriosis.
Today

Mayo Clinic trials and real-world datasets show GLP-1 receptor agonists improve left ventricular remodeling, reduce intracardiac filling pressures, decrease hospitalizations by 34%, and lower geriatric fall risks in patients with obesity and heart failure, delivering notable clinical and economic benefits.
Today

A meta-analysis of 19 studies reveals that 69% of ophthalmologists suffer from work-related musculoskeletal disorders. Slit lamps, microscopes, and high surgical loads cause severe cervical and lumbar strain, underscoring the urgent need for ergonomic workstations, micro-breaks, and institutional reforms.
Today

An analysis of 1,000 posts by macro- and mega-influencers on Instagram and TikTok revealed that 78.5% contained nutrition misinformation, while only 24% of creators held valid credentials. This article examines the clinical risks of viral dietary fads and provides actionable guidance for healthcare professionals.
Today
