

Loading, please wait...
Loading, please wait...
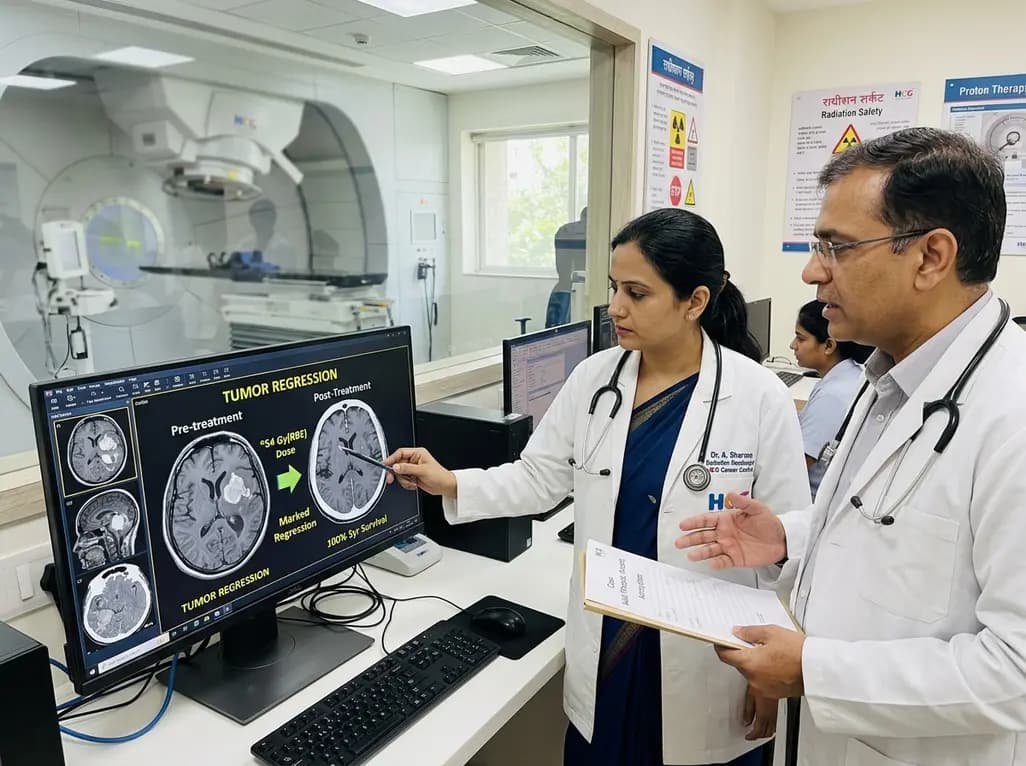
Adult pilocytic astrocytoma represents a rare central nervous system neoplasm that presents notable management challenges for neuro-oncology teams. Although the World Health Organization designates this glioma as a benign grade 1 tumor, adult patients frequently experience a less predictable clinical course than pediatric populations. Therefore, clinicians must balance aggressive local disease control against long-term neurocognitive and functional morbidity. Complete surgical resection remains the standard initial approach whenever feasible. However, these tumors frequently arise within anatomically precarious locations, including the brainstem, posterior fossa, and optical pathway. In such eloquent sites, complete neurosurgical debulking carries substantial risk of permanent neurological deficit. Furthermore, incomplete resections often lead to recurrent tumor growth. Consequently, radiation oncologists must select effective secondary treatments. Standard photon radiotherapy delivers unavoidable radiation to collateral brain tissues, increasing the danger of late adverse effects. In contrast, modern proton radiotherapy utilizes the unique Bragg peak to target the lesion while sparing normal tissue.
Surgical resection remains the primary therapy for accessible superficial astrocytomas. Nevertheless, adult lesions frequently involve complex structures such as the ventricular system, hypothalamus, and optic apparatus. Within these critical neural centers, extensive operative manipulation can induce visual loss, motor weakness, or severe endocrine dysfunction. Because surgeons often restrict procedures to cautious biopsies or partial debulking to safeguard functional independence, substantial residual tissue remains. Consequently, progressive or symptomatic disease frequently emerges over time. Systemic chemotherapy yields limited benefits in mature adult populations, making salvage irradiation essential for tumor stabilization. Unfortunately, conventional photon beam techniques deposit significant radiation across non-target neural architecture. Over prolonged survival timelines, this scattered dose increases the risk of cerebrovascular injury, secondary malignancies, and cognitive impairment. Because patients with low-grade gliomas anticipate extended survival, oncologists require highly conformal alternatives. Thus, particle radiotherapy provides a critical therapeutic option for anatomically unfavorable presentations.
Recent clinical findings published by Allmendinger and colleagues demonstrate the efficacy of proton beam therapy in this clinical setting. The researchers retrospectively evaluated fourteen adult patients presenting with progressive or surgically unfavorable low-grade astrocytomas. Ten patients received proton therapy as salvage treatment after surgical progression, whereas four individuals underwent upfront definitive proton irradiation. The clinical team administered a median dose of 54.0 Gy(RBE) utilizing advanced pencil-beam scanning. Across the follow-up period, patients demonstrated exceptional clinical outcomes. Specifically, the estimated overall survival was 100% at both three and five years. Additionally, the progression-free survival rate reached 83.3% across both time points. Furthermore, proton delivery achieved impressive radiographic responses on magnetic resonance imaging. Twelve of the fourteen patients exhibited measurable tumor regression. Specifically, three patients attained complete radiographic response, seven achieved partial response, and two demonstrated minor response. Consequently, the authors confirmed durable disease stabilization alongside substantial tumor shrinkage.
Evaluating treatment-related safety represents an essential consideration when delivering cranial radiotherapy. Because adult pilocytic astrocytoma typically progresses slowly, radiation-induced complications can compromise decades of life. In this evaluated cohort, proton radiotherapy demonstrated a remarkably benign toxicity profile. The observed adverse events were primarily low-grade and manageable according to standard toxicity criteria. Crucially, no grade 4 or grade 5 adverse events occurred during patient follow-up. Radiation-induced contrast enhancement developed in three patients, resulting in a three- and five-year enhancement-free probability of 76.2%. Clinicians successfully managed these transient inflammatory events with conservative monitoring or short corticosteroid courses. Furthermore, proton sparing of critical adjacent tissues prevented clinically significant neuroendocrine deficits and hearing loss. By substantially reducing radiation exposure to the temporal lobes and hippocampus, the treatment preserved neurocognitive function. Therefore, the data confirm that conformal proton radiotherapy provides an acceptable safety profile for adults with difficult intracranial tumors.
The favorable therapeutic ratio observed with proton therapy derives directly from the physical properties of charged heavy particles. In contrast to conventional photon beams that deposit entry and exit radiation throughout normal brain tissue, protons stop abruptly at a specified depth known as the Bragg peak. Beyond this designated endpoint, the deposited radiation dose drops rapidly to zero. Consequently, radiation oncologists can sculpt sharp dose fall-offs adjacent to radiosensitive brainstem nuclei and visual pathways. Moreover, intensity-modulated proton therapy allows millimeter-level accuracy across complex anatomical contours. By eliminating unnecessary exit doses, this technique protects healthy cerebral vasculature and functional white matter tracts. Furthermore, avoiding low-dose radiation baths significantly reduces the lifetime probability of secondary radiation-induced malignancies. Because these low-grade glioma patients often live for decades, minimizing integral whole-brain dose protects quality of life. Thus, proton physics offers substantial dosimetric advantages over traditional radiotherapy platforms.
Optimizing clinical outcomes for adult patients requires seamless coordination across neurosurgery, neuroradiology, and radiation oncology disciplines. Multidisciplinary teams must evaluate histological features and molecular alterations before selecting definitive interventions. For example, assessing BRAF fusion status and related signaling pathways provides diagnostic clarity and guides future targeted therapy decisions. When complete resection carries unacceptable neurological morbidity, early referral for proton radiotherapy prevents preventable surgical deficits. Additionally, neuroradiologists must employ advanced perfusion imaging to differentiate transient radiation-induced inflammatory enhancement from true tumor progression. Although proton therapy facilities require significant specialized infrastructure, expanding regional access will improve therapeutic availability for appropriate candidates. Ultimately, combining precise surgical biopsy, molecular diagnostics, and conformal proton irradiation provides an effective modern treatment standard. By achieving durable local control while safeguarding neurocognitive longevity, proton therapy represents a crucial advancement for adults facing surgically unfavorable pilocytic astrocytoma.
Proton radiotherapy delivers curative radiation doses to surgically inaccessible tumors while completely sparing downstream healthy brain parenchyma through the Bragg peak effect. This physical precision achieves durable local tumor control and high survival rates while substantially minimizing late neurocognitive, endocrine, and vascular toxicities in younger adult patients.
Radiation-induced contrast enhancement represents an inflammatory tissue reaction that mimics tumor recurrence on post-treatment neuroimaging. Clinicians routinely monitor these localized radiographic changes using advanced magnetic resonance sequences. Most cases resolve spontaneously or respond rapidly to conservative anti-inflammatory therapies such as corticosteroids without requiring surgical intervention or compromising overall neurological functioning.
Multidisciplinary teams consider proton radiotherapy when disease progression occurs in anatomically precarious locations such as the brainstem, optic apparatus, or deep ventricles. When repeat surgical debulking poses unacceptable risks of permanent neurological deficits, proton beam therapy provides an effective salvage option that achieves long-term disease stabilization and radiographic regression.
Disclaimer: This content is for informational and educational purposes only and should not be used as medical advice. Healthcare professionals must exercise clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent clinical study evaluated proton radiotherapy for adult pilocytic astrocytoma with surgically unfavorable disease. Delivering a median dose of 54 Gy(RBE), treatment achieved 100% 5-year overall survival, 83.3% progression-free survival, and marked tumor regression with minimal high-grade toxicity.
last month

Psoriasis is a chronic systemic inflammatory condition requiring comprehensive clinical intervention beyond topical care. Explore evidence-based insights into systemic comorbidities, patient quality of life, and targeted biologic options such as IL-23 inhibitors for sustained disease control.
Today

A nationwide cohort study published in JAMA Pediatrics reveals that maternal exposure to wildfire fine particulate matter, especially in late pregnancy, is linked to an elevated risk of childhood autism. Clinicians should evaluate ambient air quality risks and provide proactive protective counseling to mothers.
Today

Annual health checks only offer static snapshots. Real-world evidence from 2.1 million insured Indians reveals that tracking dynamic biomarker trends over time enables clinicians to spot evolving cardiometabolic risks early, reverse borderline pathology, and deliver tailored preventive interventions.
Today
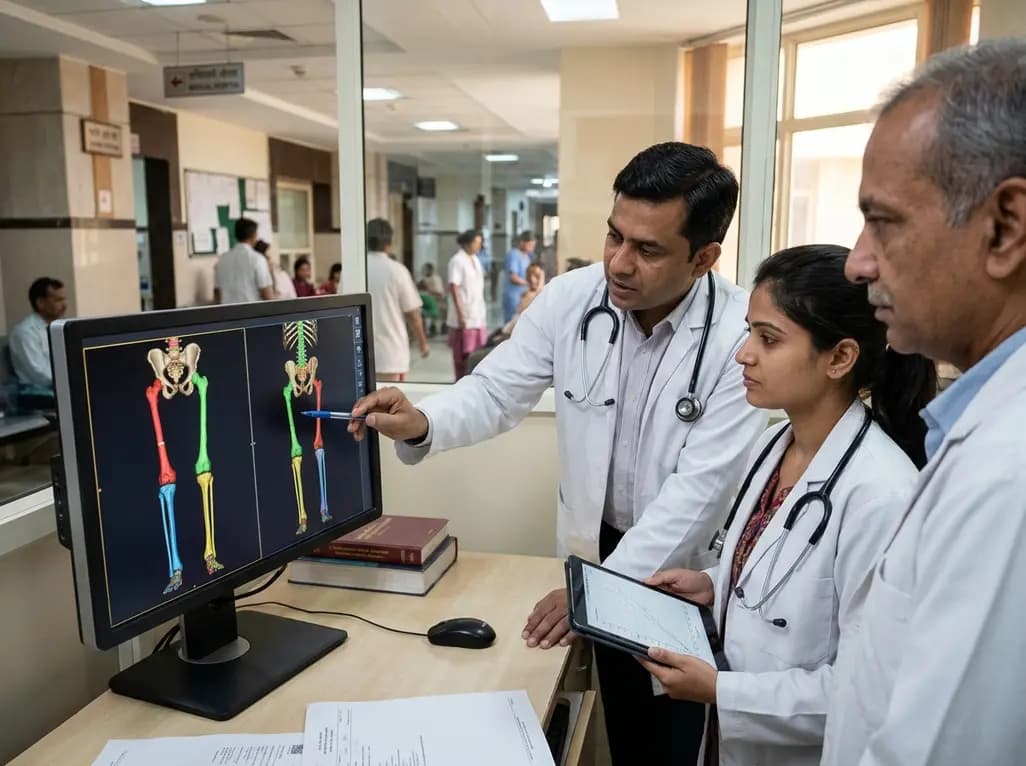
Modern 3D anthropometry reveals that pediatric leg growth ceases years before spinal elongation, exposing the clinical illusion of the classical Anderson-Green model. Learn how segmental growth dissociation improves surgical timing for epiphysiodesis in adolescent leg length discrepancy.
2 days back

With packaged goods giant HUL backing FSSAI's proposed front-of-pack red warning labels for foods high in fat, sugar, and salt, India takes a major step toward curbing non-communicable diseases. Learn how clearer nutrition disclosures empower clinicians, inform consumer choices, and drive dietary reform.
Today
