

Loading, please wait...
Loading, please wait...
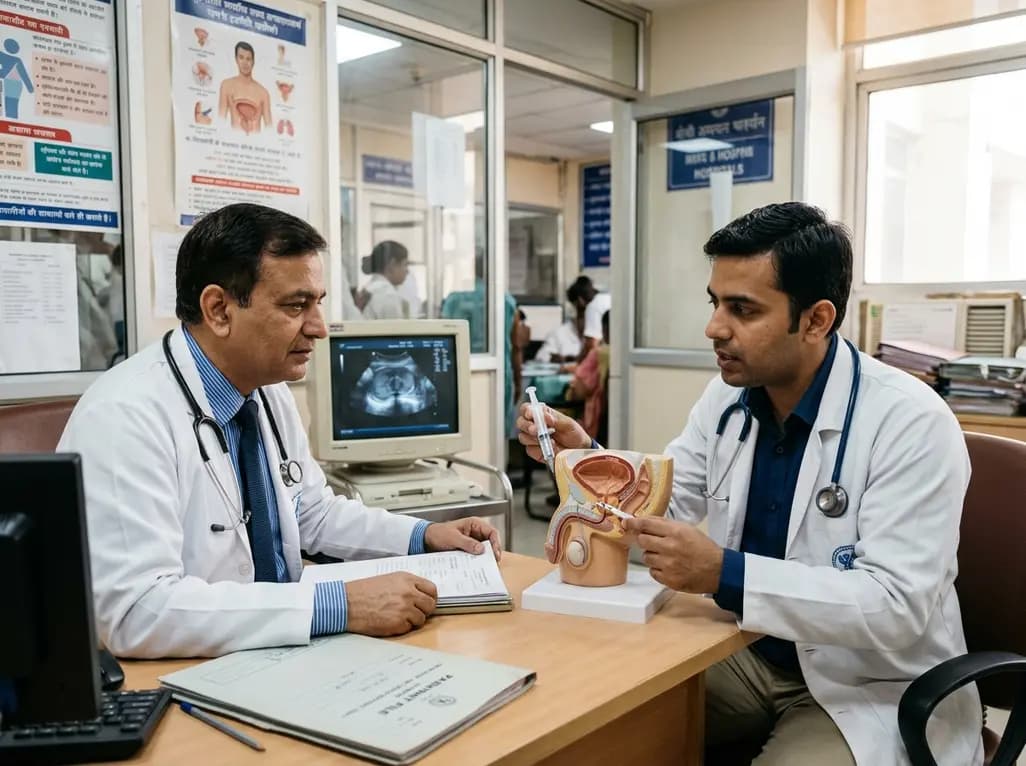
Benign prostatic hyperplasia represents one of the most widespread urological conditions among aging men worldwide. Consequently, many patients experience significant lower urinary tract symptoms that disrupt daily productivity and sleep. Recent clinical advancements have established the prostatic urethral lift as a premier minimally invasive treatment that effectively relieves obstruction while preserving quality of life.
Benign prostatic hyperplasia progressively compresses the prostatic urethra as glandular tissue expands. Therefore, affected men commonly suffer from nocturia, weak urinary stream, urinary urgency, and sensation of incomplete bladder emptying. In India, many individuals mistakenly normalize these symptoms as unavoidable consequences of aging. Thus, they delay seeking urological consultation until significant urinary retention occurs.
Historically, physicians managed symptomatic obstruction using alpha-blockers and 5-alpha reductase inhibitors. However, medical management often requires lifetime compliance and frequently triggers adverse drug effects. For instance, medications can cause chronic fatigue, dizziness, and sexual dysfunction. When medical therapy fails, traditional surgical resections become necessary. Although traditional resection delivers reliable tissue reduction, it carries notable perioperative risks. Consequently, modern urologists increasingly utilize minimally invasive surgical therapies to bridge this crucial clinical gap.
The prostatic urethral lift employs the UroLift system to physically retract obstructing lateral lobes. During this transurethral procedure, the urologist places small permanent implants through a specialized delivery device. Specifically, each implant consists of a nitinol capsular tab, a polyethylene suture, and a stainless steel urethral end-piece. Together, these components hold the encroaching prostatic tissue apart.
Importantly, the intervention achieves immediate luminal opening without cutting, heating, or resecting prostatic parenchyma. Because the surgeon avoids tissue ablation, postoperative thermal injury and significant bleeding remain extremely rare. Moreover, urologists typically perform the procedure under local anesthesia or light sedation in an outpatient setting. As a result, patients experience minimal perioperative discomfort. Most individuals avoid routine postoperative catheterization and resume normal activities within a few days.
Preserving sexual health remains a paramount consideration during benign prostatic hyperplasia interventions. Conventional transurethral resection frequently causes retrograde ejaculation and erectile dysfunction due to thermal or mechanical injury. In contrast, extensive multi-center clinical trials demonstrate that the prostatic urethral lift preserves erectile and ejaculatory functions completely.
Furthermore, clinical studies show rapid and sustained improvements in validated symptom metrics. Patients consistently demonstrate significant reductions in International Prostate Symptom Score along with marked enhancements in peak urinary flow rates. In addition, quality-of-life scores improve markedly within two weeks post-procedure. Because the technique leaves the bladder neck and neurovascular bundles intact, men experience no new-onset permanent sexual side effects. Therefore, this therapeutic modality offers high patient satisfaction rates across diverse clinical demographics.
Accurate clinical evaluation remains essential for achieving optimal procedural outcomes with prostatic urethral lift implants. Primarily, suitable candidates include men aged 50 and older who present with moderate-to-severe lower urinary tract symptoms. Additionally, standard clinical guidelines recommend assessing total prostate volume prior to intervention.
Specifically, the procedure demonstrates optimal efficacy in prostates between 30 and 80 milliliters in total volume. Preoperative cystoscopy plays a critical diagnostic role in evaluating anatomical suitability. Urologists must confirm the absence of an obstructing median intravesical lobe before recommending standard lateral lobe retraction. Furthermore, clinicians should perform transrectal ultrasonography, uroflowmetry, and post-void residual urine assessments. By carefully excluding advanced neurogenic bladder dysfunction, clinicians ensure superior long-term clinical outcomes for suitable candidates.
Transurethral resection of the prostate long served as the historical gold standard for relieving bladder outlet obstruction. However, standard electrosurgical resection carries documented risks of bleeding, stricture formation, and fluid absorption complications. Additionally, conventional surgery requires general anesthesia and prolonged hospital stays with indwelling urinary catheters.
In contrast, the prostatic urethral lift offers an exceptionally favorable safety profile with rapid convalescence. Although electroresection may achieve slightly higher maximal flow rates in severely enlarged glands, it involves higher morbidity. Patients undergoing minimally invasive implant therapy experience significantly shorter recovery durations. Furthermore, they avoid lengthy hospitalizations and report fewer immediate postoperative complications. Thus, when sexual preservation and fast functional recovery are primary patient priorities, minimally invasive implants present an advantageous therapeutic alternative.
The clinical adoption of advanced minimally invasive urological techniques is accelerating rapidly across leading healthcare institutions in India. Major medical centers have now completed thousands of successful lift procedures nationwide. This milestone illustrates increasing patient demand for cutting-edge alternatives to chronic medication and invasive resection.
To maintain rigorous safety standards, expert urologists lead structured Continuing Medical Education workshops and wet-lab training modules. These dedicated educational programs instruct practicing surgeons on precise implant deployment, cystoscopic assessment, and rigorous candidate selection. Consequently, institutional training centers promote standardized evidence-based practice across regional centers. As awareness expands among primary care physicians and patients, minimally invasive procedures will continue transforming the standard of care for benign prostatic hyperplasia management in India.
Q1: What are the primary advantages of a prostatic urethral lift over conventional surgery?
The prostatic urethral lift delivers rapid symptom relief without cutting, heating, or removing prostate tissue. Consequently, it carries minimal risk of bleeding and completely preserves erectile and ejaculatory function. Additionally, the procedure is performed on an outpatient basis under light sedation, enabling patients to recover quickly and usually avoid postoperative urinary catheterization.
Q2: Who is an ideal candidate for this minimally invasive BPH procedure?
Ideal candidates are men suffering from moderate-to-severe urinary symptoms secondary to benign prostatic hyperplasia with a prostate volume typically between 30 and 80 milliliters. Furthermore, diagnostic cystoscopy must confirm that lateral lobe enlargement is causing the obstruction rather than an obstructive middle lobe.
Q3: How durable are the clinical symptom improvements following implant placement?
Long-term clinical studies demonstrate that the prostatic urethral lift provides durable symptom reduction and improved urinary flow for five years and beyond. Moreover, because the implants mechanically hold open the urethra without destroying tissue, patients retain future options for other surgical or medical treatments if needed.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Benign prostatic hyperplasia impacts millions of aging men worldwide. Minimally invasive surgical therapies like the prostatic urethral lift offer rapid symptom relief while preserving sexual function and eliminating the need for tissue resection or long-term medication.
last month

A new systematic review protocol evaluates how virtual reality immersion levels and game formats—serious versus commercial—influence upper limb functional recovery after stroke, examining motor outcomes and adherence across acute and chronic stages.
Today

A cross-sectional study of over 33 million US live births from 2016 through 2024 reveals a 74% increase in hypertensive disorders of pregnancy. This clinical overview explores demographic drivers, maternal-fetal outcomes, and essential preventive strategies for obstetric practice.
Today

The phase II DAPA-AIC trial demonstrates that dapagliflozin 10 mg daily significantly preserves left ventricular ejection fraction compared to placebo over four months in adults undergoing anthracycline chemotherapy, highlighting a potential preventive strategy in cardio-oncology.
Today

A scoping review reveals severe gaps in long-term assistive technology provision following humanitarian emergencies. Addressing post-disaster rehabilitation requires systematic follow-up, workforce training, and integration into national health systems to sustain mobility and recovery.
Today
A randomized controlled trial investigated whether virtual reality thyroid biopsy reduces procedural pain, anxiety, and fear. While adjusted analyses showed modest pain reduction, unadjusted differences remained statistically insignificant, highlighting the need for larger confirmatory trials.
Today
