

Loading, please wait...
Loading, please wait...
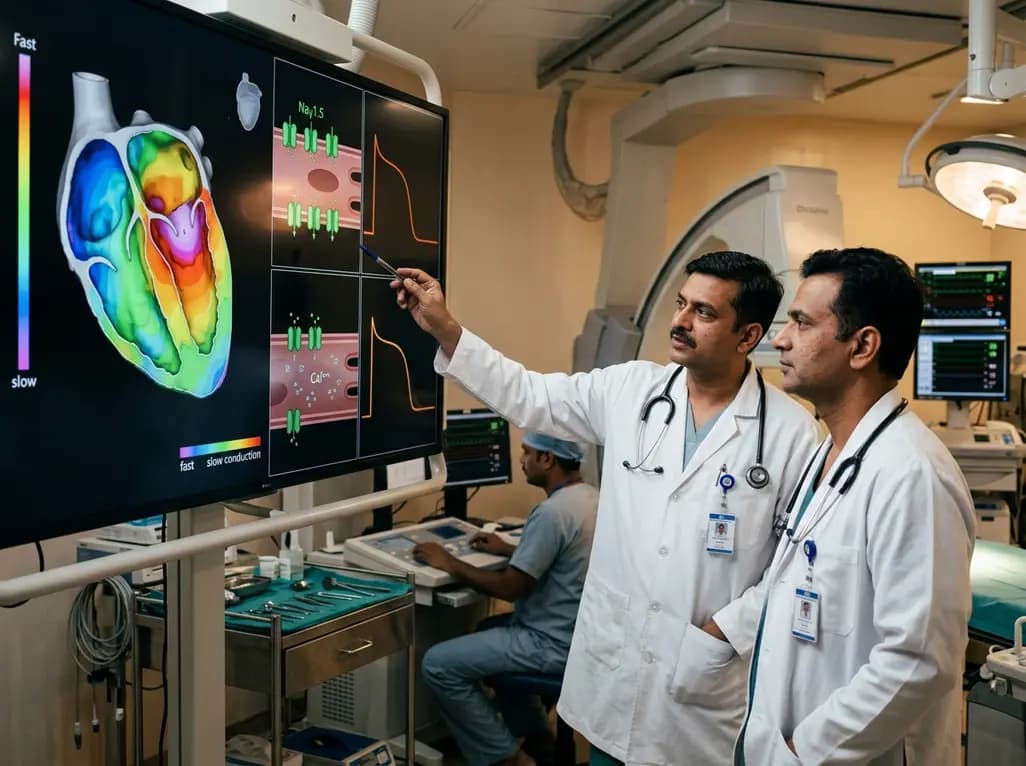
Clinicians increasingly recognize non-ablative radiotherapy as a transformative salvage option for patients experiencing refractory ventricular tachycardias. Traditionally, electrophysiologists rely on invasive catheter ablation to create permanent anatomical scars that disrupt reentrant pathways. However, many vulnerable patients face significant procedural risks or deep intramural substrates that standard radiofrequency catheters cannot reach. Stereotactic arrhythmia radioablation delivers focused ionizing radiation non-invasively, yet its fundamental therapeutic mechanisms extend well beyond simple tissue necrosis. Recent cellular investigations demonstrate that targeted irradiation suppresses ventricular tachycardia primarily by enhancing electrical conduction rather than destroying myocardial tissue. Specifically, therapeutic irradiation upregulates crucial cardiac ion channel proteins, including the cardiac voltage-gated sodium channel NaV1.5 and the gap junction protein connexin 43. Consequently, irradiated ventricular tissue exhibits improved impulse propagation, which effectively extinguishes slow-conduction corridors necessary for circuit reentry. In addition, experimental data show that radiation alters cellular electrophysiology within two weeks post-exposure, providing rapid antiarrhythmic benefits before classic fibrotic scarring develops. Therefore, understanding these unique functional modifications helps electrophysiologists and radiation oncologists optimize radiation planning and tailor target dosimetry. As clinical adoption grows, unraveling these intricate cellular responses remains paramount for maximizing procedural success and preventing unintended arrhythmogenic complications.
To elucidate these functional adaptations, investigators evaluated isolated cardiomyocytes from murine models exposed to either low-dose or high-dose cardiac irradiation. Crucially, exposure to twenty-five Gray of radiation significantly increased peak transient sodium current and markedly augmented sustained sodium current density. Because the sustained sodium component increased to a greater extent than the peak current, the overall sustained-to-transient current ratio rose sharply. This ionic remodeling directly modified myocardial cellular action potentials. For example, irradiated cardiomyocytes exhibited larger action potential amplitudes, accelerated maximal upstroke velocities, and prolonged action potential durations. Therefore, the enhanced upstroke velocity accelerates cellular wavefront propagation, thereby mitigating critical reentrant circuits within diseased tissue borders. Furthermore, prolonged action potential duration provides an additional antiarrhythmic mechanism by rendering cardiac tissue temporarily refractory to premature wavefronts. However, this pronounced prolongation simultaneously introduces significant electrical vulnerability. Specifically, enhanced sustained sodium currents delay phase-three repolarization, which substantially facilitates the generation of early after-depolarizations. Thus, while non-ablative irradiation successfully suppresses established reentrant circuits, it concurrently establishes a delicate electrophysiological substrate that demands vigilant monitoring.
In addition to altered sodium currents, non-ablative radiation triggers substantial disturbances in cardiomyocyte intracellular calcium regulation. Quantitative analyses show that high-dose radiation notably depresses intracellular calcium dynamics within irradiated ventricular myocytes. Specifically, treated cells display impaired sarcoplasmic reticulum calcium release and slower cytosolic calcium removal during diastole. Consequently, peak calcium transient amplitudes decrease significantly, thereby threatening regional myocardial mechanical performance and excitation-contraction coupling. Furthermore, depressed calcium handling can exacerbate electrical heterogeneity across the border zone between irradiated and non-irradiated tissue. When paired with prolonged action potential durations, altered cytosolic calcium cycling further heightens susceptibility to triggered activity and oscillatory afterpotentials. Notably, comparative evaluations revealed that lower radiation doses of fifteen Gray produce similar yet considerably milder electrophysiological and calcium alterations. This evident dose-dependency confirms that radiation effects on excitation-contraction mechanics scale directly with delivered ionizing energy. Therefore, radiation oncologists must meticulously define target volumes to spare adjacent healthy myocardium. Ultimately, identifying strategies to preserve calcium handling while maintaining conduction velocity benefits remains an essential challenge for translational electrophysiology teams.
To determine the upstream molecular triggers driving these ionic changes, researchers evaluated key intracellular biochemical signaling pathways. Interestingly, twenty-five Gray irradiation elicited a substantial surge in intracellular reactive oxygen species content within ventricular cardiomyocytes. Elevated oxidative stress directly promotes oxidative modification of sodium channels. Consequently, this oxidative damage provides a clear molecular rationale for enhanced sustained sodium currents. Moreover, reactive oxygen species alter channel gating kinetics. This alteration causes persistent late inward sodium currents during the plateau phase. Intriguingly, despite elevated oxidative stress, irradiated cardiomyocytes demonstrated a paradoxical reduction in calcium/calmodulin-dependent protein kinase II phosphorylation. Because active kinase signaling typically amplifies arrhythmogenic remodeling, this unexpected kinase suppression suggests a complex, unconventional regulatory network operating under acute radiation exposure. Thus, oxidative stress appears to function as the primary driver of persistent sodium influx independently of kinase activation. In addition, these biochemical findings highlight potential pharmacological avenues to modulate radiation outcomes. For instance, targeted antioxidants or late sodium current blockers could preserve conduction gains. Concurrently, these agents could mitigate proarrhythmic late current enhancements.
These benchmark experimental discoveries carry profound clinical implications for tertiary cardiology and electrophysiology programs worldwide. Stereotactic radioablation is transitioning rapidly from an experimental salvage modality to an established bail-out option for therapy-refractory ventricular arrhythmias. Clinical efficacy often manifests days after treatment. Thus, enhanced electrical conduction cleanly explains this rapid antiarrhythmic response before fibrosis develops. However, the concurrent induction of early after-depolarizations, delayed repolarization, and depressed calcium dynamics underscores legitimate safety concerns. Clinicians must recognize that irradiated myocardial regions might harbor latent electrical instability or localized contractile dysfunction. Therefore, patient selection requires rigorous multidisciplinary evaluation involving electrophysiologists, radiation oncologists, and advanced imaging specialists. Furthermore, continuous implantable cardioverter-defibrillator monitoring remains imperative during post-treatment surveillance to detect secondary arrhythmic episodes promptly. Post-procedural pharmacotherapy also requires judicious optimization. For example, clinicians might consider antiarrhythmic agents that inhibit late sodium channels without blunting conduction improvements. Ultimately, future prospective trials must evaluate intermediate radiation dosing. Such strategies could maximize conduction gains while minimizing oxidative stress and repolarization abnormalities.
Non-ablative radiotherapy terminates ventricular tachycardia circuits primarily through functional electrical remodeling rather than classic tissue necrosis. Therapeutic radiation upregulates cardiac NaV1.5 sodium channels and connexin 43 gap junction proteins, which significantly accelerates wavefront conduction velocity. In addition, prolongation of the action potential duration renders the diseased substrate temporarily refractory to reentrant wavefronts. Consequently, these combined electrical modifications extinguish slow-conduction pathways, thereby successfully terminating reentrant arrhythmias without causing immediate transmural structural damage.
Radiation noticeably increases the sustained sodium current density relative to transient peak current in irradiated cardiomyocytes. This augmented persistent sodium influx delays phase-three repolarization, which lengthens overall action potential duration. Furthermore, excessive cellular oxidative stress alters sodium channel gating kinetics, prolonging depolarizing inward currents during the plateau phase. Consequently, this persistent depolarization facilitates early after-depolarizations and regional electrical heterogeneity, creating a vulnerable electrophysiological substrate that can occasionally trigger secondary ventricular arrhythmias.
Cardiomyocyte functional remodeling exhibits clear radiation dose-dependency. Experimental investigations show that a high dose of twenty-five Gray generates substantial increases in sodium current, marked action potential prolongation, and significant intracellular calcium depression. Conversely, delivering a lower dose of fifteen Gray produces comparable electrophysiological adaptations but with notably smaller alterations in calcium dynamics and repolarization. Therefore, clinical researchers are exploring optimized intermediate doses that successfully improve electrical conduction while minimizing mechanical dysfunction.
Disclaimer: This content is for informational and educational purposes only, and does not substitute professional medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today

Diagnostic data shows that nearly one in four spine investigations now involve patients younger than 40 years. This comprehensive overview explores the drivers behind this demographic trend, evaluates ergonomic hazards, clarifies red-flag signs, and highlights clinical indications for judicious diagnostic imaging.
Today

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
