

Loading, please wait...
Loading, please wait...

Modern medicine is experiencing unprecedented acceleration in neural interfaces and therapeutic neuromodulation systems. Consequently, neurotechnology governance is entering an essential operational turn across healthcare institutions. This critical transition moves past broad ethical declarations toward actionable clinical protocols and regulatory frameworks. Clinicians, neurosurgeons, and hospital administrators must now translate theoretical principles into real-world medical practice to ensure patient safety.
For decades, bioethics committees generated aspirational statements regarding cognitive liberty and human dignity. However, abstract declarations cannot solve the operational dilemmas that clinicians confront in busy operating theatres. Surgical teams regularly implant deep brain stimulation leads and calibrate neural interfaces for motor recovery. Therefore, healthcare providers require explicit procedures rather than philosophical commentary to guide daily interventions.
Operational models must establish tangible criteria for device performance, informed consent, and device lifespan. Furthermore, clinical teams need unambiguous protocols when algorithmic decoders drift or stimulation parameters require recalibration. Without concrete operational standards, practitioners face profound uncertainty regarding legal liability and patient safety. Hospital oversight committees must therefore integrate engineering audits directly into clinical governance pathways. Consequently, leading medical organizations are establishing specialized multidisciplinary teams to review neural technologies before surgical deployment. These clinicians evaluate data streams from sensors to external monitoring platforms. Ultimately, this operational turn ensures that fundamental human rights actively shape practical therapeutic decisions.
Translating ethics into clinical workflows demands extensive capacity-building across healthcare systems. Hospital leadership must invest in secure hardware architecture to manage complex neurophysiological data streams. In addition, hospitals must train integrated teams comprising neurologists, functional neurosurgeons, software engineers, and clinical ethicists. Such collaborative networks ensure that institutions evaluate emerging technologies from both technical and humanitarian viewpoints.
Furthermore, medical centers must develop standardized guidelines for algorithmic oversight and software revisions. When machine learning algorithms interpret motor commands, minor software patches can alter stimulation thresholds unpredictably. Therefore, biomedical engineers must validate firmware updates in controlled settings before clinical implementation. Meanwhile, clinical trial coordinators should establish longitudinal monitoring registries to track adverse events and technical anomalies. Institutions also require unambiguous escalation protocols when automated neurofeedback decisions conflict with patient preferences. Consequently, structured institutional investment transforms abstract ethics into reliable operational safeguards. These proactive measures protect patients throughout long-term device therapy.
Modern regulatory oversight requires genuine regulatory fit that matches the mechanical and algorithmic reality of neural devices. Traditional medical device frameworks evaluate static implants, such as titanium plates or prosthetic joints. In contrast, advanced neural interfaces rely on dynamic machine learning models and bidirectional neurostimulation. Therefore, regulatory agencies must create adaptive clearance pathways that evaluate ongoing software evolution.
Regulators must carefully balance therapeutic innovation against patient safety. If oversight mechanisms become excessively rigid, paralyzed individuals lose access to transformative brain-computer interfaces. Conversely, insufficient oversight introduces hazardous risks, including unverified clinical claims and compromised neural safety. In response, international authorities are designing phased regulatory pathways for novel devices. These frameworks mandate rigorous pre-market validation and continuous real-world performance reporting. Furthermore, supervisory agencies must distinguish clearly between certified medical devices and unregulated consumer wellness gadgets. Consequently, rigorous regulatory fit ensures that clinical innovations scale responsibly while shielding patients from exploitation.
Neural recording platforms record complex electrophysiological signals that mirror cognitive states, emotional valence, and intention. Consequently, neural telemetry represents an exceptionally sensitive tier of personal health information. Commercial organizations increasingly seek access to central nervous system data for behavioral analysis and algorithmic training. Therefore, hospital governance structures must institute stringent data stewardship rules to prevent unauthorized exploitation.
Treating physicians must guarantee that patients retain full authority over their neural data. Furthermore, healthcare facilities must implement end-to-end encryption across all wireless neurostimulators and cloud repositories. Without robust cryptographic protections, hostile entities could intercept raw intracranial telemetry or modify stimulation parameters remotely. In addition, research consent agreements must define whether scientists can retain or share de-identified neural recordings. Traditional broad consent forms cannot address technologies that monitor cognitive activity continuously. Instead, clinical centers must adopt dynamic consent frameworks that permit patients to revise data permissions over time. Ultimately, preserving neural data privacy upholds fundamental patient autonomy and moral status.
In India, the intersection of clinical neurology, neurosurgery, and digital health regulation creates unique responsibilities. The Central Drugs Standard Control Organisation continuously updates national medical device rules to govern therapeutic hardware. Meanwhile, the Indian Council of Medical Research formulates ethical standards to safeguard human participants in clinical trials. However, the emergence of implantable neural chips and closed-loop neuromodulation demands specialized regulatory capacity.
Indian tertiary hospitals must establish dedicated neuroethics panels to evaluate investigational neural protocols. Furthermore, clinical researchers must align neurodata management with the Digital Personal Data Protection Act. Protecting domestic brain data prevents commercial actors from exploiting sensitive biometric information without consent. In addition, academic medical centers must partner with biomedical innovators to develop affordable neural technologies locally. Domestic manufacturing initiatives can reduce the price of neurorehabilitation devices and functional stimulation systems significantly. Consequently, Indian clinicians can deliver advanced therapies to underserved rural populations and urban centers alike. Ultimately, robust operational governance guarantees that cutting-edge neurotherapeutics integrate safely into Indian healthcare delivery.
The operational turn represents a deliberate move from theoretical ethical concepts to tangible clinical and administrative actions. Instead of simply debating cognitive freedom, healthcare institutions must now establish precise device calibration standards, cybersecurity measures, and patient consent protocols. Furthermore, this transition requires hospitals to train multidisciplinary teams and institute continuous post-market surveillance. Consequently, operational governance embeds ethical values directly into daily clinical workflows to protect vulnerable individuals.
Neural data captures direct electrophysiological patterns that reflect conscious thoughts, subconscious processing, and emotional states. Unlike standard biochemical markers, brain activity provides intimate insights into cognitive function and decision-making capabilities. Commercial entities frequently seek this telemetry for algorithmic training and behavioral targeting. Therefore, regulators must implement robust cryptographic safeguards and granular consent models. These protective measures prevent unauthorized corporate exploitation and safeguard individual cognitive liberty across clinical and consumer environments.
Indian medical institutions must expand specialized institutional review boards with trained neuroethicists and biomedical engineers. Furthermore, research teams must design transparent consent documents that clearly explain algorithmic updates and data telemetry risks. Hospitals must also comply strictly with the Digital Personal Data Protection Act and national ethical guidelines. In addition, centers should establish robust registries to track patient safety and device efficacy over extended therapeutic durations.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Neurotechnology governance is entering an operational turn, shifting from abstract ethics to concrete regulatory fit, institutional capacity, and clinical deployment frameworks.
Today
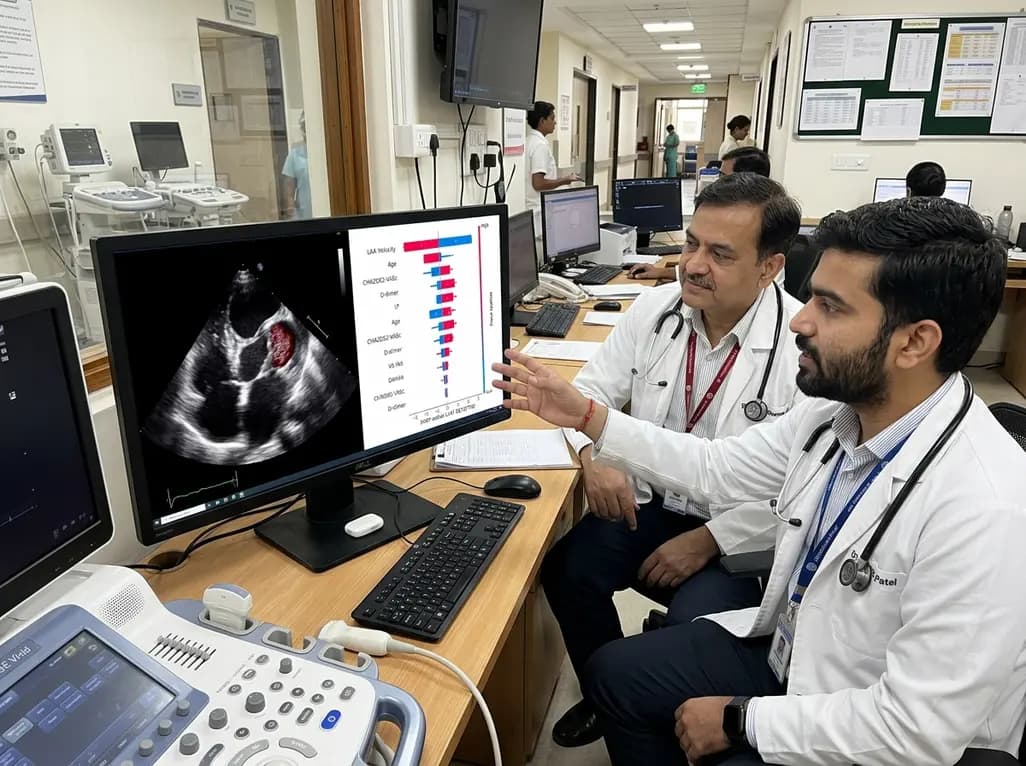
A study demonstrates an explainable machine learning framework integrating clinical and echocardiographic metrics to predict left atrial appendage thrombus in non-valvular atrial fibrillation, utilizing SHAP analysis for clinical interpretability.
Today

Maternal anaemia contributes to nearly half of pregnancy-related fatalities across India. To prevent complications, Uttar Pradesh has added single-dose parenteral iron to its essential medicines list. This clinical transition aims to restore haemoglobin rapidly and protect high-risk mothers across rural facilities.
Today

A landmark systematic review and meta-analysis establishes age-specific normative reference values for pediatric pulse wave velocity, revealing a nonlinear trajectory of arterial stiffness from early childhood through adolescence.
Today

A new systematic review evaluates lumbar facet arthroplasty, predominantly the Total Posterior Spine System (TOPS). Evidence shows significant reductions in back and leg pain and preserved segmental mobility, though revision rates and outcome heterogeneity highlight the need for careful patient selection.
Today

A landmark cross-sectional study in Asian adults with type 2 diabetes identifies novel urinary metabolites linked to mild cognitive impairment. Elevated urinary sucrose and altered metabolites highlight non-invasive pathways for early cognitive risk stratification and targeted metabolic management.
Today
