

Loading, please wait...
Loading, please wait...

The investigation of urinary metabolomics cognitive impairment pathways offers a revolutionary perspective on neurodegenerative complications in metabolic disorders. Type 2 diabetes significantly elevates the lifetime risk of developing mild cognitive impairment and vascular dementia. However, clinicians often face substantial hurdles when attempting to detect early cerebral vulnerability using routine laboratory workups. Blood-based biomarkers can be invasive, whereas comprehensive neuropsychological evaluations demand significant time and trained personnel. Consequently, researchers have shifted focus toward non-invasive biofluids to uncover subtle metabolic perturbations before irreversible neural damage manifests.
Chronic dysglycemia triggers systemic endothelial dysfunction, microvascular damage, and accelerated central nervous system aging. In Asian populations, the prevalence of type 2 diabetes continues to rise rapidly, creating an unprecedented public health challenge. Furthermore, cognitive impairment often develops silently over several decades in individuals with long-standing metabolic disturbances. Patients frequently experience insidious deficits in executive functioning, processing speed, and delayed recall long before overt dementia appears. Unfortunately, standard clinical markers like glycated hemoglobin fail to capture these intricate neuropathological transitions. Therefore, identifying objective physiological markers has become an urgent clinical priority. Metabolomics provides a comprehensive snapshot of downstream cellular processes, integrating genomic, environmental, and lifestyle influences. By analyzing small-molecule profiles in non-invasive specimens, clinicians can detect subtle metabolic shifts early. Urine serves as an exceptionally practical biofluid because it reflects whole-body clearance and renal processing without requiring venipuncture. As a result, urinary profiling represents an accessible window into both peripheral metabolic homeostasis and central neurovascular resilience.
To elucidate these critical metabolic associations, investigators conducted a well-characterized cross-sectional study comprising 1,053 Asian adults with type 2 diabetes. The cohort presented an average age of 65.1 years, representing an older demographic particularly susceptible to neurocognitive decline. Researchers quantified urinary small molecules using high-resolution proton nuclear magnetic resonance spectroscopy. Concurrently, trained examiners assessed participant neurocognition using the Repeatable Battery for the Assessment of Neuropsychological Status. This validated neuropsychological tool evaluates multiple functional domains, including immediate memory, visuospatial construction, language, attention, and delayed memory. In this investigation, clinicians defined mild cognitive impairment when an individual scored at least 1.5 standard deviations below normative domain means. In addition, the research protocol adjusted all metabolic measurements for potential confounders, such as age, sex, and renal function. The investigators applied the stringent Benjamini-Hochberg false discovery rate procedure to eliminate spurious statistical associations. Consequently, this rigorous methodological framework ensured that only robust metabolic signatures survived multiple testing corrections, providing reliable epidemiological insights.
Following comprehensive statistical adjustments, four distinct urinary metabolites demonstrated statistically significant associations with overall cognitive performance. Specifically, higher urinary concentrations of sucrose, 4-hydroxyhippurate, trans-aconitate, and tryptophan were associated with lower total cognitive index scores. Among these markers, elevated urinary sucrose emerged as an exceptionally potent signal of neurocognitive vulnerability. Participants displaying high urinary sucrose exhibited more than a twofold increased risk of mild cognitive impairment, with an adjusted odds ratio of 2.19. Furthermore, specific metabolites correlated with distinct neuropsychological domains. Sucrose, trans-aconitate, 4-hydroxyhippurate, and 4-deoxythreonate were linked to impaired delayed memory performance. Similarly, levels of hypoxanthine, sucrose, and tryptophan demonstrated meaningful correlations with visuospatial and constructional abilities. These domain-specific findings illustrate that cognitive decline in diabetes does not progress uniformly across all mental faculties. Instead, distinct biochemical imbalances may jeopardize specific cerebral networks, highlighting the nuanced utility of urinary metabolomic screening.
The biological mechanisms connecting these urinary markers to cerebral function involve intricate pathways of energy metabolism, gut dysbiosis, and neuroinflammation. For instance, elevated urinary sucrose indicates intestinal barrier hyperpermeability and compromised proximal tubular handling during severe metabolic dysregulation. When the gut-vascular barrier deteriorates, toxic microbial byproducts enter the systemic circulation and trigger neuroinflammation. Similarly, 4-hydroxyhippurate represents a key gut microbial metabolite derived from dietary polyphenols. Alterations in its excretion reflect intestinal microbiome shifts that disrupt the gut-brain axis. Furthermore, trans-aconitate acts as an inhibitor of the tricarboxylic acid cycle, indicating mitochondrial stress and impaired cellular energy production within neural tissues. In addition, tryptophan serves as an essential precursor for serotonin and neuroprotective kynurenine metabolites. Abnormal tryptophan clearance suggests dysregulated immune signaling and altered neurotransmitter synthesis. Meanwhile, hypoxanthine reflects ongoing purine turnover and oxidative stress, which accelerate microvascular injury in cerebral capillaries. Consequently, these urinary metabolites mirror multisystemic physiological breakdown affecting cerebral microvasculature and neuronal viability.
These findings carry profound clinical implications for practicing physicians, endocrinologists, and geriatricians managing type 2 diabetes. Currently, early cognitive screening remains underutilized in busy outpatient clinics due to time constraints and lack of specialized personnel. However, routine urinalysis is already an integral component of standard diabetes monitoring for nephropathy. Incorporating metabolomic panels into existing diagnostic workflows could enable opportunistic neurocognitive risk stratification. Physicians could identify vulnerable individuals years before substantial memory loss impairs functional independence. Moreover, recognizing elevated urinary sucrose or altered tryptophan dynamics could prompt clinicians to intensify glycemic control and target vascular risk factors. Clinicians might also evaluate gut microbiome health and recommend targeted nutritional modifications to restore epithelial barrier integrity. In addition, identifying high-risk patients facilitates timely referral for structured cognitive rehabilitation and multidomain lifestyle interventions. Thus, non-invasive profiling could bridge the persistent gap between routine metabolic care and proactive neurocognitive preservation.
Although these cross-sectional observations provide compelling evidence, several critical questions demand prospective validation. Future longitudinal cohort studies must determine whether urinary metabolic shifts precede measurable cognitive decline or merely reflect concurrent end-organ damage. Furthermore, researchers must validate these metabolic thresholds across diverse global cohorts, including South Asian and Western diabetic populations. Combining urinary metabolomics with advanced neuroimaging and plasma biomarkers could generate powerful multivariable risk prediction algorithms. In addition, interventional trials should investigate whether pharmacological therapies, such as sodium-glucose cotransporter-2 inhibitors or glucagon-like peptide-1 receptor agonists, modify these metabolomic profiles. Because these agents exert neuroprotective and metabolic effects, tracking urinary metabolites could provide dynamic feedback on therapeutic efficacy. Ultimately, non-invasive metabolomic phenotyping holds immense promise for personalized medicine. By translating complex biochemical signatures into actionable clinical insights, modern medicine can deliver proactive interventions that preserve brain health in aging individuals with diabetes.
Urinary sucrose excretion reflects altered intestinal permeability and subclinical renal tubular handling in diabetes. When mucosal barriers break down, intact disaccharides enter systemic circulation and clear through urine. This leaky gut phenomenon promotes systemic inflammation and compromises blood-brain barrier integrity. Consequently, elevated urinary sucrose serves as a non-invasive surrogate marker for chronic inflammatory stress and neurovascular injury, substantially elevating the clinical risk of mild cognitive impairment.
Traditional neuropsychological tests require specialized clinical staff, significant administrative time, and active patient cooperation. Furthermore, linguistic and cultural variations frequently confound neuropsychological score interpretation across diverse patient populations. In contrast, urinary metabolomics offers a rapid, non-invasive, and completely objective biochemical assessment. It detects subtle systemic metabolic perturbations long before clinical symptoms emerge, enabling clinicians to initiate proactive neuroprotective interventions during early, potentially reversible disease stages.
Optimizing glycemic control, blood pressure, and lipid parameters can reduce microvascular damage and cellular oxidative stress. However, urinary metabolomic alterations also capture complex pathways involving gut microbiome dysbiosis, mitochondrial dysfunction, and altered amino acid metabolism. Therefore, comprehensive lifestyle interventions, including Mediterranean-style diets, regular aerobic exercise, and gut microbiome optimization, may be necessary alongside conventional pharmacotherapy to restore metabolic homeostasis and protect long-term cognitive health in diabetic patients.
Disclaimer: This content is for informational and educational purposes only. It is not intended to provide specific medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark cross-sectional study in Asian adults with type 2 diabetes identifies novel urinary metabolites linked to mild cognitive impairment. Elevated urinary sucrose and altered metabolites highlight non-invasive pathways for early cognitive risk stratification and targeted metabolic management.
Today
A nationwide Korean cohort study of 265,610 individuals reveals that the link between benzodiazepine use and dementia attenuates after adjusting for comorbidity, with no accelerated progression to severe dementia.
Today

Integrating adult genetic services into reproductive and pregnancy care substantially alters clinical management. A study reveals that diagnostic genetic evaluations directly inform maternal, fetal, and neonatal care in nearly 57% of tested patients, highlighting the value of preconception and antenatal genomics.
Today
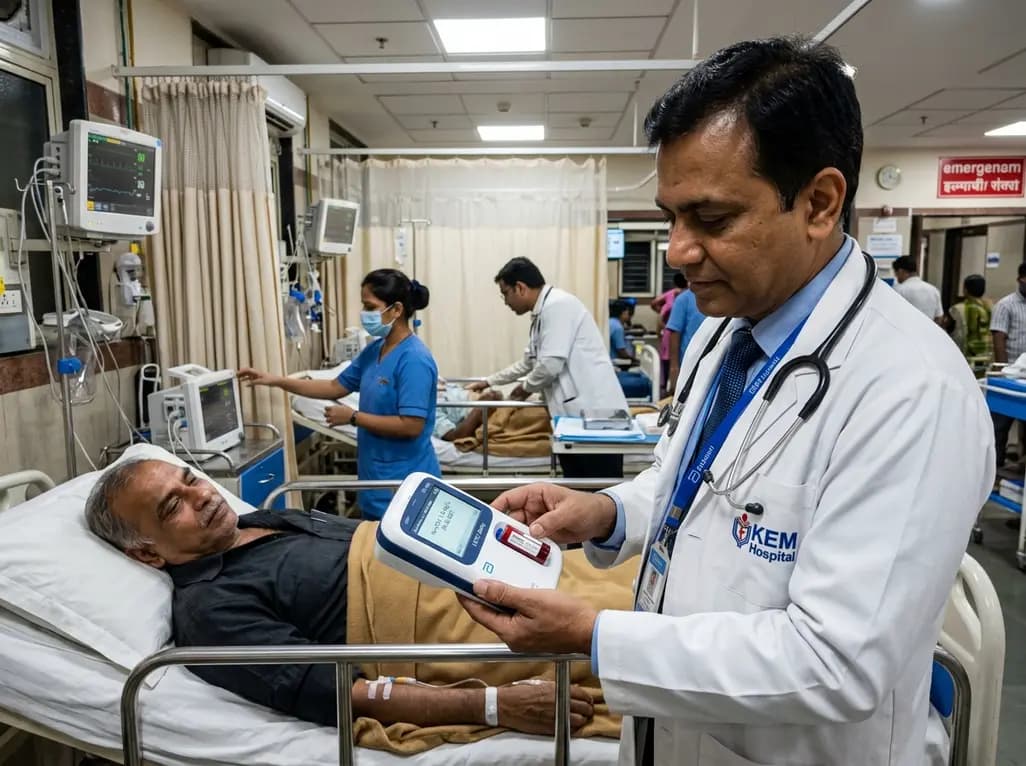
A real-world emergency department evaluation demonstrates that the Abbott i-STAT Alinity point-of-care high-sensitivity troponin I assay achieves excellent analytical precision and safely rules out myocardial infarction without false negatives, offering rapid bedside results to decongest acute care pathways.
Today

A recent scoping review highlights the efficacy, usability, and patient satisfaction of virtual reality pain management for chronic musculoskeletal pain, emphasizing psychotherapy-based VR protocols.
Today
