

Loading, please wait...
Loading, please wait...

Myelin oligodendrocyte glycoprotein antibody-associated disease represents a distinct autoimmune disorder of the central nervous system. Consequently, clinicians frequently order longitudinal antibody assays to guide therapeutic planning. Tracking MOG-IgG serostatus change offers vital diagnostic and prognostic clues for treating physicians. However, prior investigations left significant gaps regarding how often antibody levels genuinely shift over time. To address this question, researchers evaluated a large clinical cohort undergoing serial serum antibody testing. Their findings clarify longitudinal antibody trajectories and provide practical insights for real-world neurology practice.
The investigative team analyzed a longitudinal cohort of 272 patients tested serially at the Cleveland Clinic between 2017 and 2025. Neurologists routinely encounter suspected demyelinating syndromes, including optic neuritis, transverse myelitis, and acute disseminated encephalomyelitis. Therefore, establishing reproducible serological benchmarks is critical for precise diagnostic confirmation. The researchers utilized validated cell-based assays to measure circulating antibodies reliably across serial evaluations. In addition, the investigators systematically reviewed demographic characteristics, baseline clinical presentations, and concurrent immunosuppressive therapies. By following these patients over multiple years, the team calculated precise time-to-event probabilities. Furthermore, this rigorous design minimized misclassification bias by requiring consistent testing intervals. Clinicians often wonder whether a single positive result commits a patient to lifelong treatment. Consequently, understanding the genuine incidence of antibody disappearance helps prevent unnecessary chronic immunosuppression. The cohort reflects typical outpatient and inpatient neuroimmunology populations seen in tertiary referral centers. Thus, the observational data supply highly relevant insights for daily clinical encounters.
Kaplan-Meier survival analyses yielded striking findings regarding longitudinal antibody stability. Among the 272 serially evaluated individuals, 16 patients experienced confirmed seroreversion to negative status. In contrast, only 4 patients underwent seroconversion from negative to positive. When examining baseline seropositive individuals, seroreversion occurred in 16 of 59 patients, representing 27 percent of that group. Moreover, the 1-year seroreversion-free probability stood at 85 percent, with a 95 percent confidence interval spanning 76 to 96 percent. This metric indicates that more than one in ten seropositive patients lose detectable antibodies within 12 months. Conversely, seroconversion remained exceptionally uncommon throughout the follow-up period. The 1-year seroconversion-free probability reached 98 percent, with a tight confidence interval between 95 and 100 percent. Therefore, an initially negative test demonstrates remarkable stability over prolonged surveillance. These statistical observations carry substantial clinical weight. Specifically, clinicians should recognize that seroreversion happens relatively often in positive cohorts. However, repeat testing rarely uncovers new seropositivity in patients who initially present with negative titers. Accordingly, serial testing yields markedly disparate clinical returns depending on the initial antibody baseline.
Identifying specific characteristics that predict antibody clearance can substantially refine patient prognostication. In this investigation, initial antibody titer emerged as the most critical determinant of eventual seroreversion. Specifically, 11 of the 16 patients who seroreverted exhibited low baseline titers at or below 1:100. Conversely, individuals with markedly elevated baseline titers tended to maintain sustained seropositivity over longitudinal follow-up. In addition to low titers, clinical outcomes closely paralleled the serological trajectory. Notably, patients who successfully seroreverted experienced no subsequent disease relapses following antibody clearance. This finding strongly suggests that antibody disappearance reflects genuine immunological remission rather than transient laboratory fluctuations. Furthermore, patients with monophasic disease phenotypes more commonly achieved seroreversion than those with relapsing courses. Clinicians often struggle to distinguish monophasic events from early relapsing disease during initial presentation. As a result, monitoring titer decay over time provides an objective biological marker of disease quiescence. Pediatric patients also demonstrated distinctive antibody dynamics compared to older cohorts. Hence, integrating baseline titer levels with clinical history allows practitioners to identify individuals likely to experience spontaneous resolution.
The observed seroreversion frequency fundamentally alters therapeutic decision-making in demyelinating disease. In acute settings, clinicians aggressively administer high-dose intravenous corticosteroids, plasma exchange, or intravenous immunoglobulins. However, the subsequent requirement for sustained maintenance immunotherapy represents an enduring dilemma. Chronic immunosuppressive agents, such as azathioprine, mycophenolate mofetil, and rituximab, carry notable risks of opportunistic infection and malignancy. Consequently, neurologists must carefully balance relapse prevention against medication toxicity. The study data show that patients who achieve seroreversion face minimal risk of relapse. Therefore, practitioners can thoughtfully contemplate tapering and ultimately discontinuing chronic immunosuppressive regimens in patients demonstrating persistent antibody negativity. Conversely, patients with persistently high titers require prolonged prophylactic maintenance because they face elevated recurrence risks. Furthermore, routine therapeutic re-evaluations should integrate serial antibody measurements taken several months apart. If a patient maintains negative status alongside complete radiological stability, clinicians can confidently avoid unnecessary drug escalation. In this manner, longitudinal serostatus documentation directly protects patients from prolonged drug toxicity. Thus, serological monitoring transforms empirical management into tailored, precision-guided neuroimmunology.
These findings offer clear, practical guidance for ordering serial serological evaluations. Given the low rate of seroconversion, routine repeat testing in initially seronegative patients offers very low diagnostic yield. Neurologists should not order indiscriminate follow-up testing for negative patients unless new, typical demyelinating symptoms arise. Conversely, serial testing delivers substantial diagnostic and prognostic utility for patients who initially test positive. In seropositive individuals, clinicians should consider re-testing at 6 to 12 months after the index attack. Documenting persistent negativity provides objective reassurance that enables clinicians to de-escalate treatment safely. Moreover, laboratory methodologies require careful standardization across serial measurements. Clinicians should utilize live or fixed cell-based assays rather than traditional enzyme-linked immunosorbent assays. Cell-based assays provide superior diagnostic specificity and minimize misleading false-positive interpretations. In addition, treating physicians must evaluate antibody results alongside clinical relapse history and neuroimaging findings. When serial testing reveals fluctuating low titers, clinicians must exercise caution before modifying therapies. Overall, rational serological surveillance streamlines laboratory resource utilization and reduces unnecessary diagnostic costs. Consequently, targeted testing protocols empower clinicians to deliver efficient, patient-centered care for autoimmune demyelinating diseases.
Seroreversion occurs in approximately 27 percent of patients who initially test positive for MOG-IgG. Longitudinal survival analyses demonstrate that the 1-year seroreversion-free probability is 85 percent among seropositive cohorts. This antibody clearance happens most frequently in patients with baseline titers at or below 1:100. Furthermore, individuals who achieve seroreversion rarely experience subsequent relapses, suggesting that serological clearance correlates with genuine clinical quiescence and disease remission.
Clinicians should avoid routine, indiscriminate re-testing in patients who initially demonstrate seronegative status. The research demonstrates a 1-year seroconversion-free probability of 98 percent, with only 1 percent of patients seroconverting overall. Therefore, negative results remain highly stable over longitudinal follow-up. Serial re-testing yields minimal diagnostic benefit unless a patient subsequently develops atypical, progressive, or recurrent neuroinflammatory symptoms that strongly suggest newly emerging autoimmune pathology.
Low baseline antibody titers represent the single most important predictor of future seroreversion in clinical practice. In longitudinal cohorts, the vast majority of patients who seroreverted exhibited titers at or below 1:100 at presentation. In addition, patients experiencing a monophasic clinical course and pediatric patients exhibit higher likelihoods of antibody clearance. Conversely, patients presenting with markedly elevated antibody titers generally maintain persistent seropositivity over extended surveillance intervals.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A longitudinal study reveals that MOG-IgG seroreversion occurs in over a quarter of initially positive patients, particularly those with low titers, while seroconversion remains rare. These findings clarify the clinical utility of serial antibody testing in suspected neuroinflammatory disorders.
Today

A cross-sectional study of 543 patients evaluated the clinical and economic impact of hemophilia inhibitors, revealing higher annual bleeding rates, increased treatment complexity, and severe orthopedic disability, highlighting the need for routine inhibitor screening and modern prophylactic strategies.
Today

Doctors at AIIMS New Delhi have achieved a historic milestone by performing India's first open prenatal myelomeningocele repair on a 25-week unborn fetus. This landmark multidisciplinary procedure provides vital neuroprotective benefits, lowers hydrocephalus risks, and transforms maternal-fetal medicine nationwide.
Today

A randomized crossover trial reveals that daily fresh watermelon consumption significantly reduces baseline TMAO levels and favorably modulates lipid profiles, lowering triglycerides and LDL cholesterol in adults with overweight and obesity.
Today
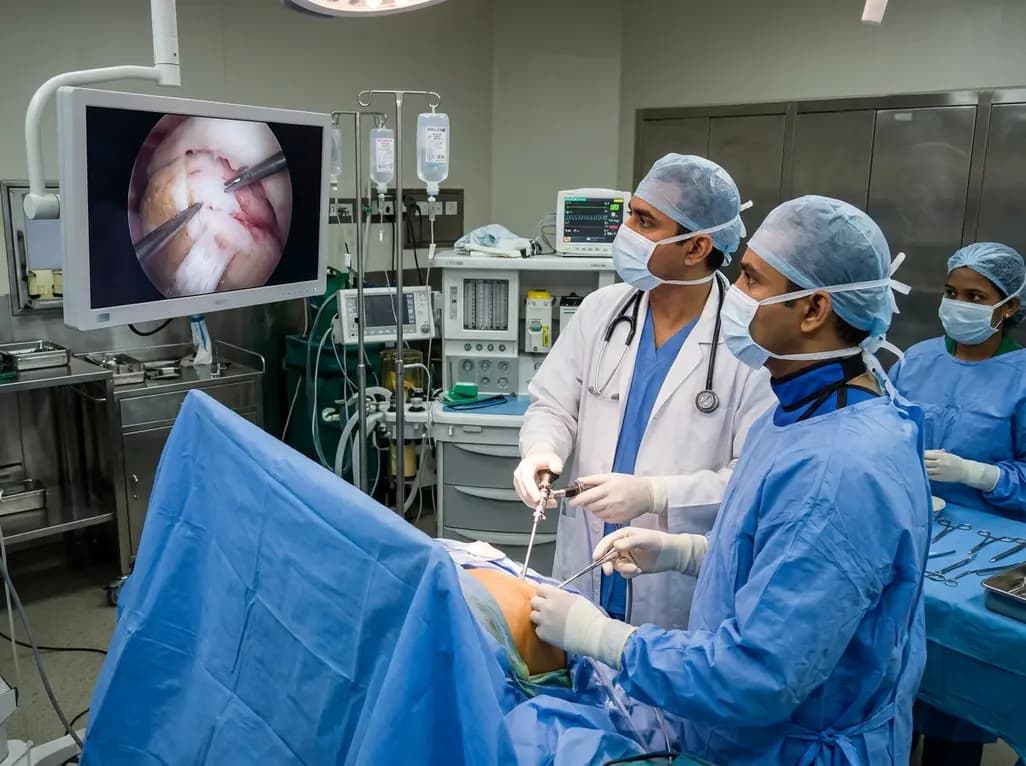
Discover how all-arthroscopic repair using a resorbable bioinductive bovine collagen implant offers a reproducible biologic solution for partial-thickness upper border subscapularis tears, enhancing healing while preserving native tendon architecture.
Today

A large-scale retrospective cohort study demonstrates that GLP-1 receptor agonists significantly reduce all-cause hospitalizations, alcohol-related admissions, major cardiovascular events, and mortality in patients with overweight or obesity and alcohol use disorder, providing profound clinical insights.
Today
