

Loading, please wait...
Loading, please wait...

Primary progressive aphasia represents a challenging group of neurodegenerative syndromes characterized by the gradual dissolution of speech and language functions. Unlike typical dementias that present primarily with episodic memory deficits, primary progressive aphasia first degrades verbal communication while relatively sparing other cognitive domains. Consequently, early clinical recognition remains critical for directing appropriate supportive therapies and counseling families. Unfortunately, comprehensive neurolinguistic evaluations often require several hours of exhaustive testing by highly specialized neuropsychologists. Because standard bedside tests like the Mini-Mental State Examination fail to capture subtle linguistic nuances, clinicians frequently struggle to detect early decline. Furthermore, general cognitive screenings cannot adequately differentiate the primary linguistic subtypes. To address this clinical barrier, international researchers designed the Mini-Linguistic State Examination as an efficient screening instrument. This bedside tool reliably assesses speech production, syntactic structures, and lexical retrieval without demanding exhaustive time commitments. Therefore, adapting and validating this structured instrument across diverse languages provides clinicians with an indispensable diagnostic bridge. Neurologists can now swiftly evaluate suspected neurodegenerative language decay in daily outpatient consultations with objective confidence.
The Mini-Linguistic State Examination evaluates communicative competence across five distinct neurolinguistic domains rather than generating an uninformative, single composite metric. Specifically, the test examines motor speech fluency, phonological competence, semantic knowledge, syntactic comprehension, and verbal working memory. During the motor speech evaluation, clinicians systematically listen for effortful articulation, dysarthria, and speech apraxia. In contrast, the phonological assays analyze phonetic substitutions, sound distortions, and phonemic paraphasias during spontaneous output and repetition. Additionally, the semantic subtests appraise word-picture matching and single-word comprehension to identify lexical deterioration. Syntactic testing evaluates complex grammatical arrangements, passive sentence constructions, and word order decoding. Finally, clinicians measure verbal working memory through challenging phrase repetition and forward auditory spans. Because each domain targets distinct anatomical networks within the left perisylvian language cortex, the screening profiles directly mirror underlying neurobiology. Furthermore, scoring relies on rigorous error classification rather than simple binary pass-fail judgments. Consequently, examiners capture granular linguistic breakdown even when patients achieve borderline scores on conventional mental status assessments. This structured approach establishes a remarkably robust baseline for longitudinal tracking.
A recent multicenter cohort study robustly evaluated the Dutch adaptation of this examination in ninety patients and 276 healthy controls. Among the clinical cohort, participants represented nonfluent variant, logopenic variant, and semantic variant presentations, alongside unclassified syndromes. Healthy volunteers achieved high total scores ranging from 83 to 100 points out of 100. In striking contrast, patients with primary progressive aphasia scored markedly lower, displaying scores between 30 and 96 points. Statistical analyses demonstrated outstanding overall diagnostic accuracy, achieving an area under the curve of 0.99 for total score discrimination. Moreover, individual linguistic subdomains exhibited strong discriminatory capacity, with domain areas under the curve spanning from 0.80 to 0.92. Nonfluent variant patients demonstrated pronounced motor speech errors and prominent agrammatism, reflecting frontal opercular damage. Conversely, semantic variant patients exhibited severe semantic degradation while preserving motor execution and phonological clarity. Linear modeling confirmed that these significant group differences persisted even after adjusting for patient age and demographic factors. Consequently, the validated examination provides clinicians with exceptional statistical precision when separating neurodegenerative speech syndromes from healthy cognitive aging.
Distinguishing logopenic variant presentations from semantic dementia often creates profound diagnostic dilemmas for practicing neurologists and geriatricians. However, the multi-domain examination reliably disentangles these contrasting clinical syndromes through distinct neurolinguistic error patterns. Patients presenting with the logopenic variant demonstrated the most profound verbal working memory deficits across all evaluated groups. Furthermore, these individuals exhibited substantial phonological retrieval breakdowns and sentence repetition failures, consistent with temporoparietal junction pathology. In contrast, patients with semantic variant progressive aphasia preserved working memory spans but demonstrated catastrophic losses in word recognition and naming. Interestingly, syntactic errors occurred across all primary progressive aphasia variants, highlighting that grammatical processing degrades broadly across neurodegenerative language disorders. However, prominent phonological errors remained uniquely elevated in both logopenic and nonfluent subtypes. Thus, clinicians can interpret domain dissociation patterns to pinpoint underlying pathological trajectories without relying entirely on expensive molecular imaging. When physicians combine these bedside neurolinguistic metrics with structural neuroimaging, diagnostic confidence increases substantially, enabling tailored behavioral interventions.
The successful adaptation and validation of this screening tool carry substantial implications for global cognitive neurology and dementia care. Crucially, the investigation included eleven patients diagnosed with unclassified primary progressive aphasia, who frequently elude strict diagnostic consensus criteria. The examination revealed widespread deficits across syntax, phonology, semantics, and working memory in these individuals, sparing only motor speech mechanics. Therefore, the examination effectively captures mixed and atypical neurodegenerative presentations that standard clinical criteria fail to categorize neatly. In routine practice, primary care physicians and specialists can complete this comprehensive linguistic screening in approximately twenty minutes. Because the instrument uses culturally and linguistically adaptable stimuli, medical centers worldwide can standardize their cognitive screening batteries. In multicultural regions such as India, adapting standardized tools across regional vernaculars remains essential for equitable neurological healthcare. Additionally, identifying precise linguistic phenotypes allows clinicians to counsel families accurately regarding anticipated functional loss. Ultimately, deploying rapid, standardized linguistic screening tools will optimize patient stratification for upcoming disease-modifying clinical trials.
Primary progressive aphasia features language and speech deterioration as its most prominent initial symptom, leaving memory, visual-spatial awareness, and reasoning relatively intact early on. In contrast, typical Alzheimer disease primarily impairs episodic memory and disorientation first, although logopenic progressive aphasia shares underlying Alzheimer neuropathology in most clinical cases.
The examination typically requires fifteen to twenty minutes to complete at the patient bedside or in an outpatient clinic. Because examiners assess five focused linguistic domains through concise, targeted tasks, the test provides rich diagnostic data without causing cognitive fatigue in vulnerable neurodegenerative patients.
Yes, the examination effectively characterizes unclassified presentations by documenting deficits across multiple domains, including phonological processing, syntactic comprehension, working memory, and semantic knowledge. While these mixed presentations fail canonical consensus criteria, the five-domain profile accurately captures their widespread linguistic breakdown while sparing motor speech.
Disclaimer: This content is for informational and educational purposes only. It should not be used as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition or treatment. Refer to the latest local and national guidelines for clinical practice.
References
Coppieters R et al. The Dutch Mini-Linguistic State Examination (MLSE-NL): findings in Primary Progressive Aphasia (PPA). J Neurol. 2026 Oct 23. doi: 10.1007/s00415-026-14203-3. PMID: 42909640.
Patel N, Peterson KA, Ingram RU, et al. A 'Mini Linguistic State Examination' to classify primary progressive aphasia. Brain Commun. 2022;4(2):fcab299.
Gorno-Tempini ML, Hillis AE, Weintraub S, et al. Classification of primary progressive aphasia and its variants. Neurology. 2011;76(11):1006-1014.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A validation study evaluates the Mini-Linguistic State Examination (MLSE-NL) across 90 patients with primary progressive aphasia and 276 controls. The tool demonstrated exceptional diagnostic discrimination with an overall AUC of 0.99, accurately differentiating canonical variants and unclassified syndromes.
Today

Novel glucose-responsive mPEG-PSA nanocarriers deliver insulin aspart on demand, achieving dual postprandial and basal glycemic control without hypoglycemia in diabetic models. This biomaterial breakthrough offers promising clinical implications for physiologic diabetes management.
Today
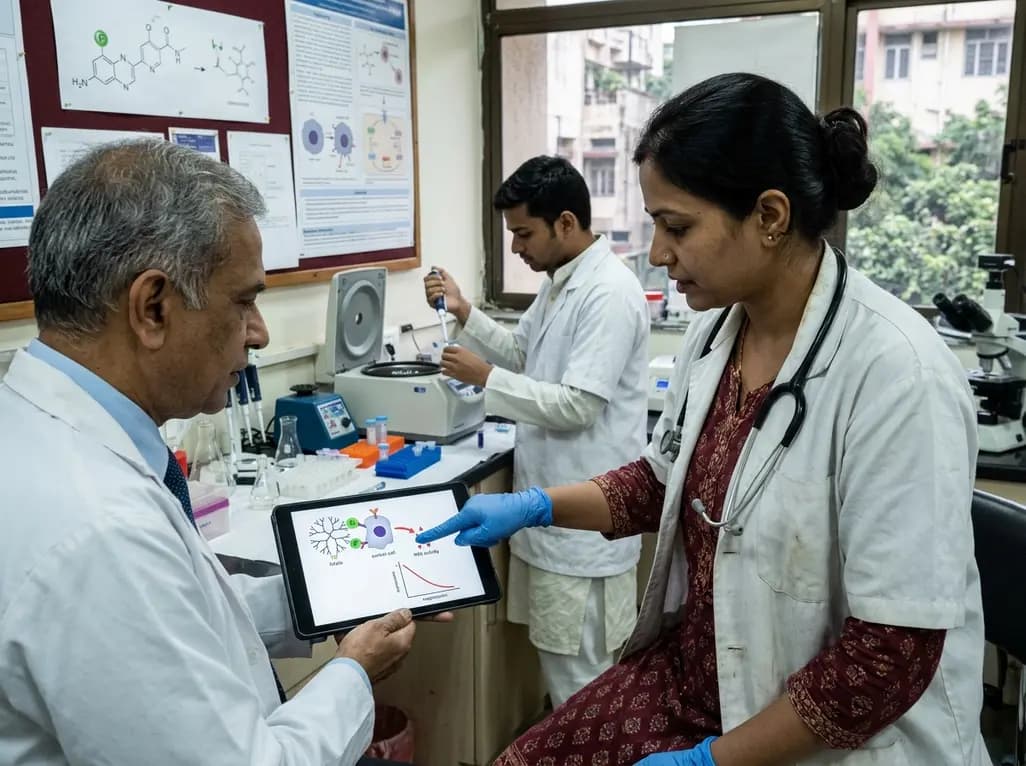
A novel folate-conjugated tecto-dendrimer nanoplatform successfully delivers siRNA to achieve targeted HK2 silencing, disrupting ovarian cancer glycolysis and suppressing lactate output.
Today

A comparative non-contact study reveals that high-power radiofrequency delivery with the QDOT MICRO catheter induces an artifactual contact force rise. Electrophysiologists must understand this power-dependent thermal and electrical phenomenon to avoid inadvertent catheter withdrawal and ineffective ablation.
Today

A novel proof-of-concept study presents a six-degree-of-freedom articulated manikin neck equipped with linear potentiometers. The system provides real-time kinematic motion feedback during cervical immobilisation, delivering sub-degree tracking accuracy to improve pre-hospital trauma training and patient safety.
Today

A retrospective comparative cohort study evaluated genitourinary safety in HFpEF between dapagliflozin and empagliflozin over six months. Rates of symptomatic UTI and asymptomatic bacteriuria showed no statistically significant differences, supporting comparable safety profiles across both SGLT2 inhibitors.
Today
