

Loading, please wait...
Loading, please wait...

Sodium-glucose cotransporter 2 inhibitors represent a foundational pillar in modern heart failure management. Today, international cardiology guidelines strongly recommend these agents for all ejection fraction phenotypes. Specifically, both dapagliflozin and empagliflozin reduce cardiovascular death and hospitalizations across diverse patient populations. However, evaluating genitourinary safety in HFpEF remains an essential consideration for practicing clinicians. Because these medications induce continuous urinary glucose excretion, physicians frequently worry about potential infectious complications. Urinary glucose creates a favorable microenvironment that may promote bacterial proliferation in the bladder. Consequently, fear of genitourinary infections often causes clinician hesitation during drug initiation. Although major clinical trials confirmed overall drug tolerability, direct comparative safety data between specific agents remain scarce. Most randomized trials evaluated adverse events in isolation rather than through head-to-head comparisons. In clinical settings, physicians wonder whether subtle pharmacological distinctions between dapagliflozin and empagliflozin influence real-world infection rates. Therefore, dedicated observational studies provide critical clarity. By analyzing comparative safety outcomes, clinicians can make balanced prescribing decisions without compromising cardioprotective care. Consequently, clinicians must examine real-world comparative evidence to optimize patient safety.
To evaluate this important clinical question, researchers conducted a retrospective comparative cohort study at a single academic medical center. The investigators analyzed electronic health records of 239 consecutive adult patients with physician-documented heart failure with preserved ejection fraction. Every included participant maintained at least six months of continuous follow-up after starting therapy. Among these patients, 113 received dapagliflozin 10 mg daily and 126 received empagliflozin 10 mg daily. Furthermore, the investigators carefully categorized urinary events to distinguish true clinical pathology from harmless findings. They separated documented events into symptomatic urinary tract infections and asymptomatic bacteriuria. This methodological approach is essential because asymptomatic bacteriuria does not indicate active tissue invasion. In contrast, symptomatic infections cause notable clinical discomfort and can interrupt lifesaving heart failure therapy. The research team systematically tracked positive laboratory cultures, clinic notes, and associated clinical diagnoses. By applying this rigorous stratification, the study evaluated genuine adverse drug events during routine clinical care. Moreover, this single-center cohort offered consistent medical record documentation and standardized laboratory testing. Thus, the analysis provides practical insights into comparative drug safety outside strict clinical trial protocols.
Throughout the six-month follow-up interval, the composite outcome of documented bacteriuria or infection showed very similar frequencies. Specifically, 21 out of 113 dapagliflozin patients developed this composite outcome, representing 18.6 percent. Similarly, 25 out of 126 empagliflozin patients met the composite endpoint, representing 19.8 percent. Consequently, the absolute risk difference between empagliflozin and dapagliflozin was only 1.3 percentage points. The 95 percent confidence interval spanned from minus 8.9 to positive 11.2 percentage points. Furthermore, symptomatic urinary tract infections occurred infrequently across both cohorts. Only four dapagliflozin patients, or 3.5 percent, experienced genuine symptomatic infection. Likewise, five empagliflozin patients, or 4.0 percent, developed symptomatic urinary symptoms. In contrast, asymptomatic bacteriuria accounted for most positive microbiological tests. Asymptomatic colonization appeared in 15.0 percent of dapagliflozin recipients and 15.9 percent of empagliflozin recipients. Other genitourinary complications, such as severe mycotic infections, remained exceptionally uncommon in both groups. Therefore, neither drug demonstrated a meaningful increase in infectious complications compared to the other. Furthermore, the low absolute rate of symptomatic infection provides strong clinical reassurance. These findings show reassuring parity between both agents during routine outpatient therapy.
To address potential baseline confounding, the investigators constructed a multivariable logistic regression model. This statistical model adjusted for patient age, biological sex, and baseline estimated glomerular filtration rate. Following adjustment, the odds ratio for documented bacteriuria or infection comparing empagliflozin to dapagliflozin was 1.62. However, this finding did not achieve statistical significance. The 95 percent confidence interval remained broad, ranging from 0.76 to 3.45 with a p-value of 0.208. Because the confidence interval encompasses both potential harm and potential benefit, clinicians cannot claim true statistical equivalence. In addition, retrospective observational designs introduce unavoidable surveillance limitations. For example, symptomatic individuals naturally undergo diagnostic testing more frequently than completely asymptomatic patients. Consequently, differential urine testing in routine practice might influence recorded infection rates. Furthermore, single-center datasets reflect localized prescribing habits and patient demographic factors. Consequently, prospective multi-center investigations remain necessary to corroborate these initial observational findings. Nevertheless, the adjusted model confirms that age and baseline renal function did not produce divergent infectious risks between therapies. Thus, the comparative findings remain broadly reassuring for bedside practitioners selecting an initial agent.
These observational results provide essential practical guidance for managing heart failure with preserved ejection fraction. Importantly, approximately fifteen percent of patients exhibited asymptomatic bacteriuria without experiencing dysuria or fever. Contemporary clinical guidelines strongly advise against screening for or treating asymptomatic bacteriuria in ambulatory patients. Indiscriminate antimicrobial therapy increases antibiotic resistance and unnecessary adverse reactions. Furthermore, inappropriate antibiotic prescribing often causes clinicians to discontinue vital heart failure therapies prematurely. Instead, physicians should educate patients on recognizing cardinal infection symptoms before treatment initiation. Patients should promptly report fever, flank pain, dysuria, or sudden urinary frequency. When uncomplicated cystitis occurs, clinicians can generally prescribe standard oral antibiotics while continuing SGLT2 inhibitor therapy. Clinicians should only stop therapy if patients experience severe complicated pyelonephritis or recurrent intractable infections. In addition, healthcare teams must encourage proper personal hygiene and consistent daily hydration. Meticulous perineal care helps prevent colonizing bacteria from establishing invasive urinary infections. Consequently, proactive patient education remains the cornerstone of safe long-term SGLT2 inhibitor therapy. Ultimately, clinicians can confidently choose either dapagliflozin or empagliflozin based on formulary availability and patient access.
Current comparative clinical data show no statistically significant difference in infection rates between empagliflozin and dapagliflozin. In real-world cohort evaluations, symptomatic urinary tract infections developed in approximately four percent of patients receiving either medication. Although minor numerical variations appear across observational studies, wide confidence intervals encompass both directions of effect. Therefore, clinicians can consider both sodium-glucose cotransporter 2 inhibitors equally safe regarding genitourinary risks when managing heart failure with preserved ejection fraction.
Clinicians should avoid routine urine culture screening in asymptomatic patients taking sodium-glucose cotransporter 2 inhibitors. Real-world studies show that up to sixteen percent of these patients have asymptomatic bacterial colonization. However, major infectious disease guidelines recommend against treating asymptomatic bacteriuria because antibiotic administration does not improve clinical outcomes or prevent symptomatic infections. Instead, indiscriminate antimicrobial therapy increases bacterial resistance and risks adverse drug reactions without providing clinical benefit to heart failure patients.
When patients develop genitourinary symptoms, clinicians must first confirm active infection through targeted urinalysis and culture testing. Healthcare providers should prescribe pathogen-directed antimicrobial therapy while reviewing personal hygiene and hydration habits. Fortunately, most uncomplicated urinary tract infections resolve promptly without discontinuing the heart failure medication. Clinicians should only consider temporary drug cessation if patients experience severe complicated infections, recurrent pyelonephritis, or invasive fungal disease unresponsive to standard outpatient antifungal regimens.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A retrospective comparative cohort study evaluated genitourinary safety in HFpEF between dapagliflozin and empagliflozin over six months. Rates of symptomatic UTI and asymptomatic bacteriuria showed no statistically significant differences, supporting comparable safety profiles across both SGLT2 inhibitors.
Today
A novel folate-conjugated tecto-dendrimer nanoplatform successfully delivers siRNA to achieve targeted HK2 silencing, disrupting ovarian cancer glycolysis and suppressing lactate output.
Today
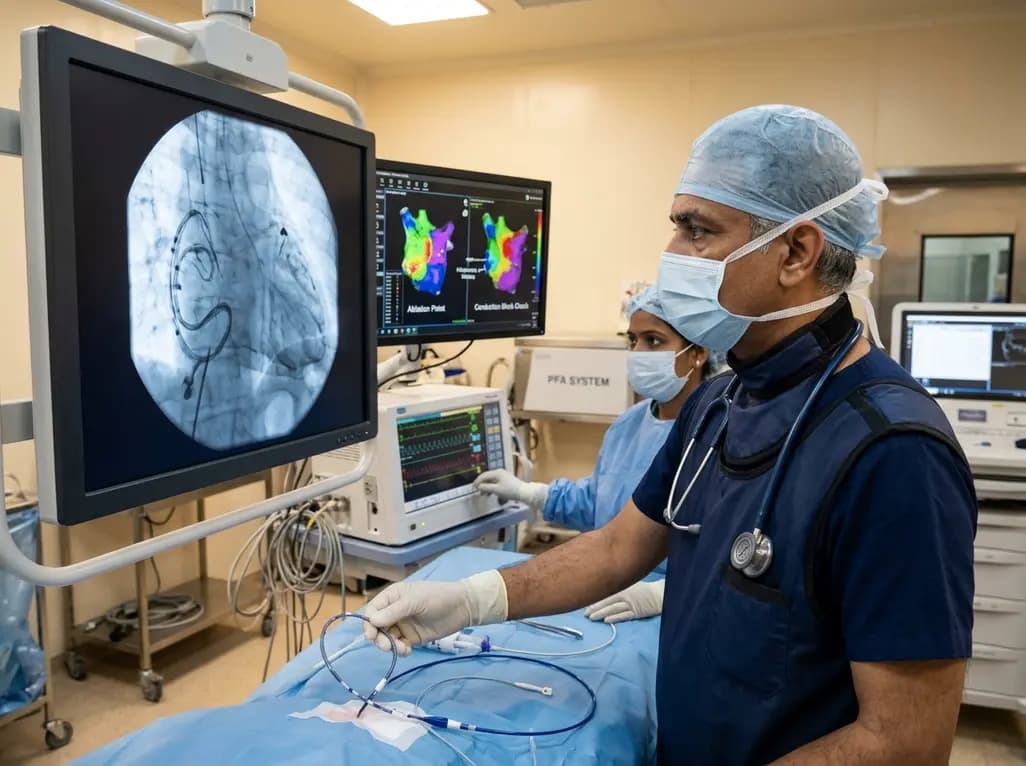
A retrospective analysis reveals that cavotricuspid isthmus ablation using a variable-loop pulsed field ablation catheter achieves acute conduction block safely and efficiently during concomitant atrial fibrillation procedures.
Today

A novel proof-of-concept study presents a six-degree-of-freedom articulated manikin neck equipped with linear potentiometers. The system provides real-time kinematic motion feedback during cervical immobilisation, delivering sub-degree tracking accuracy to improve pre-hospital trauma training and patient safety.
Today

Protein O-GlcNAcylation couples cellular nutrient status to vital neuronal functions. This review explores how disrupted O-GlcNAc cycling drives both neurodevelopmental delays and neurodegenerative cascades, positioning metabolic post-translational modifications as therapeutic targets in clinical neurology.
Today
