

Loading, please wait...
Loading, please wait...
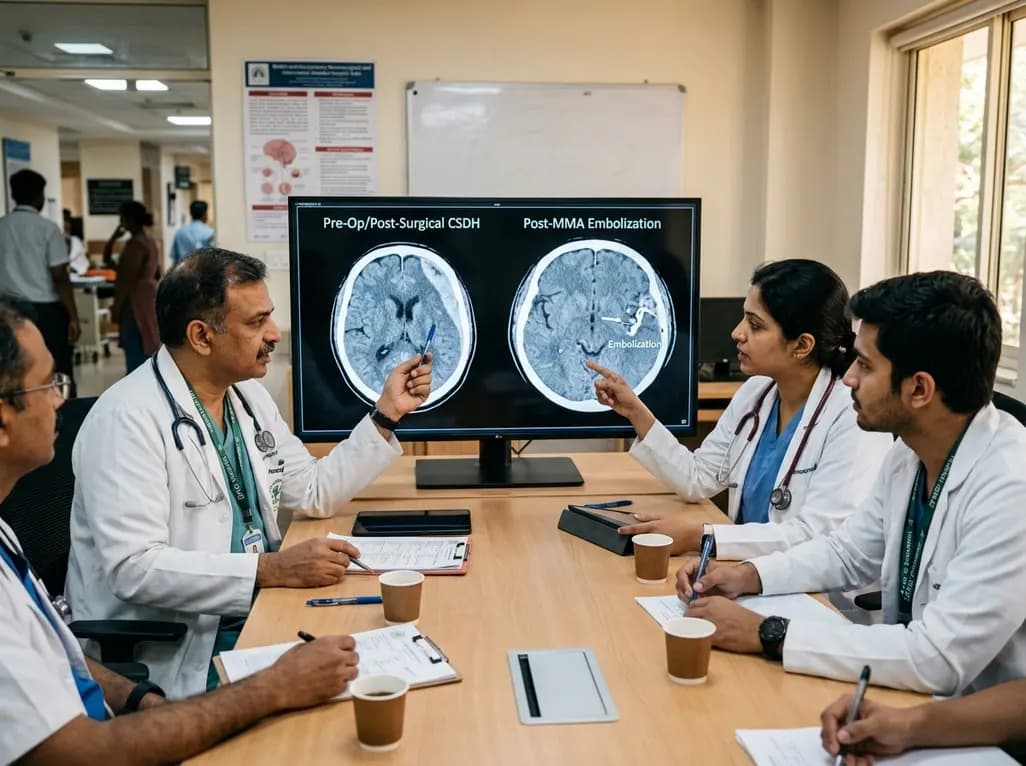
Chronic subdural hematoma represents an escalating neurosurgical challenge worldwide, particularly among aging demographics. Recent clinical findings highlight that adjunctive middle meningeal artery embolization substantially improves post-procedural outcomes following surgical evacuation. Historically, standard operative interventions such as burr-hole craniostomy and craniotomy have provided immediate brain decompression. However, high recurrence rates remain a persistent obstacle in routine neurosurgical care. The integration of endovascular devascularization directly targets the pathophysiology of recurrent microhemorrhages, offering clinicians a powerful adjunctive strategy to improve patient survival.
Chronic subdural hematoma is rapidly becoming the most frequently encountered cranial neurosurgical pathology worldwide. As life expectancy increases, clinicians observe a dramatic surge in elderly patients presenting with symptomatic subdural fluid collections. Furthermore, widespread antiplatelet and anticoagulant regimens significantly amplify bleeding risks in this vulnerable population. Pathophysiologically, the condition originates when bridging cortical veins rupture within the dural border cell layer after minor head trauma. Consequently, an inflammatory cascade triggers neo-angiogenesis, forming fragile, hyperpermeable neocapillaries along outer subdural membranes.
These fragile microvessels continually weep exudate and microhemorrhages, resulting in insidious hematoma expansion. Although open surgical evacuation rapidly relieves mechanical brain compression, it frequently leaves the outer vascularized membranes intact. Consequently, recurrence rates historically range between 10% and 30%, frequently mandating hazardous revision surgeries. Therefore, addressing the underlying dural vascular supply represents an essential therapeutic objective for preventing long-term clinical deterioration and repeat hospitalizations.
Recent real-world data from the National Readmissions Database demonstrate compelling clinical benefits when combining surgery with middle meningeal artery embolization. In a rigorous propensity score-matched analysis of adults undergoing surgical evacuation, researchers evaluated index hospitalization and follow-up metrics. Notably, the study revealed that adjunctive transcatheter arterial occlusion significantly reduced 30-day all-cause readmission rates compared to surgical evacuation alone. Specifically, post-match regression analyses demonstrated a statistically significant 18% relative reduction in readmissions, underscoring enhanced therapeutic durability.
In addition, multiple landmark multicenter randomized trials provide robust validation for these observational findings. Interventional studies utilizing liquid embolic agents have consistently demonstrated substantial reductions in hematoma recurrence requiring reoperation. Furthermore, real-world registry evaluations confirm that embolization functions safely alongside standard burr-hole drainage without increasing serious procedural complications. Thus, these cumulative findings establish endovascular devascularization as a transformative adjunct in modern neurosurgical practice.
The reduction in post-discharge readmission translates into major clinical and economic improvements for health systems. In the propensity-matched nationwide cohort, patients receiving adjunctive endovascular therapy exhibited an 8.8% readmission rate versus 11% in the control group. Because repeated hospitalizations in frail, elderly individuals precipitate nosocomial complications, this reduction preserves cognitive and functional independence. Additionally, preventing repeat surgical decompression mitigates anesthesia risks, systemic infections, and secondary functional decline in vulnerable geriatric patients.
Even more strikingly, the nationwide analysis documented a substantial decrease in in-hospital mortality among patients receiving embolization. Specifically, in-hospital mortality dropped from 4.5% in the surgery-alone cohort to 2.4% in the adjunctive embolization cohort. This relative risk reduction of approximately 48% highlights the life-saving potential of stabilizing the dural vascular network. Consequently, minimizing rebleeding events directly prevents lethal intracranial pressure spikes and secondary neurological deterioration.
To understand these profound clinical gains, clinicians must examine how endovascular therapy halts chronic hematoma progression. The middle meningeal artery serves as the primary arterial feeder supplying the outer neocapillary membranes of the subdural collection. By selectively catheterizing the anterior and posterior convexities of the middle meningeal artery, neurointerventionalists deploy embolic agents directly into target branches. Consequently, this targeted occlusion starves the hypervascular dural membranes of arterial inflow, shutting down the cycle of rebleeding and exudation.
Currently, operators employ various embolic materials, including polyvinyl alcohol particles and non-adhesive liquid embolic systems. Successful microcatheter positioning distal to dangerous anastomoses, particularly petrosal branches and ophthalmic collaterals, ensures maximum procedural safety. Furthermore, performing the procedure during the index hospitalization provides immediate dural stabilization prior to hospital discharge. Thus, this endovascular technique directly addresses the biological driver of hematoma persistence while preserving surrounding parenchymal perfusion.
Implementing adjunctive transcatheter embolization necessitates close collaboration between neurosurgeons, neurologists, neurointerventional radiologists, and neurointensivists. First, early multidisciplinary screening identifies high-risk surgical candidates who derive maximum benefit from concurrent endovascular therapy. Specifically, patients with bilateral collections, extensive membrane neo-vascularization, brain atrophy, or mandatory anticoagulation represent ideal candidates. Moreover, establishing standardized clinical pathways accelerates procedural scheduling, thereby minimizing unnecessary delays during index admissions.
In addition, post-procedural neurological monitoring in neurointensive care units ensures prompt detection of rare access-site or embolic complications. Clinicians must also tailor antithrombotic resumption timelines based on individual hemostatic and thromboembolic risks. Consequently, comprehensive interdisciplinary management protocols optimize clinical pathways and reduce acute lengths of stay. Therefore, institutions adopting coordinated neurovascular workflows can achieve superior patient outcomes and reduce overall readmission burdens.
Looking forward, neurovascular guidelines are evolving rapidly to integrate endovascular techniques into standard management algorithms. As global population aging accelerates, chronic subdural hematomas will place unprecedented demands on hospital resources. Consequently, adopting minimally invasive strategies that definitively curtail recurrence will prove essential for healthcare sustainability. Ongoing randomized trials continue to evaluate standalone embolization for mildly symptomatic hematomas, potentially expanding indications beyond adjunctive surgery.
Furthermore, continuous advances in microcatheter navigation, selective intra-arterial imaging, and specialized embolic materials enhance procedural efficacy and safety. As health economic models increasingly demonstrate cost-effectiveness through averted reoperations, health systems will expand access to interventional suites. Ultimately, embedding transcatheter dural embolization within multidisciplinary protocols establishes a proactive, physiology-directed approach to managing this complex intracranial disorder.
The procedure selectively occludes the middle meningeal artery branches supplying the fragile, hypervascular outer membranes of the hematoma. Consequently, shutting down this arterial inflow halts continuous microhemorrhages and fluid exudation. This interruption of chronic inflammatory cycles allows natural resorption of fluid and prevents recurrent hematoma expansion.
Adjunctive embolization is typically performed during the index hospitalization, either immediately preceding or shortly following surgical evacuation. Performing the intervention early ensures rapid devascularization of neo-membranes. Consequently, this timely approach stabilizes the subdural space, minimizes early rebleeding risks, and protects patients prior to hospital discharge.
Nationwide propensity-matched studies demonstrate that adjunctive embolization significantly reduces 30-day all-cause readmissions and cuts in-hospital mortality by nearly half compared to surgery alone. Additionally, multicenter clinical trials confirm substantially lower rates of reoperation and treatment failure, thereby preserving neurological function in elderly populations.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals must exercise independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References
Al Saiegh F et al. Adjunctive middle meningeal artery embolization is associated with lower 30-day readmission and mortality in chronic subdural hematoma: A propensity-matched national analysis. Clin Neurol Neurosurg. 2026 Sep. doi: 10.1016/j.clineuro.2026.109514. PMID: 42190492.
Knopman J, et al. Adjunctive Middle Meningeal Artery Embolization for Subdural Hematoma. N Engl J Med. 2024;391(20):1901-1911.
Davies JM, et al. Consensus Statement on Middle Meningeal Artery Embolization in Chronic Subdural Hematoma Treatment: A Guideline from the Society of Vascular and Interventional Neurology Guidelines and Practice Standards Committee. J Neurointerv Surg. 2025;17(3):210-218.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A nationwide propensity-matched analysis reveals that adjunctive middle meningeal artery embolization significantly lowers 30-day readmission and in-hospital mortality following surgical evacuation for chronic subdural hematoma, establishing a transformative paradigm in multidisciplinary neurovascular management.
4 weeks back
A laboratory technician's death in Siberia from an unverified respiratory pathogen has renewed global vigilance for pneumonic plague. Clinicians must recognize early presentations of Yersinia pestis, enforce immediate respiratory isolation, and start early bactericidal therapy to prevent severe secondary spread.
Today

Tripura has launched a comprehensive statewide oncology campaign to address late-stage breast cancer presentations. By strengthening community screening for women aged 30 and older and expanding District Day Care Cancer Centres, the initiative improves early clinical detection and decentralized chemotherapy access.
Today
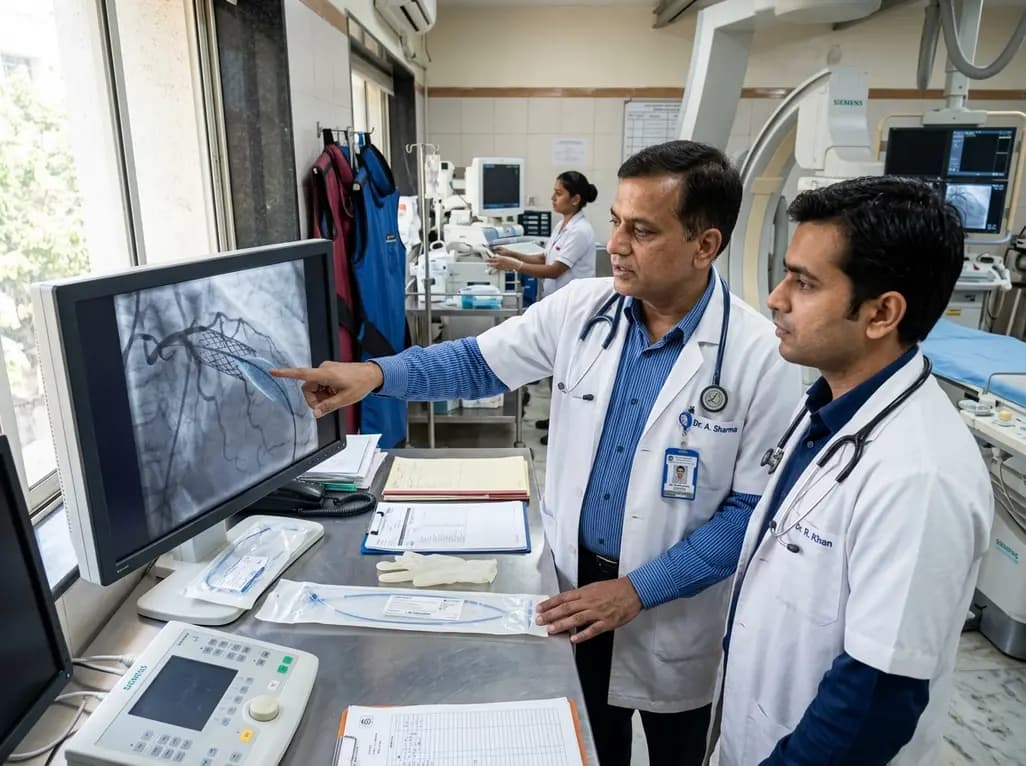
The US FDA has granted approval to the SELUTION SLR drug-eluting balloon for treating coronary in-stent restenosis. This milestone introduces a sustained-release sirolimus platform that eliminates the need for additional permanent metallic stents while maintaining robust vascular healing and luminal patency.
Today

The Thumbs-Out Classification (TOC) is a reliable screening tool for detecting thumb-in-palm deformity in children with cerebral palsy. Utilizing traffic-light tiers for radial abduction, TOC enables clinicians to monitor upper limb function and initiate timely therapeutic or surgical interventions.
Today

A comprehensive review analyzes periconceptional GLP-1 receptor agonist exposure, revealing reassuring data on congenital anomalies and adverse perinatal outcomes while emphasizing the need for cautious patient counseling.
Today
