

Loading, please wait...
Loading, please wait...

A prolonged mental health treatment delay represents one of the most critical public health hurdles facing modern Indian healthcare. Although psychiatric disorders affect millions across diverse demographics, individuals frequently suffer in silence for extended intervals before seeking professional help. A recent national report underscores that patients endure distressing emotional and psychological symptoms for many months before consulting clinical professionals. Consequently, healthcare practitioners must understand the drivers behind these delays. By recognizing the early red flags of psychiatric distress, physicians across outpatient clinics can bridge this care gap promptly.
Timely diagnosis forms the cornerstone of effective clinical psychiatric management. However, recent real-world data demonstrates that vast treatment gaps persist across the country. According to the Amaha Mental Health Report 2026, which surveyed 13,825 individuals between October 2025 and September 2026, more than half of the respondents waited at least a full year before seeking professional consultation. Furthermore, only 11.3 per cent of participants accessed clinical care within the first month of experiencing distressing symptoms.
This prolonged latency mirrors historical data from the National Mental Health Survey, which reported national treatment gaps exceeding seventy to eighty percent for common psychiatric ailments. When individuals delay treatment, their conditions invariably progress from mild psychological distress to entrenched neurobiological patterns. Therefore, physicians must appreciate that a twelve-month delay is not a benign pause. Instead, this delay represents an extended interval of unmitigated suffering, during which coping mechanisms degrade.
Additionally, social conditioning and limited psychiatric literacy prevent individuals from recognizing early symptomatology. Patients often normalize their chronic fatigue, irritability, and despair as ordinary life stress. Consequently, they defer seeking qualified medical guidance until personal and professional relationships suffer irreparable damage. General practitioners must identify these hidden cases earlier during routine visits.
The data from the comprehensive survey reveals valuable insights into the exact symptom profiles that prompt eventual consultation. Anxiety emerged as the most prevalent complaint, reported by 72.1 per cent of the surveyed cohort. Furthermore, stress troubled 67.5 per cent of individuals, while persistent low mood affected 58.3 per cent. Interpersonal difficulties and recurrent mood swings also burdened 55.6 per cent and 54.1 per cent of participants, respectively.
These findings highlight that common mental disorders represent the bulk of outpatient psychological suffering. However, patients rarely recognize isolated anxiety or low mood as treatable clinical entities in the early stages. Instead, they attempt diverse non-clinical coping strategies before presenting to medical providers. Specifically, 54.5 per cent of individuals initially turned to friends or family for emotional assistance, and 44.6 per cent attempted unguided self-help routines.
While informal social support provides vital comfort, it cannot substitute for structured evidence-based psychological or pharmacological interventions. In fact, by the time respondents consulted specialists, nearly a third had tried therapy, and 19.4 per cent required prescription psychiatric medications. Therefore, primary care clinicians must maintain high clinical suspicion when patients report non-specific somatic complaints, as underlying anxiety and mood dysregulation frequently drive these presentations.
When clinical care remains deferred for months, the cumulative burden takes a severe toll on everyday functionality. The report demonstrates that chronic psychological morbidity profoundly disrupts social, cognitive, and occupational performance. Remarkably, only 12.3 per cent of surveyed individuals stated that they could still manage all their routine daily tasks by the time they finally reached professional care.
Even more concerning, more than a quarter of respondents, specifically 27.3 per cent, could not manage most or any of their daily responsibilities. This functional collapse illustrates how untreated psychiatric morbidity leads to severe disability. Consequently, patients frequently face academic failure, career disruption, economic hardship, and profound marital strain. The World Health Organization consistently identifies depressive and anxiety disorders among the leading global contributors to years lived with disability.
Moreover, prolonged neurobiological stress exacerbates physical comorbidities, elevating systemic inflammatory markers and worsening cardiometabolic health. Therefore, clinicians must assess functional impairment alongside subjective complaints. When an adult presents with declining work productivity or unexplained absenteeism, physicians should systematically screen for psychiatric distress. Early intervention preserves global functional status, prevents secondary interpersonal crises, and reduces long-term disability rates across communities.
Several multifaceted barriers contribute directly to the widespread avoidance of psychiatric services in Indian society. First, pervasive social stigma continues to shroud mental illness, fostering irrational fear of social ostracization or familial embarrassment. Consequently, patients often conceal their emotional suffering until symptoms become completely overwhelming. Many individuals worry that acknowledging psychological vulnerability might derail their employment opportunities or marriage prospects.
Second, substantial structural deficits within the public healthcare infrastructure amplify treatment resistance. India experiences a critical shortage of qualified psychiatrists, clinical psychologists, and psychiatric social workers, particularly outside major urban centers. As a result, long travel distances and fragmented referral pathways discourage patients from pursuing timely evaluation. Furthermore, widespread financial constraints and out-of-pocket healthcare expenses create substantial economic hurdles for sustained psychotherapy or pharmacotherapy.
Additionally, pervasive misinformation regarding psychotropic medications drives apprehension. Many individuals harbor unfounded fears of chemical addiction, personality change, or severe side effects. Consequently, they prioritize informal advice or unscientific wellness remedies over clinical consultations. Therefore, healthcare providers must actively debunk these pervasive myths. By framing psychiatric conditions as treatable medical disorders, clinicians can dissolve hesitation and encourage timely help-seeking behaviors.
Primary care physicians occupy a strategic vanguard position to curtail treatment delay across vulnerable populations. Because patients with undiagnosed depressive or anxiety disorders regularly visit family clinics for somatic issues like dyspepsia, tension headaches, or chronic insomnia, practitioners must leverage these visits for timely screening. Incorporating brief validated tools, such as the Patient Health Questionnaire or the Generalized Anxiety Disorder scale, requires only minutes.
Furthermore, general practitioners should cultivate clear referral networks with qualified mental health professionals in their communities. When primary doctors normalize psychological distress during routine clinical consultations, patients feel validated rather than judged. Clinicians should explain that psychological conditions involve objective neurochemical and behavioral pathways that respond predictably to evidence-based interventions. Consequently, demystifying psychiatric pharmacotherapy and cognitive behavioral therapies builds immediate treatment adherence.
Moreover, doctors should actively engage family members during counseling discussions whenever appropriate. Because over half of struggling individuals consult loved ones first, educating families transforms them into supportive advocates rather than unintentional gatekeepers. Ultimately, proactive physician screening, destigmatized communication, and streamlined multidisciplinary collaboration will eliminate unnecessary delays, enabling patients to reclaim their health before functional impairment solidifies.
Q1: Why do patients frequently experience a mental health treatment delay exceeding one year?
Patients delay seeking professional care primarily due to social stigma, poor mental health literacy, and systemic infrastructure gaps. Many individuals normalize disabling distress as everyday stress or attempt unguided self-help routines first. Furthermore, fears regarding confidentiality, high treatment costs, and misconceptions about psychopharmacological dependency discourage individuals from consulting qualified clinicians until symptoms compromise their daily functional abilities.
Q2: What were the most common mental health complaints highlighted in the 2026 report?
According to the 2026 survey data, generalized anxiety emerged as the most frequent clinical complaint, affecting 72.1 per cent of participants. Chronic psychological stress followed closely at 67.5 per cent, while persistent low mood impacted 58.3 per cent. Additionally, more than half of the respondents reported significant interpersonal relationship difficulties and frequent emotional mood swings prior to their medical evaluation.
Q3: How can primary care doctors identify psychiatric conditions before severe functional decline occurs?
General practitioners can detect psychiatric disorders early by maintaining high clinical suspicion whenever patients present with recurrent, medically unexplained somatic symptoms like chronic fatigue, palpitations, or insomnia. Implementing rapid validated screening questionnaires during routine consultations enables objective evaluation. Furthermore, actively inquiring about occupational stress, interpersonal stability, and daily task management helps physicians initiate timely interventions or psychiatric referrals.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The Amaha Mental Health Report 2026 highlights a significant care gap across India, showing that more than 50% of seeking individuals wait over twelve months before consulting a specialist. Early identification of anxiety and mood disorders by general practitioners remains vital to prevent severe functional decline.
Today

A study shows that the aggregate index of systemic inflammation (AISI) significantly associates with elevated myocardial injury markers, including cardiac troponin T and CK-MB, in patients with coronary heart disease, highlighting its potential utility for cardiovascular risk stratification.
Today
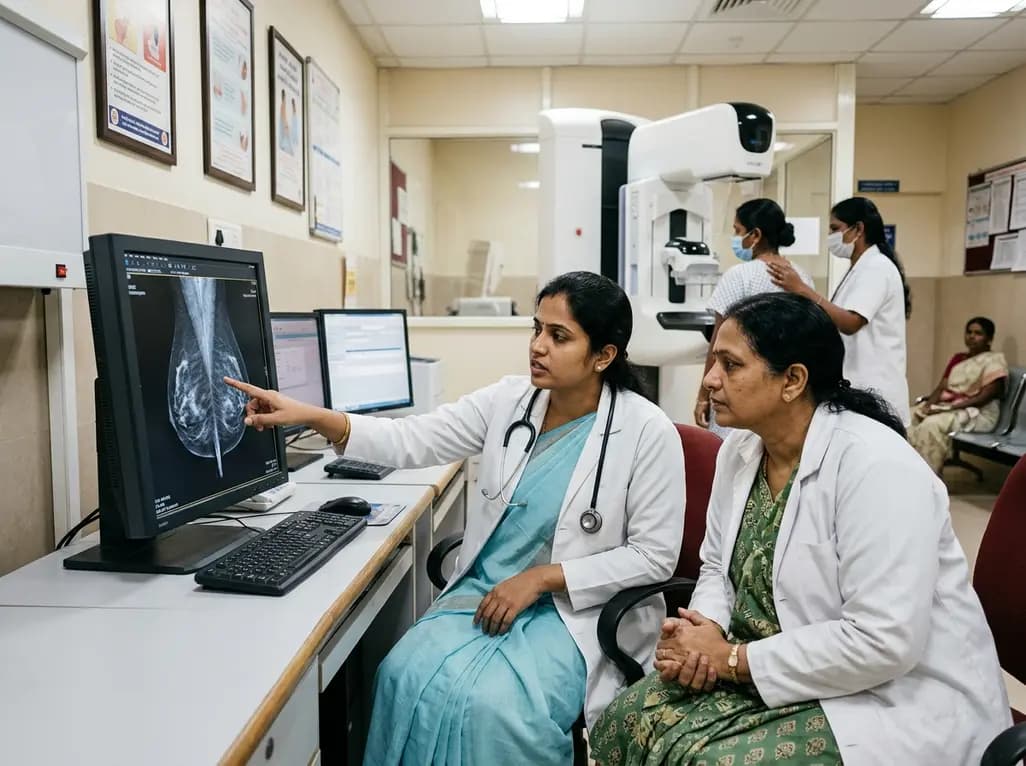
India faces an escalating breast cancer burden marked by late diagnosis and elevated mortality. Shifting from reliance on physical exams to an organized, AI-assisted mammography screening protocol can detect malignancies early, bridge urban-rural disparities, and improve patient survival outcomes across the nation.
Today

A retrospective study reveals that adults with congenital heart disease have significant deficits in peripheral muscle mass and handgrip strength compared to healthy peers. Greater lesion complexity exacerbates muscle loss, demonstrating the need for comprehensive nutritional and muscular assessments beyond standard BMI.
Today
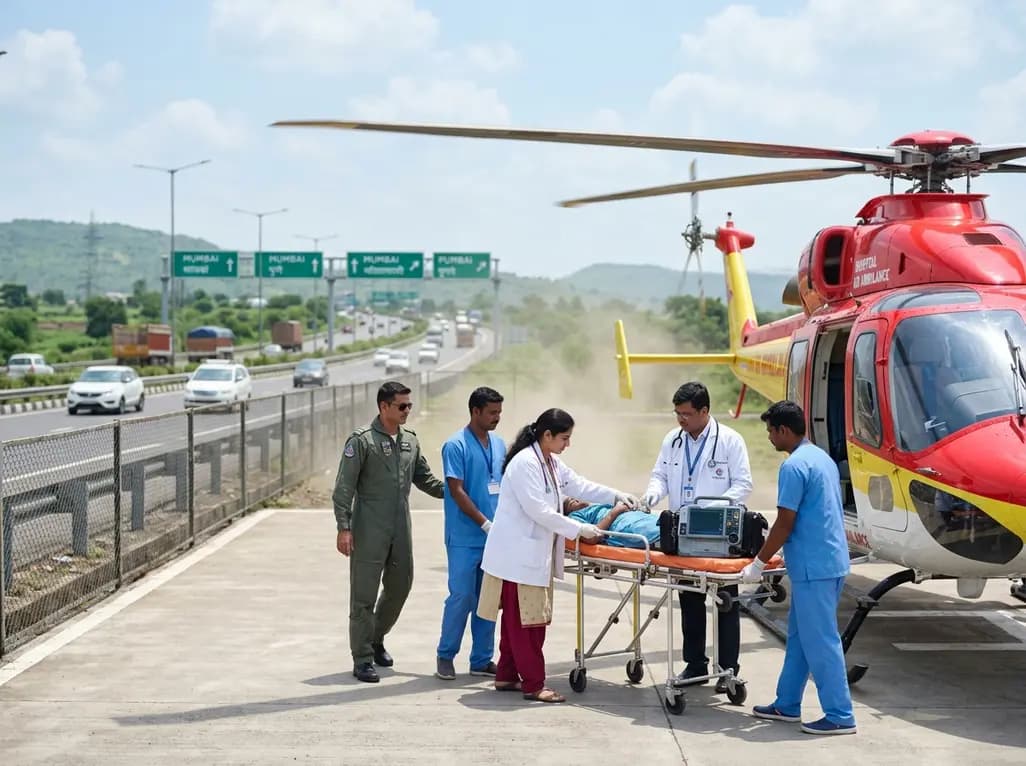
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today
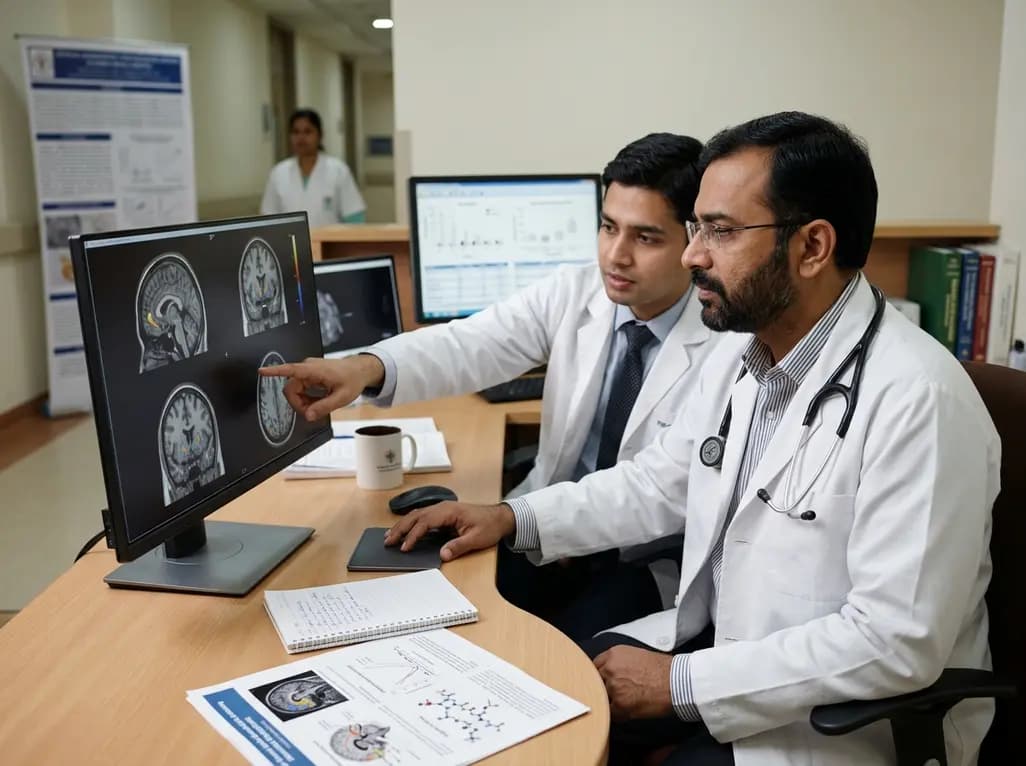
A systematic review of 66 preclinical studies reveals that GLP-1 mono-agonists modulate central reward processing. These findings demonstrate significant reductions in palatable food intake, substance self-administration, and compulsive behaviors, offering novel neurobiological targets for neuropsychiatry.
Today
