

Loading, please wait...
Loading, please wait...

Patients living with cystic fibrosis face numerous systemic challenges throughout their lifespan. Among these progressive complications, cystic fibrosis-related diabetes represents the most frequent non-pulmonary comorbidity, affecting nearly half of all adults. For decades, clinicians recognized that glucose intolerance accelerates pulmonary decline. However, the precise quantitative correlation between sustained hyperglycemia and mortality risk remained uncertain. Prior observational studies provided incomplete insights because small patient numbers limited long-term statistical precision. Recently, a comprehensive investigation utilizing the UK Cystic Fibrosis Registry offered definitive clarity on this relationship. The registry findings show that rising glycated hemoglobin drives a significant, dose-dependent rise in mortality. Consequently, proactive metabolic surveillance and targeted glucose control are crucial clinical imperatives.
Cystic fibrosis stems from mutations that alter epithelial CFTR channels, generating abnormally viscous mucus across various organs. In the pancreas, inspissated secretions obstruct small ductules and ignite persistent inflammation with progressive tissue autolysis. Over time, extensive fibrotic remodeling replaces healthy parenchyma and severely compromises islet architecture. Consequently, patients develop marked beta-cell depletion, leading to delayed and deficient early-phase insulin release. Unlike typical type 2 diabetes, absolute insulin deficiency represents the predominant metabolic lesion. Furthermore, fluctuating systemic inflammation during pulmonary exacerbations provokes acute insulin resistance. Therefore, patients experience intense protein catabolism, rapid muscle wasting, and worsening weight loss. Hyperglycemia simultaneously weakens airway innate defenses, stimulating bacterial proliferation and chronic respiratory inflammation. Thus, unchecked dysglycemia accelerates pulmonary decline and dramatically elevates patient vulnerability.
The national cohort study evaluated 4,477 individuals with diagnosed diabetes from the UK Cystic Fibrosis Registry across 31,311 person-years. Throughout this extended surveillance window, 758 individuals died. Investigators calculated updated interval mean hemoglobin A1c values to track glycemic patterns over time accurately. Subsequently, researchers used multivariable Poisson regression to compute mortality rate ratios. Importantly, the analysis controlled for age, sex, calendar year, body mass index, lung function, and CFTR modulator use. The results established a strong, stepwise association between elevated glycemia and increased mortality rates. Compared with HbA1c values at or below 42 mmol/mol, values between 42 and 53 mmol/mol yielded a 41 percent higher mortality rate ratio. Furthermore, intermediate values between 53 and 69 mmol/mol increased the risk ratio by 66 percent. Finally, HbA1c levels exceeding 69 mmol/mol produced a striking 93 percent elevation in mortality.
Metabolic stability and respiratory endurance exhibit an intimate, reciprocal relationship in this patient population. Insulin serves as a crucial anabolic mediator that protects respiratory skeletal muscle against proteolysis. When insulin secretion collapses, systemic cachexia accelerates and diaphragmatic mass rapidly diminishes. Consequently, patients suffer measurable declines in pulmonary function tests alongside progressive weight loss. In addition, persistent hyperglycemia increases airway surface liquid glucose concentrations. This elevated glucose microenvironment creates fertile soil for opportunistic bacterial pathogens like Pseudomonas aeruginosa. As a result, respiratory exacerbations recur more frequently, requiring aggressive antibiotic regimens and hospitalizations. Conversely, these acute pulmonary infections generate high concentrations of pro-inflammatory cytokines that exacerbate peripheral insulin resistance. Therefore, a vicious feedback cycle takes hold, driving rapid tissue destruction. Ultimately, this metabolic and pulmonary spiral leads toward irreversible respiratory failure, which remains the leading cause of mortality.
The pronounced mortality risk associated with minor glycemic elevations demands stringent screening and proactive management protocols. Clinical practice guidelines advocate for annual oral glucose tolerance testing starting at age ten. While glycated hemoglobin serves as an established monitoring parameter, it lacks sufficient diagnostic sensitivity when used alone. Specifically, accelerated red blood cell turnover and repeated pulmonary bleeding can artificially depress HbA1c values. Nonetheless, as demonstrated by the UK registry findings, serial HbA1c measurements reliably track longitudinal mortality risk once diabetes develops. Regarding therapeutic management, subcutaneous insulin replacement remains the undisputed cornerstone. Basal-bolus insulin regimens reverse nutritional wasting, restore positive nitrogen balance, and control postprandial glucose surges effectively. Conversely, clinicians generally avoid oral antidiabetic agents because they lack proven anabolic potency and often cause gastrointestinal intolerance. Additionally, medical teams must preserve high-calorie dietary plans with adequate enzyme therapy rather than restricting caloric intake.
Multidisciplinary cystic fibrosis teams must integrate these prognostic insights into standard ambulatory care pathways. Clinicians should establish proactive individualized glycemic targets, aiming for optimal metabolic control whenever achievable. Because even moderate HbA1c elevations above 42 mmol/mol confer a substantial mortality disadvantage, clinicians must address mild dysglycemia promptly. Furthermore, the advent of highly effective CFTR modulators has dramatically transformed pulmonary outcomes across the globe. Although modulators often reduce systemic inflammation and improve beta-cell function, they rarely reverse established diabetes. Consequently, routine glycemic surveillance must continue unabated in patients receiving modulator therapy. Moreover, continuous glucose monitoring technology provides valuable granular insights into occult glycemic excursions. These wearable sensors uncover asymptomatic postprandial spikes and nocturnal hypoglycemia, facilitating precise insulin adjustments. Ultimately, bridging endocrinology and pulmonology care protects vital organ reserves, diminishes systemic morbidity, and enhances long-term survival in this high-risk population.
Cystic fibrosis-related diabetes represents a distinct metabolic entity characterized primarily by severe insulin deficiency. Viscous secretions obstruct pancreatic ducts, which causes progressive fibrotic destruction of islet architecture. While peripheral insulin resistance frequently emerges during acute pulmonary exacerbations or systemic corticosteroid therapy, the foundational defect remains impaired beta-cell mass and delayed insulin secretion. Unlike classic autoimmune type 1 diabetes, islet autoantibodies are absent, and unlike type 2 diabetes, absolute insulin scarcity predominates without obligatory antecedent obesity.
International clinical guidelines recommend an annual two-hour oral glucose tolerance test starting at age ten for all patients. Interestingly, standard glycated hemoglobin often underestimates chronic hyperglycemia in cystic fibrosis due to increased red blood cell turnover, frequent chronic infections, and recurring micro-hemorrhages. Consequently, normal HbA1c levels cannot reliably exclude early dysglycemia. In contrast, the postprandial glucose challenge detects early post-challenge spikes and impaired glucose tolerance before persistent baseline hyperglycemia develops, allowing clinicians to intervene promptly.
Exogenous insulin remains the undisputed standard of care for managing dysglycemia in this patient group. Specifically, basal-bolus subcutaneous insulin regimens restore postprandial glycemic balance, curb protein catabolism, and facilitate nutritional weight gain. Conversely, clinical trials show inconsistent efficacy and potential gastrointestinal adverse effects with traditional oral hypoglycemic agents. Furthermore, newly approved cystic fibrosis transmembrane conductance regulator modulators show promising indirect benefits on endogenous insulin secretion, but clinicians still prioritize individualized insulin replacement for definitive glycemic control.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should use their clinical judgment when applying this information. Readers are advised to confirm the details with other medical literature and consult relevant specialists where necessary. The views expressed in this article are solely those of the author(s) and do not reflect the opinions of any affiliated organization. The author(s) and publisher assume no responsibility for any adverse effects resulting from the use of the information presented. Refer to the latest local and national guidelines for clinical practice.
References
Adler AI et al. Long-term Glycemia and Risk of Death in Cystic Fibrosis-Related Diabetes: A UK Cystic Fibrosis Registry Study. Diabetes Care. 2026 Oct 26. doi: undefined. PMID: 42930457.
Moran A, Brunzell C, Cohen RC, et al. Clinical care guidelines for cystic fibrosis-related diabetes. Diabetes Care. 2010;33(12):2697-2708.
Granados A, Chan CL, Moheet A, Moran A, Ode KL. Management of Cystic Fibrosis-Related Diabetes. Curr Diab Rep. 2019;19(11):115.
ElSayed NA, Aleppo G, Aroda VR, et al. Comprehensive Medical Evaluation and Assessment of Comorbidities: Standards of Care in Diabetes—2023. Diabetes Care. 2023;46(Suppl 1):S19-S40.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A nationwide UK Cystic Fibrosis Registry study demonstrates that higher updated mean HbA1c levels correlate with a graded, significant increase in all-cause mortality among individuals with cystic fibrosis-related diabetes, reinforcing the critical need for proactive glycemic monitoring and intervention.
Today

A KGMU study reveals over half of women with breast abnormalities fail to undergo diagnostic confirmation, leading to advanced-stage detection. Discover the socio-cultural barriers, clinical risks of incomplete resection, and community-level solutions needed to bridge the critical screening-to-diagnosis gap in India.
Today

A comparative non-contact study reveals that high-power radiofrequency delivery with the QDOT MICRO catheter induces an artifactual contact force rise. Electrophysiologists must understand this power-dependent thermal and electrical phenomenon to avoid inadvertent catheter withdrawal and ineffective ablation.
Today
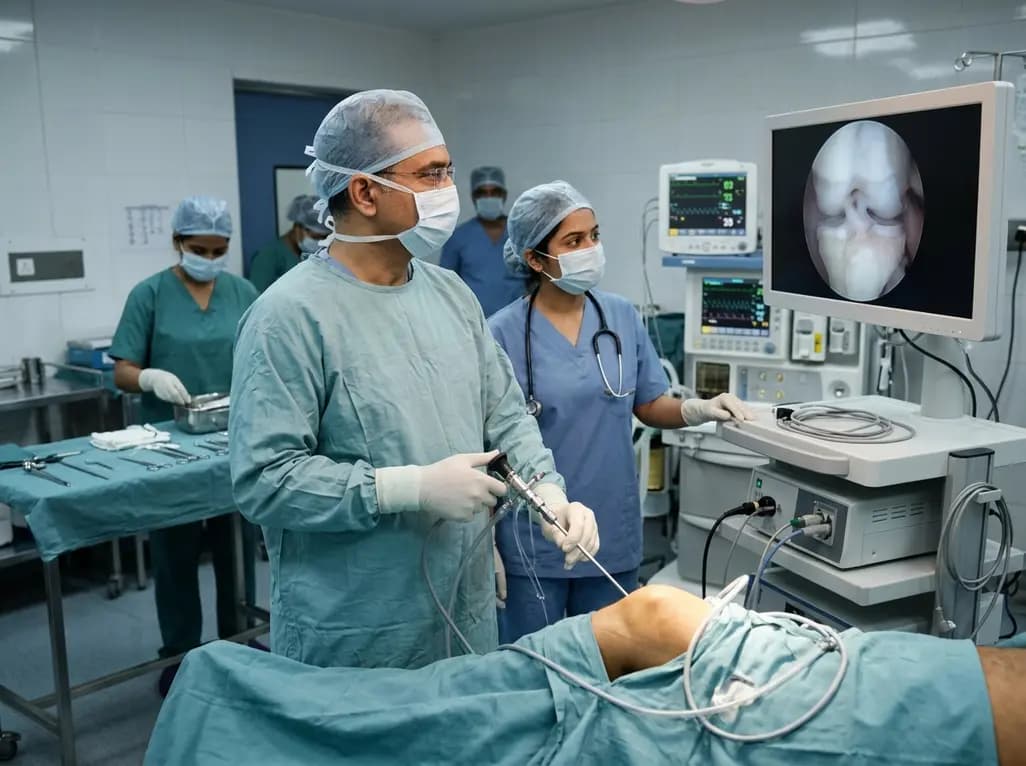
Healthium Medtech has transitioned its arthroscopy vertical into SIRONIX Orthopedics, aiming to capture key segments of the global joint care market. The strategic shift introduces dedicated portfolios in sports medicine, joint regeneration, surgical reconstruction, and digital operating technologies.
Today

Preclinical research demonstrates that BMI1 overexpression alleviates metabolic syndrome-related liver injury. By triggering ubiquitin-mediated METTL3 degradation, BMI1 prevents AHNAK m6A methylation and suppresses fibrogenic TGF-β/SMAD signaling, significantly improving hepatic steatosis and insulin resistance.
Today
