

Loading, please wait...
Loading, please wait...

Environmental carcinogens represent a significant global health burden, especially when natural subterranean processes drive residential toxic exposures. Recent geological investigations demonstrate that indoor radon lung cancer associations require careful epidemiological evaluation across distinct geographical territories. Radon, an inert radioactive gas produced by uranium decay, diffuses through bedrock and accumulates silently inside residential structures. Although public health programs routinely emphasize tobacco smoking cessation, environmental radiation exposure poses a pervasive secondary threat. Clinicians must recognize how local bedrock geology influences chronic respiratory risk profiles.
Underlying lithology strongly dictates subterranean gas emission into domestic environments. Granitic bedrock and fractured metamorphic formations naturally possess elevated concentrations of uranium and radium isotopes. As these parent radionuclides decay, they generate gaseous radon-222, which migrates upward through soil porosity and rock fissures. Consequently, buildings constructed over permeable granitic substrata experience substantial radon influx. Thermal stack effects and indoor negative pressure draw radioactive gas through foundation cracks, slab joints, and plumbing penetrations.
Furthermore, building characteristics and ventilation dynamics modulate final indoor concentrations. Modern energy-efficient constructions frequently incorporate airtight insulation, which inadvertently traps radioactive isotopes inside living spaces. Therefore, indoor concentrations often exceed outdoor baseline measurements by several orders of magnitude. The World Health Organization recommends maintaining domestic radon levels below 100 Becquerels per cubic meter. However, many national frameworks establish higher action levels, such as 300 Becquerels per cubic meter. In regions with heterogeneous bedrock, adjacent communities can display divergent exposure profiles due to localized geological faults.
A recent ecological assessment in Northern Portugal evaluated the link between geology-derived radon concentration potential and crude lung cancer rates across Alto Minho municipalities. The researchers classified administrative areas using Portugal's national reference threshold of 300 Becquerels per cubic meter. Notably, statistical analysis demonstrated a significant difference in crude lung cancer rates between high and low potential zones (p = 0.044). Municipalities with elevated geological potential exhibited higher crude disease prevalence, underscoring the relevance of geological mapping in public health.
Nevertheless, the study investigators explicitly noted that ecological correlations cannot establish direct causation. Because the investigation analyzed municipal-level aggregates rather than individual patient histories, unmeasured confounding variables could influence findings. In particular, regional variations in tobacco smoking prevalence and differing elderly demographic proportions alter crude cancer statistics. Older populations naturally experience higher baseline oncological rates, which amplify crude municipal figures. Consequently, the authors described their findings as a suggestive correlation rather than definitive proof of localized radon causation. These observations highlight the critical need for continuous indoor monitoring paired with case-control studies.
Understanding cellular pathophysiology clarifies why radon represents a formidable pulmonary hazard. When individuals inhale ambient radon gas, short-lived alpha-emitting decay progeny deposit directly along the tracheobronchial epithelium. Polonium-218 and polonium-214 release dense alpha particles that possess high linear energy transfer. Consequently, these energetic particles penetrate delicate epithelial membranes and deposit localized radiation within cellular nuclei.
Moreover, alpha particle irradiation produces complex, clustered DNA lesions that overwhelm intrinsic enzymatic repair pathways. Double-strand breaks frequently result in chromosomal translocations, point mutations, and large deletions. Specifically, studies identify recurrent aberrations in tumor suppressor genes such as TP53, alongside oncogenic alterations in KRAS and EGFR pathways. In addition, radiation generates reactive oxygen species, which sustain chronic tissue inflammation and oxidative stress. Therefore, chronically exposed bronchial cells undergo progressive genomic instability and phenotypic transformation. This malignant progression predominantly yields pulmonary adenocarcinoma and small-cell carcinoma, confirming that alpha radiation constitutes a potent physical carcinogen.
Ecological investigations offer valuable geographic insights, but researchers face significant methodological hurdles when interpreting environmental cancer registries. Chief among these challenges is the ecological fallacy, which occurs when population-level associations fail to reflect individual-level biological risks. For instance, tobacco smoking remains the predominant etiology for pulmonary malignancy worldwide. Even modest municipal variations in smoking habits can confound subtle environmental radiation effects.
Furthermore, tobacco smoke and radon exposure exhibit a pronounced supra-additive synergistic interaction. Carcinogens within cigarette smoke impair bronchial ciliary clearance, which allows radioactive decay progeny to remain lodged against airway mucosa. As a result, smokers exposed to elevated indoor radon experience a manifold higher lifetime lung cancer risk compared to non-smokers. Demographic shifts also introduce substantial confounding into crude prevalence metrics. Because cancer incidence rises steeply with advancing age, municipalities with older age distributions inevitably register elevated crude rates. In addition, residential mobility obscures long-term exposure histories, because lung cancer latency spans decades. Therefore, robust epidemiological models must employ multivariable regression, lifetime residence dosimetry, and individualized smoking histories.
Although the Alto Minho study assessed European terrain, its core findings carry profound relevance for pulmonary and oncology specialists in India. Certain geological regions in India, including parts of the peninsular shield and granitic belts in southern and northern states, exhibit naturally elevated background radiation. Moreover, Indian clinicians frequently encounter non-smoking patients diagnosed with advanced pulmonary adenocarcinoma. While biomass smoke and ambient particulate air pollution represent established risks, unmonitored indoor radon constitutes an overlooked environmental contributor.
Consequently, clinicians should adopt a comprehensive environmental history during routine respiratory examinations. Asking patients about residential construction types, basement occupancy, ground-floor living, and local granite geology provides valuable context. Furthermore, respiratory physicians should encourage radon testing in buildings situated over suspected geological formations. From a preventive medicine perspective, sealing foundation fissures and enhancing domestic ventilation dramatically reduce indoor alpha radiation exposure. Integrating structural mitigation with aggressive anti-tobacco counseling maximizes preventive impact. Therefore, Indian medical professionals must advocate for targeted screening policies to detect lung cancer at early, curable stages.
Radon decay emits dense alpha particles directly into bronchial tissues when inhaled over prolonged periods. Consequently, these energetic particles cause severe double-strand deoxyribonucleic acid breaks in pulmonary epithelial cells. Because biological repair mechanisms often misrepair radiation-induced genomic damage, progressive oncogenic mutations gradually accumulate. Therefore, sustained exposure substantially accelerates malignant transformation across respiratory tissues, which drives tumor progression even in individuals without occupational exposure.
Non-smokers remain vulnerable because naturally occurring radon gas seeps invisibly into poorly ventilated living spaces. In addition, people spend significant time resting indoors, which creates persistent, unmonitored baseline exposure to alpha radiation. While tobacco smoke acts synergistically with ionizing radiation, alpha emitters alone provide sufficient kinetic energy to initiate carcinogenesis. Thus, non-smoking patients living within radon-prone geological terrain can develop pulmonary adenocarcinoma despite lacking conventional behavioral risk factors.
Property owners can lower domestic radon concentrations through active sub-slab depressurization and dedicated mechanical ventilation. Furthermore, sealing structural foundation cracks, crawlspace gaps, and basement utility joints prevents subterranean radioactive gas infiltration. Installing continuous indoor air exchange systems also dilutes ambient radiological isotopes effectively. Consequently, routine diagnostic testing using certified alpha-track detectors enables timely structural interventions, which substantially reduces lifetime cumulative radiation exposure for all household occupants.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. Consult qualified healthcare professionals for diagnosis and treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent ecological assessment in Northern Portugal investigates the link between geology-driven indoor radon levels and crude lung cancer rates. The findings highlight the necessity of regional radiological surveillance, age-adjusted epidemiological models, and proactive respiratory health assessments.
Today
Hospitalization for severe viral lower respiratory tract disease causes lasting physical, psychological, and productivity burdens for patients and their caregivers. Real-world multinational data reveal major gaps in discharge planning, emphasizing the urgent need for structured transitional pulmonary care.
Today
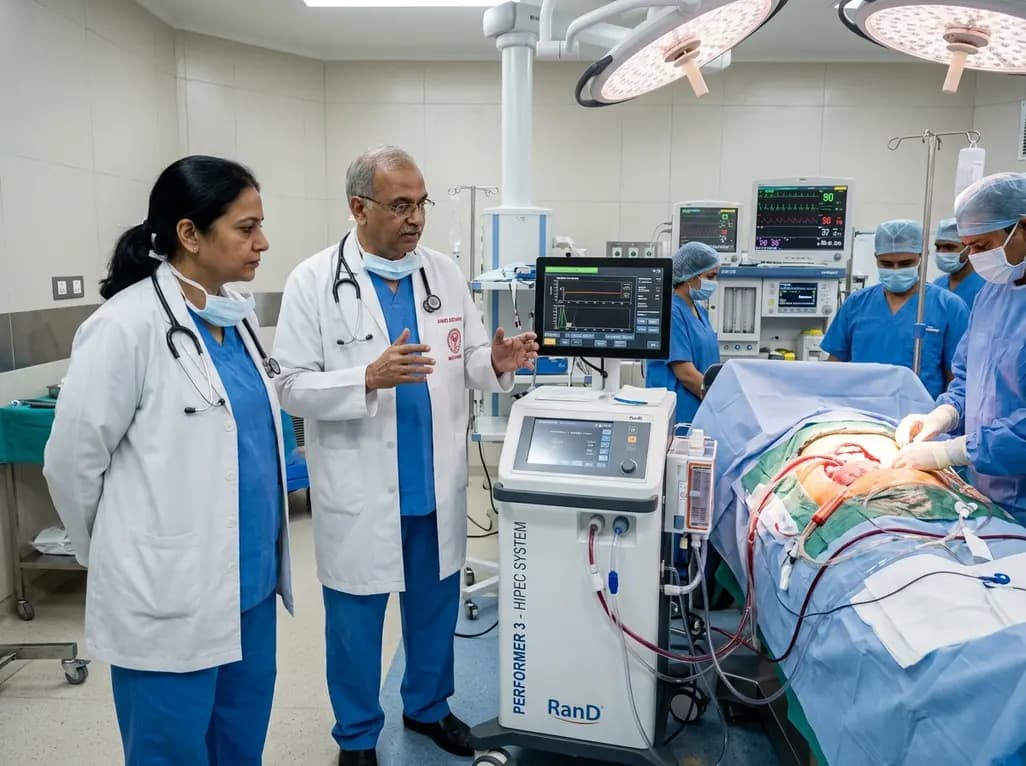
AIIMS Bathinda has inaugurated a specialized peritoneal oncology service featuring the RanD Performer 3 HIPEC platform. The facility offers cytoreductive surgery alongside hyperthermic intraperitoneal chemotherapy, transforming regional management for advanced ovarian, colorectal, and appendiceal malignancies.
Today
Cinematic rendering utilizes advanced global illumination to transform coronary CT angiography datasets. This imaging technique provides lifelike depth perception, helping cardiologists and surgeons precisely evaluate anomalous coronary artery origins, high-risk interarterial courses, and post-surgical anatomy.
Today

This clinical overview examines recent advancements in lumbar disc herniation surgery, comparing microscopic and full-endoscopic discectomy while highlighting biportal techniques and emerging motion-preserving innovations for spine specialists.
Today

A breakthrough study reveals that loss of SELENOT in hypothalamic POMC neurons triggers premature cellular senescence, ATF6α stress activation, and ER calcium depletion, linking neuroendocrine decay to metabolic disease.
Today
