

Loading, please wait...
Loading, please wait...

Managing high-grade glioma recurrence remains one of the most formidable challenges in neuro-oncology. Historically, clinicians recognized mutations in the isocitrate dehydrogenase (IDH) genes as key prognostic indicators that confer significant survival advantages. According to the World Health Organization (WHO) CNS5 criteria, IDH-mutant high-grade astrocytomas represent biologically distinct entities compared to IDH wild-type glioblastomas. In newly diagnosed patients, IDH-mutant tumors predictably demonstrate delayed progression and more durable responses to initial chemoradiotherapy. However, disease recurrence eventually confronts nearly every patient regardless of mutation status. Consequently, researchers must determine whether the biological advantages associated with IDH alterations endure throughout later disease phases or diminish after initial recurrence.
Recent multi-institutional evidence clarifies this critical question by analyzing adult cohorts with pathologically confirmed tumors. Investigators found that IDH mutations delay the initial failure of therapy, granting patients several additional months of progression-free survival. Therefore, molecular testing remains indispensable during the baseline diagnostic workup to establish baseline prognosis. Nevertheless, the natural history of glioma evolves dynamically under treatment pressure. Therapeutic interventions, including alkylating chemotherapy and radiotherapy, induce selective genomic changes in residual tumor clones. Consequently, clinicians require deeper insight into subsequent recurrence intervals to design realistic salvage regimens and counseling strategies.
The primary finding of recent multi-institutional research centers on the discrepancy between first and second recurrence timelines. In a retrospective cohort of 121 high-grade glioma patients, patients harboring IDH mutations achieved a mean time to first recurrence of 17.5 months. In contrast, patients with IDH wild-type glioblastoma experienced disease progression after an average of only 9.8 months. This statistically significant divergence reinforces the protective role of IDH mutations during primary treatment. Because IDH mutations fundamentally reprogram cellular metabolism and impair DNA repair pathways, tumor cells initially exhibit heightened susceptibility to cytotoxic chemoradiation.
However, this survival advantage unexpectedly disappears once the disease returns. When researchers evaluated the interval between the first and second recurrences, the difference between the cohorts lost statistical significance. Specifically, IDH-mutant patients demonstrated a mean time to second recurrence of 10.8 months, whereas IDH wild-type patients recurred in 8.1 months. Thus, following the first progression, the biological velocity of IDH-mutant astrocytomas accelerates to mimic the aggressive behavior of IDH wild-type tumors. This finding profoundly alters how oncologists view tumor evolution. Although patients benefit substantially during the initial phase of their illness, secondary recurrences arrive swiftly across all genetic subtypes.
Accurately identifying glioma progression requires strict imaging benchmarks to distinguish true recurrence from treatment-induced pseudoprogression. In this analysis, investigators strictly employed the Response Assessment in Neuro-Oncology (RANO) 2.0 criteria to define recurrence intervals. RANO 2.0 provides crucial updates for both neuro-radiologists and neuro-oncologists managing high-grade neoplasms. For instance, the guidelines refine how clinicians evaluate contrast-enhancing lesions and non-enhancing infiltrative disease. Additionally, RANO 2.0 addresses post-radiotherapy inflammation by establishing clear standards for repeat neuroimaging within the vulnerable post-treatment window.
By utilizing standardized criteria, clinicians eliminate observer bias and avoid misinterpreting transient treatment effects as premature therapeutic failure. Furthermore, the updated criteria emphasize that non-enhancing tumor progression holds different diagnostic weight across glioma subtypes. In IDH-mutant astrocytomas, infiltrative non-enhancing disease frequently signals evolving malignant transformation. Conversely, IDH wild-type glioblastomas often manifest rapid, bulky contrast enhancement and central necrosis. Therefore, implementing RANO 2.0 ensures reproducible clinical trial end points and informs everyday practice. Neuro-oncology teams must align routine follow-up protocols with these criteria to capture progression accurately. Consequently, multidisciplinary tumor boards should integrate advanced neuroimaging reviews regularly during surveillance.
Beyond molecular signatures, the multi-institutional study identified noteworthy demographic disparities in tumor progression. Multivariate Cox regression revealed that Black race independently predicted a significantly shorter time to first recurrence alongside IDH wild-type status. This observation underscores the complex intersection between underlying biology and systemic healthcare determinants. Although researchers adjust for extent of resection and molecular classification, racial disparities in oncology frequently reflect differences in healthcare access, treatment delays, and supportive resources. Consequently, clinical teams cannot evaluate tumor biology in complete isolation from socio-demographic factors.
Furthermore, population-based disparities highlight the urgent need for equitable neuro-oncology care pathways globally. In many healthcare systems, including tertiary centers managing diverse socioeconomic strata, delays in initiating standard concurrent temozolomide and radiotherapy degrade long-term disease control. Moreover, variations in supportive medications, nutritional status, and clinical trial enrollment may exacerbate differences in progression intervals. Therefore, clinicians must actively screen for barriers to treatment adherence and healthcare access. Addressing these systemic obstacles ensures that all high-grade glioma patients receive prompt, standardized multidisciplinary management regardless of background. Moreover, proactive patient support systems help mitigate disparities in progression timelines across diverse clinical settings.
Why does the protective effect of IDH mutations evaporate after the first disease recurrence? Scientific data suggest that recurrent IDH-mutant tumors undergo significant genomic and clonal evolution. Primary IDH-mutant gliomas typically possess homogenous driver events that confer chemoradiation sensitivity. However, exposure to alkylating agents like temozolomide frequently selects for aggressive, treatment-resistant sub-clones. In many instances, tumors acquire hypermutation phenotypes through mutations in mismatch repair genes such as MSH6. Consequently, when the glioma recurs, the relapsed mass consists of highly refractory cellular populations that no longer behave like treatment-naive tissue.
Additionally, late-stage tumors frequently acquire tertiary genetic alterations, including CDKN2A/B homozygous deletions or secondary alterations in the MET and PDGFRA pathways. These molecular events drive profound genomic instability, microvascular proliferation, and widespread necrosis. As a result, the secondary growth trajectory of IDH-mutant astrocytoma closely mirrors the aggressive kinetics of IDH wild-type glioblastoma. Thus, clinicians should not assume that recurrent IDH-mutant disease will respond favorably to rechallenge with prior regimens. Recognizing this evolutionary convergence allows teams to pivot toward targeted clinical trials, re-resection when feasible, and individualized molecular re-profiling. Ultimately, understanding these evolutionary shifts empowers clinicians to set realistic expectations for patients facing second-line therapy.
IDH mutations significantly prolong the time to first recurrence, extending the disease-free interval to a mean of 17.5 months compared to 9.8 months in wild-type tumors. However, this protective benefit attenuates at second recurrence, where progression intervals between mutant and wild-type cohorts show no statistically significant survival difference.
The updated RANO 2.0 criteria establish standardized imaging benchmarks that accurately differentiate true tumor progression from radiation-induced pseudoprogression. By standardizing measurements of contrast-enhancing lesions and non-enhancing infiltrative components, RANO 2.0 ensures objective evaluation across clinical trials and routine neuro-oncology practice, avoiding premature cessation of effective maintenance therapy.
Because recurrent IDH-mutant gliomas frequently acquire resistant clonal mutations and behave more aggressively, clinicians should not rely solely on standard initial rechallenge protocols. Recommended strategies include surgical re-resection when anatomically feasible, repeat molecular profiling, consideration of novel targeted agents or clinical trials, and personalized salvage chemoradiation regimens.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Lally AR et al. Do the benefits of IDH mutations in high-grade glioma persist beyond the first recurrence? A multi-institutional retrospective analysis. J Neurooncol. 2025 Aug. doi: 10.1007/s11060-025-05049-2. PMID: 40261557.
Wen PY et al. RANO 2.0: Update to the Response Assessment in Neuro-Oncology Criteria for High- and Low-Grade Gliomas in Adults. J Clin Oncol. 2023 Nov;41(33):5187-5199.
Louis DN et al. The 2021 WHO Classification of Tumors of the Central Nervous System: a summary. Neuro Oncol. 2021 Aug;23(8):1231-1251.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A multi-institutional study shows that IDH mutations significantly delay initial progression in high-grade glioma, but this survival benefit diminishes by the second recurrence, underscoring clonal resistance and demographic disparities.
Today
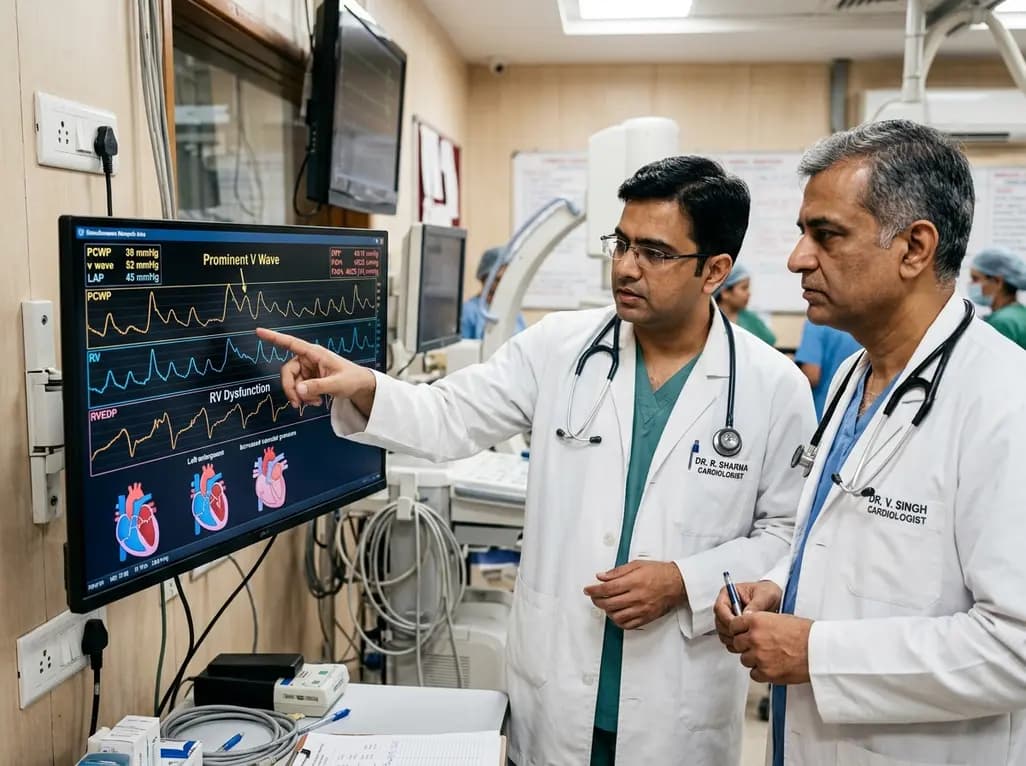
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
