

Loading, please wait...
Loading, please wait...

The therapeutic management of acute myeloid leukemia continues to evolve with targeted immunotherapies. Clinical utilization of gemtuzumab ozogamicin in AML represents a major advancement in antibody-drug conjugate development for hematologic oncology. Gemtuzumab ozogamicin delivers a potent calicheamicin cytotoxic payload directly into leukemic cells expressing CD33 surface glycoprotein. While randomized prospective trials demonstrated substantial survival benefits, real-world registry evaluations remain essential to confirm clinical safety, remission depth, and longevity outside restrictive clinical trial settings. A newly published multicenter study from France provides crucial real-world insights into patient responses, tolerability, and post-remission pathways.
Investigators conducted a multicenter observational study evaluating 113 adult patients with de novo acute myeloid leukemia. These individuals received therapy under the French authorization for temporary use and post-authorization cohorts between 2014 and 2022. Because real-world patients often present with complex medical histories, their median age at treatment initiation was 63 years. Furthermore, nearly 55% of the study cohort were male, and more than 80% maintained a baseline ECOG performance status of 0 or 1. Additionally, genetic risk assessment using European LeukemiaNet criteria classified 65.3% of evaluable patients into favorable-risk cytogenetic subgroups. In standard clinical practice, clinicians administered fractionated doses to balance targeted cytotoxic potency against treatment-related myelosuppression. During the initial induction phase, 98.1% of patients received the immunoconjugate alongside companion chemotherapeutic drugs. Specifically, 60% of these patients received standard induction combining daunorubicin and cytarabine. Consequently, this large cohort accurately reflects modern induction strategies across regional leukemia networks. The study establishes critical real-world benchmarks for clinical response rates, minimal residual disease negativity, and sustained survival outcomes in frontline hematology practice.
Frontline induction therapy produced striking antileukemic activity across this observational cohort. Overall, 78.6% of evaluable patients responded positively to their initial therapeutic regimen. Complete response occurred in 72.3% of individuals, confirming the robust antileukemic potency of CD33 targeting in clinical practice. In addition to morphologic blast clearance, clinicians examined the depth of molecular response through flow cytometry and molecular assays. Importantly, among patients assessed for measurable residual disease, 52.2% achieved measurable residual disease negativity. Achieving residual disease negativity represents a pivotal milestone in contemporary leukemia management because persistent clones directly accelerate disease recurrence. Furthermore, patients who attained early negative residual disease status experienced fewer disease relapses during subsequent maintenance and consolidation phases. These findings demonstrate that antibody-drug conjugate combination therapy successfully clears resistant leukemic clones without requiring intolerable dose escalation. Therefore, frontline CD33 targeting produces deep cytoreduction that rivals prospective clinical trial data. Consequently, hematologists can confidently incorporate this agent into standard induction pathways to maximize complete remission rates and optimize deep disease control.
Long-term survival metrics provide essential prognostic perspectives for practicing clinical hematologists. Over a median follow-up period of 44.6 months, the median event-free survival reached 13.1 months. Moreover, the median relapse-free survival extended to 17.5 months among responding patients. Most impressively, the median overall survival reached 49.8 months across the entire cohort. However, multivariate survival analysis identified significant differences based on demographic and disease characteristics. Specifically, older age predicted shorter overall survival, underscoring the vulnerability of elderly individuals to physiological toxicities and treatment complications. In addition, cytogenetic risk stratifications heavily influenced long-term leukemia recurrence rates. Patients with favorable-risk cytogenetics derived substantial survival advantages compared to those with adverse disease features. Although cumulative mortality reached 46.9% over extended follow-up, disease progression accounted for most deaths rather than direct drug toxicities. Consequently, careful risk stratification remains essential when selecting candidates for intensive combination regimens. Thus, while elderly patients require attentive monitoring, gemtuzumab ozogamicin delivers remarkable durable survival benefits for appropriately selected individuals.
Evaluating toxicity remains paramount when administering antibody-drug conjugates to patients with acute leukemia. Historically, gemtuzumab ozogamicin raised clinical concerns regarding hepatic sinusoidal obstruction syndrome, formerly known as veno-occlusive disease. Fortunately, modern fractionated dosing schedules have substantially mitigated these severe hepatic complications. In this French observational registry, clinicians monitored liver function tests and coagulation parameters vigilantly throughout all treatment cycles. As expected, prolonged myelosuppression represented the most frequent adverse event requiring supportive care interventions. Consequently, patients required regular transfusion support alongside proactive antimicrobial prophylaxis during severe neutropenic nadirs. Moreover, clinicians exercised exceptional caution when coordinating subsequent allogeneic hematopoietic cell transplantation. Because prior calicheamicin exposure can theoretically injure sinusoidal endothelial cells, transplant teams optimized conditioning regimens and maintained adequate intervals before stem cell infusion. As a result, serious transplant-related hepatic toxicities remained infrequent in this real-world cohort. Thus, fractionated dosing combined with structured supportive management ensures manageable toxicity profiles during frontline antileukemic treatment.
Translating registry evidence into practical bedside oncologic care requires systematic multidisciplinary collaboration. When clinicians initiate therapy for acute myeloid leukemia, prompt cytogenetic and molecular diagnostics must guide treatment decisions. In particular, identifying CD33 expression and cytogenetic risk categories ensures that appropriate candidates receive targeted immunoconjugates during first-line induction. Furthermore, hematologists must systematically monitor measurable residual disease after completion of induction. Because residual disease eradication predicts sustained remission, clearing minimal residual disease guides subsequent consolidation pathways. Remitters with favorable genetic profiles can proceed to consolidation chemotherapy without immediate stem cell transplantation. Conversely, patients with intermediate or high-risk features should rapidly undergo donor searches for allogeneic transplantation while maintaining complete remission. In addition, treating teams must establish dedicated transfusion schedules, antimicrobial stewardship, and rapid-response protocols for neutropenic fever. By integrating molecular profiling, rigorous supportive care, and risk-adapted consolidation, hematology teams maximize curative potential. Therefore, real-world French observational registry data confirm that antibody-drug conjugate integration represents a cornerstone of personalized leukemia care.
Gemtuzumab ozogamicin consists of a monoclonal antibody linked chemically to a potent cytotoxic calicheamicin derivative. The antibody specifically binds to CD33 receptors on leukemic myeloblasts. Upon binding, the cell internalizes the entire complex through endocytosis. Inside lysosomes, intracellular enzymes release the active calicheamicin antitumor antibiotic. Subsequently, calicheamicin binds minor DNA grooves and causes double-stranded DNA breaks, inducing selective apoptotic death of leukemic blast populations.
Clinical data demonstrate that patients with favorable-risk and intermediate-risk cytogenetics derive the most pronounced survival benefits from CD33-targeted therapy. In contrast, individuals with adverse-risk cytogenetics show less significant disease control improvements. Furthermore, younger adults and fit older patients tolerate combination induction therapy effectively. Therefore, comprehensive diagnostic workups including cytogenetic analysis, mutational profiling, and CD33 surface expression testing remain essential before selecting frontline targeted induction regimens.
Clinicians minimize sinusoidal obstruction syndrome risk by strictly utilizing lower, fractionated dosing schedules rather than older single high-dose infusions. Additionally, oncology teams continuously monitor serum transaminases, bilirubin, and body weight for early fluid retention. If patients require allogeneic hematopoietic stem cell transplantation, teams maintain an adequate time interval after conjugate exposure. Furthermore, avoiding hepatotoxic companion medications significantly prevents endothelial injury and improves procedural safety.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. It is not intended to substitute for professional medical care, diagnosis, or treatment by a qualified healthcare provider. Always consult a physician or other healthcare professional regarding any medical condition or treatment options. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A French multicenter observational study confirms the real-world efficacy and safety of gemtuzumab ozogamicin combined with chemotherapy in newly diagnosed CD33-positive AML, demonstrating a 78.6% response rate, 52.2% MRD negativity, and a median overall survival of nearly 50 months.
Today

A cross-sectional study of 543 patients evaluated the clinical and economic impact of hemophilia inhibitors, revealing higher annual bleeding rates, increased treatment complexity, and severe orthopedic disability, highlighting the need for routine inhibitor screening and modern prophylactic strategies.
Today

Doctors at AIIMS New Delhi have achieved a historic milestone by performing India's first open prenatal myelomeningocele repair on a 25-week unborn fetus. This landmark multidisciplinary procedure provides vital neuroprotective benefits, lowers hydrocephalus risks, and transforms maternal-fetal medicine nationwide.
Today

A randomized crossover trial reveals that daily fresh watermelon consumption significantly reduces baseline TMAO levels and favorably modulates lipid profiles, lowering triglycerides and LDL cholesterol in adults with overweight and obesity.
Today
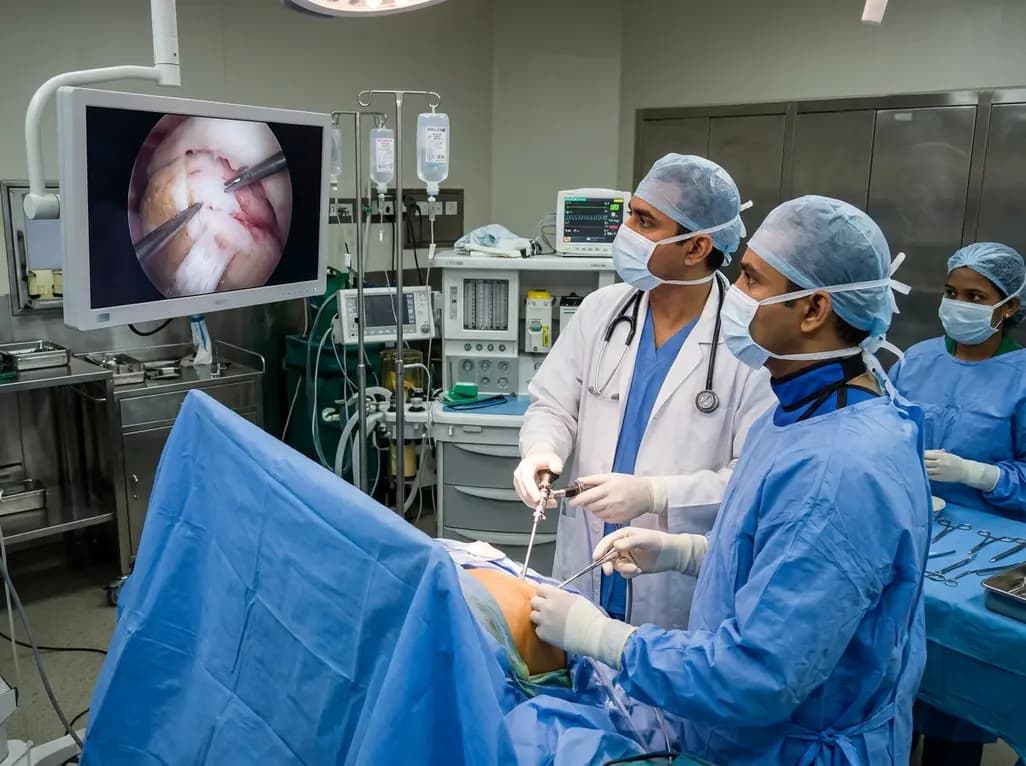
Discover how all-arthroscopic repair using a resorbable bioinductive bovine collagen implant offers a reproducible biologic solution for partial-thickness upper border subscapularis tears, enhancing healing while preserving native tendon architecture.
Today

A large-scale retrospective cohort study demonstrates that GLP-1 receptor agonists significantly reduce all-cause hospitalizations, alcohol-related admissions, major cardiovascular events, and mortality in patients with overweight or obesity and alcohol use disorder, providing profound clinical insights.
Today
