

Loading, please wait...
Loading, please wait...

Clinicians increasingly encounter behavioral addictions in routine clinical practice worldwide. Among these conditions, understanding gambling disorder subtyping has become essential for precise psychiatric care. Historically, researchers segregated gambling behaviors into distinct categories based on game mechanics. However, traditional models frequently overlook the psychological drivers that fuel compulsive wagering. Consequently, clinicians struggle to align research categories with real-world clinical presentations. In this review, we examine modern classification frameworks and targeted management pathways.
Historically, addiction specialists divide gambling activities into strategic and non-strategic modalities. Strategic games primarily involve skill, analysis, and perceived decision-making control. For example, sports betting, poker, and financial market speculation represent strategic gambling. In contrast, non-strategic games rely entirely on pure chance and automated mathematical algorithms. These activities include electronic gaming machines, lotteries, roulette, and digital slot applications.
Furthermore, these structural differences attract distinctly different demographic patient cohorts. Strategic gamblers are predominantly younger males who pursue intellectual stimulation and competitive mastery. In contrast, non-strategic gamblers often include older adults and women seeking emotional escape or mood numbing. Consequently, clinical presentations diverge markedly between these two broad populations. Strategic players frequently present after acute financial losses from escalating bets. Meanwhile, non-strategic players often experience insidious financial erosion over many years. Therefore, recognizing these baseline distinctions provides a critical foundation for diagnostic stratification. However, relying solely on broad game categories can obscure individual patient vulnerabilities and comorbid psychiatric risks.
Cognitive distortions manifest differently depending on the specific gaming mechanics involved. Specifically, strategic gamblers frequently harbor an intense illusion of control. They believe that statistical research and perceived expertise can overcome mathematical house edges. Consequently, they fall prey to confirmation bias, remembering wins while rationalizing catastrophic losses as bad luck. Furthermore, high sensation seeking and impulsivity frequently characterize this subgroup. In many clinical presentations, these individuals also display underlying traits of narcissistic personality disorder.
In contrast, non-strategic gamblers engage in repetitive play primarily to regulate negative affective states. For instance, slot machine players often report entering a trance-like dissociative state. This dissociative absorption shields them temporarily from severe anxiety, chronic pain, or unresolved trauma. Therefore, negative reinforcement drives their addictive loop far more than monetary gain. Moreover, these individuals exhibit exceptionally high rates of comorbid major depressive disorder. Consequently, therapeutic teams must address severe emotional distress alongside the gambling behavior itself. Addressing these divergent cognitive profiles ensures that therapists deliver targeted, effective psychological interventions.
Despite widespread clinical use, existing classification methodologies suffer from substantial empirical limitations. Most notably, researchers define gambling subtypes inconsistently across published literature. Some clinical investigators categorize gamblers strictly by their primary preferred activity. However, other researchers utilize complex behavioral cluster analyses or multi-game frequency thresholds. This lack of standardization severely compromises the reproducibility of clinical research findings. Furthermore, contemporary gamblers rarely confine their activities to a single gambling modality.
Instead, modern digital platforms promote extensive cross-gambling and polymodal betting patterns. For example, a sports bettor can instantly transition to automated online casino games on the same smartphone application. Consequently, classifying a patient as purely strategic or non-strategic often oversimplifies clinical reality. In addition, this methodological heterogeneity impedes the synthesis of systematic reviews and clinical trials. Therefore, the psychiatric community must adopt standardized, validated classification frameworks. Establishing reproducible criteria will ultimately improve diagnostic precision and strengthen multi-center treatment trials globally.
Clinicians must execute structured evaluations when patients present with signs of behavioral addiction. First, physicians should screen for gambling disorder using validated psychometric instruments like the Problem Gambling Severity Index. However, establishing the diagnosis represents only the initial step in comprehensive management. Clinicians must subsequently evaluate the patient's dominant gambling modalities, betting schedules, and access triggers. Furthermore, evaluating the patient's underlying emotional motives clarifies whether play functions as an escape or a thrill.
In addition, clinicians must screen rigorously for co-occurring psychiatric conditions. Disordered gamblers exhibit elevated lifetime rates of substance use disorders, major depression, and generalized anxiety. Notably, strategic gamblers display higher rates of concurrent alcohol and stimulant misuse. In contrast, non-strategic gamblers show marked vulnerability to sedative misuse and chronic dysthymia. Moreover, suicide risk assessment remains paramount across both cohorts. Patients facing catastrophic financial collapse or legal exposure experience acute self-harm vulnerability. Therefore, clinicians must routinely assess suicidal ideation during every clinical encounter. Stratifying patients by behavioral phenotype directly informs safety planning and personalized level of care.
Effective management of gambling disorder requires combining evidence-based psychotherapy with targeted pharmacotherapy. Specifically, cognitive behavioral therapy serves as the first-line psychosocial intervention for all gambling subtypes. However, therapists must tailor cognitive restructuring exercises to the patient's specific subtype profile. For strategic gamblers, therapy focuses aggressively on dismantling the illusion of control and statistical fallacies. In contrast, therapy for non-strategic gamblers emphasizes emotion regulation skills, distress tolerance, and behavioral activation.
Furthermore, pharmacotherapy offers valuable adjunctive benefit, especially when managing severe cravings and impulsivity. Opioid receptor antagonists like naltrexone diminish dopamine-mediated reward reinforcement during gambling urges. In addition, selective serotonin reuptake inhibitors effectively treat comorbid anxiety and depressive illness. Clinicians should also facilitate financial harm reduction by establishing bank transaction blocks and voluntary self-exclusion registries. Family psychoeducation represents another indispensable pillar of sustainable long-term recovery. Involving family members helps restore transparency, manage household finances, and monitor early warning signs of relapse. Consequently, multimodal treatment protocols yield superior clinical outcomes compared to isolated therapeutic measures.
Subtype identification allows clinicians to tailor psychotherapy to specific cognitive distortions and emotional vulnerabilities. For strategic gamblers, therapists target illusions of control, perceived analytical skill, and excessive risk-taking behaviors. In contrast, treatment for non-strategic gamblers addresses mood regulation, coping mechanisms, and emotional escape from chronic stress. Additionally, subtype profiling alerts clinicians to specific comorbidity patterns, including concurrent substance misuse. Consequently, physicians can deliver timely, targeted, and comprehensive psychiatric care.
Non-strategic gamblers often play games like electronic slots or lotteries in private, solitary environments. Consequently, friends and family members fail to notice early financial losses or escalating engagement. Furthermore, these individuals frequently gamble to numb underlying feelings of loneliness, shame, or grief. This emotional suppression delays recognition of behavioral loss of control. Often, patients only present to psychiatric clinics after experiencing severe debt, severe depression, or acute suicidal crises.
Currently, regulatory health agencies have not formally approved specific medications exclusively for gambling disorder. However, clinical psychiatrists successfully utilize several off-label pharmacotherapies to suppress cravings. In particular, opioid receptor antagonists like naltrexone effectively blunt the dopamine rush associated with gambling cues. In addition, doctors frequently prescribe selective serotonin reuptake inhibitors to manage comorbid mood and anxiety symptoms. Mood stabilizers such as topiramate can also help attenuate severe behavioral impulsivity.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive clinical overview evaluating gambling disorder subtyping, distinguishing strategic and non-strategic gambling phenotypes, and addressing the diagnostic and therapeutic implications for behavioral addiction practice.
Today
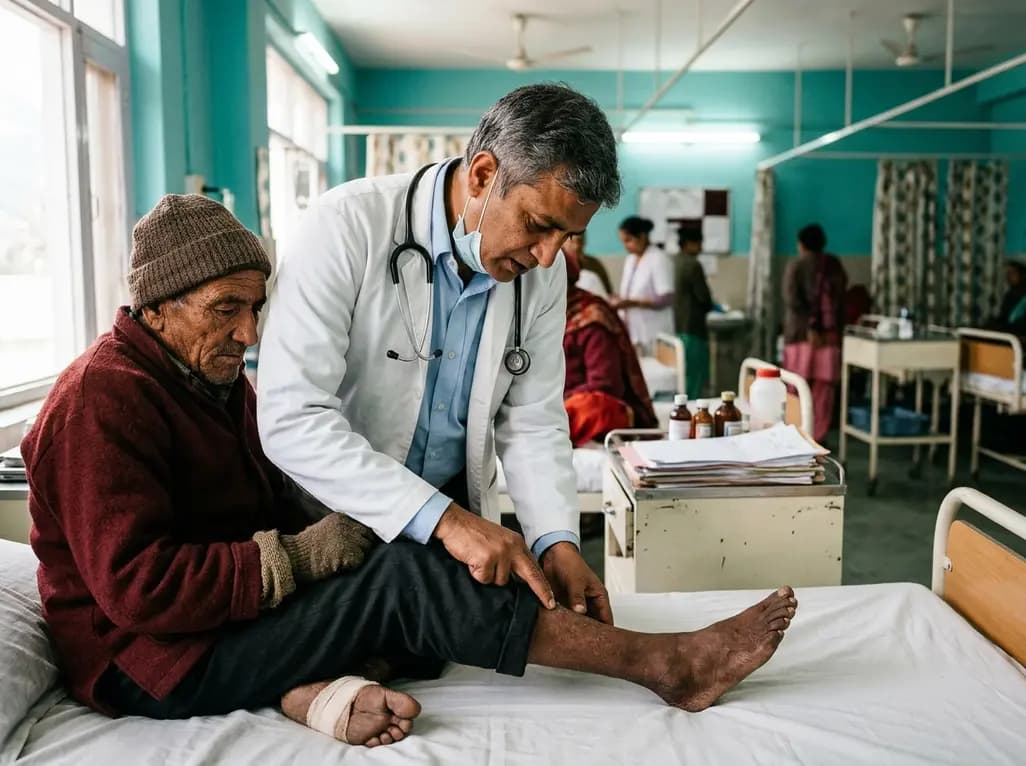
A recent cross-sectional study reveals that prolonged residence at high altitude significantly escalates foot frostbite risk among lowland migrants, with chronic mountain sickness acting as a significant physiological mediator through hyperviscosity and microcirculatory stasis.
Today
A litigation-derived series of 252 women highlights the risks of repeat revisions after midurethral sling surgery. Recurrent incontinence occurred in up to 60% of patients, and repeat revision rates reached 70%, emphasizing cautious patient selection and skilled multidisciplinary management.
Today
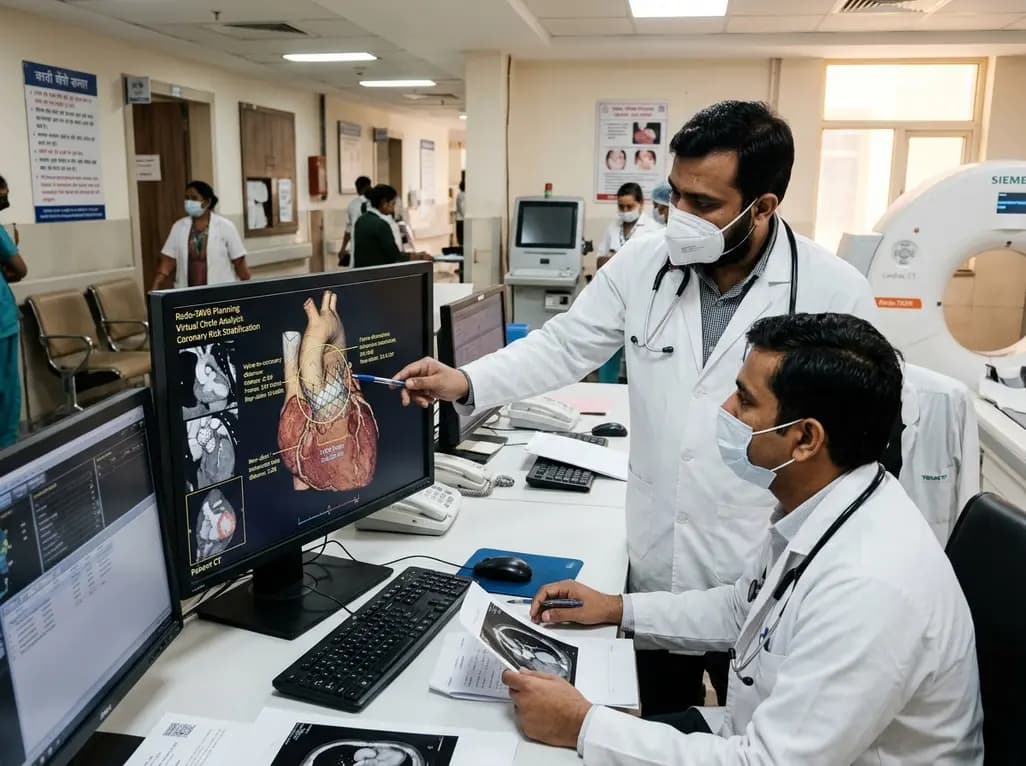
A multicenter study evaluating paired cardiac CT scans reveals that the virtual circle method reliably predicts index transcatheter valve frame expansion and changes in valve-to-aorta distance during redo-TAVR, offering accurate or conservative coronary risk stratification in 85% of cases.
Today
Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Today

India is poised to transform chronic disease management through wearable health technology. Discover how continuous remote monitoring and predictive algorithms empower clinicians to detect early cardiovascular signals, personalize metabolic interventions, and deliver equitable preventive care across populations.
Today
