

Loading, please wait...
Loading, please wait...
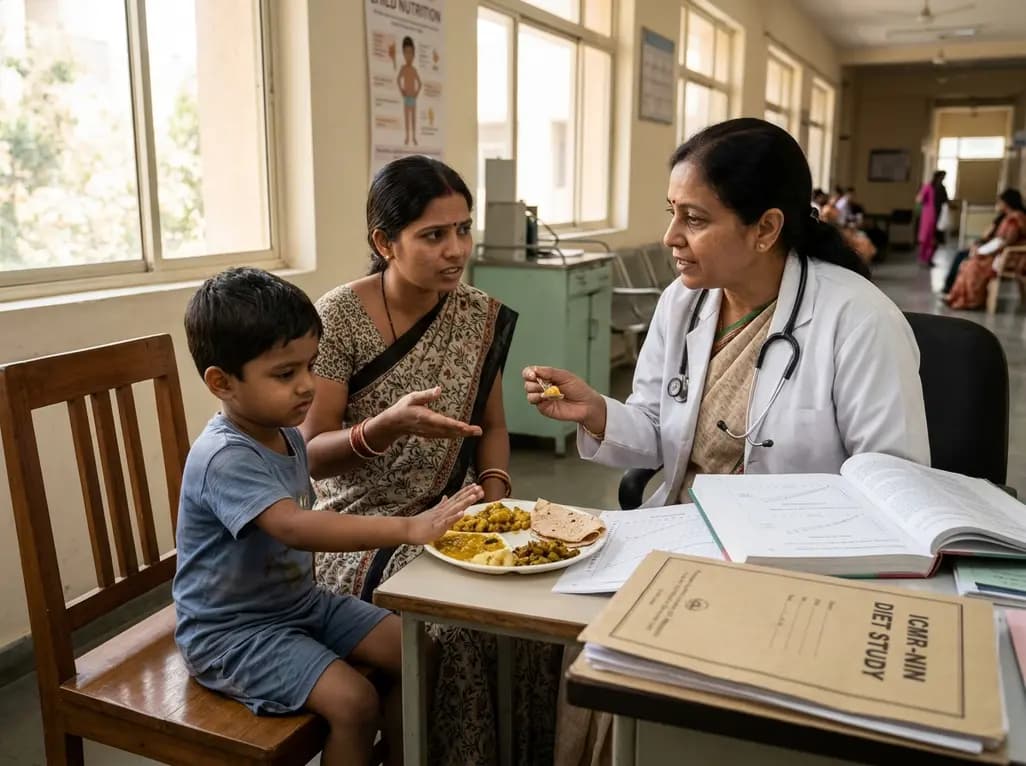
A landmark investigation by the Indian Council of Medical Research–National Institute of Nutrition has illuminated the prevalence of food neophobia in children within urban settings. Published in the Journal of Nutritional Science, the research evaluated 150 mother-child dyads in Addagutta, Hyderabad. The investigators observed that nearly 77% of children aged two to seven years exhibited moderate reluctance to try unfamiliar foodstuffs. Furthermore, 11.3% presented with severe aversion, whereas only 12% demonstrated low neophobia. These findings emphasize that early food hesitance represents a widespread developmental hurdle rather than an isolated behavioral eccentricity.
Food neophobia in children describes an adaptive yet challenging developmental phase wherein pediatric patients display persistent hesitation toward novel foods. The researchers employed the validated Child Food Neophobia Scale alongside World Health Organization anthropometric standards to systematically evaluate eating behaviors. Consequently, the team gathered rigorous behavioral data across early childhood age groups. Although male children registered slightly higher mean neophobia scores than female peers, the difference remained statistically insignificant. Therefore, biological sex does not appear to dictate food acceptance patterns during these formative preschool years.
Additionally, the researchers observed that behavioral reluctance peaks during transition periods from breast milk to diversified family diets. Young children often view novel textures, bitter vegetables, or unfamiliar aromas with suspicion. When clinicians do not recognize this protective evolutionary instinct, mealtime friction frequently intensifies. Consequently, pediatric healthcare providers must interpret these patterns as standard developmental stages rather than intentional obstinacy. A clear clinical grasp of these nuances enables practitioners to reassure stressed parents effectively.
Crucially, the study established a clear relationship between maternal knowledge, attitudes, and practices (KAP) and child eating behaviors. Children whose mothers scored moderately on comprehensive feeding assessments demonstrated significantly lower food neophobia levels compared to children of low-scoring mothers. Thus, caregiver knowledge directly shapes child food acceptance and dietary variety. When mothers adopt responsive feeding techniques, young children adapt more readily to unfamiliar flavors.
Conversely, inconsistent maternal behaviors and excessive mealtime pressure frequently worsen dietary resistance. For example, pressuring a hesitant child to clear their plate often reinforces aversion toward that specific food group. In contrast, parental role modeling and communal family dining encourage spontaneous exploration. Caregivers who consume diverse vegetables, fruits, and whole grains visibly validate dietary safety for their children. Therefore, early parental education must become a central pillar of pediatric dietary counseling. When clinicians equip mothers with patient behavioral strategies, children gradually overcome sensory hesitations.
Perhaps the most critical clinical finding involves the link between acute malnutrition and heightened food rejection. Specifically, children exhibiting wasting—a severe form of acute undernutrition defined by low weight-for-height—recorded markedly higher neophobia scores than non-wasted peers. As a result, food refusal directly compounds existing nutritional vulnerabilities, accelerating micronutrient deficiencies and muscle wasting.
This bidirectional correlation creates a perilous clinical dilemma in resource-limited communities. Undernourished children frequently experience decreased appetite, altered gustatory sensitivity, and compromised gut integrity. Consequently, these physiological disturbances diminish their enthusiasm for trying unfamiliar, nutrient-dense items. Simultaneously, persistent rejection of diverse food items deprives these vulnerable patients of essential proteins, vitamins, and minerals. Thus, early identification of acute malnutrition demands simultaneous behavioral screening. Pediatricians must address both nutritional replenishment and feeding psychology to secure durable clinical recovery.
Lead study author Dr. Karthikeyan Ramanujam emphasized that structured behavioral modifications effectively resolve childhood food neophobia. Most importantly, clinicians must advise caregivers to avoid coercive feeding techniques, bribery, or force-feeding. Instead, families should offer unfamiliar food items repeatedly without attaching conditions or emotional stress. Pediatric literature indicates that toddlers often require eight to fifteen separate exposures before accepting an unfamiliar texture or flavor.
Furthermore, structuring mealtimes into calm, predictable routines significantly lowers mealtime anxiety. Parents should pair a small portion of a novel ingredient alongside familiar comfort foods on the same plate. In addition, encouraging young children to interact with raw produce through touch, washing, and kitchen participation demystifies unfamiliar items. Sensory play reduces apprehension without forcing immediate ingestion. Over time, gentle familiarity replaces fear, allowing children to develop broader taste profiles naturally.
ICMR-NIN Director Dr. Bharati Kulkarni highlighted that national health frameworks must integrate feeding behavior counseling into community outreach. Existing public health structures, such as the Integrated Child Development Services (ICDS) and POSHAN Abhiyaan, maintain extensive grassroots networks across India. Consequently, these programs offer an ideal platform to train frontline Anganwadi workers and Accredited Social Health Activists (ASHAs).
Moreover, community health workers can deliver actionable feeding guidance directly during routine home visits and immunization drives. When public programs emphasize responsive feeding rather than solely distributing supplementary rations, community nutrition improves substantially. Frontline workers can teach caregivers how to prepare colorful, attractive, and nutrient-dense local meals. By leveraging institutional platforms, national health policy can systematically address both behavioral neophobia and acute wasting on a wide geographic scale.
Primary care physicians and pediatricians occupy the frontline in identifying and managing pediatric dietary challenges. During routine well-child visits, clinicians must routinely assess feeding dynamics alongside standard growth plotting. Whenever a child presents with growth faltering or acute wasting, physicians should actively screen for food neophobia. Identifying behavioral resistance early prevents prolonged malnutrition and reduces parental distress.
Additionally, clinicians must provide reassuring yet pragmatic counseling to anxious caregivers. Healthcare professionals should emphasize that neophobia is often transient and amenable to patient environmental adaptations. By discouraging punitive mealtimes and promoting pressure-free exposure, practitioners empower families toward sustainable success. Collaborative clinical discussions regarding diet diversity ensure children achieve their full developmental and physical growth potential.
Q1: What does food neophobia mean in young children?
Food neophobia refers to the developmental reluctance or refusal to taste and consume unfamiliar foods. It represents an adaptive evolutionary protective mechanism that typically emerges during the preschool years. While most children experience moderate hesitation when encountering new textures or flavors, persistent neophobia can limit dietary diversity, compromise caloric intake, and impede balanced childhood nutrition without supportive caregiver intervention.
Q2: How does childhood food neophobia correlate with acute wasting?
The ICMR-NIN investigation revealed that children with wasting scored significantly higher on food neophobia scales than well-nourished peers. This correlation establishes a dangerous cycle where restricted dietary intake worsens acute weight loss and nutrient depletion. Concurrently, physiological illness and micronutrient deficiencies can suppress appetite and increase sensory aversion, thereby exacerbating existing food refusal behaviors.
Q3: What methods help caregivers introduce new foods without mealtime conflict?
Caregivers should offer unfamiliar ingredients repeatedly—often up to fifteen separate times—without forcing or pressuring the child. Serving tiny portions alongside preferred comfort foods minimizes mealtime anxiety. Additionally, involving children in food selection, maintaining calm meal schedules, and demonstrating positive parental eating habits effectively foster curiosity, significantly improving long-term willingness to taste novel foods.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark ICMR-NIN study in Hyderabad highlights that nearly 77% of children aged two to seven exhibit moderate food neophobia. Discover how maternal feeding practices, nutritional wasting, and repeated non-coercive food exposure influence dietary diversity and early childhood growth.
Today

With packaged goods giant HUL backing FSSAI's proposed front-of-pack red warning labels for foods high in fat, sugar, and salt, India takes a major step toward curbing non-communicable diseases. Learn how clearer nutrition disclosures empower clinicians, inform consumer choices, and drive dietary reform.
Today

A nationwide cohort study published in JAMA Pediatrics reveals that maternal exposure to wildfire fine particulate matter, especially in late pregnancy, is linked to an elevated risk of childhood autism. Clinicians should evaluate ambient air quality risks and provide proactive protective counseling to mothers.
Today

With India still adhering to 2009 air pollution benchmarks, the delayed NAAQS revision exposes populations to fine particulate matter far exceeding global safety limits. Clinicians face surging cardiopulmonary morbidity, emphasizing the urgent need for stringent, health-centered regulatory thresholds nationwide.
Today

Modern 3D anthropometry reveals that pediatric leg growth ceases years before spinal elongation, exposing the clinical illusion of the classical Anderson-Green model. Learn how segmental growth dissociation improves surgical timing for epiphysiodesis in adolescent leg length discrepancy.
2 days back

A meta-analysis of 18 studies reveals that bariatric surgery does not significantly alter circulating homocysteine levels, regardless of follow-up duration. Clinicians must maintain vigilance over post-surgical micronutrient supplementation to prevent hyperhomocysteinemia.
2 days back
