

Loading, please wait...
Loading, please wait...

Prenatal detection of intracardiac flow alterations frequently generates clinical anxiety during late gestation. Among these vascular changes, fetal foramen ovale restriction represents a distinct hemodynamic entity requiring careful echocardiographic surveillance. While clinicians often fear cardiac decompensation or impending fetal compromise, recent clinical evidence illuminates the real-world trajectory of this diagnosis. Understanding its natural progression enables obstetricians and fetal medicine specialists to formulate balanced perinatal strategies without resorting to premature intervention. Consequently, evidence-based management protects both maternal and neonatal health.
Echocardiographic assessment of the interatrial septum requires standardized metrics to distinguish physiological variation from true flow restriction. Specifically, clinicians diagnose fetal foramen ovale restriction when the anatomical diameter measures under 3 millimeters alongside an elevated peak Doppler flow velocity exceeding 40 centimeters per second. Normal fetal circulation depends on an unobstructed right-to-left interatrial shunt to supply oxygenated blood directly to the left atrium. Consequently, narrowing of this aperture accelerates blood flow across the septum and increases resistance within the atrial chambers. In a large retrospective cohort evaluating this entity, the incidence reached 1.88% across all fetal echocardiographic evaluations. Ultrasonographers also examine the excursion of the septum primum into the left atrium during the cardiac cycle. However, redundant or aneurysmal septal membranes can mimic obstruction without creating true flow limitation. Therefore, spectral Doppler interrogation remains essential to confirm high-velocity flow across the narrowed orifice. By combining precise two-dimensional anatomical measurements with spectral Doppler velocities, maternal-fetal medicine teams establish an accurate baseline. This systematic evaluation prevents diagnostic ambiguity and anchors subsequent antenatal monitoring on objective parameters. Diagnostic clarity allows clinicians to avoid misinterpreting benign physiological variations as severe structural anomalies.
When the interatrial aperture narrows, fetal intracardiac hemodynamics shift markedly toward the right-sided cardiac structures. Because blood cannot freely enter the left atrium, the right atrium and right ventricle absorb an increased volume load. Consequently, fetal echocardiography reveals right heart enlargement in approximately 74.6% of affected fetuses, making it the most frequent secondary cardiac feature. Clinicians observe dilation of the right atrium, tricuspid valve annular enlargement, and right ventricular dominance on four-chamber views. In addition, elevated right-sided intracardiac pressures may provoke mild-to-moderate tricuspid regurgitation without intrinsic leaflet pathology. Notably, fetal physiology accommodates this volume redistributive burden through the low-resistance pulmonary vascular bed and patent ductus arteriosus. Furthermore, systemic venous Doppler patterns in the ductus venosus typically maintain forward flow unless severe decompensation occurs. Obstetricians must recognize that chamber asymmetry in late pregnancy frequently stems from this altered flow pattern rather than true aortic coarctation. Therefore, serial echocardiographic evaluations should track chamber dimensions and ventricular function. This focused surveillance reassures clinicians that isolated right heart dominance rarely causes overt congestive failure. Consequently, clinicians avoid premature iatrogenic delivery when myocardial performance remains intact.
The gestational timing of diagnosis provides valuable prognostic perspective for perinatal clinicians. Most cases emerge during late pregnancy, with a median gestational age at diagnosis of 35 weeks and 4 days. In contrast, only 11.7% of fetuses receive a diagnosis before 32 weeks of gestation. This late emergence aligns with physiological changes in late pregnancy, including enhanced pulmonary venous return and evolving septal geometry. Furthermore, clinical investigations demonstrate that coexisting pregnancy complications or non-cardiac fetal anomalies occur in 51.6% of diagnosed mothers. These maternal conditions frequently include gestational diabetes, hypertensive disorders, and fetal growth restriction. Conversely, isolated restriction without extracardiac pathology occurs in approximately 41.2% of presentations. Because concomitant maternal-fetal comorbidities independently influence fetal health, specialists must not attribute all signs of fetal vulnerability exclusively to the interatrial defect. Instead, maternal-fetal medicine units should conduct a thorough structural survey alongside umbilical artery Doppler evaluations. When clinicians isolate the interatrial narrowing from other systemic complications, they can tailor prenatal counseling accurately. Consequently, comprehensive evaluation ensures that management addresses maternal systemic pathology and fetal cardiac hemodynamics concurrently. Therefore, identifying maternal metabolic and hypertensive states provides an essential foundation for balanced clinical decisions.
The discovery of intracardiac flow restriction often provokes unwarranted clinical alarm and hasty operative planning. Historically, obstetricians frequently scheduled early surgical delivery out of concern for impending fetal circulatory collapse. Indeed, registry data indicate a cesarean delivery rate of 64.7% among these pregnancies, with non-reassuring fetal status serving as the leading indication in 24.0% of births. However, rigorous multivariate analyses challenge the necessity of routine surgical intervention. Researchers confirmed that foramen ovale diameter, diagnosis timing, and right heart enlargement do not independently dictate delivery mode. Therefore, isolated interatrial narrowing does not warrant elective preterm induction or primary cesarean section. Rather, clinicians should base delivery timing and route on standard obstetric indications, such as progressive non-reassuring cardiotocography or severe preeclampsia. Furthermore, labor management requires continuous intrapartum electronic fetal monitoring because compromised fetuses may display reduced reserve under contractile stress. In the absence of acute distress, obstetric teams can safely pursue a trial of vaginal labor at term. Consequently, modern evidence strongly supports conservative antepartum management over reactionary surgical delivery.
Postnatal follow-up offers profound reassurance to both anxious parents and clinical teams. Although intrauterine hemodynamics display striking right heart prominence, neonatal outcomes remain predominantly favorable. Among infants undergoing structured postnatal follow-up, approximately 27.1% display echocardiographic cardiac abnormalities immediately after birth. These findings predominantly comprise benign interatrial communications, trivial valvular regurgitation, or transient chamber disproportion. Crucially, longitudinal registry tracking demonstrates that 93.8% of these postnatal cardiac anomalies resolve spontaneously within the first year of life. In addition, true persistent congenital heart disease occurs in only 1.7% of neonates. Once the newborn transitions to pulmonary respiration, left atrial pressures rise swiftly and pulmonary vascular resistance drops precipitously. This physiological transformation promptly alleviates the right-sided volume overload that predominated in utero. Consequently, neonates rarely require pharmaceutical inotropic support or urgent catheter interventions. Pediatric cardiologists recommend a baseline postnatal echocardiogram within the early neonatal period followed by reassessment at six to twelve months. This physiological shift demonstrates that prenatal chamber enlargement usually reflects temporary volume shifts rather than permanent malformations. Because spontaneous resolution occurs in most infants, multidisciplinary teams can counsel families with confidence regarding favorable long-term cardiovascular health.
No, the presence of interatrial flow restriction does not independently necessitate a cesarean delivery. Multivariate analyses confirm that anatomical orifice size, gestational age at diagnosis, and secondary right ventricular enlargement do not predict adverse outcomes during labor. Consequently, obstetricians should reserve surgical delivery strictly for standard obstetric indications or verified intrapartum fetal distress, allowing stable mothers to pursue normal vaginal delivery under continuous cardiotocographic surveillance.
Specialists confirm the diagnosis on fetal echocardiography by documenting an anatomical foramen ovale diameter under 3 millimeters alongside an accelerated Doppler peak flow velocity greater than 40 centimeters per second. Additionally, sonographers assess right-to-left interatrial shunting, septal flap mobility, and secondary signs of volume loading. These secondary signs frequently include right atrial and ventricular enlargement, tricuspid regurgitation, and altered pulmonary venous Doppler waveforms during the late second or third trimester.
The long-term neonatal prognosis is overwhelmingly favorable for infants born with this condition. Although roughly 27% show transient cardiac findings such as patent interatrial communications immediately after birth, nearly 94% resolve spontaneously within one year. Persistent structural congenital heart defects occur in less than 2% of infants. Therefore, most newborns adapt smoothly to post-gestational hemodynamics without needing cardiac medications, catheter procedures, or surgical operations.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Fetal foramen ovale restriction typically emerges in the third trimester with right heart enlargement. Evidence demonstrates it does not independently mandate cesarean delivery, and over 93% of postnatal cardiac findings resolve spontaneously within one year, supporting conservative obstetric management.
Today

Discover a synchronized faculty and fellow quality improvement curriculum designed for geriatric and palliative care, strengthening institutional mentorship and clinical outcomes.
Today
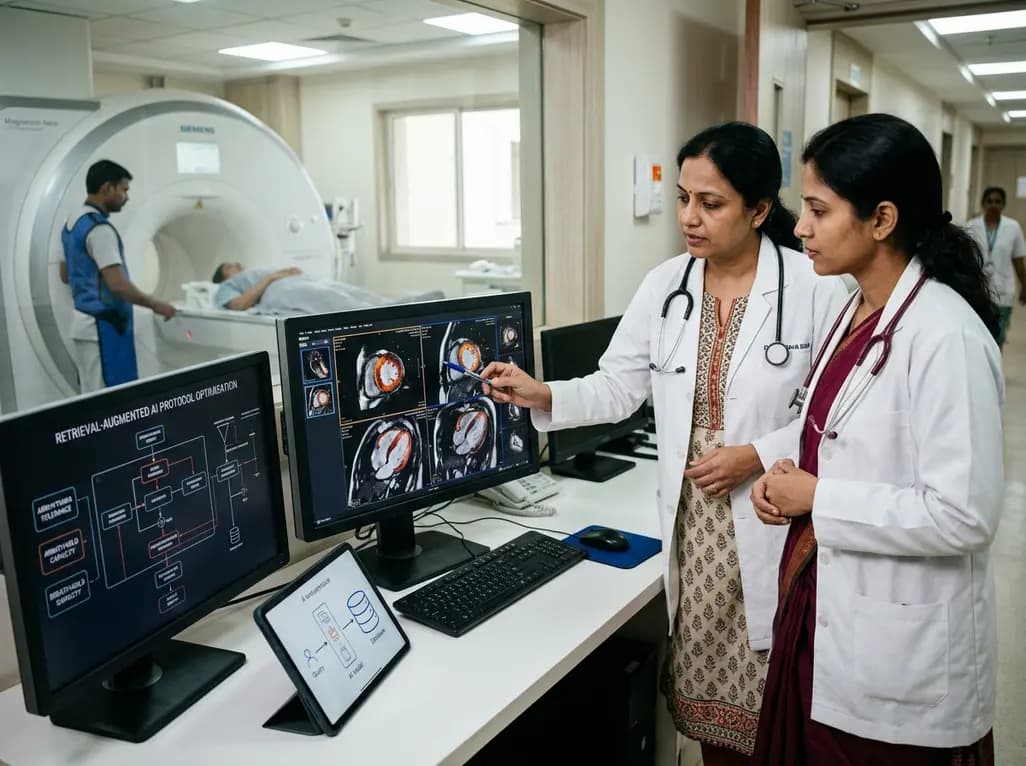
A prospective study demonstrates that an AI framework utilizing a retrieval-augmented LLM personalizes cine cardiac MRI protocols with diagnostic accuracy noninferior to experienced technologists, even in complex clinical scenarios involving arrhythmia and limited breath-holding capacity.
Today
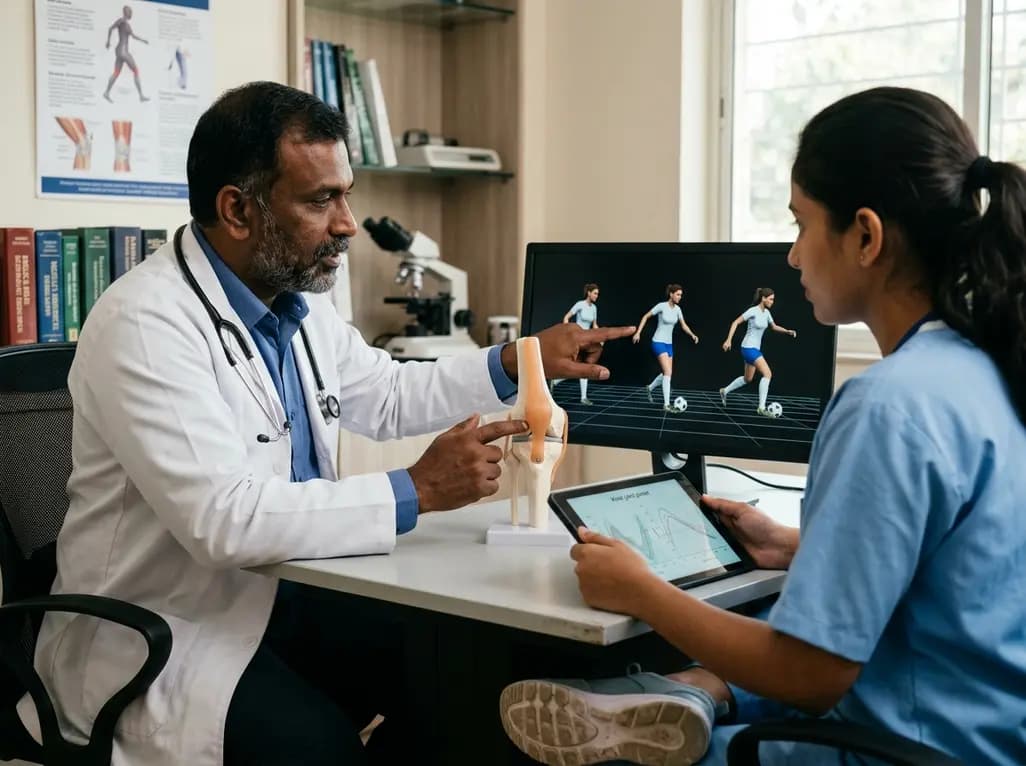
New biomechanical research reveals that foot-strike angle significantly influences knee energy absorption during cutting tasks in female soccer players. Understanding these kinematic patterns offers clinicians valuable pathways for targeted ACL injury prevention and athletic retraining.
Today
A comprehensive review analyzes periconceptional GLP-1 receptor agonist exposure, revealing reassuring data on congenital anomalies and adverse perinatal outcomes while emphasizing the need for cautious patient counseling.
Today
