

Loading, please wait...
Loading, please wait...
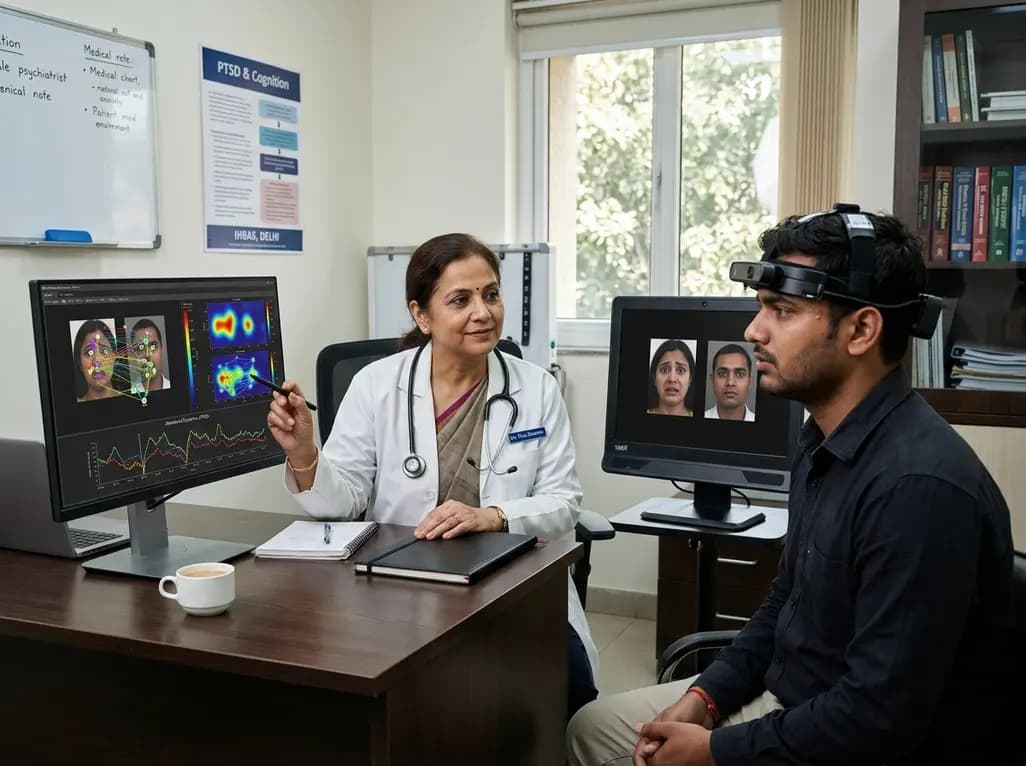
Post-traumatic stress disorder alters neural circuits responsible for executive control and affective processing. Consequently, affected individuals frequently display pronounced disruptions in visual exploration when encountering emotionally salient environmental cues. Clinical neuroscience traditionally characterized these abnormalities as persistent, immutable hypervigilance toward potential survival threats. However, contemporary empirical investigations demonstrate that visual processing alterations represent a far more nuanced, fluid phenomenon. Recent advances in eye-tracking in PTSD reveal dynamic, context-dependent attentional fluctuations that alternate between rapid threat detection and deliberate sensory evasion. Understanding these oculomotor mechanics provides clinicians with critical insights into trauma-related cognitive dysfunction. Thus, objective physiological markers are reshaping modern trauma diagnostics.
Historically, psychiatric formulations viewed trauma survivors as perpetually scanning their surroundings for danger. In contrast, emerging oculomotor data portray attentional control as a fluctuating, adaptive process that shifts across varying contexts. Early cognitive models relied heavily on manual reaction-time paradigms, such as emotional Stroop or dot-probe tasks. However, these traditional assessments only capture the static end-product of cognitive evaluation. They inherently fail to measure intermediate ocular shifts, early fixational tendencies, and sustained gaze persistence. Therefore, researchers now utilize ocular movement recording to map gaze trajectories continuously across hundreds of milliseconds. When trauma survivors view emotionally charged scenes, their ocular responses reflect rapid shifts between hypervigilant initial fixation and subsequent gaze aversion. Furthermore, this dynamic variability often corresponds to acute subjective distress, elevated re-experiencing symptoms, and functional executive impairment. As a result, clinicians recognize that attentional bias in trauma is dynamic rather than uniformly elevated. In addition, neurobiological investigations indicate that rapid shifts between vigilance and avoidance mirror underlying dysregulation within the salience and default mode networks. Consequently, modern psychopathology views gaze instability as a core behavioral phenotype. This paradigm shift encourages clinicians to evaluate cognitive flexibility rather than isolated vigilance metrics.
Specialized laboratory protocols evaluate diverse facets of oculomotor and executive functioning in traumatized individuals. Specifically, visual search, free-viewing, and antisaccade paradigms offer complementary perspectives on distinct cognitive domains. In free-viewing tasks, patients frequently demonstrate shortened scanpaths and reduced visual exploration when viewing threat-related or trauma-congruent stimuli. Consequently, their gaze patterns indicate constricted environmental processing, cognitive avoidance, and elevated emotional apprehension. Meanwhile, antisaccade tasks demand substantial prefrontal inhibitory control, requiring participants to direct their gaze rapidly away from sudden visual onsets. Studies consistently demonstrate that patients with post-traumatic stress exhibit impaired inhibitory control, displaying increased antisaccade error rates and prolonged saccadic latencies. Furthermore, visual search paradigms reveal that trauma survivors struggle to disengage attention from threat-related distractors when pursuing neutral visual targets. Moreover, multimodal experiments combining ocular recording with electroencephalography reveal that early perceptual encoding abnormalities precede conscious cognitive appraisal. Therefore, eye-tracking in PTSD elucidates both pre-attentive sensory processing and downstream executive dysregulation with millisecond temporal precision. In addition, these specialized behavioral paradigms highlight profound disruptions in voluntary cognitive control across diverse environmental settings. These distinct experimental tasks establish granular physiological profiles that standard clinical interviews cannot duplicate.
While early threat detection characterizes initial trauma responses, downstream cognitive mechanisms often trigger marked attentional avoidance. Traumatized individuals deliberately redirect their visual attention away from distressing stimuli to diminish autonomic arousal and emotional distress. Furthermore, escalating working memory load significantly impairs top-down executive control over visual processing. Under demanding cognitive conditions, trauma survivors exhaust central prefrontal resources, which hinders flexible attentional allocation. Consequently, patients exhibit reduced visual exploration and constricted viewing patterns across neutral and threatening contexts alike. Researchers observe that this pronounced ocular constriction reflects an active, protective strategy designed to minimize emotional overload and physiological hyperarousal. In addition, neuroimaging studies indicate that hypoactivation within the dorsolateral prefrontal cortex directly correlates with delayed disengagement and oculomotor fatigue. As a result, cognitive fatigue exacerbates visual avoidance behaviors during complex daily tasks. Similarly, elevated stress hormones disrupt prefrontal catecholamine signaling, worsening ocular scanpath truncation during dual-task challenges. Clinicians must therefore recognize that avoidance represents an active compensatory mechanism rather than passive emotional apathy. In conclusion, addressing executive depletion remains crucial for designing targeted clinical interventions.
Recent psychotraumatology investigations highlight attention bias variability as an indispensable metric of symptom severity. Instead of maintaining stable attention or sustained avoidance, patients frequently oscillate unpredictably between both extremes. Consequently, this continuous gaze instability reflects a destabilized attentional monitoring system struggling to balance safety and threat detection. Notably, individuals with higher bias variability report more severe intrusive memories, severe hyperarousal, and elevated functional disability. Furthermore, trauma typology heavily shapes ocular profiles and oculomotor performance. For instance, survivors of chronic interpersonal violence often exhibit distinct visual search patterns compared to survivors of acute civilian accidents. Similarly, severe dissociative subtypes frequently demonstrate profound sensory detachment, manifesting as prolonged staring episodes, decreased blink frequency, and reduced saccadic velocity. In contrast, non-dissociative hyperarousal phenotypes demonstrate rapid saccadic trajectories and frequent glance shifts toward peripheral areas. Therefore, evaluating individualized oculomotor profiles accounts for clinical heterogeneity, refining personalized neurocognitive treatment plans. In addition, recognizing individual cognitive variations prevents clinicians from applying oversimplified therapeutic assumptions. By mapping these subtle variations, practitioners can identify patient-specific cognitive markers that predict treatment responsiveness.
The clinical translation of oculomotor analytics promises to revolutionize neuropsychiatric assessment and intervention strategies. Because traditional psychiatric evaluations rely upon subjective self-report questionnaires, clinician-rated scales often suffer from retrospective recall bias. In contrast, gaze tracking yields reliable, objective, and quantifiable biomarkers of underlying central nervous system dysfunction. Furthermore, eye movement metrics offer sensitive endpoints to monitor pharmacological and psychotherapeutic efficacy over time. For example, successful trauma-focused cognitive behavioral therapy or exposure interventions can gradually normalize erratic visual scanpaths and reduce gaze avoidance. Additionally, specialized attentional bias modification paradigms utilize gaze-contingent software to train patients toward healthier visual foraging behaviors. Clinicians can simultaneously assess physiological improvement and cognitive remediation throughout recovery. In addition, coupling eye-tracking with pupil dilation metrics provides real-time information regarding sympathetic nervous system activation during therapeutic challenges. Consequently, integrating gaze monitoring within multimodal psychiatric diagnostics bridges the divide between theoretical cognitive neuroscience and real-world clinical practice. Modern clinicians will increasingly employ these sophisticated digital biomarkers to optimize individualized psychiatric care.
Eye-tracking records continuous ocular fixations and rapid saccades with millisecond temporal resolution during visual exposure. Consequently, it captures the initial orienting reflex toward a stimulus, reflecting early hypervigilance, alongside subsequent gaze direction. If an individual quickly fixates on a threat cue and then consistently shifts their gaze elsewhere, the paradigm captures dynamic avoidance. Therefore, ocular tracking clearly differentiates immediate sensory detection from downstream voluntary avoidance strategies.
Traditional reaction-time tasks only measure the final motor outcome of a complex cognitive process. In contrast, ocular tracking captures continuous, intermediate attentional shifts occurring prior to any physical button press. Furthermore, gaze metrics evaluate pupil dilation, fixational duration, and scanpath velocity across the entire visual presentation window. As a result, ocular parameters identify subtle cognitive instability and inhibitory dysregulation that single-point behavioral response times consistently overlook.
Trauma characteristics and individual symptom profiles profoundly alter visual exploration patterns during cognitive testing. For instance, chronic developmental trauma often triggers prolonged attentional avoidance, blunted pupillary reactivity, and constricted scanpaths. Conversely, acute single-incident trauma typically produces pronounced initial hypervigilance and elevated antisaccade error rates. Moreover, dissociative symptoms foster prolonged, unfocused fixations, whereas predominant hyperarousal manifests as rapid, erratic saccadic movements across environments.
Disclaimer: This content is for informational and educational purposes only. It is not intended to provide medical advice, diagnosis, or treatment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive scoping review synthesises recent evidence on eye-tracking in post-traumatic stress disorder. The findings demonstrate that attentional biases are dynamic and context-dependent, oscillating between vigilance and avoidance, providing key objective biomarkers for clinical psychiatry.
Today

A retrospective cohort study evaluates the short- and long-term impacts of SARS-CoV-2 infection on patients with Graves' disease receiving antithyroid drug therapy, highlighting thyroid status destabilization, clinical symptom exacerbations, and post-viral sequelae.
Today

A comprehensive meta-analysis of over 278,000 women demonstrates that maternal atopic dermatitis significantly increases risks of premature rupture of membranes and low birth weight. Discover essential clinical insights on disease mechanisms, serial antenatal growth monitoring, and safe therapeutic interventions.
Yesterday

Pharmacogenomics and artificial intelligence are revolutionizing cardiology by tailoring therapies to individual genetic profiles and clinical data, reducing adverse drug events, and improving cardiovascular patient outcomes.
Today

India's premier scientific bodies have joined the Armed Forces Medical Services to solve unique physiological and operational challenges faced by soldiers. The national collaboration covers combat casualty care, artificial intelligence diagnostics, bionic prosthetics, and extreme-environment physiological resilience.
Today

Over 60 international public health researchers have advised FSSAI to mandate front-of-pack warning labels for any packaged product high in even one critical nutrient: sugar, saturated fat, or sodium. This reform counters phased rollouts to accelerate consumer protection and address India's chronic disease burden.
Today
