

Loading, please wait...
Loading, please wait...

The culinary identity of traditional dairy foods faces unprecedented regulatory and clinical scrutiny across India. On Wednesday, the Delhi High Court issued formal notices to the Food Safety and Standards Authority of India (FSSAI), the Union Government, and the Delhi Government regarding a public interest litigation. The petition challenges the rampant commercial distribution of dairy analogue paneer sold under the guise of authentic cottage cheese. Consequently, judicial authorities have demanded rigorous accountability from food regulators within six weeks.
A division bench comprising Acting Chief Justice Nitin W Sambre and Justice Sanjay Singh presided over the judicial proceedings. Specifically, petitioners Ridhima Singh and Avlokiteshwar Padmapani Sidharth drew urgent judicial focus to misleading marketing practices that exploit unsuspecting consumers. The petitioners highlighted that commercial vendors frequently serve dairy analogues as genuine cottage cheese across restaurants, wedding caterers, and online delivery portals. Because commercial kitchens blend these substitutes into spiced curries, everyday diners cannot easily detect the omission of genuine dairy milk. Therefore, the petitioners pleaded for immediate regulatory intervention, citing heightened dairy demand during the ongoing festive season. During the hearing, the bench noted that enforcement authorities have already initiated sampling drives and placed preliminary testing statistics on record. However, the petitioners argued that sporadic seizures cannot substitute for comprehensive, permanent market surveillance. Consequently, the court directed statutory bodies to submit formal responses outlining concrete measures to curb deceptive commercial practices. This judicial scrutiny underscores an urgent necessity to safeguard consumer autonomy and guarantee transparent nutritional standards across all hospitality venues. Ultimately, public health advocates hope this decisive judicial intervention will force food safety commissioners to enforce strict penal actions against intentional misbranding.
Under existing food safety regulations, authentic paneer holds a strictly protected statutory classification. The regulatory framework defines chhana or paneer exclusively as a product obtained from bovine milk through heat-acid precipitation. Therefore, authentic paneer must derive all of its protein and lipid fractions directly from genuine milk solids. In sharp contrast, dairy analogues represent formulated imitation matrices designed to mimic traditional sensory characteristics at a fraction of production costs. Manufacturers typically replace high-cost dairy fats with inexpensive refined palm oil, hydrogenated fats, or soybean fractions. Additionally, processors incorporate modified starches, hydrocolloids, and industrial emulsifiers to recreate the firm, sliceable texture of pressed curd. While food safety regulations allow the licensing of analogues under designated technical categories, sellers must never market them under the protected name of paneer. Misrepresenting an analogue as an authentic dairy product directly violates statutory labelling mandates and consumer rights. Thus, substituting milk fats with industrial vegetable oils without explicit consumer disclosure constitutes blatant adulteration and commercial deception. Regulatory agencies must therefore bridge the massive enforcement gap between packaged supermarket goods and unpackaged restaurant dishes.
The deceptive sale of analogue foods poses serious nutritional hazards for the Indian population. Traditionally, millions of vegetarians rely heavily on paneer as an indispensable source of high-biological-value protein. Authentic paneer provides a balanced profile of essential amino acids alongside bioavailable calcium, phosphorus, and fat-soluble vitamins. Conversely, dairy analogues frequently deliver substantially inferior nutritional returns. Industrial formulations often replace superior milk casein with inferior plant isolates or carbohydrate fillers like potato and corn starches. Consequently, consumers ingest calorie-dense meals loaded with refined carbohydrates and processed lipids rather than muscle-preserving dairy proteins. Furthermore, the substantial reduction in bioavailable dietary calcium compromises musculoskeletal health over time. Growing pediatric populations and elderly individuals face the greatest nutritional risks from this invisible protein dilution. When families pay premium prices for restaurant meals, they rightfully expect wholesome nourishment rather than empty starch-fat conglomerates. Therefore, clinical nutritionists must actively educate patients regarding the deceptive compositional differences between genuine milk curds and industrial substitutes. Accurate dietary history taking must now account for hidden imitation foods consumed during social dining. Clinicians should specifically counsel vulnerable populations to prioritize verified dairy sources to avert chronic nutritional deficits.
From a cardiometabolic perspective, the widespread ingestion of unlabelled dairy analogues creates substantial health hazards. Traditional dairy fat contains complex saturated fatty acids, short-chain lipids, and natural odd-chain fats that exhibit neutral cardiovascular effects. In contrast, dairy analogues frequently rely on hydrogenated palm olein or partially hydrogenated vegetable oils to achieve functional rigidity. Consequently, these synthetic lipid blends deliver high concentrations of atherogenic saturated fatty acids and potentially harmful industrial trans fatty acids. Regular consumption of these industrial oils elevates low-density lipoprotein cholesterol, impairs arterial flow-mediated dilation, and drives chronic systemic inflammation. Furthermore, endocrinologists observe that hidden starches in analogue paneer significantly spike the glycemic index of meals. This unannounced carbohydrate load complicates glycemic control for patients managing type 2 diabetes or metabolic syndrome. Cardiologists treating dyslipidemia frequently discover that patients unknowingly ingest substantial quantities of cheap vegetable fat during routine social eating. Therefore, medical professionals must recognize that unlabelled food substitutions undermine standard clinical dietary recommendations. Clinicians should proactively counsel cardiac and diabetic patients to scrutinize food sources and patronize transparent eateries that disclose authentic ingredients. Transparent disclosure empowers patients to safeguard their vascular integrity against unverified commercial fats.
The legal challenge in Delhi follows decisive regulatory crackdowns initiated by several other Indian states. Recently, food safety administrations in Maharashtra, Gujarat, Chhattisgarh, and Punjab launched widespread enforcement drives against unstandardized analogue paneer. These regional authorities cracked down on unauthorized distribution, confiscated synthetic batches, and initiated strict penal proceedings against deceptive distributors. The public interest litigation now demands that Delhi authorities establish equivalent enforcement protocols across the national capital region. Crucially, the petitioners advocate for mandatory menu disclosures across all dining establishments, cloud kitchens, and e-commerce platforms. If commercial caterers choose to serve dairy analogues, they must explicitly inform patrons prior to order confirmation. Informed consumers retain the fundamental legal right to choose affordable, plant-based alternatives voluntarily. However, supplying an unsuspecting diner with hydrogenated oil instead of standardized milk constitutes an egregious breach of trust. As the Delhi High Court deliberates on this crucial petition, regulatory agencies must formalize robust testing mechanisms. Only stringent food testing, severe punitive fines, and transparent labelling mandates can restore consumer confidence in everyday culinary staples. Ultimately, robust regulatory oversight protects public health while preserving the integrity of traditional Indian dairy heritage.
Q1: What is dairy analogue paneer, and how does it differ from traditional paneer?
Traditional paneer is a standardized dairy item coagulated strictly from milk solids using heat and food-grade acidulants. Conversely, dairy analogue paneer is an imitation food product where manufacturers substitute milk fat and natural milk protein with hydrogenated vegetable oils, starches, and plant-based emulsifiers. Consequently, while the analogue mimics the texture and look of cottage cheese, it lacks the complete amino acid profile, bioactive calcium, and natural vitamins characteristic of authentic dairy.
Q2: Why did the Delhi High Court issue notices to the FSSAI and the Centre?
The Delhi High Court issued notices following a public interest litigation that highlighted rampant misbranding in eateries and commercial markets. Specifically, the petitioners contended that restaurants and vendors routinely serve non-dairy substitutes disguised as genuine paneer without disclosing their true ingredients. Because consumers cannot readily distinguish between genuine dairy and vegetable-oil formulations during dining, the court asked authorities to present their official enforcement statistics and explain preventative measures.
Q3: What specific health risks arise from substituting dairy milk fat with vegetable oils?
Substituting dairy fat with refined or hydrogenated vegetable oils introduces significant metabolic hazards. For instance, these processed vegetable fats often contain elevated levels of saturated fatty acids and industrial trans fats. Regular consumption promotes atherogenic dyslipidemia, drives systemic low-grade inflammation, and accelerates vascular endothelial dysfunction. Furthermore, the substitution dilutes vital micronutrients like bioavailable calcium, posing insidious nutritional risks for vegetarians, growing children, and individuals managing preexisting cardiometabolic conditions.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The Delhi High Court has directed the FSSAI and Centre to address petitions regarding dairy analogue products sold as genuine paneer. Learn about the statutory standards, nutritional differences, cardiometabolic health risks, and required consumer disclosure mandates in eateries across India.
Today

The government of Maharashtra is establishing a novel state-level Living Lab to elevate clinical outcomes, bridge public-private service gaps, and test real-world health interventions. By integrating digital innovations and frontline feedback, the platform fosters sustainable, equitable care models across communities.
Today

Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
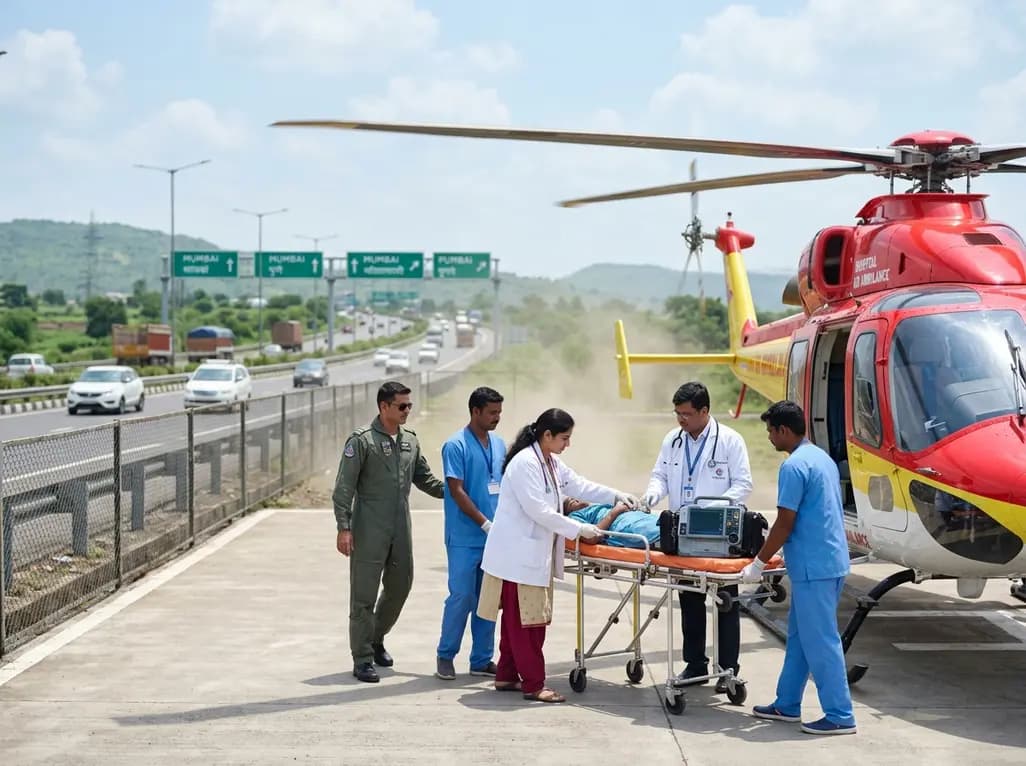
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
